What actually helps when your legs won't stop locking up
Spasticity after a spinal cord injury is not a mystery, but it is stubborn. The standard advice always seems to boil down to "stretch more," which is technically correct and completely unhelpful if you have never been shown the mechanics of why certain stretches make it worse. I learned this the hard way about three years into my own recovery, when I started hammering through a generic hamstring routine at 7 PM on a day I had already been sitting in a wheelchair for eleven hours. My popliteal region seized so hard I could not flex the knee past thirty degrees for the next two days. The routine was fine on paper. The timing was wrong. The core problem with spasticity exercises is that most people treat them like generic flexibility work. They are not. Spasticity is a velocity-dependent resistance. That means the speed at which you move a joint determines how much the muscle fights back. Move slowly and you get some stretch. Move quickly and you trigger the stretch reflex, which only makes things tighter. This is why pacing matters more than intensity, and it is the single most common mistake I see people make in rehab settings.
Exercises For Spasticity In Spinal Cord Injury
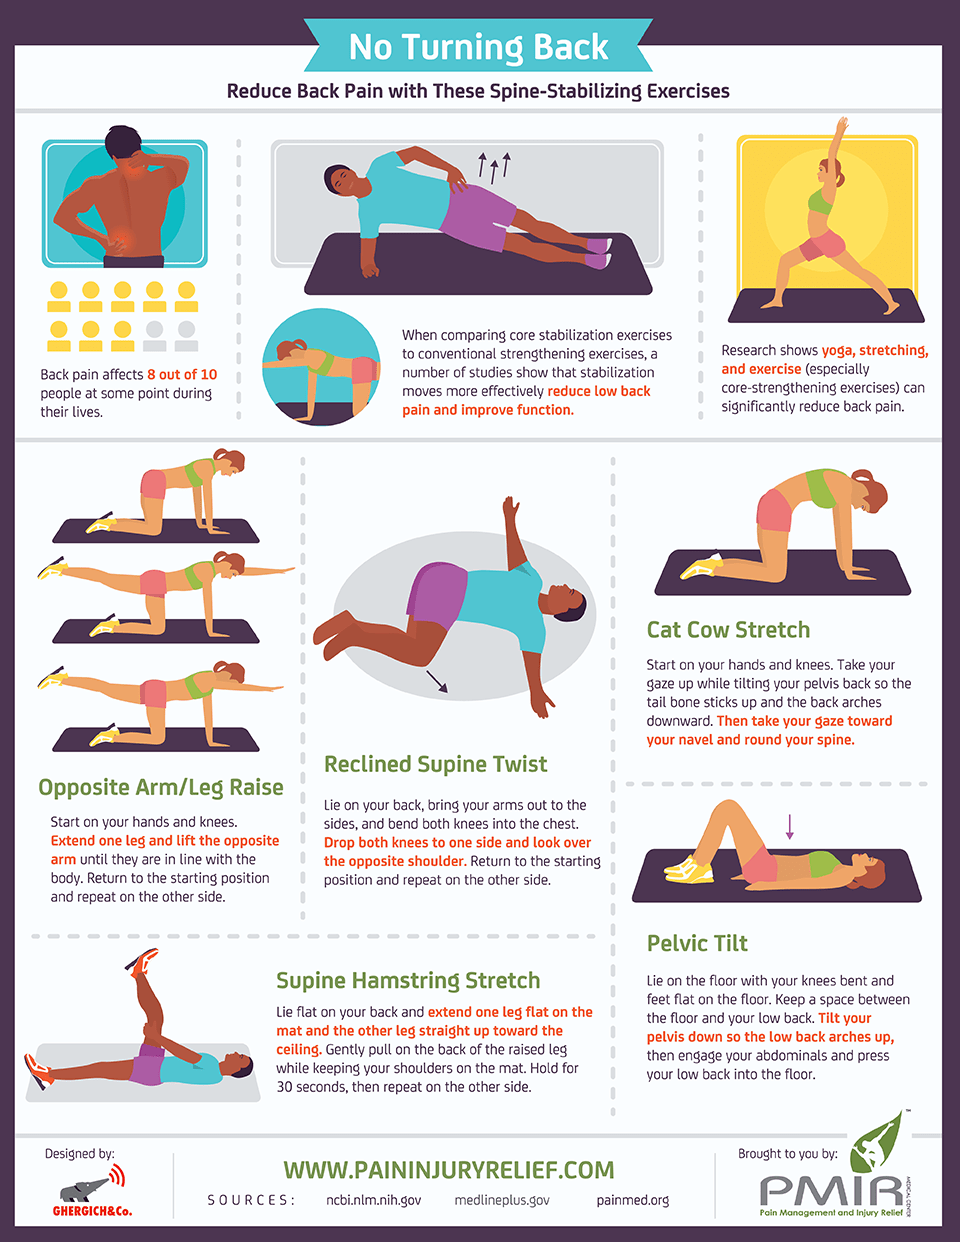
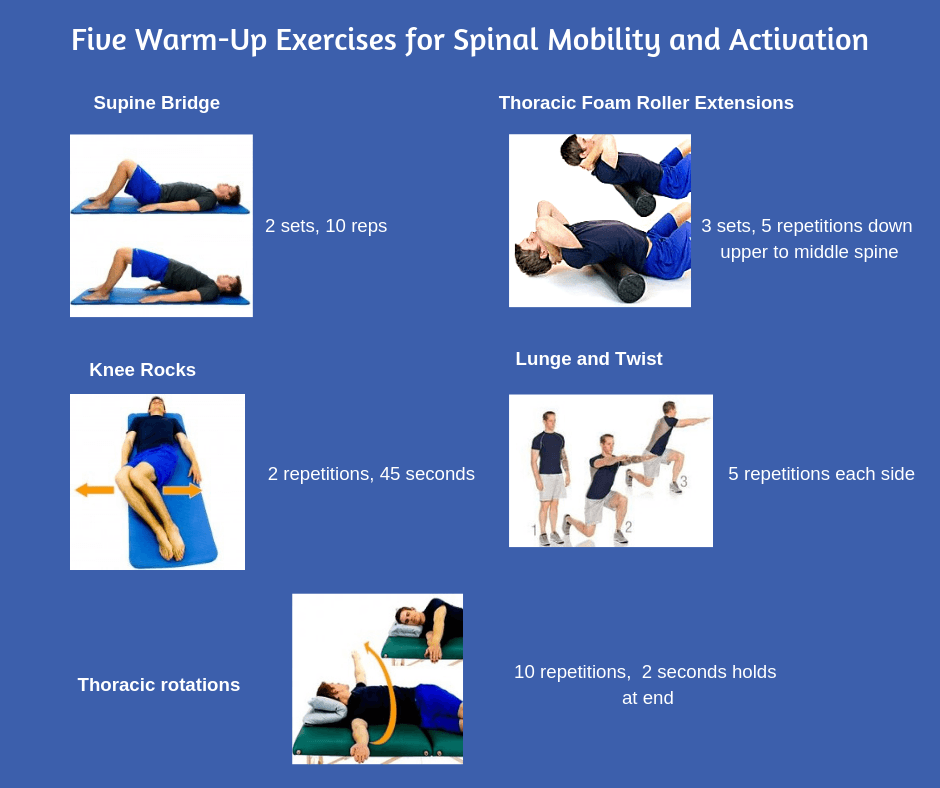
Below is a breakdown of the movements I actually use and recommend, along with the specific conditions where they work and where they completely fall apart. Hamstring lengthening with the knee extended and the ankle dorsiflexed is the foundational move for lower-extremity spasticity. The trick is doing it at a rate of roughly two seconds per degree of movement. Hold for twenty to thirty seconds at the point of tension, not pain. Pain means you are stretching into a protective clench. If the leg starts jumping during the hold, stop immediately and reset. I keep a stopwatch on my phone for this now. Guessing the duration never works because spastic muscles feel like they hold for ten seconds when it has actually been forty-five. Calf and ankle dorsiflexion stretches come next. Place the foot flat against a wall or a block and lean forward until you feel the stretch travel up the posterior chain. Again, slow. If you catch yourself bouncing, you are feeding the spasticity loop. The bounce reflex is real and it is automatic. You cannot reason your way out of it. You have to consciously slow down until the reflex stops firing.
Adductor stretching is often neglected but it is probably the most functionally important movement for anyone with hip internal rotation spasticity. Sitting on the edge of a bed with knees together and leaning toward one side gives a decent medial thigh stretch. The problem here is that adductor spasticity often presents as a constant squeezing sensation rather than a sharp pull. That makes it harder to gauge when you have reached the end range. I usually tell people to use the other leg as a reference point. If the stretched leg is crossing significantly farther than the other side ever did before the injury, you are probably in the right zone. Quad sets and gluteal holds are the isometric counterpart to all of this. They do not produce stretch but they help recalibrate the nervous system's baseline tone. A simple quad set is just pressing the back of the knee into a rolled towel and holding for five seconds, releasing, and repeating ten times. It sounds trivial. It is not. This is where the central drive gets a different signal, and over time that matters more than any single stretch session.
Get the Full Details
What does not work and why people keep doing it anyway
Ballistic stretching. This is the most dangerous habit I see because it feels like it is working in the moment. You bounce into the end range, you feel a release, you think you got a good stretch. What actually happened is you triggered the myotatic reflex and your nervous system responded by tightening the muscle even more as a protective measure. The temporary relief is followed by a rebound effect that usually lasts several hours. Avoid this completely. Vibration therapy on the belly of a spastic muscle. There is some evidence this can help in very specific cases, but the evidence is mixed and the risk of making things worse is real. I had one person try vibrating the quadriceps for three minutes before a stretching session and the spasticity increased by an observable amount. Their knee would not extend afterward. We switched to vibration on the antagonist muscle group instead, which is a completely different approach and worked better for them. Context matters a lot with this one. Rapid passive range of motion performed by a caregiver who is rushing. I have watched physical therapy aides try to "get through" a ROM session in eight minutes because of schedule pressure. This is counterproductive. A proper slow passive stretch through the full available range takes twelve to fifteen minutes per limb. Doing it faster than that is essentially pointless and sometimes harmful.
A specific problem and the workaround
About two years in, I hit a wall with right-sided hip flexor spasticity. Standard stretching was not touching it. The muscle would contract the moment I tried to extend the hip past neutral. I tried everything in the textbook. Nothing moved the needle. Then I noticed that if I bent the knee fully before attempting hip extension, the spasticity dropped off significantly. The rectus femoris crosses both the hip and the knee. Bending the knee puts that part of the muscle on slack and removes one source of the reflex tension. From there, gentle hip extension with the knee bent allowed me to stretch the iliopsoas portion without triggering the same level of resistance. This was the moment I stopped trying to stretch spastic muscles in isolation and started thinking about them as functional units that respond differently depending on joint position. It is a small shift but it changed everything for me. Now I test multiple positions before committing to a routine. If a stretch hurts or triggers spasm in one position, I try two or three alternatives until I find the one that produces tension without the reflex response. Usually there is one.
Timing and frequency
Do the work when your tone is lowest. For most people that is within the first hour of waking up, before the accumulated fatigue and gravity have built up spasticity throughout the day. If you stretch after a warm shower or bath, the heat lowers muscle tone enough to make the sessions more effective. I typically spend about twenty minutes on lower extremities and ten on upper extremities, four to five days a week. Some days I skip entirely because the spasticity is already too high and forcing it makes things worse. That is normal. Skipping a day is better than doing a bad session. Medication timing is also worth considering if you are on baclofen or tizanidine. Taking the medication about thirty minutes before your exercise window can give you a wider range of motion, but it also means you need to be careful about drowsiness and coordination. I learned that one the hard way when I tried a full stretching routine while peaking on a new baclofen dose and nearly fell out of my chair from the combination of relaxation and dizziness. Start low, go slow, and do not stack new variables at the same time.

When exercises stop being enough
Severe contractures that have been present for more than a year or two will not respond to stretching alone. The connective tissue has remodeled and the muscle fibers have shortened permanently. At that point you need surgical consultation or serial casting, not more hamstring stretches. Botulinum toxin injections can help in targeted areas and they make the surrounding exercises more effective for a window of about three to four months. This is not a permanent solution but it is a useful bridge. There is no exercise that addresses spasticity caused by an underlying issue like a urinary tract infection, an ingrown toenail, or pressure sores. I once spent six weeks trying to stretch away what turned out to be spasticity driven by an untreated UTI. The exercises did nothing because the driver was never addressed. If your spasticity suddenly worsens without an obvious trigger, check for these first before changing your routine.
A note on tracking progress
Keep a simple log. Date, time of day, which stretches you did, and a one to five scale of how tight the area felt before and after. You do not need anything complicated. After about six weeks you will start seeing patterns. You might discover that your spasticity is worse on days you sleep poorly, or that certain stretches feel great one week and trigger spasms the next. This data is more valuable than any generic protocol you will find online because your nervous system is not generic. The work is repetitive and it is boring and it rarely produces dramatic results in a short timeframe. But it is the thing that keeps function intact and prevents the kind of fixed contractures that end up requiring surgery. Show up consistently, move slowly, and pay attention to what your body is actually telling you rather than what the textbook says should happen.