
Why Your Tennis Elbow Won't Go Away After Three Months
You've probably already tried wrapping it, icing it after workouts, maybe even getting a cortisone shot. The shot takes the pain away for six weeks, then it comes back worse. Here's what actually moves the needle: load management through specific Exercises To Cure Tennis Elbow, done consistently over months, not days. I'm going to walk through what works, what looks right but isn't, and where most people derail themselves. Let's start with the exercise because that's the core of it. The most evidence-backed movement for lateral epicondylitis is the eccentric wrist extension, often called the Tyler Twist when done with a FlexBar. You hold the bar vertically, healthy side gripping the top, affected side at the bottom. You use the good arm to lift the bar into extension, then the affected arm slowly lowers it back down over about five seconds. That slow lowering is the only part that matters. The lifting is just setup.
Exercises To Cure Tennis Elbow: What the Research Actually Says
The classic study by Leroux and friends compared eccentric training, stretching, and a control group. The eccentric group had the best outcomes at one year. More recent meta-analyses have been mixed because a lot of the early studies were small and poorly controlled, but the signal still points toward progressive eccentric loading as the single most effective intervention. Not rest. Not massage. Eccentric loading. Here's the part nobody tells you: the exercise should hurt while you're doing it. If you're not feeling some discomfort at the lateral epicondyle during the slow lowering phase, you're probably going too light or moving too fast. I want you at a 4 out of 10 on the pain scale during the set. Not 2, not 6. Four. You walk away from it sore but functional. If you're limping around your apartment like you've been shot, you went too hard. I did this wrong for weeks when I first tried it. I was using a Theraband resistance loop and basically just doing regular wrist curls with a slight pause at the bottom. The band didn't give me enough isolated tension on the extensors and I was recruiting my biceps instead. Swapped to a rigid bar — a wooden dowel with a towel loop at one end — and the difference was immediate. The lever arm forced the forearm extensors to do the work without any compensation. Took me about twenty minutes to rig it up.
The protocol is straightforward but not easy to stick with. Three sets of ten repetitions, once daily. That's it. Not three times a day. Once. The tendon needs the stimulus and then it needs the recovery window. Doing it twice daily just resets the inflammation clock every time. Progression happens when ten reps at a given resistance feels like a 3 out of 10 pain instead of a 4. Then you add a little weight. A quarter turn of a screw clamp on the bar or switching to a thicker towel loop is enough to increase the tension incrementally. Now let me tell you about the thing that trips people up. Isometric holds. In the very early painful phase, when even light gripping causes sharp pain, eccentrics are too much. At that point you do isometric wrist extensions: push your affected hand against a wall or the other hand with maximum effort you can sustain without collapse, hold for forty-five seconds, rest for sixty, repeat five times. This actually downregulates pain through the cross-edema effect and can buy you a couple weeks of reduced sensitivity while you wait for the acute inflammation to settle. Then you transition to eccentrics. I used this bridge approach with a client who couldn't even hold a coffee cup without wincing. After two weeks of isometrics, she could do the first set of eccentrics at zero resistance. She was skeptical the whole time. It still worked. Stretching gets a lot of love and it does help with symptom management. The classic prayer stretch — hands pressed together, affected arm extended straight in front, gently pulled back with the other hand — increases extensor flexibility and reduces the resting tension on the tendon insertion. Do it for thirty seconds, three times. But stretching alone won't cure it. I've seen people stretch for months and stay exactly where they started because the tendon is still being overloaded during their day-to-day activities. Stretching is maintenance, not treatment.
Get the Full Details
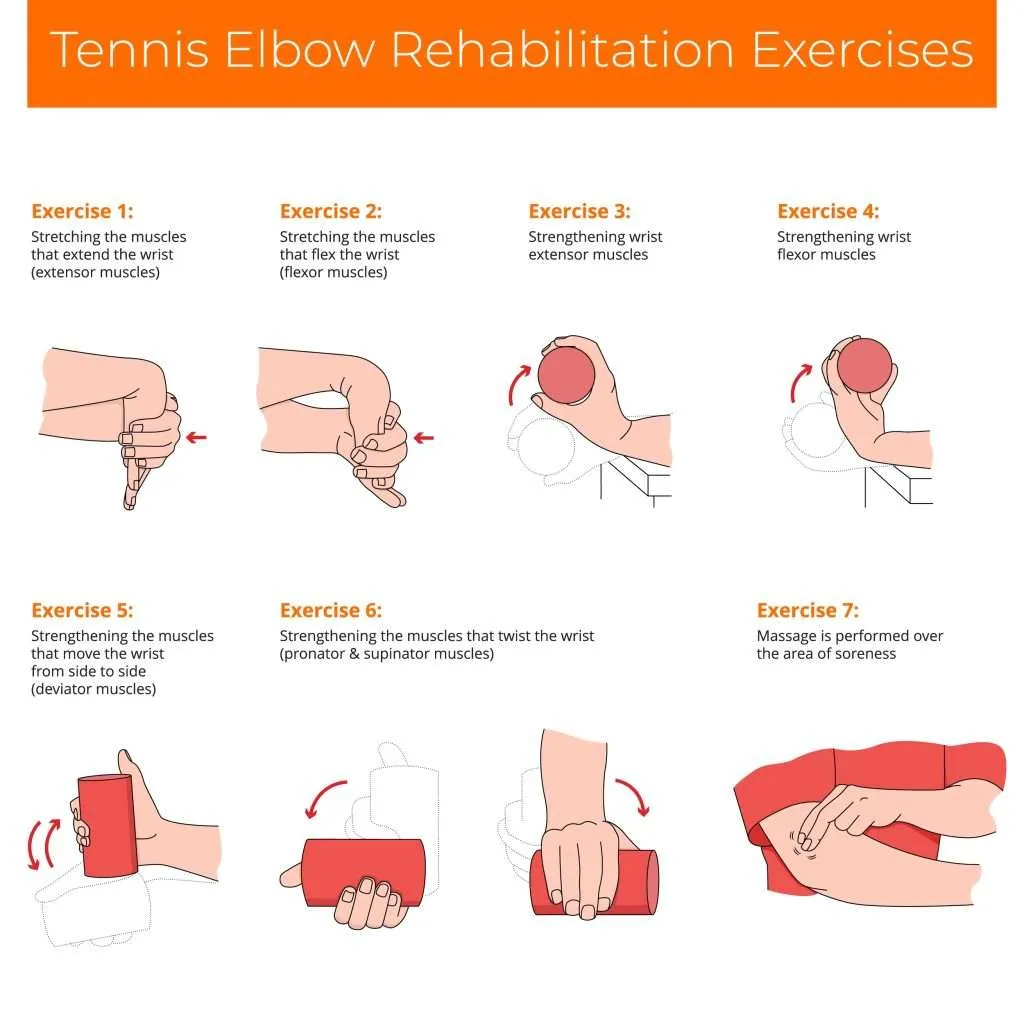
There's a common mistake with grip strength. People assume grip weakness is the problem and start squeezing stress balls and hand grippers all day. The issue with tennis elbow isn't grip flexor weakness — it's extensor tendon degeneration. Overworking the grip flexors can actually pull the radius and ulna into positions that increase compression at the lateral epicondyle. If you're doing grip work, pair it with equal or greater extensor work and keep the volume modest. Two sets of fifteen with a light putty or soft ball, once daily, is plenty. Let me address the timeline because this is where everyone quits. Tennis elbow is a tendinopathy, which means the collagen structure in the tendon is disorganized and the load capacity is reduced. Remodeling collagen takes time. Twelve weeks is a realistic minimum for meaningful improvement. Six months is more typical for full resolution. People who expect it to be gone in three weeks are the ones who end up back here asking why it keeps coming back. The pain you feel at week three is not a sign the exercise is wrong. It's a sign you're in the messy middle of healing. Push through it at the right intensity and it gets better. Stop because it hurts and it never does. There is a scenario where these exercises won't help and you need to stop and see a doctor. If you have numbness or tingling going past the elbow into the ring and little fingers, if you have weakness in finger abduction, if you've lost sensation in parts of your hand — that's not tennis elbow, that's likely ulnar nerve entrapment at the elbow or a cervical radiculopathy from C8-T1. I ran into this with a guy who'd been doing eccentrics for four months with zero progress. He kept saying the exercise felt like it was targeting the wrong spot. Turns out his pain was referring from a pinched nerve in his neck. MRI confirmed it. Surgery fixed it. The exercises weren't the problem, the diagnosis was.
Another red flag: pain that wakes you up at night consistently. Tendinopathy aches during the day and after activity. It doesn't typically cause pain. Night pain suggests a different pathology — bursitis, a stress reaction in the distal humerus, something inflammatory. Get it checked. For the modality stuff, if you want something adjunctive, contrast therapy — alternating three minutes of heat with one minute of cold, four cycles — can help with pain management around the workout window. Ice after is fine if it makes you more comfortable. There's no evidence it speeds healing. Shockwave therapy has moderate evidence behind it for chronic cases over twelve weeks. It's expensive and not covered by most insurance, but if you're past the six-month mark and still stuck, it's worth a conversation with a sports med physician. The one thing I wish more people understood is that you need to modify your actual activities, not just do the exercise. If you're doing heavy gripping at work all day — plumbing, carpentry, even prolonged computer mouse use with a tight grip — the exercise is fighting an uphill battle. You can't out-exercise a bad ergonomic habit. Find ways to reduce the loading: switch to a vertical mouse, use tools with larger handles, take micro-breaks every twenty minutes to open the hand and shake it out. These adjustments matter more than most people realize.
Here's the practical routine I'd suggest starting with, assuming your diagnosis is solid lateral epicondylitis and you're past the ultra-acute phase where even touching the area hurts: Morning: isometric wrist extension hold against a wall, fourty-five seconds, five rounds. Two minutes rest between rounds. Don't max out — aim for about seventy percent of your max effort. You should feel it in the forearm, not the shoulder. Evening: eccentric wrist extensions with a Tyler Twist bar or dowel setup. Three sets of ten, five-second lowering phase. Rest ninety seconds between sets. Pain should be around four out of ten. If it's higher, lighten the resistance. If it's lower, you need more resistance or a slower tempo.

Once daily: prayer stretch, thirty seconds, three rounds. Light grip work with putty, two sets of fifteen, optional but helpful if your job requires heavy gripping. Reassess every two weeks. If pain during the exercise hasn't decreased at all after four weeks, something is off — either the diagnosis, the technique, or there's a secondary issue. If pain has decreased but function hasn't improved, you're probably progressing the load too slowly. Tendon adaptation follows a dose-response curve and you need enough stimulus to trigger remodeling. Most people I've worked with who actually stuck with this for twelve to sixteen weeks saw significant improvement. The ones who didn't were the ones who stopped when it got inconvenient or painful in the wrong way. Pain that's dull and ache-y during the exercise is normal. Sharp, stabbing, localized pain at the insertion site that makes you stop mid-rep is not. Learn the difference.



