Experiential Techniques In Therapy
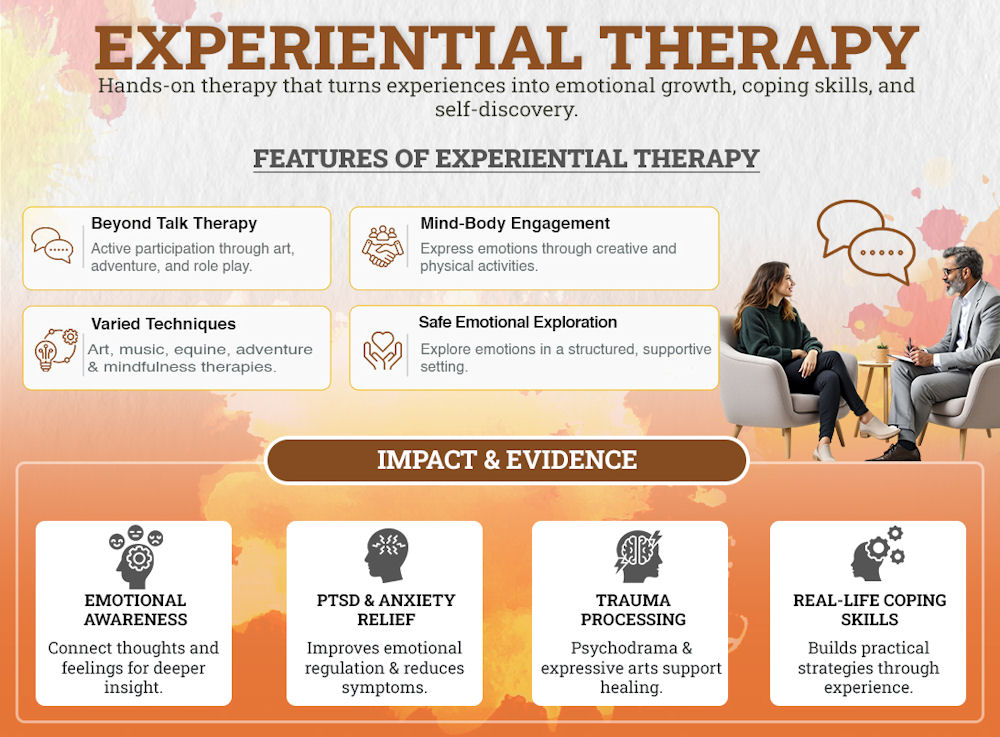
Most therapists spend their first few years stuck in talk therapy, asking clients to describe their feelings instead of helping them actually feel anything. I made that mistake early on. It took me about two years to realize that asking someone to put words to a panic attack doesn't change the panic. The nervous system doesn't care about your vocabulary. Experiential Techniques In Therapy bypass the verbal loop and work directly with emotion, body sensation, and action. They're not a single method. They're a collection of approaches that include empty chair work, guided imagery, role-playing, psychodrama elements, body-focused interventions, and expressive arts. The common thread is simple: you create a situation where the client experiences something in the room rather than talking about it.
How Experiential Techniques In Therapy Actually Work
The mechanism is straightforward but easy to mess up. You take an unresolved emotional conflict and externalize it. Instead of sitting across from you describing their relationship with their father, the client sits in an empty chair and talks to the father. The conflict that was abstract and internal becomes something happening right now, in the room, with spatial presence. That shift alone changes the neurological processing. I used to run empty chair work like a script. First you do this, then you switch chairs, then you summarize. That approach is sterile and usually ineffective. What actually works is slower and messier. You let the client stay in the emotion longer than feels comfortable. The real work happens in the third or fourth minute when they've moved past the intellectualized version of their feeling and hit the raw thing underneath. That's where you intervene. Not before. Here's a specific problem I ran into. A client came in with severe social anxiety rooted in childhood humiliation. Standard approach would be to explore the memory cognitively. I tried guided imagery, asking them to visualize the original event and then imagine a compassionate figure entering the scene. It didn't work. Not even a little. The client could describe the visualization perfectly but remained completely disconnected. They were so cognitively sophisticated that imagery just became another intellectual exercise. They were watching a movie of their trauma, not re-experiencing it.
The workaround was to strip the imagery entirely and go direct and physical. We used a simple grounding technique where they pressed their feet flat against the floor and described exactly what muscles were engaged. Then we had them speak the humiliating memory out loud in first person present tense, with their body positioned as it was during the original event. That physical anchoring bypassed the visualization habit. The affect actually shifted that session. Took three more sessions to get the real work done, but the first breakthrough came from abandoning the textbook method. Role-playing is another common tool and another place where beginners make the same mistake. You might ask a client to rehearse a difficult conversation with their boss. Sounds useful. The problem is that most people already know how to have that conversation in their head. They've rehearsed it a hundred times. The role-play only helps if you introduce unexpected elements mid-scene that disrupt their prepared script. You play the boss and push back in a way they didn't anticipate. That's when the real anxiety surfaces and you can work with it. Body-focused experiential work deserves more attention than it gets. Techniques like tracking bodily sensations, somatic experiencing elements, and tension release through movement can be more effective than any verbal intervention for trauma-related cases. The limitation is that you need training. Not a weekend workshop. Actual supervised hours. Attempting to guide someone through trauma material without understanding the nervous system's capacity for discharge can leave a client dysregulated for days. I've seen it happen. Once had a client who stayed in hypervigilance for a week after a guided imagery session I wasn't qualified to run. I didn't touch that again until I got proper supervision.
Get the Full Details

Guided imagery itself has a practical constraint. Not everyone can access it. Some people have aphantasia — the inability to form mental images. About two to five percent of the population falls into this range. You won't know upfront. The first time I tried a standard imagery intervention with a client who couldn't visualize, I spent twenty minutes watching them struggle to see what wasn't there. We pivoted to focusing on bodily sensations related to the scene instead. Slower, but it worked. Always have a somatic fallback ready. Expressive arts techniques like drawing, clay work, or free movement sound appealing because they feel creative and non-threatening. They work well with clients who resist talking but struggle with those methods too. A client who can't sit still long enough to hold a conversation might find three minutes of aggressive clay work more honest than any hour of CBT restructuring. The data on this is thin but the clinical observation is consistent across practices. One counter-intuitive point about pacing. Beginners in experiential therapy tend to move too slow, not too fast. They're afraid of triggering something and pull back at the wrong moments. The actual bottleneck is usually the therapist's discomfort with silence and stillness, not the client's capacity. The client will tell you when they're ready to go deeper. You'll know because the emotion shifts from descriptive to present-tense and the body starts moving without instruction. That's the window. Close it quickly.
The biggest failure mode for these techniques is using them with clients who lack basic emotional awareness. If someone has never identified a single feeling in their life beyond "good" and "bad," throwing them into an empty chair exercise will produce confusion and frustration, not insight. You need to build the emotional vocabulary first through simpler affect identification work. It usually takes four to six sessions minimum before experiential work lands effectively. Another area where these approaches hit walls is severe personality pathology. Clients with significant borderline or narcissistic features may use experiential exercises as performance rather than genuine experience. The chair work becomes theatrical. The imagery stays surface level. The emotions perform without depth. In those cases, a more structured and longer-term approach tends to produce better outcomes. Experiential techniques can be part of the treatment but they won't carry it alone. For complex PTSD specifically, I've found that phase-based treatment is non-negotiable. Experiential work before a client has adequate stabilization and coping skills can actually worsen symptoms. I follow a standard sequence: stabilization first, processing second, integration third. Skipping ahead because a technique feels exciting is a career-limiting move.
The training landscape for experiential techniques is fragmented. You'll find courses in Gestalt therapy, Focusing-oriented therapy, EMDR protocols, sandplay, and several others that claim experiential foundations. Each has different assumptions about how change happens. Pick one framework and commit to it for at least a year before jumping between approaches. The inconsistency is worse than the gap in knowledge. Most competent practitioners are solid in one model and mediocre everywhere else.

Practical Steps to Start Using These Techniques
Begin with assessment. Determine whether the client has the emotional capacity, cognitive flexibility, and stabilization level needed for experiential work. Ask about past experiences with emotion-focused interventions. If they've had positive results with meditation, journaling, or even intense storytelling, they're likely a good candidate. If they describe all emotional work as useless or superficial, proceed with caution. Start small. A two-minute guided breathing exercise with attention to body sensation is experiential therapy. You don't need to jump straight to role-playing family dynamics. Build the skill gradually. Your own comfort with the techniques matters as much as the client's readiness. If you're nervous, they'll sense it and shut down. I spent months doing simplified versions of empty chair work alone in my office before I ever tried it with a client. You need to know where your own discomfort lives before you can tolerate sitting with someone else's. Documentation after an experiential session is different from standard notes. Instead of just recording what was discussed, note the specific techniques used, the client's affective shifts during the session, any moments of resistance or breakthrough, and what you would adjust next time. This creates a practical record that helps you track progress across sessions rather than relying on vague impressions.
The techniques themselves should be adapted to each client, not the other way around. A standard empty chair protocol takes about forty-five minutes in a textbook. In practice, I usually complete a meaningful cycle in twenty to thirty minutes. Running longer produces diminishing returns and sometimes emotional fatigue that makes the final integration less effective. Watch the clock but let the work dictate the pace. If you're looking for structured materials, the Gestalt Institute of Cleveland and the Perls Institute publish training manuals that cover empty chair work, exaggeration techniques, and dream work in detail. The International Society for Gestalt Practice has a directory of certified trainers. For somatic approaches, the Sensorimotor Psychotherapy Institute offers both online and in-person training with supervised practicum. Don't skip the supervised component. Reading about these techniques and doing them under supervision are two different skills. The core principle is simpler than most training suggests. Experience before understanding. Let the client feel something real in the session and the understanding tends to follow. You can't reason someone out of an emotion they haven't fully felt. That's the entire premise and it's also why these techniques remain controversial in circles that prioritize cognitive restructuring above all else. They work differently. Not better or worse, just differently. And sometimes differently is exactly what's needed.