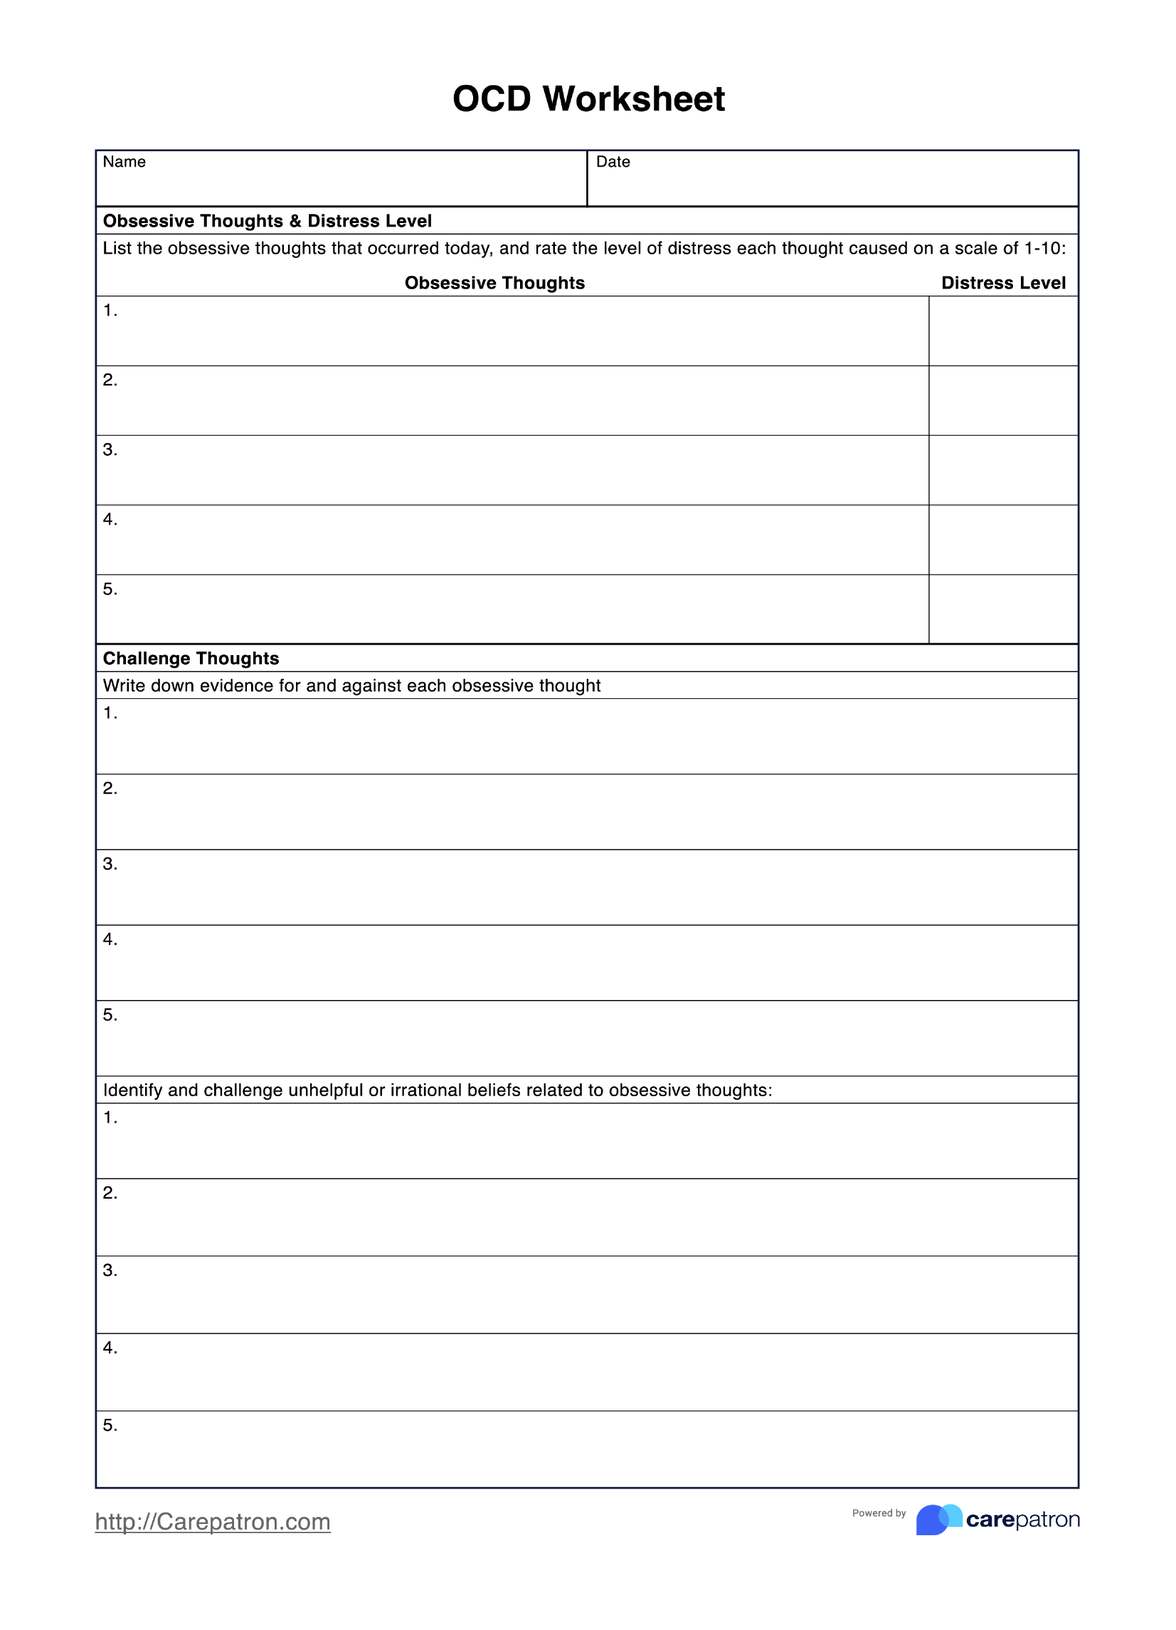
Working With Exposure Therapy For Ocd Worksheets In Practice
Most people who try to use ERP worksheets on their own hit the same wall within two weeks. The structure exists on paper but something about actually doing the exposures makes the worksheet fall apart. I ran into this repeatedly when I was helping people work through contamination OCD, specifically the variant where someone would rate a situation as a 7 out of 10 anxiety and then manage to talk themselves out of holding the exposure for more than four minutes because they convinced themselves the ritual just needed to be "slightly modified" rather than fully blocked. The core mechanism is straightforward. You create a fear hierarchy, pick a stimulus, sit with the anxiety without performing the compulsion, and let the anxiety decrease on its own over time. The worksheet is just a tracking tool. What most people miss is that the worksheet needs to capture the right data at the right intervals, and getting that record clean enough to actually learn from is harder than it sounds.
How To Set Up Exposure Therapy For Ocd Worksheets That Actually Work
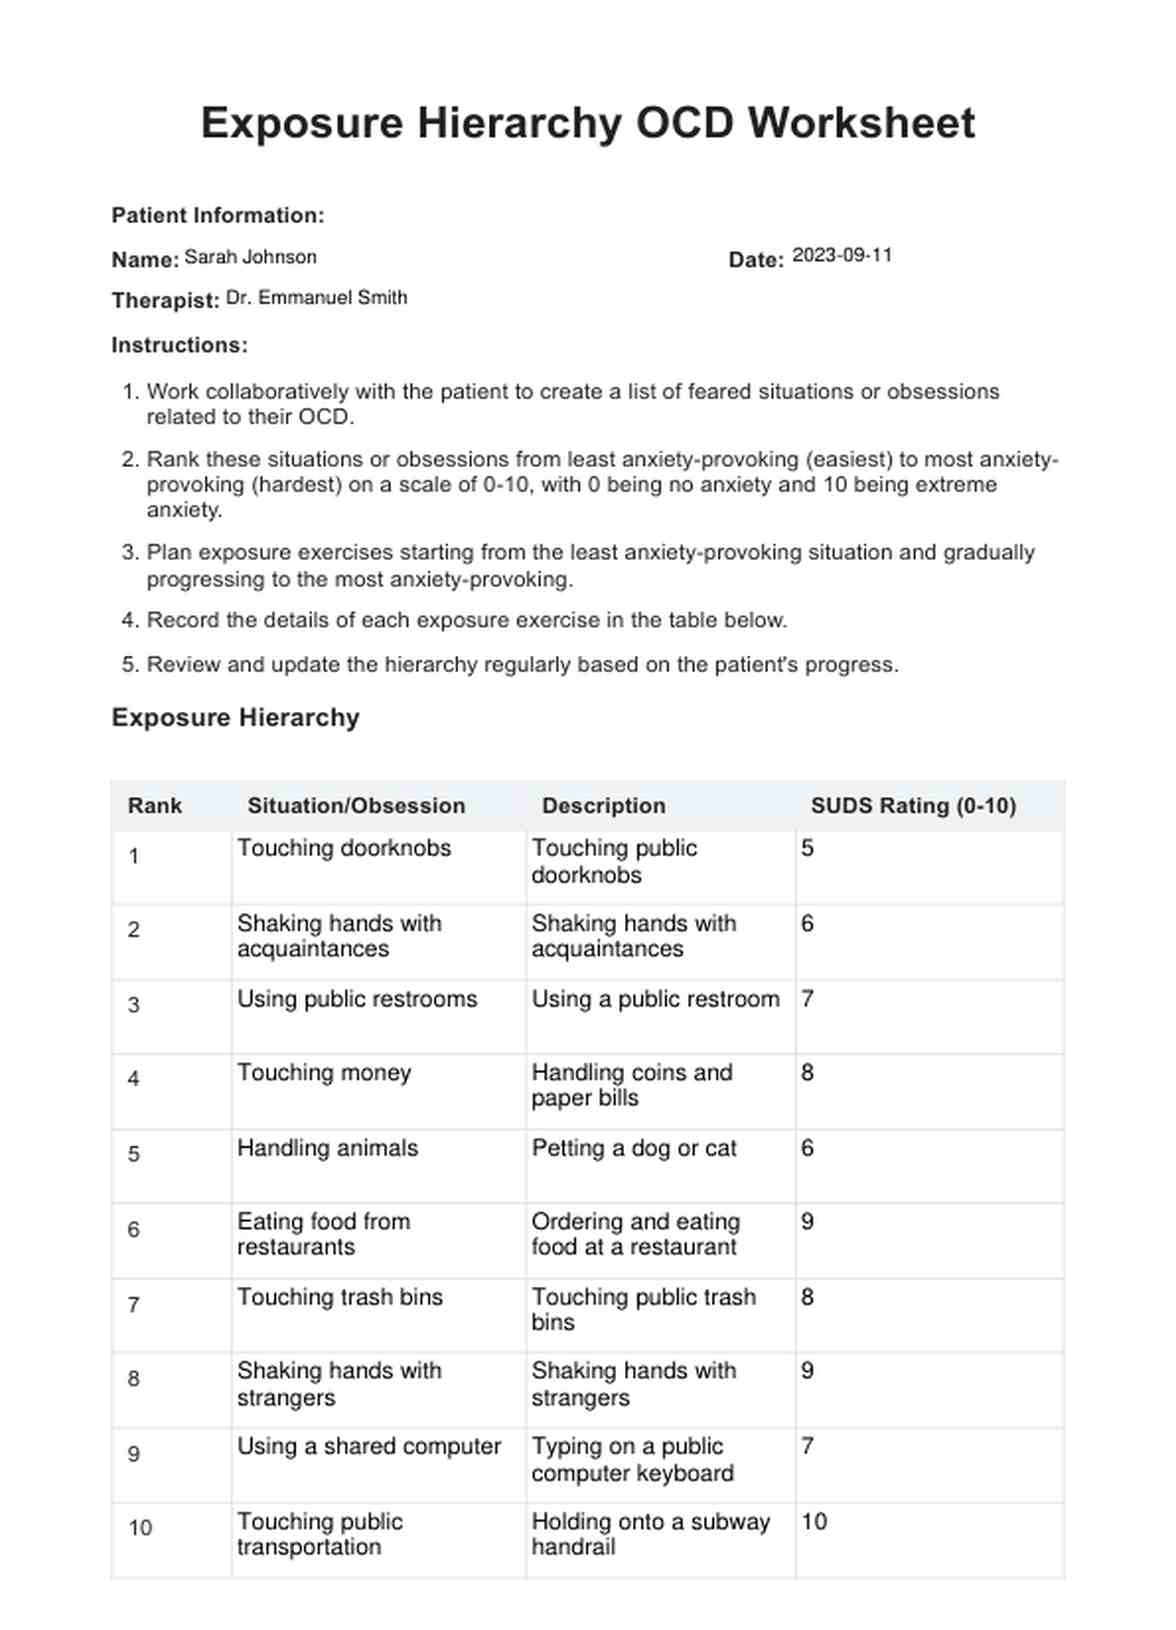
I use a structured template that has five columns at minimum. Column one is the exposure item with the exact stimulus described. Not "dirty doorknob" but "public restroom door handle in a high-traffic grocery store, touching it with bare fingers for ten seconds, then sitting with the anxiety for twenty minutes before washing." The specificity matters because vagueness lets people cheat themselves into doing an easier version than they signed up for. Column two is the Subjective Units of Distress Scale rating before the exposure starts. This is usually an integer from zero to ten. Column three is the peak anxiety during the exposure. Column four is the anxiety level after response prevention has held for the full duration. Column five is a notes field for what went wrong, what safety behaviors crept in, whether the anxiety spiked faster or slower than expected. Here is the part nobody tells you about the worksheet format. The column order should put the post-exposure rating next to the pre-exposure rating so you can visually see the gap. If you stack them on opposite ends of the page, your brain skips over the actual delta. I rearranged my sheets so the before and after numbers sat side by side. It made the habituation data obvious in a way that changed how aggressively people would design their next exposure.
Another structural choice that matters: the worksheet should have a box where you write the feared outcome before the exposure, and another box where you write what actually happened afterward. The mismatch between prediction and outcome is where the cognitive shift happens. People who skip this section tend to repeat the same exposure over and over without the belief update that makes the next one easier. When I was working with someone who had symmetry OCD and needed to arrange objects unevenly, they kept filling out the worksheet correctly on paper but the actual exposures kept getting ruined by mental checking. They would arrange the objects, feel the anxiety spike, and then spend the entire prevention period mentally rehearsing that the arrangement was acceptable. The worksheet had no field for mental compulsions because traditional templates are built around overt rituals. I added a checkbox for "mental ritual performed" with a separate column recording its duration. That single addition cut the average exposure time down from forty-five minutes to roughly twelve minutes over eight sessions because once they saw the mental rituals tracked in black and white, the behaviors lost some of their automatic quality. There is a downside to worksheet-based ERP that deserves to be stated plainly. Worksheets create a false sense of progress when the data is sloppy. People will rate their anxiety a six before and a four after, which looks like partial habituation, but if they spent the entire exposure subtly fidgeting or counting or avoiding eye contact with the feared object, the four is meaningless. The reduction came from undetected micro-rituals, not from learning that the anxiety can resolve on its own. A proper worksheet needs a row at the bottom for "complications or ritual substitutions" that forces honest accounting.
Get the Full Details
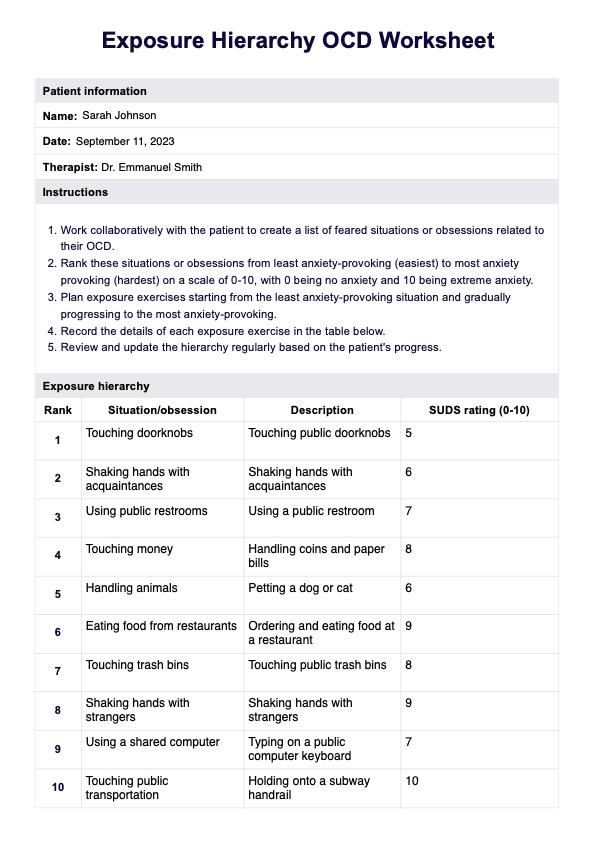
For people with primarily obsessional OCD where the compulsions are purely internal, the worksheet becomes less useful unless you adapt it heavily. The traditional form assumes there is a physical response to prevent. With mental rituals, you need to add a section where the person describes the exact thought loop, writes down a planned behavioral anchor to interrupt it, and records whether the anchor worked or whether they drifted back into the obsession within thirty seconds. This is where the worksheet stops being a generic template and has to be customized per exposure cycle. If you are building this from scratch and want a working template, the essential fields are: date and time, exposure description with exact parameters, pre-exposure SUDS, post-exposure SUDS at five minute intervals up to twenty minutes, feared outcome predicted, feared outcome observed, compulsion type (overt, mental, avoidance, reassurance-seeking), duration of any compulsion, and a one-sentence summary of what the exposure taught you. Anything beyond that is optional clutter that people skip when the form gets long. The reason most people abandon these worksheets is not that the method fails. It is that the first three exposures feel terrible and the tracker does not reflect the actual discomfort in a way that motivates continuation. The data looks flat because the anxiety drops are incremental, not dramatic. The trick is to look at the compulsion column, not the anxiety column, when deciding whether to continue. A worksheet where the SUDS barely drops but the ritual count goes from nine instances per session down to two over five sessions is a sign the treatment is working even when it feels like nothing is changing.
Where The Standard Templates Fall Short
Free PDFs you find online almost always share the same three limitations. They assume a contamination or checking subtype. They do not include space for tracking safety behaviors, which account for a significant portion of treatment-resistant cases. And they use a single peak-anxiety rating instead of interval recordings, which means you lose the information about whether anxiety spikes once and then plateaus, or whether it oscillates in a way that suggests the person is still subtly engaging with the obsession during the exposure window. A practical workaround for the safety behavior problem is to add a "did you avoid anything to make this easier?" line directly under each exposure entry. It takes ten seconds to fill out and catches things like "I wore gloves underneath the bare-hand exposure" or "I only looked at the dirty object for three seconds before looking away repeatedly." These micro-avoidances are invisible unless the worksheet forces the person to name them. Interval recordings solve themselves with a simple timer. Set a vibration on your phone every five minutes during the exposure. When it goes off, mark the current anxiety number in the appropriate column. Five data points per exposure take roughly forty seconds to log but give you a trajectory curve that is far more diagnostic than a single before-and-after pair. It tells you whether the anxiety is descending steadily, whether it rebounds after an initial drop, and whether the person is holding prevention consistently or breaking rhythm near the end.
For people who want a downloadable version that incorporates these adjustments rather than piecing together a template from scattered resources, the structure I described above can be laid out as a single-page table that fits roughly six exposures per sheet with enough margin for the notes column. One page per day is usually sufficient. Anything more creates a log so large that people stop filling it out faithfully, which defeats the purpose of having a record in the first place.
Exposure Therapy For Ocd Worksheets Common Mistakes To Avoid
The most expensive mistake is using a worksheet before the person can distinguish between anxiety and actual danger. If someone believes the contamination is genuinely going to make them violently ill, the worksheet becomes a torture log. They will sit through the exposure, rate the anxiety, and conclude the data proves the obsession is rational because the fear felt real. The worksheet needs a brief psychoeducation section at the top that explicitly frames the discomfort as a training signal, not evidence of threat. Three sentences is enough. "This discomfort is your brain practicing a new prediction. The goal is not to feel calm during the exposure. The goal is to learn that the predicted outcome does not occur regardless of how uncomfortable the feeling is." Another common error is designing exposures that are too easy. People will put a feared object at the bottom of their hierarchy and then spend weeks working there because the worksheet rewards completion with checkmarks. The checkmark reinforces the behavior more than the data reinforces the learning. Start higher on the hierarchy than feels comfortable, accept that the first few entries will be messy, and move down only after the anxiety curve flattens across at least three repeated trials at the same level. For severe cases where compulsions are deeply ingrained and time-consuming, worksheets alone will not produce durable change. The structure helps, but the underlying fear network often requires more intensive intervention than self-directed tracking can untangle. In those situations, the worksheet functions best as a supplement to therapist-guided ERP rather than a standalone protocol. It keeps the daily practice accountable between sessions, but expecting the sheet to replace the therapeutic relationship is where people get stuck for months without making measurable progress.