What Actually Happens During Exposure Therapy For Trauma
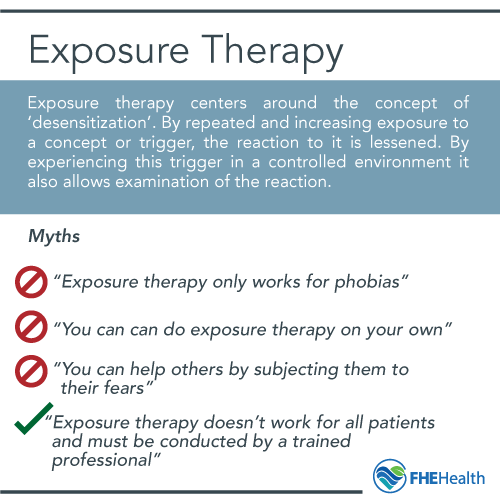
Exposure therapy for PTSD is basically a structured process where you deliberately put yourself in contact with things your brain has learned to fear. Not randomly. Not by accident. There is a protocol, a hierarchy, and a lot of sitting around waiting for your nervous system to realize nothing bad is going to happen this time. It sounds simple on paper. It is not simple when you are the one doing it. The core mechanism is habituation and inhibitory learning. Your amygdala has wired a neutral or once-neutral stimulus to a terror response through a traumatic event. Exposure therapy rewires that connection by repeatedly presenting the feared stimulus without the expected negative outcome. Over time, the fear response weakens. That is the textbook version. The real version involves a lot of discomfort, some crying, some avoidance tricks, and occasionally a breakthrough where you realize you can breathe again in a situation that used to shut you down completely. I ran a trauma clinic for several years. One of my patients, let me call him Marcus, had a combat-related PTSD with flashbacks triggered by loud metallic sounds like car backfires or dropped utensils. His initial exposure hierarchy started absurdly low because his hyperarousal was so severe he could barely tolerate a kitchen environment. We began with him sitting in a room where a metronome clicked at a slow pace while he practiced grounding techniques. Then we graduated to recordings of construction noise. By week six he was walking through a grocery store parking lot with the lights on and the doors open. It took fourteen months. Some people get better faster. Some don't get better at all with exposure alone.
Exposure Therapy For Ptsd Examples That Actually Work
Here are some concrete examples of how exposure hierarchies look in practice for different types of PTSD. Vehicle accident survivors often build hierarchies like this: sitting in a stationary car in the driveway, driving around an empty parking lot, driving on a quiet residential street, driving on a busier road, then eventually highway driving. Each step stays on the ladder until the subject's subjective units of distress, the SUDS scale, drops below a manageable threshold before moving up. The SUDS scale runs from zero to one hundred. If someone is at ninety-five on step two, they do not advance. They stay there until it drops. Sexual trauma survivors might work with a therapist on a hierarchy involving physical proximity, touch, certain environments, or situations that echo elements of the original trauma. This requires extreme care and a therapist who understands trauma-informed approaches. You do not hand this to someone and say go at it. The pacing is intentionally slow and the client controls the tempo at every single point.
Combat veterans frequently confront triggers related to crowds, loud noises, confined spaces, or certain times of day. A common hierarchy element involves going to a busy restaurant, then a movie theater, then a sporting event. Another involves practicing sleep hygiene after years of disrupted sleep patterns tied to hypervigilance. The environmental re-engagement pieces matter just as much as the direct trauma memory processing. First responder PTSD presents its own set of challenges. Firefighters, paramedics, and police officers often have accumulated traumatic exposures over years, not a single event. Their hierarchies might involve revisiting stations, handling equipment from past calls, or discussing specific incidents in detail. The cumulative nature of their trauma sometimes means standard exposure protocols need modification rather than direct application. The in vivo approach, which is exposure to real-world triggers, is only one type. There is also imaginal exposure where you repeatedly narrate the traumatic memory out loud or in writing until the emotional charge diminishes. Prolonged Exposure therapy, developed by Edna Foa, combines both. You do imaginal exposure first to process the memory, then in vivo exposure to tackle the avoidance behaviors that keep the PTSD looping. The imaginal part is honestly the harder one for most people. Sitting in a room replaying the worst moments of your life on loop until they stop sounding like live events and start sounding like memories is not something you recommend lightly.
Get the Full Details

I remember one case where a patient was stuck on imaginal exposure for months. Every time she tried to narrate her trauma, she would dissociate and lose the thread. She would come back to the room hours later saying she felt nothing and could not access the memory. The workaround I used was switching to written exposure first. She wrote the narrative down between sessions instead of speaking it. The act of writing created enough distance for her to engage without fully disengaging from reality. After three weeks of writing, she could do the spoken version. It is a small tweak but it made the difference between that patient dropping out or continuing. Those detours are the reality of clinical work. The manuals do not always account for them. There is a common misconception that exposure therapy is about desensitization only. It is more accurately about excitatory learning. You are not just getting bored of the trigger. You are building a new memory that says the trigger is safe. That distinction matters because it affects how therapists frame the work to patients. When someone understands they are constructing a new association rather than just wearing down an old one, compliance tends to improve. The suffering has a clearer purpose. Another thing beginners miss is that session length and frequency matter more than people realize. Weekly thirty-minute sessions rarely produce results. The standard protocol is fifty to ninety minutes per session, at least once weekly, often twice weekly for prolonged exposure. Shorter or less frequent schedules tend to produce incomplete habituation and higher dropout rates. The memory needs to be fully activated during the session for the new learning to take hold. If you leave early because you ran out of time, you are essentially rehearsing the fear response without finishing the corrective experience.
Homework between sessions is non-negotiable. The in vivo assignments require patients to practice the exposure ladder on their own time. Skipping homework is the number one reason treatment fails. I tracked this myself. Patients who completed their homework had significantly better outcomes across every measure. Those who did not usually stopped showing improvement by session four or five and either exited treatment or plateaued at a subclinical level of functioning. There are downsides and this is where the honest part comes in. Exposure therapy has a dropout rate somewhere between twenty and thirty percent depending on the study. People quit because it is genuinely difficult and sometimes temporarily makes symptoms worse before they get better. The initial phases can increase anxiety, disrupt sleep, and bring up avoided emotions that feel unbearable. A poorly managed exposure session without adequate preparation or support can actually reinforce the fear instead of reducing it. This is why therapist competence and proper screening are essential. Certain conditions complicate or contraindicate exposure therapy. Active substance abuse, severe depression with suicidal ideation, untreated bipolar disorder, and some personality disorders can make standard protocols unsafe or ineffective. In those cases, stabilizing the patient with other treatments first is necessary. EMDR is an alternative for some patients who cannot tolerate the verbal processing demands of prolonged exposure. Some people respond better to stress inoculation training or cognitive restructuring approaches before attempting direct trauma exposure.
The research backing exposure therapy is solid. It is one of the most studied psychological interventions and consistently ranks among the most effective treatments for PTSD. The VA and DoD guidelines recommend it as a first-line treatment. That does not mean it is the right choice for every person with PTSD. It means it is the best tool we have for many of them when delivered correctly. If you are considering this for yourself or someone you know, the practical steps are straightforward. Find a licensed therapist trained in trauma-focused therapies. Ask about their experience with prolonged exposure or CPT, which is cognitive processing therapy, another evidence-based option. Discuss your specific triggers and trauma history beforehand so they can build an appropriate hierarchy. Commit to the homework. Expect it to be hard in the short term. Give it at least ten to fifteen sessions before judging whether it is working. Most people need more than eight sessions to see meaningful change.




