How to Actually Use Expressed Emotions In Psychology in Clinical Practice
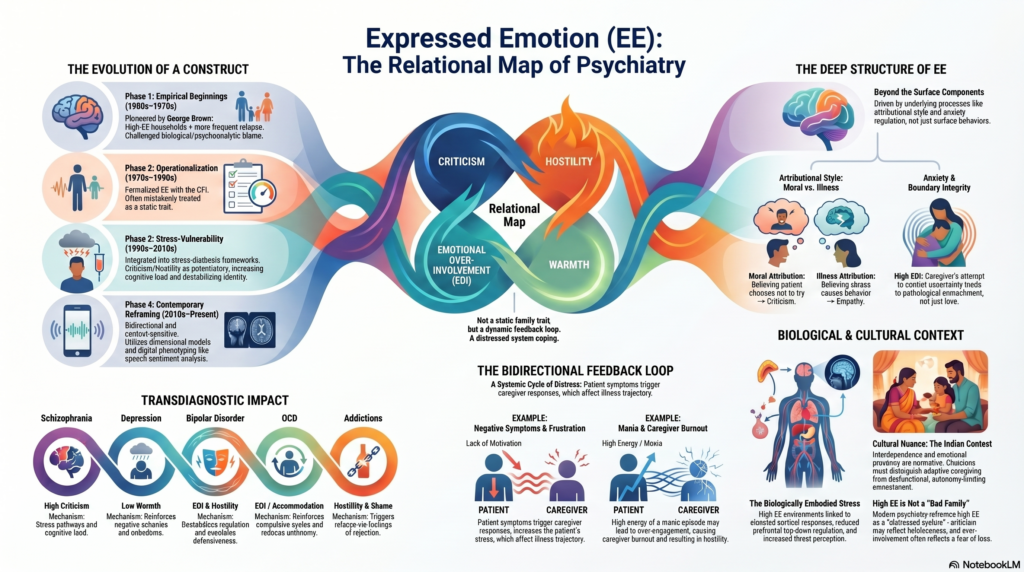
Most people coming across Expressed Emotions In Psychology for the first time read a textbook definition and think they understand it. They don't. The concept itself is straightforward, but applying it correctly in a real clinical setting is where things fall apart for a lot of people. I've sat through hundreds of EE interviews, scored dozens, and watched trainees completely miss the signal because they were looking for the wrong thing. Here is how it actually works when you strip away the academic language. The standard tool most programs use is the SAEI, the Schedule for the Assessment of Relatives, or the older CMI, the Cambridge Mental Illness interview. Both follow the same basic structure. You record a 5-to-10-minute segment where the patient describes their main relative and explains why that person is important to them. After that, you ask a series of structured questions about conflicts, criticisms, and emotional reactions. The relative does not need to be present. You are coding the patient's speech, not the relative's behavior directly. The scoring happens after you have a full transcript. You code for critical comments, hostility, emotional overinvolvement, warmth, and positive remarks. Critical comments are statements that express a negative judgment about the patient's character or behavior. Hostility goes further and attacks the patient as a person. Emotional overinvolvement is the tricky one. It shows up as exaggerated emotional reactions, overprotective behavior, or interrupting the patient to finish their sentences. Warmth and positive remarks are recorded separately and can buffer high EE scores, but they do not erase them.
I ran into a specific case last year that illustrates why the coding process is harder than it looks. I was scoring a patient who described their mother as "very supportive" and mentioned no conflicts at all. On the surface, this looked like low EE. But when I went back through the transcript carefully, I noticed the patient kept saying things like "my mother would never let me feel bad about anything" and "she always fixes everything before I even realize there is a problem." That is classic emotional overinvolvement masked by positivity. The initial read-through missed it entirely. I had to re-listen to the recording three times before the pattern became clear. The workaround I ended up using was timing myself on the first pass and refusing to finalize a score until I had coded every statement at least twice, looking specifically for indirect markers of overinvolvement rather than just the obvious ones. The inter-rater reliability on EE coding is somewhere around 0.75 to 0.85 when trained clinicians do it properly. That sounds good until you realize it drops to about 0.60 when clinicians from different training backgrounds score the same interview. This matters because a lot of programs still rely on single-rater scoring. If you only have one person coding, your reliability goes down and your conclusions become less trustworthy.
What High EE Actually Predicts
High expressed emotion in a patient's family environment is one of the most replicated findings in psychiatric research. Schizophrenia patients returning to high-EE families have a relapse rate of roughly 50 to 55 percent within nine months compared to about 20 percent when they return to low-EE families. The numbers shift a bit depending on medication adherence and other factors, but the direction is consistent across dozens of studies across multiple countries. The effect is not limited to schizophrenia. I have seen it applied to bipolar disorder, where high EE correlates with faster recurrence of mood episodes. In eating disorders, particularly anorexia and bulimia, family EE predicts poor response to treatment and longer hospital stays. The mechanism is not fully understood, but the leading explanation involves chronic stress activation. Living in a high-criticism environment keeps the hypothalamic-pituitary-adrenal axis activated, which interferes with treatment response and emotional regulation. Here is something most introductory texts do not emphasize enough. High EE is not a fixed trait of a family. It changes. A family that scores high on EE today can drop to low EE within six months if they receive targeted psychoeducation and communication skills training. The Patel and Leff study from the late 1980s showed that providing families with basic information about the illness along with practical communication strategies reduced relapse rates by about half. That finding has held up in subsequent replications.
Get the Full Details
Common Pitfalls When Applying EE Frameworks
The biggest mistake I see is treating EE as a verdict on a family rather than a snapshot of interaction patterns at a specific point in time. Families are not high-EE or low-EE permanently. They shift depending on stress levels, caregiver fatigue, cultural context, and the stage of the patient's illness. A mother who is exhausted and sleeping four hours a night will score higher on emotional overinvolvement than the same mother six months later when she has restored her routine and received adequate support. Cross-cultural assessment is another minefield. The standard EE categories were developed in British and American clinical settings. In collectivist cultures, what looks like emotional overinvolvement to a Western rater might be normal caregiving behavior. A relative who shares a bedroom with an adult patient, monitors their medication closely, and makes frequent visits is not necessarily displaying pathological overinvolvement. Some studies have found that South Asian families score higher on EE measures without showing the same relapse rates predicted by the original research. This suggests the measure may be capturing cultural differences in caregiving norms rather than a genuine risk factor. I encountered this directly when I was working with a Bangladeshi family where the patient's sister lived in the same household and checked on him four to five times daily. By standard coding criteria, this scored as high emotional overinvolvement. The relapse rate was no different from families with lower contact frequency. The workaround was to add a cultural adaptation step to the assessment, consulting with a community health worker who understood the family structure before finalizing the score. Without that step, the EE rating would have been meaningless and potentially harmful if it led to an incorrect intervention recommendation.
Interventions That Actually Move the Needle
Psychoeducation alone improves outcomes modestly. Adding cognitive-behavioral family therapy on top of psychoeducation produces a larger and more durable effect. The most robust programs include explicit communication training where families learn to express concerns without criticism, to make specific requests rather than general complaints, and to reinforce positive behavior. Sessions typically run for eight to twelve weeks with weekly contact. One counter-intuitive finding from the literature is that increasing warmth and positive remarks without addressing criticism and hostility does not reliably reduce relapse rates. Families will pour on the warmth, but if the underlying pattern of critical interaction remains unchanged, the patient still experiences high stress. The intervention needs to target the negative expressions directly. This is why some programs spend more time on helping families reframe criticism into concrete problem-solving language rather than simply encouraging them to be nicer. A practical detail that rarely gets mentioned is the burden on the family. Asking a caregiver to attend weekly sessions for three months is a significant commitment on top of an already demanding situation. In my experience, programs that offer flexible scheduling, telehealth options, or integrated group sessions see much higher retention rates. Dropout from family-based EE interventions is around 20 to 30 percent in unmodified programs, and that number matters because dropouts tend to be the families that need the intervention the most.
When EE Assessment Fails Completely
EE is not useful in every clinical scenario. If the patient has no ongoing contact with family members, the assessment is moot. I have seen clinicians insist on completing an EE interview with a patient who lives alone and sees their parents once a year. The resulting score tells you nothing about the patient's current environment. In those cases, assessing peer relationships or romantic partners might be more informative, though the research base for EE outside the family context is thin. Severe cognitive impairment in the patient also complicates EE assessment. The standard interview relies on the patient's ability to recall and articulate their relationship with a relative. A patient with moderate to severe dementia or an acute psychotic episode may not provide reliable information. In those situations, interviewing the relative directly or using observational methods is more appropriate, but those alternatives lack the validation history of the standard SAEI approach. The strongest evidence base exists for schizophrenia and bipolar disorder. For depression, anxiety disorders, and personality disorders, the predictive value of family EE is unclear. Some small studies suggest a link, but the findings are inconsistent enough that I would not recommend routine EE assessment for those populations. If a colleague asks me whether they should start doing EE assessments for a borderline personality disorder clinic, the honest answer is no, not unless you have a research protocol in place and a team trained in the methodology.

Practical Steps for Getting Started
If you are considering implementing EE assessment in your practice, the first requirement is proper training. Watching a webinar is not sufficient. You need supervised practice with recorded interviews and feedback from an experienced coder. Most reputable training programs require at least ten supervised codings before a clinician is considered reliable. The cost of training is real, but skipping it guarantees inconsistent results. You will need recording equipment, transcription services or software, and a scoring manual. The SAEI manual is available through Hogrefe Publishing. The CMI materials are older and harder to obtain. Budget roughly 10 to 15 minutes per interview for transcription and another 20 to 30 minutes for scoring once you are proficient. A novice will take considerably longer. The total time investment per patient is somewhere between 45 and 60 minutes, which is significant in a busy clinical setting. The payoff comes in treatment planning. Knowing a family's EE status helps you decide whether family-based intervention should be a priority, which patients are at higher risk for relapse after discharge, and where to direct your limited resources. It is not a crystal ball. It is a risk indicator that improves decision-making when used alongside other clinical information. Used in isolation, it gives a false sense of precision that the data does not actually support.