Most people think of extensor tendons as just the cables that straighten your fingers. That is not wrong, but it is also not nearly enough if you are actually working with them clinically or surgically. The dorsal aspect of the hand has a layered architecture that people routinely overlook until something goes wrong. I spent years mapping this out during repairs and reconstructions, and even now I get tripped up by the subtler relationships if I am not careful.
Key Zones of Extensor Tendon Anatomy
The extensor tendons are divided into nine functional zones, originally described by Veltri and Matthews and later refined by Eaton and Lamb. Zone I runs from the distal interphalangeal joint to the insertion on the distal phalanx. Zone II is the most notorious zone in flexor terminology but on the extensor side it refers to the area from the nail bed to the proximal interphalangeal joint. Zone III covers the middle phalanx, Zone IV is the proximal phalanx, Zone V is over the metacarpals, Zone VI is the dorsum of the hand beneath the extensor retinaculum, Zone VII is the distal radius, Zone VIII is the forearm near the musculotendinous junction, and Zone IX is within the forearm proper. This zoning system matters because each zone has different healing constraints, pulley systems, and surgical access limitations.
The sagittal bands are one of the most easily damaged structures in the extensor mechanism. They stabilize the extensor tendon over the metacarpal head and the proximal phalanx. When these tear, the tendon subluxes or dislocates laterally, usually toward the ulnar side on the radial fingers and toward the radial side on the ulnar digits. I have seen this happen after a simple dorsal hand laceration where the skin wound looks minor but the underlying sagittal band is completely disrupted. Without surgical repair, the patient loses active extension and the finger drifts into a swan-neck deformity pattern within weeks.
The central slip insertion on the base of the proximal phalanx is another critical landmark. A dorsal avulsion fracture here or a direct laceration through the central slip produces a boutonniere deformity if left untreated. The lateral bands then drift volarly and the proximal interphalangeal joint flexes while the distal interphalangeal joint hyperextends. I once spent three weeks trying to manage a failed conservative treatment case where a small avulsion was missed on initial x-ray. The range of motion was permanently compromised. Early recognition and splinting in extension at the PIP joint for six weeks is the standard approach, though some surgeons prefer surgical repair for larger fragments.
The juncturae tendinum are fibrous connections between adjacent extensor tendons, typically spanning from the second through fifth digits. These are not present on every hand in the same configuration. In about twenty to thirty percent of cases, the index finger extensor tendinosus indicis has no functional connection to the adjacent tendons. This has clinical significance during tendon transfers and repairs because the other digits can still contribute some extension even if one tendon is injured. I learned this the hard way during a trauma case where I underestimated how much function the remaining interconnected tendons could provide after a zone V repair.
Pitfalls That Are Easy to Miss
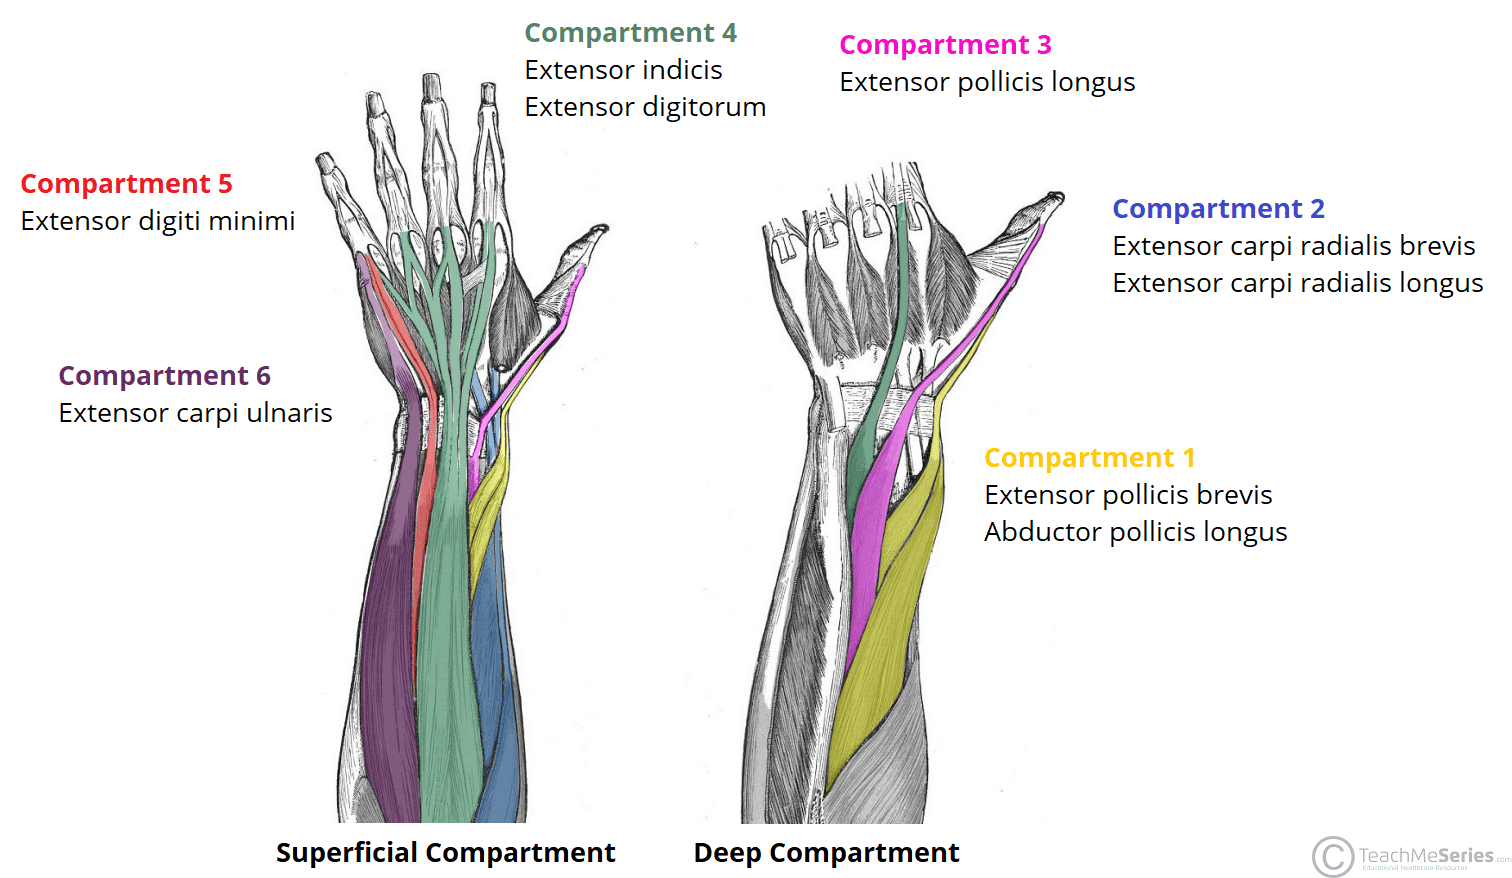
One thing that causes real problems is assuming the extensor tendons are uniform structures. They are not. The tendons change in composition as they travel distally. In Zone VI, under the extensor retinaculum, the tendons are reinforced by the intrinsic musculature contributions. The extrinsic extensor digitorum communis runs through distinct compartments under the retinaculum, and each compartment is separated by fibrous septa. These septa can catch on sharp bone fragments or suture material, leading to adhesive formation and restricted glide. I have seen adhesions develop in as little as two weeks post-surgery when the repair site is in a high-tension compartment.
Another common error involves the oblique bundle, also called the triangular ligament, which connects the extensor indicis to the extensor digiti minimi. This structure is relevant when planning tendon transfers for median nerve palsy. If you harvest the extensor indicis for transfer without considering the oblique bundle, you may unintentionally compromise the independent index finger extension. The patient can still extend the index finger, but not in isolation from the other digits. This matters for pinch and fine motor tasks.
The paratenon surrounding the extensor tendons in Zone VI is thin but clinically important. It provides some vascular supply but minimal nutritional support. Unlike the flexor tendons with their mesotendons, the extensor tendons rely heavily on the surrounding tissue for blood flow. This is why extensive stripping of the paratenon during debridement leads to higher rates of tendon necrosis and rupture. I usually leave at least a sliver of paratenon intact whenever I am working in Zone VI, even during revision cases.
The interconnections between the extensor digitorum communis and the lumbricals via the lateral bands create a functional unit. When the lumbricals contract, they pull the lateral bands dorsally, which extends the interphalangeal joints while flexing the metacarpophalangeal joints. This is the intrinsic plus position. Surgeons reference this constantly during hand therapy protocols. A hand therapist who understands Extensor Tendon Anatomy can explain to a patient why early motion in the intrinsic plus position prevents stiffness without risking repair integrity.
A Practical Approach to Assessment
When evaluating extensor tendon injuries, you need to assess each finger individually at each joint. The patient should make a fist, then extend each finger independently. Look for lag at each joint. Then ask the patient to rest their hand palm-down on a table and lift each finger off the surface. This isolates the individual extensor digitorum slips from the common extensor mechanism. Loss of independent extension at the metacarpophalangeal joint with preserved distal extension often points to a sagittal band injury rather than a tendon laceration.
Radiographs are essential but limited. You will see bony avulsions in about ten to fifteen percent of central slip injuries if you look carefully at the lateral view with the proximal interphalangeal joint slightly flexed. Most soft tissue injuries are invisible on plain film. Ultrasound can be useful in experienced hands, particularly for partial tears and dynamic assessment of tendon glide, but it is operator dependent and not universally available.
MRI is overkill for most acute extensor tendon injuries. It becomes relevant in chronic cases where there is suspected tendon attrition, rheumatoid tenosynovitis, or preoperative planning for complex reconstructions. I generally do not order MRI for straightforward lacerations. Clinical examination tells you what you need to know ninety percent of the time.
Treatment decisions hinge on the zone, the completeness of the injury, and the timing. Complete lacerations in Zones I through V generally require surgical repair. Zone VI repairs are more controversial because the risk of adhesion formation is high. Some surgeons prefer primary repair with a rigorous early motion protocol. Others opt for secondary grafting after the scar matures. There is no strong evidence favoring one approach over the other, so practice patterns vary widely.
Zones VII and VIII are rare injury sites. When they occur, they are usually associated with high-energy trauma or fractures of the distal radius. The forearm extensor compartments are tighter here, and compartment syndrome is a real risk. I have managed two cases where the initial presentation was subtle swelling and pain out of proportion, and both required fasciotomy. Do not dismiss forearm extensor injuries just because the hand looks fine.
Conservative management works well for certain injuries. Central slip injuries without significant displacement are splinted in extension at the PIP joint for four to six weeks with the MCP joints free to move. Boutonniere deformities caught early respond to this protocol. Mallet finger injuries at the DIP joint are similarly managed with a dorsal splint in full extension for six to eight weeks. The success rate for acute mallet fingers treated conservatively is approximately eighty to eighty-five percent.
Surgical repair techniques vary. For zone I and II injuries, a Krackow or cruciate core suture combined with a running epitendinous suture is standard. The suture material choice matters less than the technique and the tension applied. I use 4-0 or 5-0 non-absorbable suture and verify glide before closing the skin. Postoperative protocols differ significantly among surgeons. Some advocate immediate controlled motion using a dynamic extension splint. Others prefer a period of immobilization followed by gradual mobilization. The evidence does not clearly support one protocol across all zones.
The complication profile is dominated by adhesions, stiffness, and tendon rupture. Rupture after repair is uncommon in clean lacerations but becomes more likely in crush injuries, degenerative tendons, or when the paratenon was stripped. De Quervain tenosynovitis is not directly related to extensor tendon injury but can coexist when the first dorsal compartment is involved in the same trauma. I have seen patients present with both a Zone VI extensor digitorum communis laceration and concurrent first compartment tenosynovitis from the same injury mechanism.
There is no single perfect reference for this topic. Textbooks like Green's Operative Hand Surgery have the most comprehensive coverage, but the information is dense and occasionally outdated. Peer-reviewed articles in journals like the Journal of Hand Surgery provide the most current evidence, though individual studies are often small and limited by retrospective design. YouTube surgical videos can be useful for visualizing techniques but they lack critical context about indications and contraindications.
The field moves slowly. Most guidelines are based on expert opinion and case series rather than randomized controlled trials. This is true across hand surgery generally. If you are new to this, do not assume that any single protocol is the definitive answer. Clinical reasoning and anatomical understanding will serve you better than memorizing a treatment algorithm.
Gallery Extensor Tendon Anatomy
Extensor Tendon Anatomy – Extensor Tendon Injuries – GMCRXG
Extensor Tendon Anatomy – Extensor Tendon Injuries – GMCRXG
Extensor Tendon Anatomy – Extensor Tendon Injuries – GMCRXG
Extensor Tendons Of The Hand Anatomy Extensor Expansion Of Hand
Extensor Tendons Of Hand Anatomy Anatomy Drawing Diagram 479x619