Reading the outside of the heart
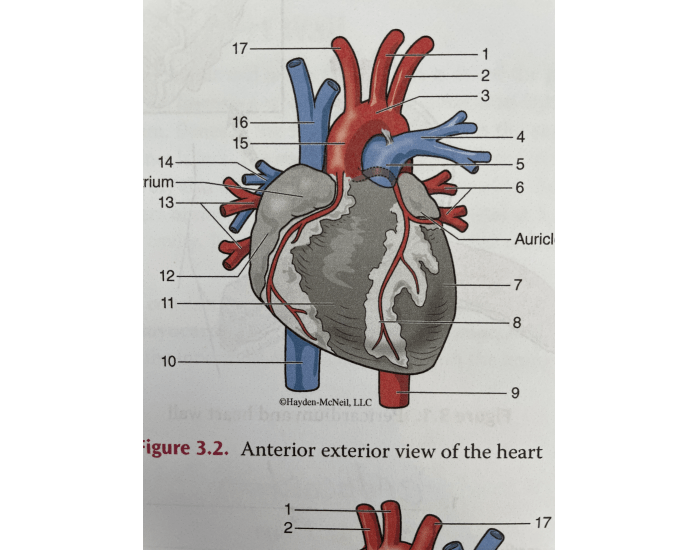
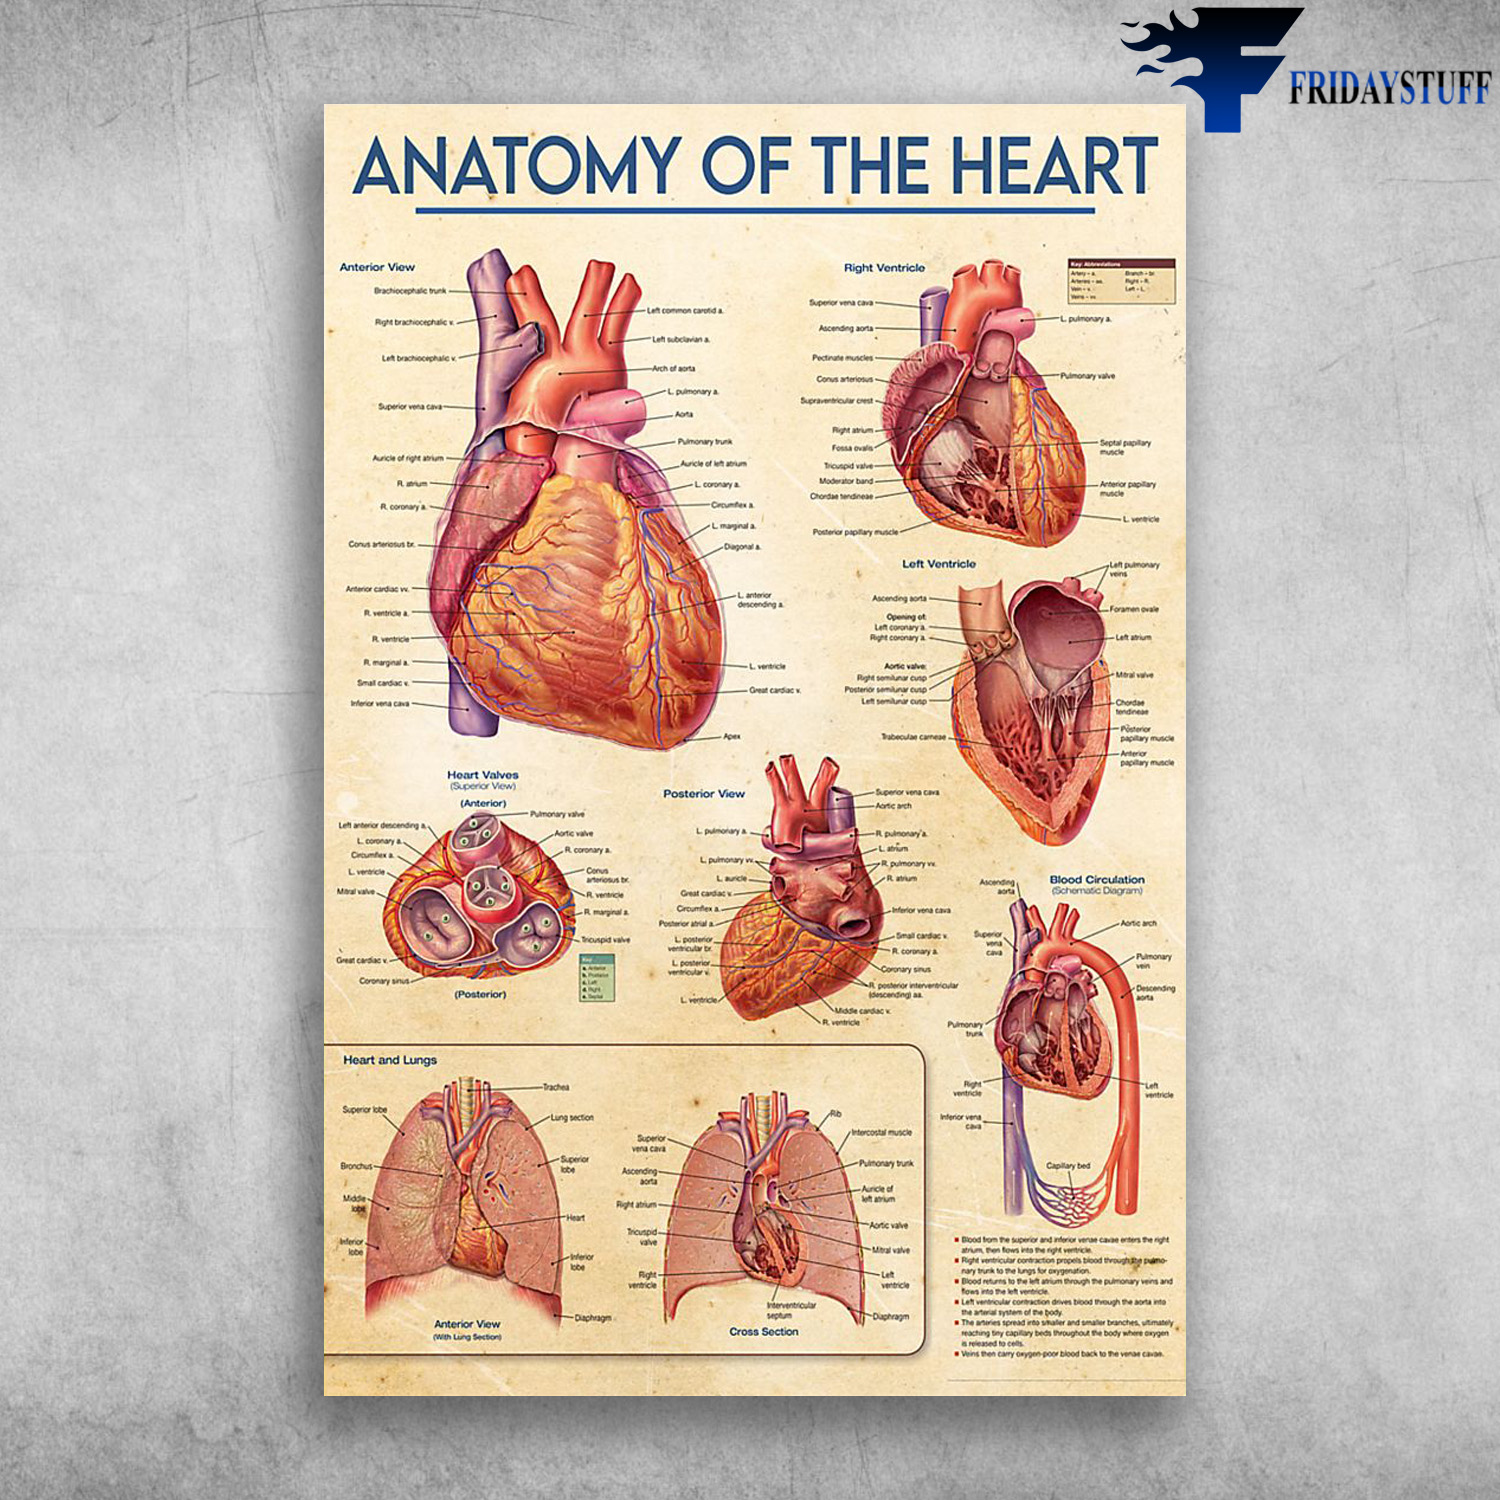
The External Anatomy Of The Heart is not as clean as the diagrams in textbooks. When you look at a real heart specimen or a high-quality cadaver image, you see a somewhat asymmetrical, roughly conical organ sitting in the middle of the chest, with major vessels emerging from its top and grooves marking where the muscle layers are. The surface features are reliable enough if you know what to look for, but the landmarks can be tricky when you are working with imaging data rather than a physical specimen. I spent years working with cardiac imaging and surgical planning, and even after all that time, I still catch myself second-guessing my orientation on coronal CT slices. The surface of the heart has several important features that tell you what you are looking at and where you are on the organ. The most obvious is the anterior interventricular sulcus, also called the anterior descending sulcus. This groove runs diagonally from the coronary sulcus near the top down toward the apex of the heart. It contains the anterior interventricular artery, which is a branch of the left coronary artery. That artery is clinically significant because it is one of the most common sites for coronary artery disease. The sulcus itself is a fairly reliable surface landmark, but its depth and visibility vary considerably between individuals. In some people it is deep and clearly defined. In others, especially those with more adipose tissue in the pericardial space, it can be shallow and difficult to trace. The posterior interventricular sulcus runs on the diaphragmatic surface of the heart. It usually contains the posterior interventricular artery, which in about 70% of people is a branch of the right coronary artery, and in the remaining 30% comes from the left circumflex artery. That anatomical variation matters if you are doing anything involving surgical planning or catheterization. A radiologist might report that the posterior descending artery arises from the left system, and you need to know what that means before you proceed with any intervention.
The coronary sulcus, sometimes called the atrioventricular groove, encircles the heart and separates the atria from the ventricles. It contains the right coronary artery on the right side and the left coronary artery, or left main stem, on the left side. The left main coronary artery typically bifurcates into the left anterior descending artery and the left circumflex artery within a few millimeters of its origin. That short segment is a common location for critical stenosis, and identifying it on imaging requires a good understanding of the surrounding anatomy. The sulcus itself is not always easy to identify on standard echocardiographic views because the fat within it can blend in with adjacent structures. The apex of the heart is formed primarily by the left ventricle and points downward, forward, and to the left. It sits at approximately the fifth intercostal space in the midclavicular line in most adults. The right ventricle forms most of the anterior surface of the heart. The left ventricle forms the left border and the apex. The right atrium forms the right border. These are the basic territorial rules, but they break down in conditions like severe cardiomegaly or dextrocardia. I once had a patient with an unusual case of situs inversus totalis who was being prepared for cardiac catheterization. The standard approach relies heavily on the assumption that the right ventricle is anterior and the left ventricle is posterior and to the left. In that patient, everything was mirrored, and I almost set up the equipment wrong before double-checking the pre-procedure imaging. That experience made me much more careful about confirming orientation on every scan, regardless of how routine the case seemed.
How to work with surface anatomy in practice
The most common way people encounter external cardiac anatomy is through imaging, particularly CT angiography and echocardiography. On CT, you can trace the sulci and identify the major surface features. The anterior interventricular sulcus is visible as a linear low-attenuation structure running along the anterior surface of the heart. The coronary sulcus appears as a circumferential groove containing fat and the coronary arteries. Identifying these structures on axial slices can be challenging because you are looking at cross-sections, not a gross anatomical specimen. The trick is to use multiplanar reformats. Coronal and sagittal reformats make it much easier to see the course of the sulci and the relationship between the chambers. On echocardiography, the external anatomy is less directly visible because ultrasound shows internal structures better than surface landmarks. However, you can infer the external configuration from the internal images. The parasternal long-axis view shows the anterior border of the heart, which is the right ventricle. The apical four-chamber view shows the apex formed by the left ventricle and the overall symmetry of the chambers. Understanding where the external grooves correspond to internal structures helps you navigate the images more effectively. Digital subtraction angiography provides a different perspective. The coronary arteries themselves are the most important surface landmarks in that modality because they run within the sulci. When you are injecting contrast and watching the fill pattern, you are essentially seeing the external vascular anatomy in real time. The right coronary artery courses through the coronary sulcus on the right side, giving off branches such as the acute marginal branch that runs along the acute border of the heart. The left main coronary artery is short and bifurcates quickly, and you need to capture the bifurcation clearly because missing it is one of the most common errors in coronary angiography interpretation.
Get the Full Details

One thing that is not always emphasized in basic anatomy courses is the variability of the surface features. The coronary sulcus may not form a complete circle in some hearts. The anterior interventricular sulcus may terminate before reaching the apex. There may be multiple septal perforator arteries arising from the anterior descending artery at variable positions. These variations are normal, not pathological, but they can confuse someone who is expecting the textbook description to match perfectly every time.
Common mistakes people make
The most frequent error is misidentifying the right and left sides of the heart on imaging. On a standard axial CT slice, the left side of the image corresponds to the right side of the patient. This sounds obvious, but it is surprising how often people reverse it when they are working quickly. I have lost count of the number of times I have seen a report that attributes a left ventricular finding to the right ventricle because the reader was orienting the image incorrectly. Always mark the patient's left and right on the screen before you begin your review. A two-second habit that prevents real problems. Another common mistake is assuming that the anterior interventricular sulcus always contains a single vessel. In reality, there may be multiple arteries running in close proximity within that sulcus. The septal perforators branch off at right angles and descend into the interventricular septum. They are easy to miss if you are only looking for the main vessel. When you are reading a coronary CT, zoom in on the anterior descending artery and trace each branch carefully. The septal perforators can be as small as 0.5 millimeters in diameter, and they are clinically important because occlusion of a large septal perforator can cause a septal infarction. A third mistake is underestimating the importance of the pericardial fat. Fat deposits in the coronary sulcus and along the surface of the heart can obscure the underlying coronary arteries on non-contrast CT scans. This is a particular problem in obese patients. The solution is to use contrast-enhanced CT and appropriate window settings. A mediastinal window set to a width of 400 Hounsfield units and a level of 40 Hounsfield units usually provides good contrast between the fat, the vessel walls, and the blood pool. Adjust the window if the images are too dark or too bright, but start there as a default.
What this approach does not do well
External cardiac anatomy, as viewed through imaging, has limitations that are worth acknowledging. CT angiography involves ionizing radiation and iodinated contrast, neither of which is ideal for repeated or screening use. Echocardiography is safer but operator-dependent and limited by body habitus and lung interference. MRI provides excellent soft tissue detail without radiation, but it is less widely available and takes longer to perform. No single modality gives you a complete picture of the external anatomy in every situation. Surface anatomy also tells you very little about the internal architecture of the heart. The position of the papillary muscles, the thickness of the ventricular walls, the status of the valve apparatus, and the condition of the myocardium are not reliably assessed from external landmarks alone. You need cross-sectional imaging of the chambers and valves to get that information. External anatomy is a starting point, not the final word. If you are trying to understand the gross anatomical relationships of the heart for a physical exam or a hands-on dissection, the best resource is still direct observation. Textbook diagrams and online images are useful supplements, but they are flat representations of a three-dimensional structure. Rotating a 3D model or examining a preserved specimen gives you a sense of depth and spatial relationships that no 2D image can fully convey. If your goal is practical clinical application, combining imaging review with a review of gross anatomical atlases will give you the most reliable foundation.