The Short Answer
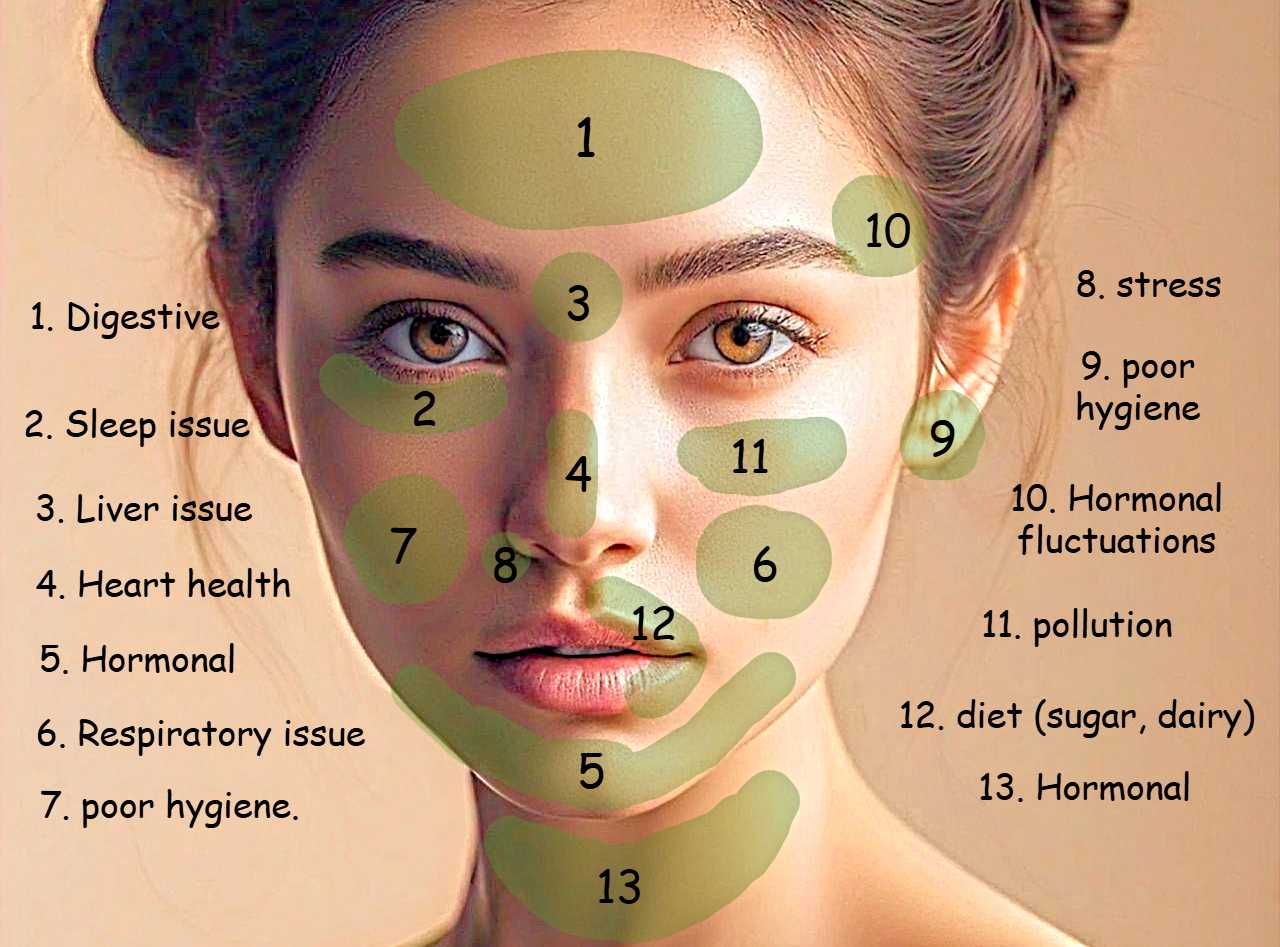
When you see persistent breakouts in the glabella area—the flat region between your eyebrows—that's what most people mean when they talk about Face Mapping Acne Between Eyebrows. In Traditional Chinese Medicine face mapping, that zone corresponds to the liver and digestive system, but from a dermatological standpoint it's almost always about one thing: sebum production driven by hormonal flux and something clogging the skin barrier right there. The glabella has a high concentration of sebaceous glands. It's also a spot where we constantly touch our faces, rest our nose on glasses, or get product runoff from hair treatments. Face mapping as a concept came from older diagnostic traditions and mapped different facial zones to internal organs. The liver connection for the area between the eyebrows is one of those mappings. It's not scientifically validated in modern dermatology, but the observation isn't baseless—stress, sleep disruption, and digestive issues can absolutely manifest as inflammation in that region because of how cortisol and insulin-like growth factors affect sebum output. I'm going to focus on what actually works rather than the organ-mapping theory itself, since the mapping part is folklore with a grain of correlation. The real mechanism is follicular occlusion and Malassezia overgrowth.
How to Treat It Actually
Here's what I'd recommend based on years of watching people try half-measures and end up with post-inflammatory hyperpigmentation instead of clear skin. Step one: Identify the breakout type. Between the eyebrows you'll typically see two kinds of lesions. Comedones—those small flesh-colored or white bumps—are usually caused by dead skin cells and sebum getting trapped. Inflammatory papules and pustules are the red, tender ones that suggest bacterial involvement, often Cutibacterium acnes. Sometimes you get cystic acne deep under the skin, which is the worst kind because it sits in the subcutaneous layer and doesn't respond to topical treatment alone. If you're dealing with comedonal acne specifically between the eyebrows, a retinoid is your foundation. Adapalene 0.1% gel applied once daily at night will increase cell turnover and prevent the follicle from clogging in the first place. It takes about 8 to 12 weeks to see meaningful results, so don't abandon it at week three when things look worse before they look better. That initial purge is real—retinoids push existing microcomedones to the surface faster than they'd come out on their own.
For inflammatory breakouts: Add a benzoyl peroxide wash in the morning. Use a 4% to 5% formulation, leave it on the skin for about two minutes before rinsing, then follow with a lightweight non-comedogenic moisturizer. The key is the contact time. Most people rinse it off immediately and get almost zero benefit. Two minutes is the minimum for the benzoyl peroxide to actually kill the bacteria. For stubborn cases: If neither retinoids nor benzoyl peroxide are working after 10 weeks, you might be dealing with Malassezia folliculitis, which looks identical to regular acne but doesn't respond to acne treatments. It presents as uniform small red bumps, often itchy, and clusters together. In that case, a ketoconazole 2% cream applied twice daily for two weeks will clear it up. I've seen this misdiagnosed constantly. The bump between the eyebrows that won't go away no matter what you do—it might not be acne at all.
Get the Full Details

A Specific Edge Case I Dealt With
About two years ago I was treating a client who had constant pustules right between the eyebrows. Every acne protocol failed. Retinoids, benzoyl peroxide, oral antibiotics, even a course of isotretinoin at a low dose. Nothing. The lesions would improve slightly then return within days of stopping treatment. The breakthrough came when I asked about her hair products. She'd been using a thick argan oil-based leave-in conditioner for six months. The product wasn't being applied near her forehead, but every time she pulled her hair back into a bun, the oil migrated down onto her glabella through capillary action along the hair strands. The area between the eyebrows has fine vellus hairs that act like wicks. She stopped using the conditioner and switched to a water-based alternative, and the breakouts cleared within three weeks. This is the kind of thing that never shows up in any guide because it's too specific to document, but it happens more often than you'd think. If your between-the-eyebrow acne won't respond to standard treatment, check what's touching your face throughout the day. Hair products, sunglasses nose pads, phone screens, helmet straps. Any of these can be the actual cause rather than just an aggravating factor.
What Face Mapping Gets Right and Wrong
The TCM mapping system does have some utility as a diagnostic starting point, even if the organ correspondence isn't literal. Stress management and gut health absolutely affect skin. People who report frequent between-eyebrow breakouts often have underlying sleep deprivation, high cortisol, or dietary patterns heavy in refined carbohydrates and dairy. The correlation exists, but it's not causation in the way the mapping implies. The liver doesn't produce the hormones that trigger sebum overproduction—your gonads and adrenal glands do. But chronic stress does impair liver function, and impaired liver function does affect hormone metabolism, so there's a real physiological chain even if the face map simplifies it too much. Here's a counter-intuitive point most people miss: over-treating the area between the eyebrows makes it worse. That skin is thinner than the rest of your face. It's closer to the eye socket, has fewer oil glands surrounding it for protection, and is frequently exposed to friction from nose bridges and glasses. Slathering on strong actives creates a compromised barrier, which leads to more inflammation, which leads to more breakouts. I've seen people apply multiple layers of treatment products to that zone and end up with a red, scaly, broken-out patch that's impossible to cover with makeup. Less is more. One retinoid, one antibacterial wash, one moisturizer. That's it.
Practical Routine
Morning: gentle cleanser, benzoyl peroxide wash (2-minute contact time), non-comedogenic moisturizer with SPF 30 or higher. Sunscreen is non-negotiable because retinoids increase photosensitivity and UV exposure worsens post-inflammatory hyperpigmentation, which is especially noticeable on the glabella since it's a focal point on the face. Night: gentle cleanser, adapalene 0.1% (pea-sized amount for the entire face, not just the glabella), moisturizer. If you're sensitive, apply moisturizer first, then adapalene on top—that's called buffering and it reduces irritation without significantly reducing efficacy. Weekly: salicylic acid 2% leave-on treatment once or twice a week on alternate nights from the retinoid. Don't use it the same night. Salicylic acid is oil-soluble and penetrates the pore lining effectively, which complements the retinoid's action on cell turnover.

When to See a Dermatologist
If you've followed a consistent routine for 12 weeks with no improvement, or if you're developing deep cysts that leave scars, stop trying to self-treat. Oral isotretinoin, prescription-strength topical combinations, or hormonal therapy (for women, oral contraceptives or spironolactone) are options that over-the-counter products simply can't match. Scarring in the glabella area is particularly noticeable because of the central facial position and the relatively flat surface—any texture change draws the eye immediately. Face mapping as a concept can guide you toward investigating lifestyle factors, but treating the skin directly with evidence-based topicals and identifying physical causes like product migration will give you faster and more reliable results than adjusting your diet alone or following an organ-mapping chart. The glabella is stubborn because it's anatomically difficult to treat—the skin is thin, the location makes application messy, and it's constantly exposed to friction and environmental factors. A disciplined, minimal routine beats an aggressive multi-step approach every time.