Understanding the Muscles That Actually Matter for Botox
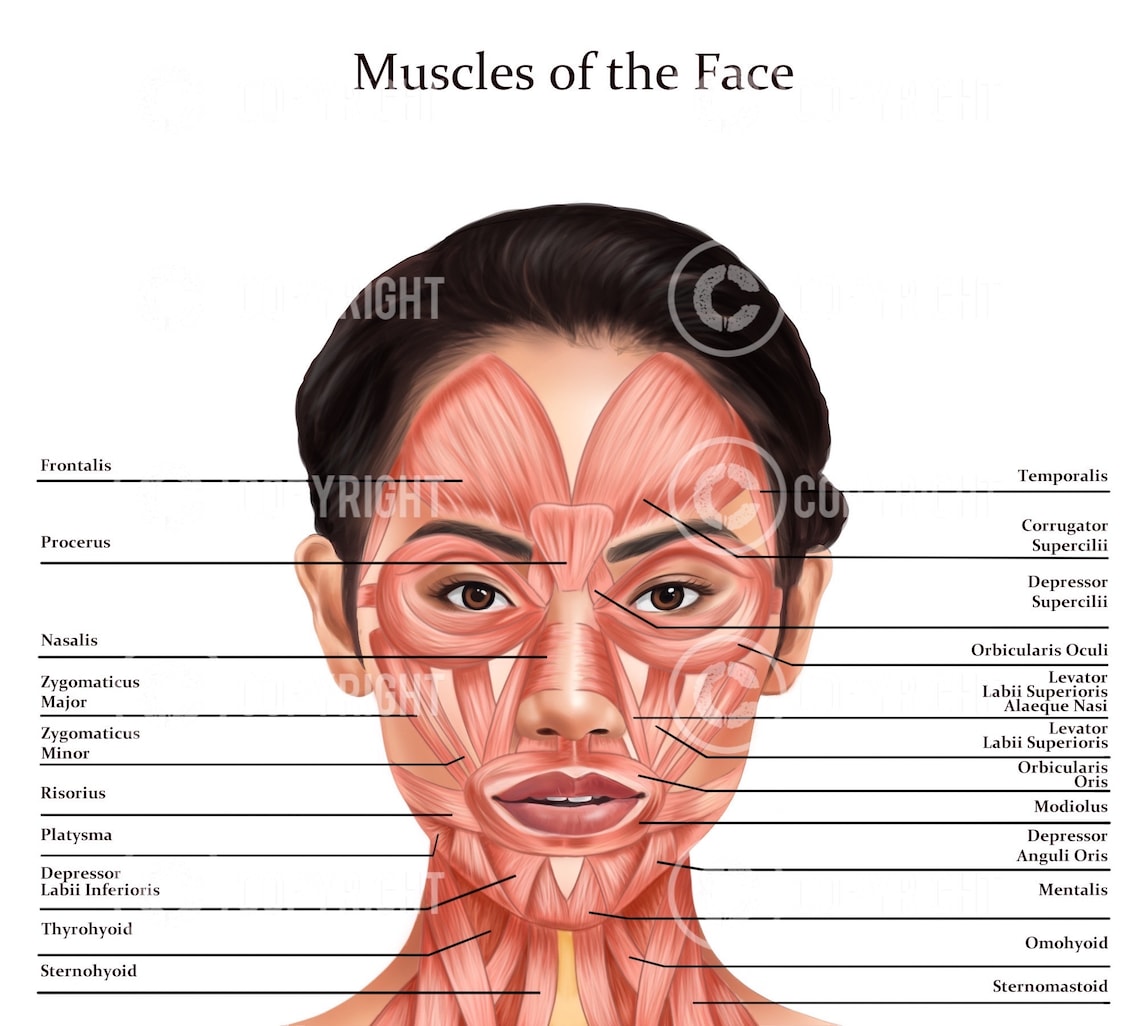
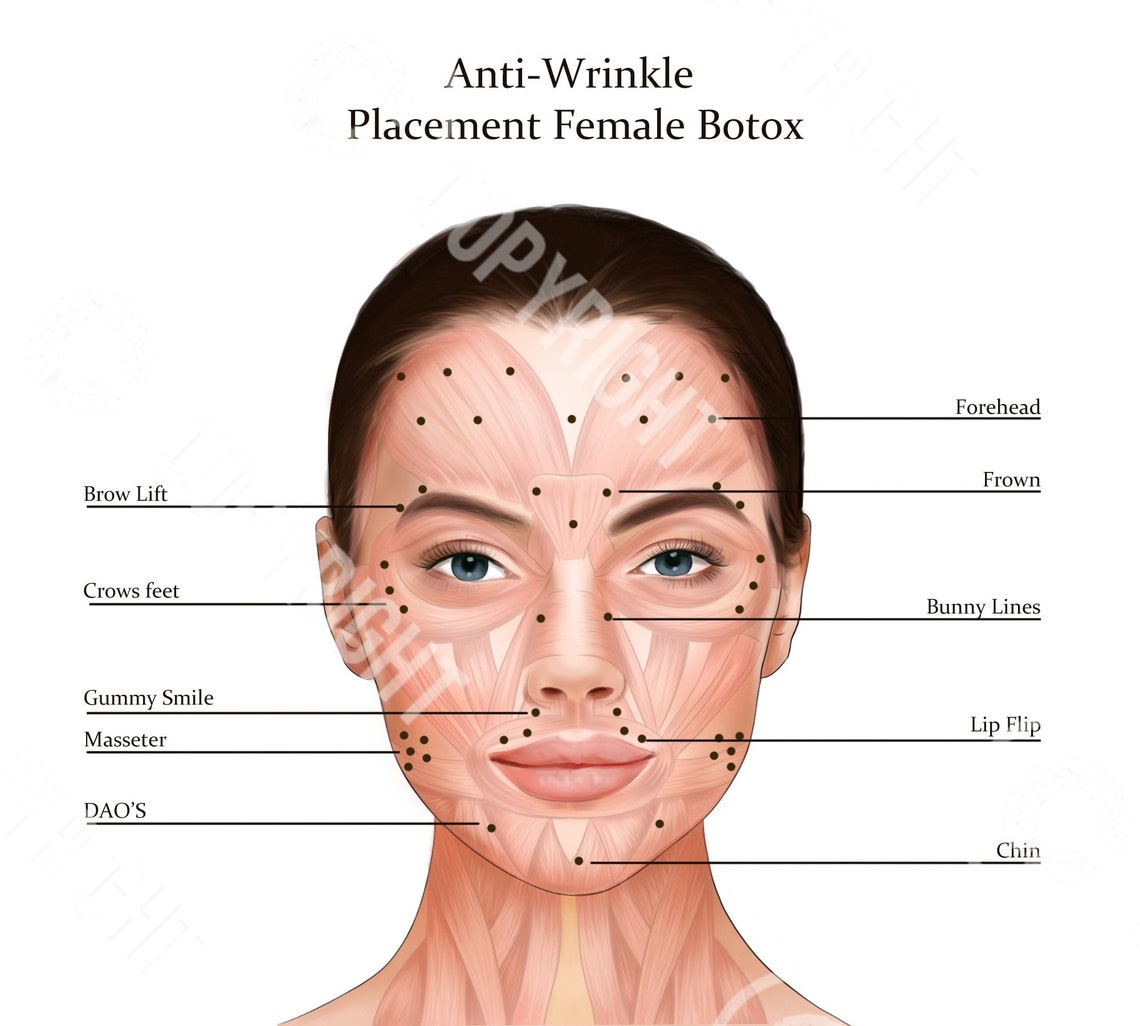
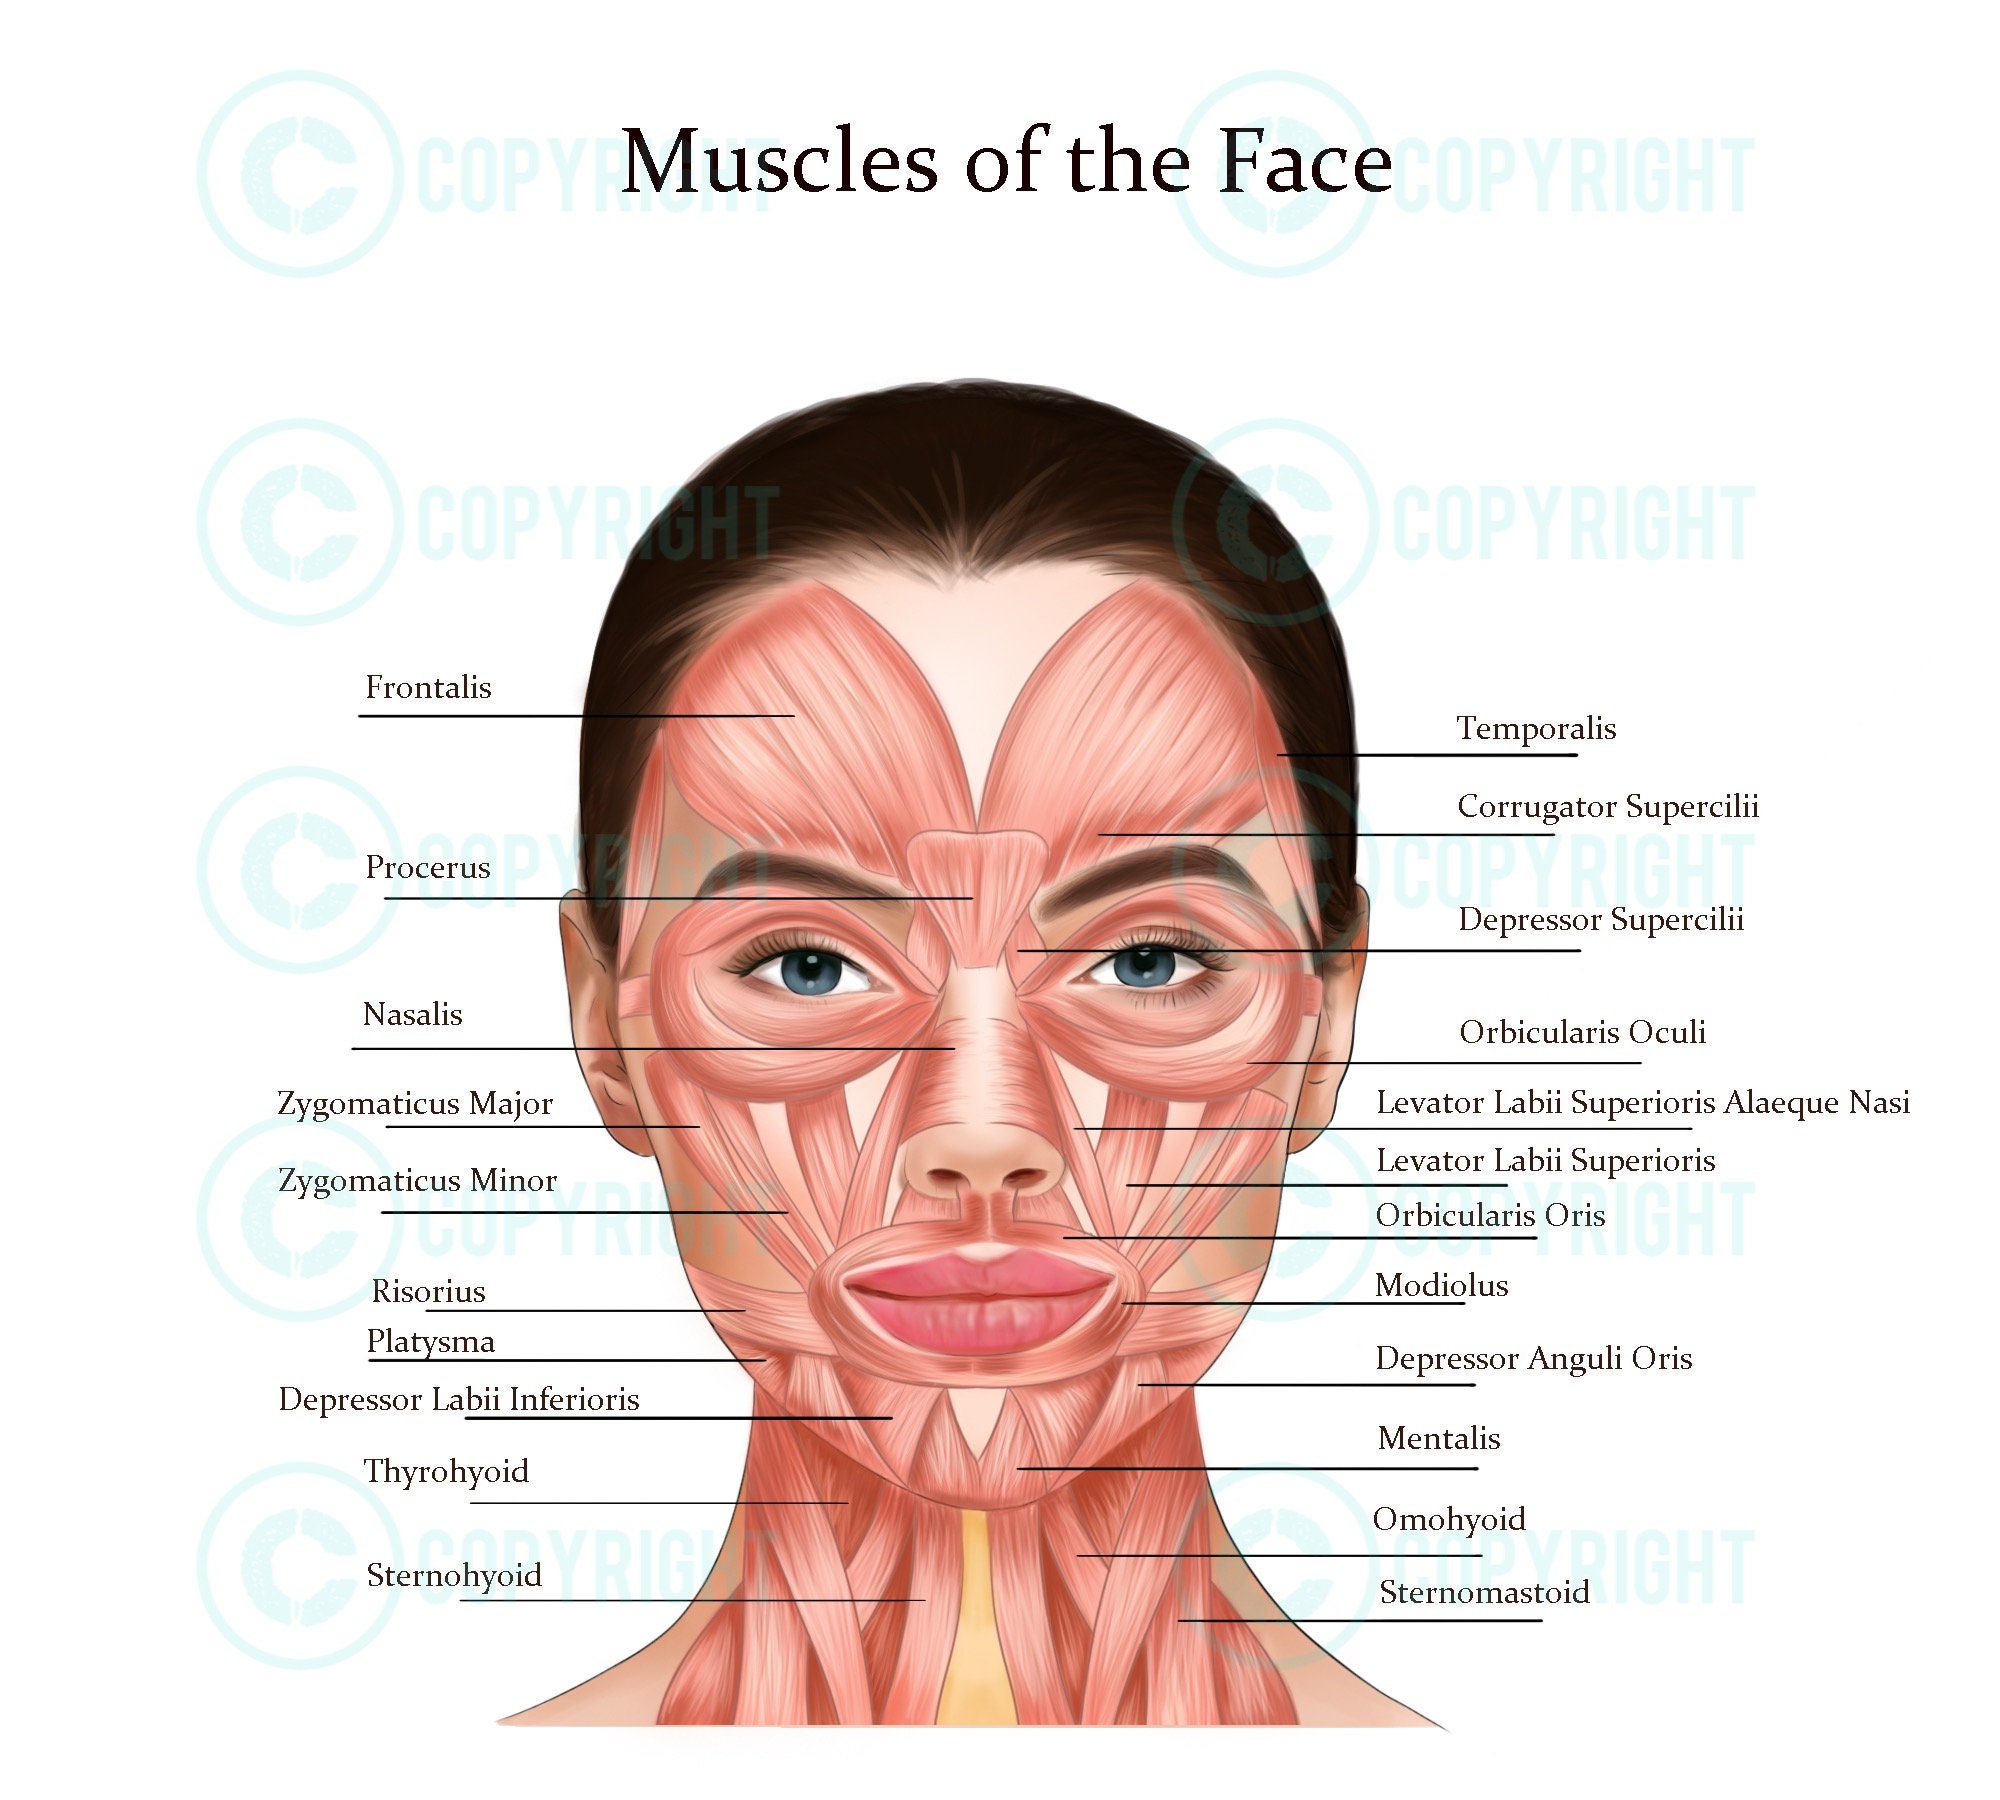
The face has roughly 43 muscles responsible for expression, and most of them don't need touching. When I started doing Botox, I learned the hard way that injecting everything you see on an anatomy chart just makes people look frozen and weird. The ones that actually respond to treatment are the corrug supercilii, procerus, frontalis, orbicularis oculi, and a handful of others. The platysma sometimes. The masseter occasionally, depending on what you're treating. Everything else is either too deep, too complex, or too risky to mess with without extensive training. Let me walk through how this actually works in practice. You're not just aiming at a muscle and pressing the plunger. You're working in a three-dimensional space where a millimeter of error can change someone's entire appearance. The corrugator pair sits deep under the medial third of the eyebrow. If you inject too high, you risk ptosis because the Müller's muscle gets affected. If you go too lateral, you're wasting product on tissue that won't move anyway. Most practitioners use 2 to 4 units per corrugator site, two injection points per side. I learned this after watching a colleague drop a patient into a noticeable brow droop that took four months to resolve because she was trying to save units by shooting one point instead of two. The glabellar complex is where most clinicians lose money and reputation. The corrugators, procerus, and the depressor sepi superioris all work together to create those vertical frown lines. The key insight nobody tells beginners is that the procerus gets targeted differently than the corrugators. For the procerus, you place injection points lower, about 1 cm above the nasal bridge, aiming slightly laterally to avoid the pyramidalis muscle. For corrugators, you enter just above the orbital rim at the lateral border of the pupil and angle the needle upward and inward. About 4 units per side for corrugators, 2 to 4 for procerus. The total glabellar dose typically lands between 20 and 30 units depending on muscle bulk. I've seen providers underdose the corrugators repeatedly because they're afraid of ptosis, only to have patients come back in six weeks complaining the lines are still there. They weren't underdosing the procerus enough either, which is usually the other half of the equation.
The frontalis is the most straightforward muscle but also the most misunderstood. It elevates the brow and creates horizontal forehead lines. The standard approach is 4 units per injection point across 5 to 6 sites, for a total of 10 to 20 units. The critical detail here is staying below the Superbrow line, which sits roughly 2 cm above the orbital rim in most people. Go lower than that and you'll hit the temporal fossa attachments or the levator palpebrae. Patients who come in wanting a completely smooth forehead often get disappointed because we leave just enough frontalis function to keep the brow from dropping when they smile. You can remove all activity if you want, but then they look permanently surprised and tired. I usually recommend a mid-range approach that preserves natural movement while reducing the lines. Crows feet are where orbicularis oculi treatment happens. This is a circular muscle, so you're treating a fan shape around the lateral canthus. Three injection points per side at 1 to 2 units each, spaced about 1 cm apart. The danger zone here is the lower lid. If the toxin diffuses downward, you get lower lid laxity or a slight droop that lasts as long as the treatment itself. I map the injection points with the patient sitting upright and asking them to squint, then I mark the spots. This takes about 90 seconds extra and prevents about 90 percent of lateral migration issues. I once treated a patient who had unusually thin skin at the lateral canthus and watched the product diffuse more than expected even at standard doses. The workaround was switching to a more dilute solution and injecting slower, which gives the tissue time to absorb the toxin before it spreads. Downsides and limitations exist that nobody talks about enough. First, Botox doesn't work on static wrinkles caused by sun damage or volume loss. If a patient has deep nasolabial folds from collagen degradation, injecting the muscles around them does nothing. You need fillers or skin resurfacing for that. Second, some people develop neutralizing antibodies after repeated treatments over years, though this is rare with proper dosing. Third, the effects are temporary. Every single time. Four to six months for most areas, sometimes eight for the masseter. There is no permanent option unless you want to start cutting nerves, which is a different conversation entirely.
Masked jawline is another scenario where anatomy gets complicated. The platysma runs from the clavicle up to the mandible and lower face. When treating the masseter for bruxism or jaw slimming, you need to be careful not to hit the marginal mandibular branch of the facial nerve. That nerve runs just below the mandible border and controls lip depression. Damage there causes an asymmetric smile where one side of the mouth doesn't lower properly. I always ask patients to clench their jaw first to identify the masseter belly, then I inject 20 to 30 units total per side depending on size, placing the needle 1 cm below the mandible angle and angling slightly upward. The marginal mandibular branch sits about 1.5 cm below the jawline, so staying above that threshold keeps you safe. If a patient has a very low-set nerve, which occurs in maybe 15 percent of the population based on cadaver studies, you might need to go even more superficial or use a different injection pattern. Training matters enormously. Watching a YouTube video and trying this on yourself or friends is not a viable path. The margin for error is measured in millimeters and units, and the consequences are real. I'd recommend starting with formal courses that include live cadaver dissection if possible, then shadowing experienced clinicians for at least a year before independent practice. The learning curve is steep and linear. There is no shortcut around understanding the facial nerve branches and how they interact with each muscle layer. Botox works by blocking acetylcholine release at the neuromuscular junction. The toxin cleaves SNAP-25, a protein essential for vesicle fusion and neurotransmitter release. This causes temporary chemical denervation of the injected muscle. Recovery happens through collateral sprouting of new nerve endings and eventual regeneration of the original terminals, which takes three to four months on average. Understanding this mechanism helps explain why higher doses take longer to wear off but also increase the risk of diffusion-related complications. It's a balance between efficacy and safety that you adjust based on individual anatomy, not a one-size-fits-all protocol.
Get the Full Details