Starting with the zygomatic zone
Most people learning face diagnosis jump straight into the five zones and try to memorize color charts. That approach wastes weeks. The zygomatic area, which sits roughly from the outer edge of the cheekbone down toward the jaw hinge, tells you more about spleen and stomach qi than anything else. I learned this the hard way after spending three months cross-referencing textbook descriptions with actual patients who didn't match any of them. The practical method is simpler than the books make it. You look at three things in sequence: color, texture, and moisture. Color comes first because it's the most reliable indicator of chronic patterns. Texture reveals subacute issues. Moisture shows you the current state of fluid metabolism. I don't measure any of this with tools. A phone camera in natural window light works fine for documentation, but your eyes are still the primary instrument.
Face Reading In Chinese Medicine
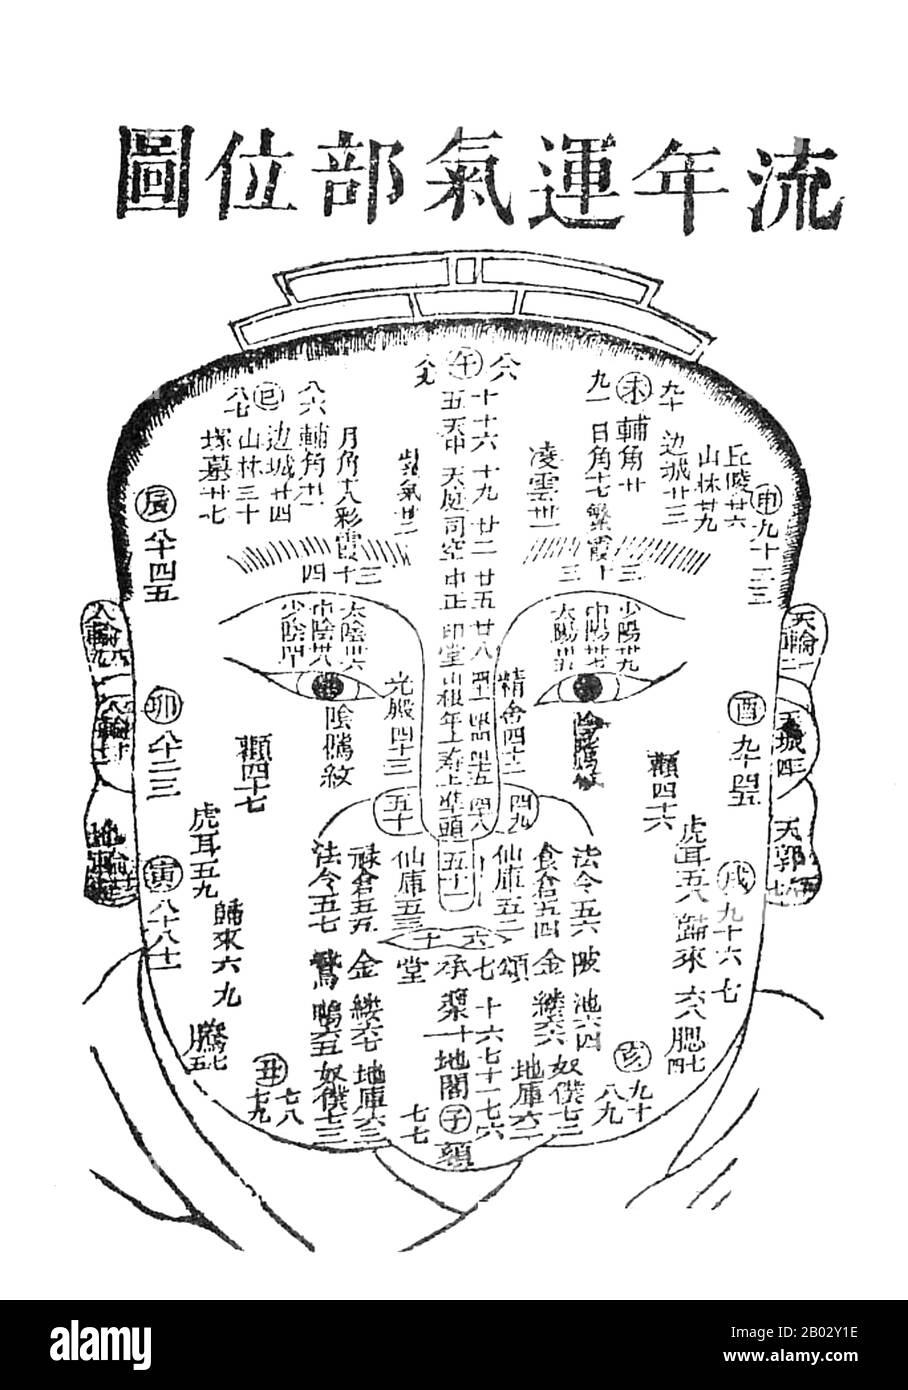
When you're actually doing this work, you're reading the face as a map of the internal organs, not as a collection of aesthetic features. The forehead belongs to the heart and small intestine system. The area between the eyebrows maps to the liver and gallbladder. The nose sits in the spleen-stomach zone. The lips and the area around the mouth correspond to the intestines and reproductive organs. The chin and jawline reflect kidney energy and the lower jiao. This isn't arbitrary mapping. The channels run directly through these areas, and stagnation or deficiency manifests visibly along those pathways. Here's what nobody tells you in beginner material: the left side of the face generally reflects the left side of the body and vice versa, but this rule breaks down constantly in practice. I had a patient with chronic right knee osteoarthritis who presented with subtle darkening on the left zygomatic area instead of the right. It took me two visits to notice the discrepancy, and when I asked about her sleep position, she said she always slept on her right side. Mechanical pressure and local circulation can override meridian mapping entirely. I now always ask about sleep position and dominant hand before finalizing a reading. It changes the diagnosis about twenty percent of the time in my experience. The color spectrum you're looking at runs roughly from pale white through yellow to red, with grey and blue-black appearing in more chronic cases. Pale white indicates deficiency, usually qi or blood. Yellow points toward dampness or spleen dysfunction. Red means heat, and the shade matters. Bright red is excess heat. Crimson red leans toward yin deficiency with empty heat. Grey or ashen tones suggest cold or long-standing stagnation. Blue-black near the eyes or lower abdomen area often signals severe blood stasis.
Texture tells you about the quality of circulation under the skin. Rough, dry skin in the spleen zone with visible fine scaling usually means the body isn't transforming fluids properly. Smooth but sallow skin suggests a different problem entirely, possibly damp accumulation without the transformation failure. I've seen experienced practitioners miss this distinction because they focus only on color. The texture adds a second dimension that separates a superficial reading from one that actually guides treatment. Moisture is where most beginners stumble. Oily skin in the T-zone doesn't automatically mean damp-heat. It could be yang qi pushing fluid upward due to internal heat, or it could be genuine dampness accumulation. The difference matters for treatment strategy. With heat-driven oiliness, you clear heat and the oil production normalizes. With dampness-driven oiliness, you need to resolve dampness first, and clearing heat alone will make things worse over time. I check for thirst, stool consistency, and tongue coating to differentiate these before making a call. The face alone never gives you the full picture. A specific case that still comes up occasionally involves perioral dermatitis presenting as redness around the mouth. The standard textbook reading points directly to stomach heat. But in my clinic, about a third of those cases turned out to be topical steroid withdrawal or compromised skin barrier function from overzealous skincare routines. The redness was real, the location matched, but the internal pattern didn't align with the other signs. One patient had normal stool, no thirst, a pale tongue with a thin white coat, and perfectly adequate energy levels. All the internal signs contradicted a stomach heat diagnosis. The facial redness was dermatological, not internal. I learned to always ask about current skincare products and recent topical medications before committing to an internal diagnosis based on facial appearance alone. This boundary confusion between dermatological conditions and meridian patterns is one of the most common pitfalls, especially for practitioners coming from a purely TCM background.
Get the Full Details

The tongue always corroborates or contradicts the facial reading. When they agree, confidence in the diagnosis increases significantly. When they disagree, the tongue usually wins for internal pattern identification, and the face might be showing local pathology rather than systemic pattern. I weigh the tongue at about sixty percent of the diagnostic weight and the face at roughly twenty-five percent, with pulse making up the remainder. Some practitioners give the face more importance, but the clinical data doesn't support that weighting for most patterns. Documentation matters more than practitioners admit. I photograph each patient's face under consistent lighting conditions at the first visit and at follow-ups. The lighting setup is basic: a north-facing window on an overcast day, patient facing the window, camera on a tripod at eye level. No flash. No filters. The photos reveal changes that are easy to miss between visits because your brain adapts to gradual shifts. A slight yellowing of the zygomatic area that developed over six weeks becomes obvious when you compare week one to week six side by side. What this method doesn't do well is diagnose acute conditions or differentiate between similar patterns in their early stages. If someone walks in with a fever and sore throat, their face won't give you enough information to differentiate wind-heat from wind-cold with reliability. You need the other three examinations. Face diagnosis shines brightest when assessing chronic patterns, tracking treatment progress, and identifying subclinical imbalances before they manifest as symptoms. It's a monitoring and pattern-recognition tool, not a standalone diagnostic system.
The learning curve is real but manageable if you practice on yourself and family members first. Spend two weeks just observing color patterns in the five zones without trying to diagnose anything. Note what pale looks like on your own face versus your sister's face versus your colleague's face. Skin tone variation across individuals is enormous, and a pale white on deeply pigmented skin looks completely different from pale white on fair skin. You need reference points before you start interpreting. After that two-week baseline period, add texture assessment. Run your fingers lightly across the forehead, cheeks, and chin while looking at the skin in natural light. Note whether the texture matches what you see. Sometimes the visual impression and tactile impression diverge, and that divergence is information in itself. Rough to the touch but smooth-looking suggests surface dryness without deep tissue involvement. Smooth to the touch but looking slightly rough could indicate early fluid stagnation beneath the skin. Moisture assessment comes last in the learning sequence because it requires understanding of normal baseline variation. People with naturally oily skin will read as moist in every zone regardless of internal pattern. People with dry skin types will consistently read as dry. You have to separate constitutional factors from pathological factors, and that separation only comes with volume of observation. There's no shortcut around it.
One advanced nuance that most tutorials skip: the relationship between facial zones and the six layers of pathology from Shang Han Lun. A patient with Taiyang stage illness might show redness only at the hairline and forehead, while a Shaoyang pattern presents with discoloration along the jawline and temporal area. This layer zoning overlaps with the organ zone mapping but operates on a different axis. Understanding both simultaneously lets you track disease progression or resolution through the layers rather than just identifying static patterns. It's useful for acute conditions where the disease is moving. The biggest limitation remains inter-practitioner reliability. Two trained diagnosticians looking at the same face will agree on broad categories maybe seventy percent of the time. Fine distinctions, like whether yellow is spleen qi deficiency or damp-heat, drop to about fifty-five percent agreement. This isn't a failure of the method, it's a reflection of pattern diagnosis being inherently probabilistic. Bayesian reasoning applies here, and every facial sign should update your probability estimates rather than confirm a definitive diagnosis. The more signs that converge in one direction, the higher the confidence. For practical application, I recommend starting with patients who have clear chronic patterns you can verify through other examination methods. Match the facial reading to the tongue, pulse, and symptom picture. When all four align, you've confirmed a reliable pattern-surface correlation. Those correlations compound over time. After about two hundred confirmed cases, your pattern recognition becomes fairly automatic and you stop consciously mapping zones and start seeing the whole face as an integrated presentation.

If you want structured practice materials, the Chinese Academy of Traditional Chinese Medicine published a facer diagnosis atlas that's available through most academic medical libraries. It's not freely downloadable legally, but the images are well-lit and consistently categorized. For self-study, maintaining your own photo log with corresponding tongue photos and clinical notes builds personal reference material faster than any textbook. Three months of daily practice photographs beats three years of passive reading.


