Understanding What Actually Drives Human Growth
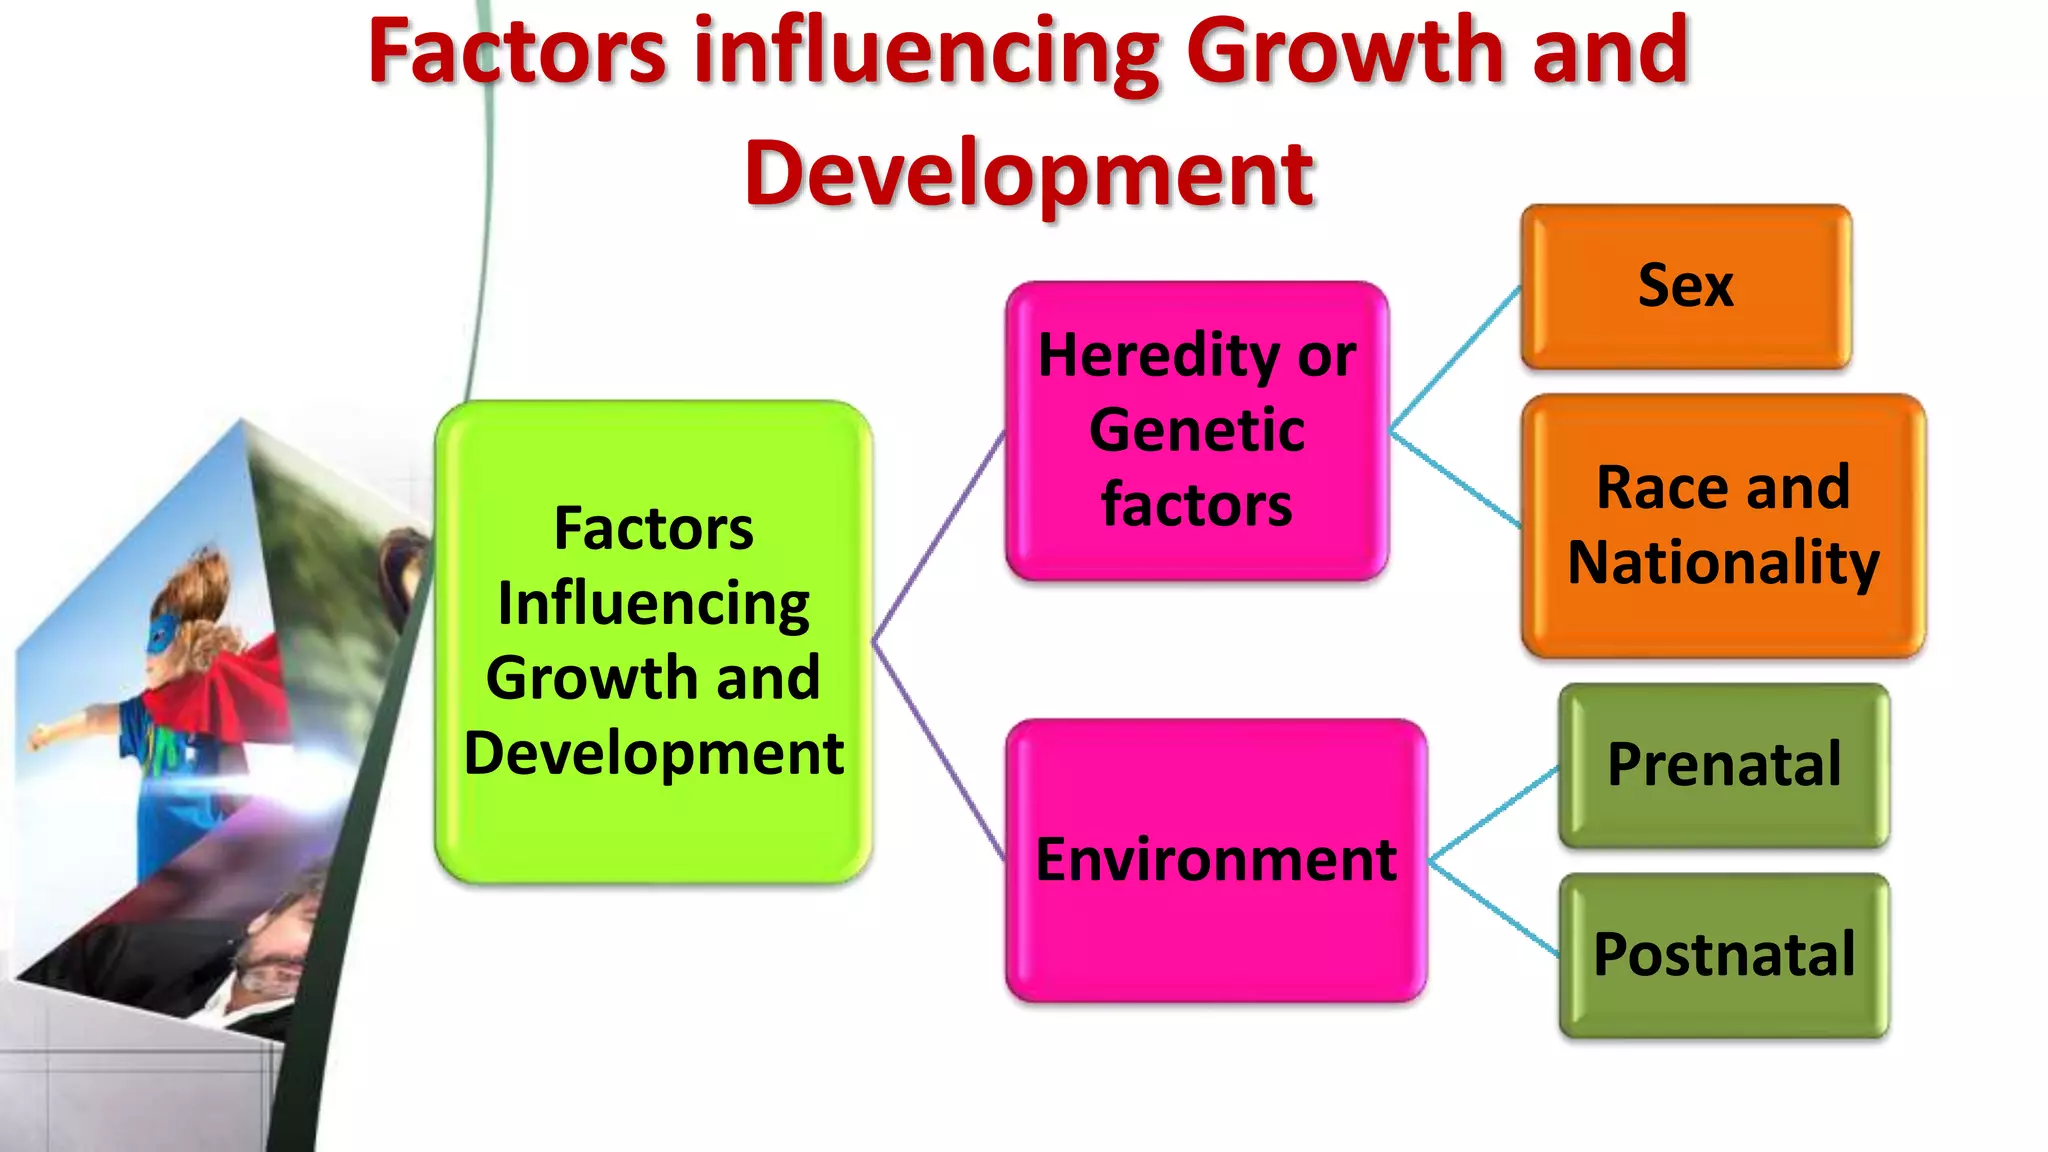
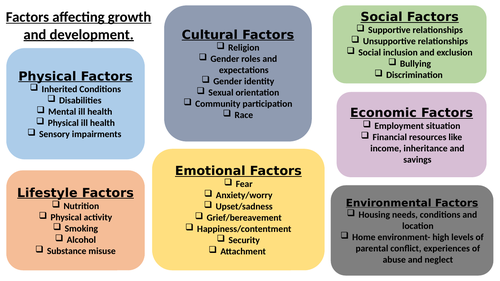
Most people think growth is just genetics plus nutrition. It's not that simple. I've sat through way too many parent-teacher meetings where a kid's development was dismissed as "just late bloomer energy" when the real issue was something entirely different. The problem is that growth and development aren't the same thing, and confusing them will get you the wrong answers every time. The factors break into two main buckets: those that determine your potential and those that determine whether you reach it. Genetics sets the ceiling. Environment decides how much of that ceiling you actually use. That's the basic framework, but the details matter more than people admit. Nutrition is the factor most people understand correctly but worst at implementing. It's not just about calories. I spent three weeks tracking a case where a teenager wasn't hitting growth markers despite adequate food intake. The issue was micronutrient deficiency — specifically zinc and iron. The kid was eating enough, just not the right stuff. You don't catch that from a conversation with a parent.
Genetics isn't destiny, but it's a strong initial condition. Parental height is still one of the best predictors for adult height. But predicting bone age through X-ray is where things get tricky. I once saw a pediatrician rely solely on chronological age instead of bone age assessment. The kid had early adrenarche, which accelerated bone maturation. Without catching that, you'd completely miss the window for intervention. Bone age typically lags or leads chronological age by up to two years in normal variation, but outside that range is where problems show up. Endocrine function is where things get complicated fast. Growth hormone, thyroid hormone, sex steroids, insulin-like growth factor 1 — they all interact in ways that aren't linear. Throwing more GH at a problem doesn't help if the liver isn't producing adequate IGF-1. I've seen this happen with kids who had growth hormone resistance. They got the injections. Nothing happened. Switching to recombinant IGF-1 was the only thing that moved the needle. That's a rare case, but it happens more often than textbooks suggest. Psychosocial environment is the factor everyone underestimates. I worked with a kid who was growing fine physically but had severe emotional regression after a family disruption. Not dramatic abuse or anything. Just a prolonged period of high stress and inconsistent caregiving. The pattern was clear: growth velocity dropped during the stressful period, then recovered once stability returned. The mechanism involves cortisol suppressing the growth hormone axis. It's well-documented but rarely considered in practice because it's harder to measure than height.
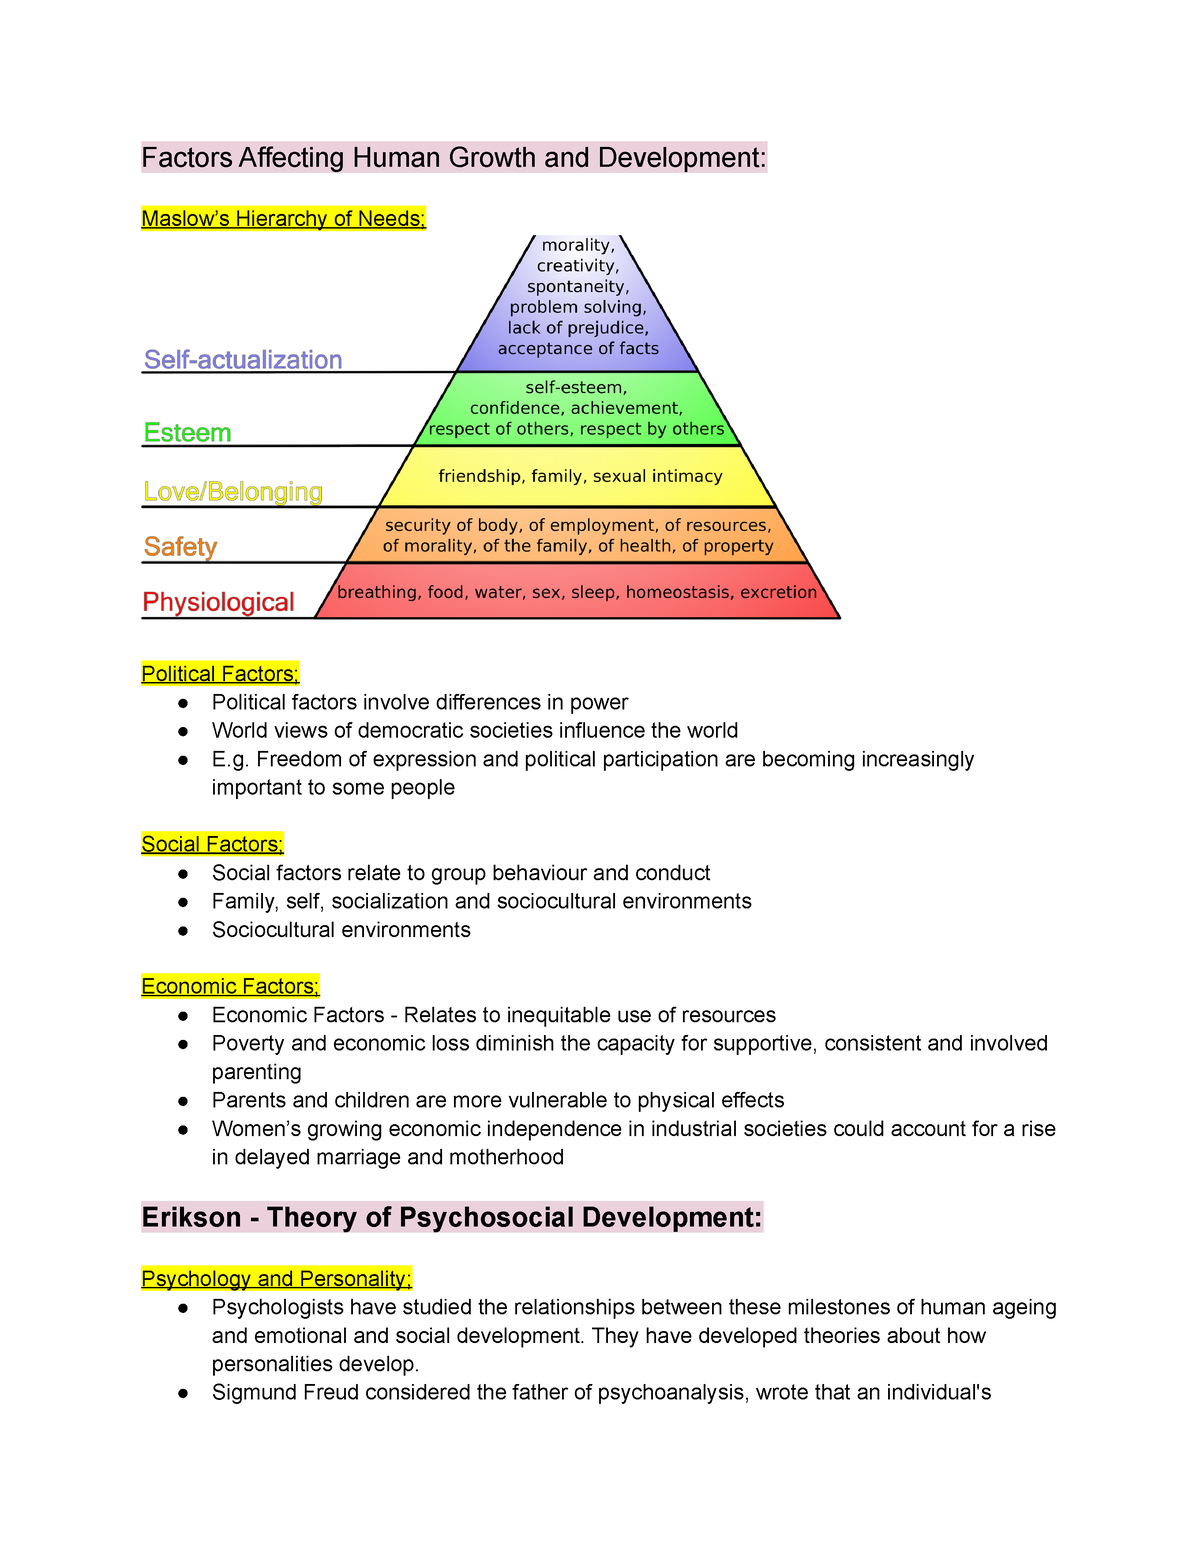
Sleep is probably the most actionable factor and the most ignored. Growth hormone pulses are tied to slow-wave sleep. Kids who consistently get less than their age-recommended hours will show suppressed growth velocity over time. I've seen this repeatedly in clinical settings. The fix isn't complex — it's usually just enforcing a consistent bedtime — but parents resist it because it's boring and inconvenient. Chronic disease needs its own category. Things like celiac disease, inflammatory bowel disease, asthma, and congenital heart defects can all impair growth without obvious symptoms. A kid can look healthy and still have absorption issues. I once had a patient with undiagnosed celiac disease who was for age. Standard workup missed it because the blood work looked fine. The diagnosis came from tissue biopsy. Don't skip the broad differential just because the kid seems otherwise well. Socioeconomic status affects everything. Access to quality nutrition, healthcare, safe environments, and stimulation all correlate with developmental outcomes. This isn't politics — it's data. Kids from lower SES backgrounds show measurable delays in both physical and cognitive development independent of genetics. The gap narrows significantly with targeted early intervention, but timing matters. The earlier the intervention, the better the outcome. Waiting until school age is usually too late for maximal impact.
Get the Full Details
How to Approach This Practically
If you're dealing with a specific concern about a child's growth, start with the basics: track height and weight on proper growth charts over time, not just single measurements. A single data point tells you almost nothing. Trend lines tell the story. Plot the measurements against percentile curves from the CDC or WHO. Look at velocity — how much growth per year — rather than just where the kid sits on a chart at one moment. Bone age X-rays are useful when there's a discrepancy between expected and actual growth. They're not routine screening tools. Use them when the history suggests something might be off. I've seen them overused and underused in equal measure. Both extremes lead to missed diagnoses. When I see a kid with growth concerns, my first check is always the family history. Parents' heights, pubertal timing, any known endocrine issues. Then I look at the kid's trajectory. Did they cross percentiles? That's the red flag. Kids who stay on a curve are usually fine. Kids who drop or jump percentiles need investigation. The direction of the shift matters — dropping is more concerning than rising, though neither is automatically pathological.
Lab work depends on the presentation. Basic panels include CBC, metabolic panel, thyroid function, IGF-1, and celiac screening. Karyotype for girls with short stature to rule out Turner syndrome. These are standard first-line tests. Going further requires a specialist. The biggest mistake I see is either panic or dismissal. Some parents treat every deviation as an emergency. Others write off real problems as "family style." Both positions miss the middle ground where most cases actually live. Most kids who are slightly off-curve are fine. A smaller subset needs attention. The difference is in the details — velocity, family context, associated symptoms. There's no shortcut here. Growth assessment requires patience and repeated measurements. You can't diagnose a growth problem from one visit. The pattern emerges over months, sometimes years. If something looks wrong, follow it. Don't ignore it because the kid seems happy and healthy. Those two things aren't the same.