Why Most Falls Risk Assessments Are Waste of Time
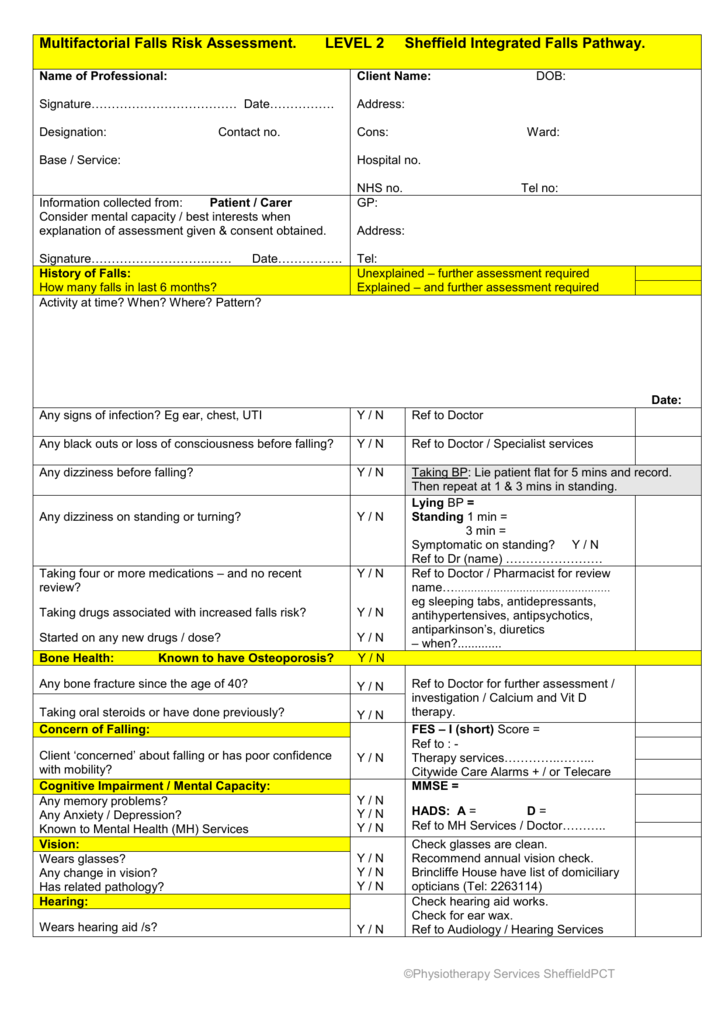
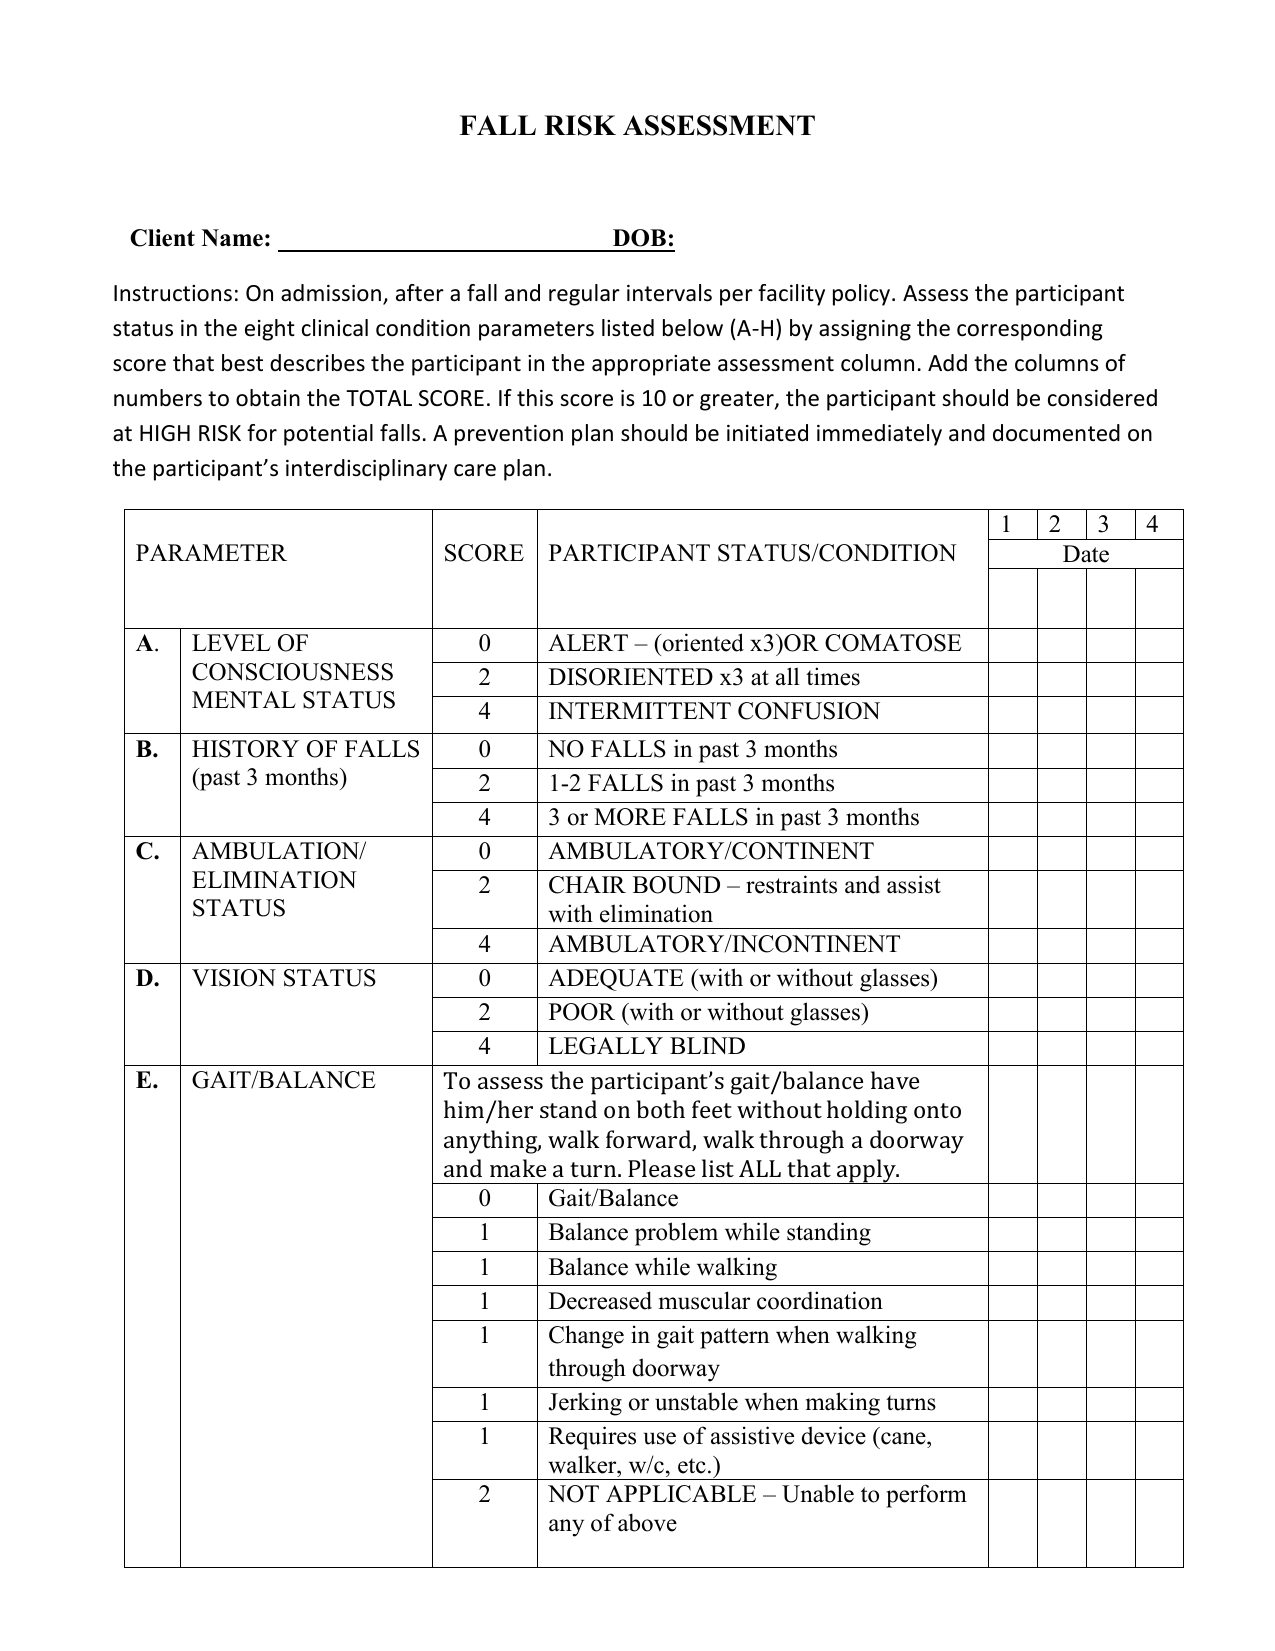
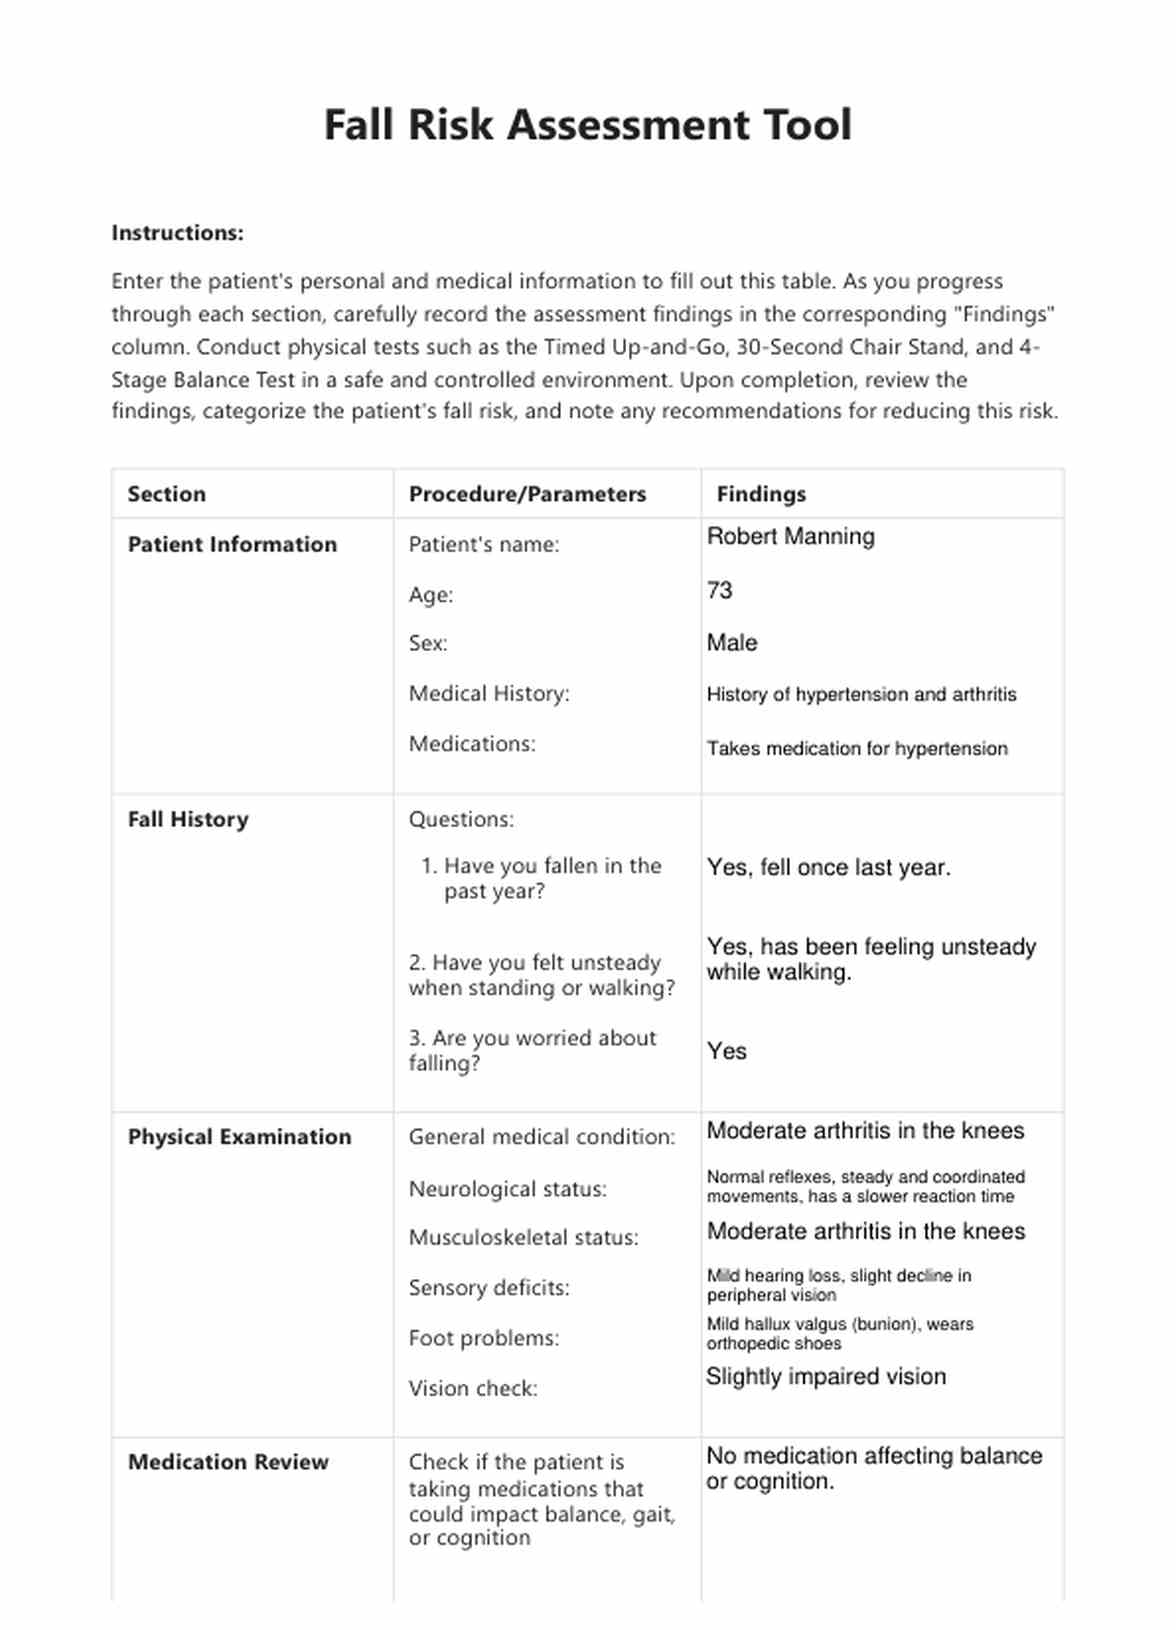
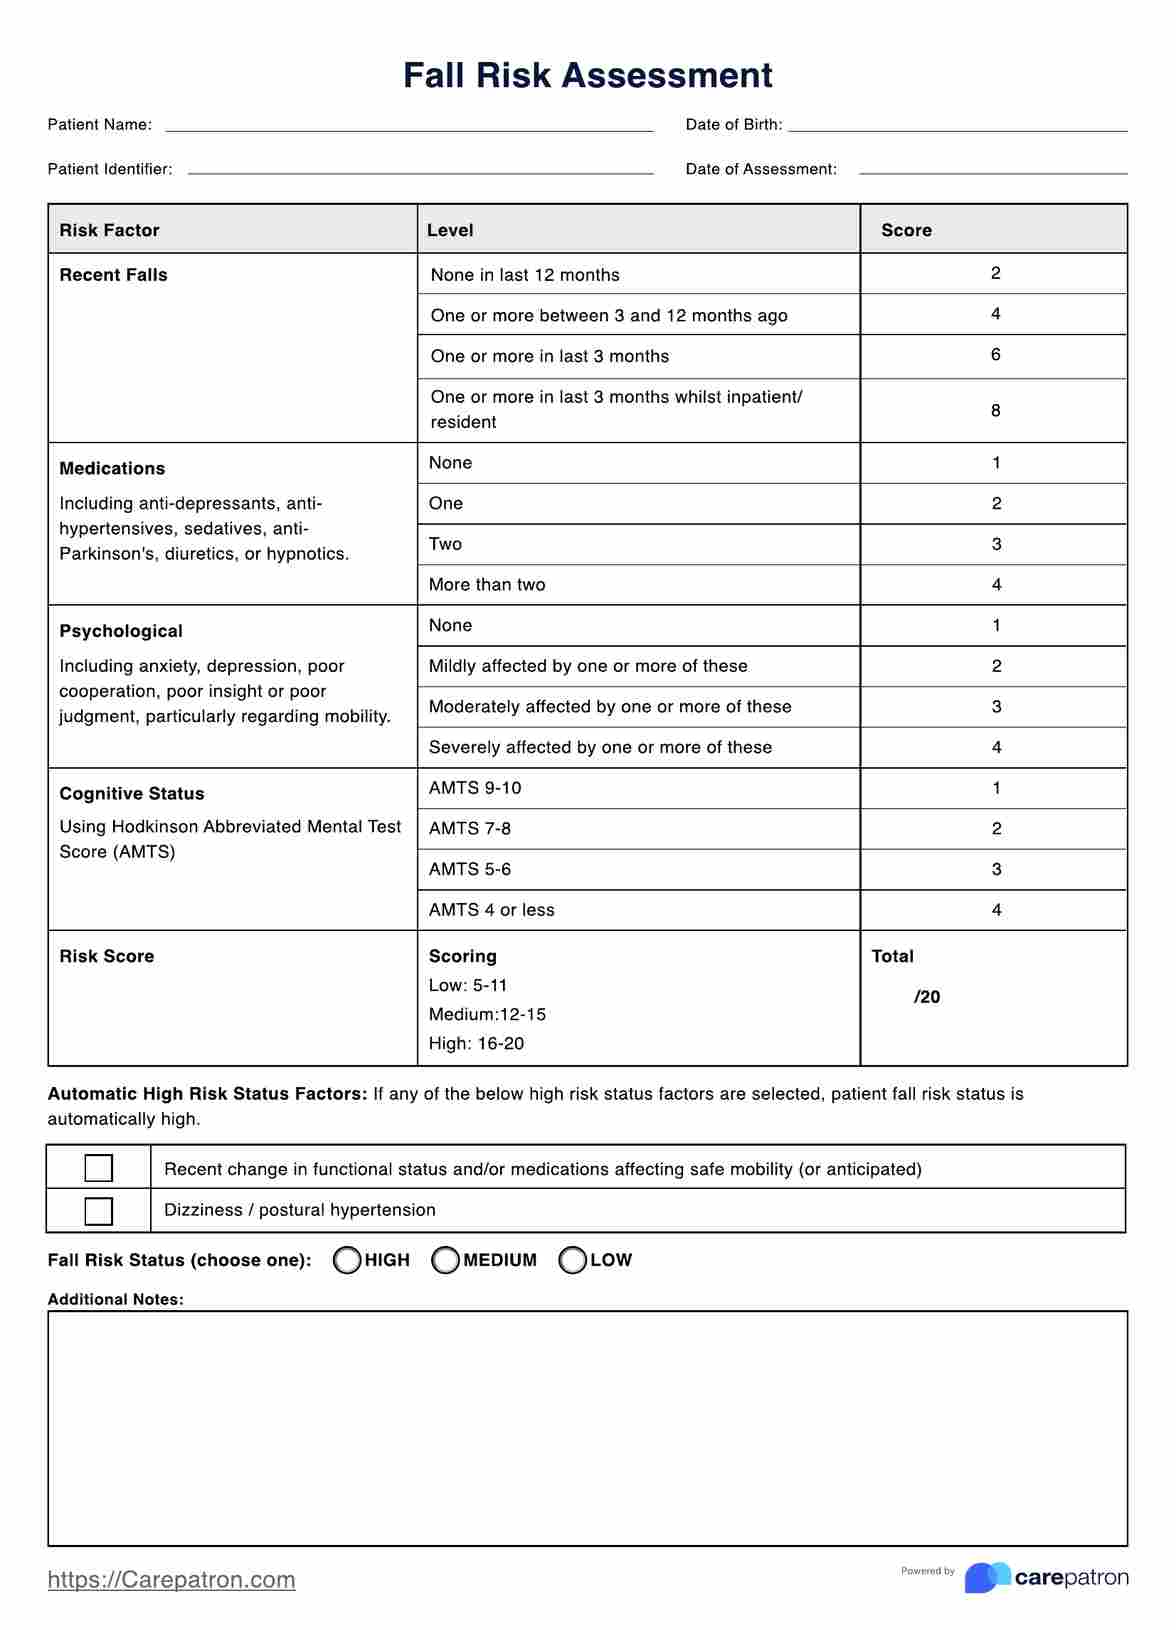
I've seen this play out too many times to count. A hospital buys some fancy tablet-based assessment system, sends staff through a half-hour training module, and then wonders why falls rates haven't budged. The problem isn't the tool. It's how people actually use it in a busy ward at 2 PM on a Tuesday.A Falls Risk Assessment Tool is really just a structured checklist disguised as a clinical instrument. The most common ones you'll encounter are the Morse Fall Scale, the Hendrich II Fall Risk Model, the STRATIFY tool, and the Johns Hopkins Fall Risk Assessment Tool. Each one takes a handful of patient factors — history of falls, gait, medications, mental status — and spits out a score that maps to a risk category. Here's the practical version nobody puts in the orientation binder. Pick one tool and stick with it. Don't switch between Morse and Hendrich depending on which nurse manager is having a favorite day. Consistency matters more than the specific instrument you choose. Administer it on admission, then reassess according to your facility's protocol. Most places do it every shift or whenever there's a significant change in condition. The data from reassessment is where the real value lives. A patient who scores low on admission but starts diuretics and becomes confused by day two needs a different level of intervention than the same patient would have gotten on day zero.
I once worked a unit where the electronic health record was set to auto-flag high-risk patients, but the alert threshold was set so low that nearly everyone lit up red. What happened next was predictable and frustrating. The nursing staff stopped reading the alerts entirely. They called it alarm fatigue, which is the clinical world's version of crying wolf. We fixed it by narrowing the criteria to match actual evidence-based thresholds and adding a mandatory clinical justification field. Documentation time went up by maybe ninety seconds per assessment, but the accuracy of our flagging improved dramatically. Falls within the first forty-eight hours dropped by roughly a third over the next quarter.
What the Literature Gets Wrong About These Tools
Most published papers on falls risk assessment treat the tools like they're diagnostic tests with clean sensitivity and specificity numbers. They're not. Here's what actually happens when you use them in real clinical settings. The Morse Fall Scale has a sensitivity problem. It catches a lot of people who fall, which sounds good, but it misses a meaningful number of patients who present with subtle balance issues that a four-item scale doesn't adequately capture. I've had patients score "low risk" on Morse because they hadn't fallen in the past year and their gait was "fair," but they were on multiple sedating medications and had orthostatic hypotension that showed up the moment they stood. They fell twice in three days. The Hendrich model accounts for more pharmacological variables, which helps. But it assumes the nurse completing it has reliable access to a complete medication list and knows which drugs carry fall risk. In practice, that's often not the case during a busy admission assessment. You'll get incomplete data, the score will be wrong, and the risk category will be misleading.
Get the Full Details

Neither tool reliably predicts falls in patients with neurological conditions like Parkinson's or post-stroke patients with hemiparesis. The standard item about "history of falls" doesn't capture the mechanistic difference between a fall caused by orthostatic hypotension and one caused by gait apraxia. The interventions for those two mechanisms are completely different. A single composite score flattens that distinction.
What Actually Works Beyond the Score
The risk score is a starting point, not a conclusion. After you get the number, you need to do something with it. The best programs I've seen tie the assessment to a tiered intervention protocol. Low risk gets standard precautions. Those are the basics — call light within reach, non-slip footwear, clear pathways. Nothing fancy. Medium risk triggers additional measures like hourly rounding, bed alarms, and a more thorough medication review. High risk gets everything above plus physical therapy consultation, occupational therapy for adaptive equipment, and often family education about supervision needs. The intervention protocol is where most facilities fail. They assess well but don't follow through because the protocols live in a policy binder that nobody references during actual workflow. The fix is usually integration into the EHR so that when a risk score comes back elevated, the corresponding interventions are auto-populated as orders that the nurse can accept or modify. It adds maybe fifteen seconds of work at the point of care and makes compliance something like seventy percent higher than paper-based systems.
Environmental modification is another area where the tools fall short. No assessment score tells you that the lighting in that particular patient's room is inadequate or that the bed height is set wrong. You have to actually walk the floor and look at things. The best nurses I've worked with did both — they scored the patient and they looked around the room. The scores and the environment check informed each other. If your facility doesn't have a validated tool yet, pick one and implement it properly rather than trying to build something custom. Custom tools tend to be under-validated and over-complicated. The Morse scale alone took decades of research to reach its current form. There's no shortcut around that validation work.