So you want to get into healthcare fast
The Bureau of Labor Statistics compiles this data every year, and the patterns are pretty consistent if you know where to look. The fastest growing careers in healthcare tend to cluster around three things: aging population demand, technology integration, and scope-of-practice expansion for mid-level providers. Most people pick their path based on a job posting title without understanding what the actual day-to-day work looks like, which is why roughly half of career changers leave the field within two years. I spent about seven years working in hospital staffing and credentialing, and the thing that consistently trips people up isn't the education part. It's the licensing timeline. A lot of candidates think they can complete a program and start working immediately. That almost never happens. There are background checks, state board verifications, privileging committees, and orientation periods that can stretch four to six months after graduation depending on the facility and state. Plan around that or you will be sitting on unpaid income for longer than you expect.
Fastest Growing Careers In Healthcare
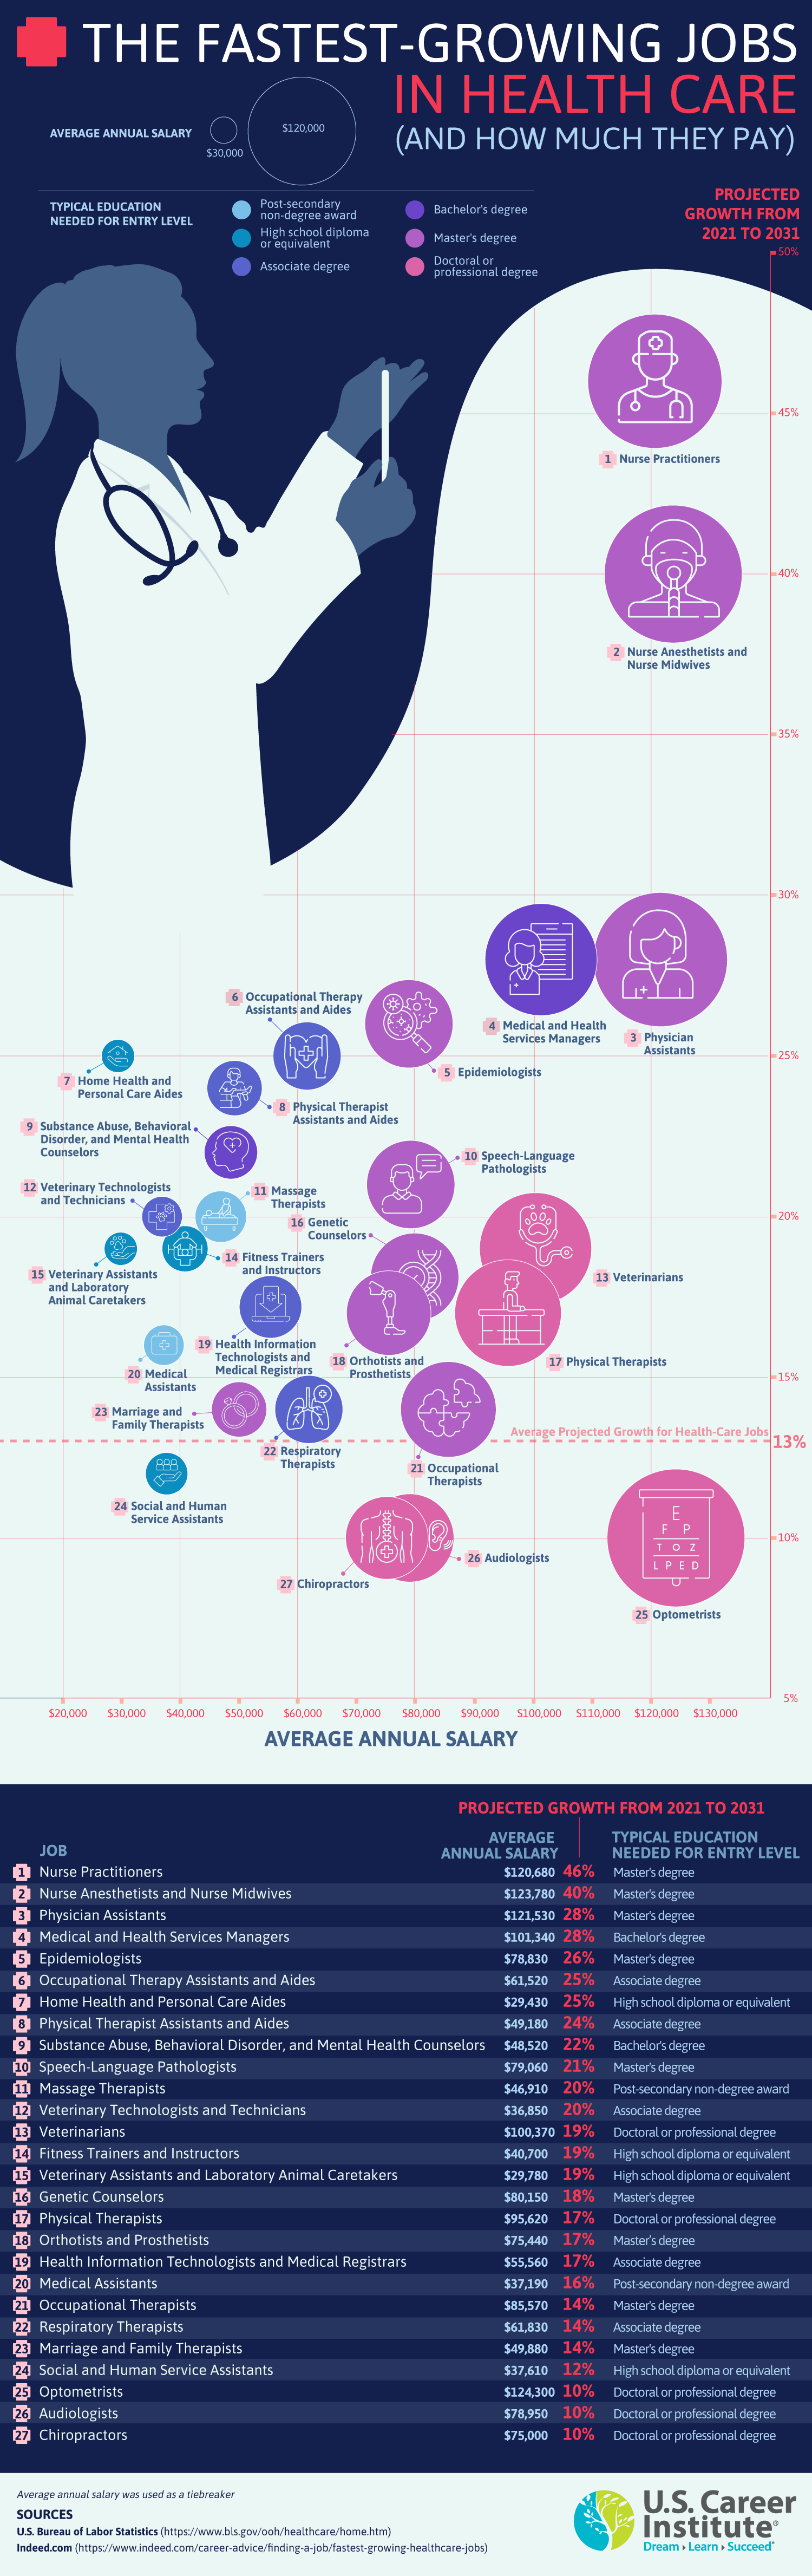
Here is what the current data actually shows, broken down by what you need to do to get there and what the realistic timelines look like. Nurse Practitioners — Projected growth around 40-45% through 2032. Requires a Master of Science in Nursing or a Doctor of Nursing Practice, plus passing a national certification exam in your population focus. The total pipeline from RN to NP is typically 2-4 years depending on whether you do an accelerated BSN-to-DNP or go the post-master's certificate route. One thing nobody tells you: some states require a collaborative physician agreement before you can practice independently, and finding a physician willing to sign that in rural areas is genuinely difficult. Urban markets are less restrictive on that front. Medical and Health Services Managers — Projected growth around 28-32%. This is the administrative side. You do not need a clinical license. A bachelor's degree gets you in the door at smaller facilities, but most competitive positions at mid to large hospitals now list a Master's in Health Administration as preferred, sometimes required. The counter-intuitive part here is that clinical experience actually helps more than a general business MBA. I had a candidate once who completely ignored this and went straight for an MHA with no healthcare background. They spent eighteen months applying to entry-level coordinator roles before anything materialized. Another candidate with three years as a medical assistant and a targeted bachelor's got an assistant manager position within six months of graduating because they could speak the language of the floor staff.
Statisticians and Data Scientists in Healthcare — This category has exploded. Growth rates vary by source but consistently rank in the top tier. You need strong quantitative skills, preferably a master's in biostatistics, epidemiology, or health informatics. The practical reality is that pure data science credentials alone are not enough. You need to understand clinical workflows, EHR systems, and regulatory constraints like HIPAA. I hired a candidates once who had an impressive GitHub portfolio and zero healthcare domain knowledge. They could build a model but had no idea why a clinician would never trust it in practice. Took about three months of paired work before they produced anything usable. The ones who move fast here are people who already have healthcare exposure and add the technical layer on top. Physical Therapist Assistants — Projected growth around 25%. Two-year associate degree from an accredited program, plus a state licensure exam. Shorter training than PTs but the pay ceiling is noticeably lower. The catch is that PTA scope of practice varies significantly by state. Some states allow direct access without physician referral, others require ongoing physician supervision. Check your state board before enrolling in a program, because the curriculum can differ based on those constraints. Medical Lab Scientists — Growth around 21-23%. Bachelor's degree, often a NAACLS-accredited program, plus ASCP or equivalent certification. The hidden advantage here is location flexibility. Every hospital needs a lab. You are not competing against someone who happens to live near a big metropolitan center. Smaller community hospitals and reference laboratories in mid-sized cities often struggle to fill these positions and will sponsor relocation. The downside is shift work. Night and weekend rotations are standard in most lab environments, and it impacts your social life whether you admit it or not.
Get the Full Details

Home Health Aides and Personal Care Aides — Projected growth around 22-25%. Training is measured in weeks, not years. State requirements vary but many are 75-120 hours of supervised training. The pay is low, the turnover is high, and the demand is real. People avoid this path because the compensation does not reflect the growth projection, but if you need to be working within three months and you do not care about the salary ceiling, this is the shortest path to a paycheck in healthcare.
How to actually pick the right one
The biggest mistake I see is people optimizing for growth rate alone. A career with 45% growth that requires eight years of training and $150,000 in debt is a different calculation than one with 25% growth and a two-year associate degree. Run the numbers yourself. Factor in tuition, lost wages during training, certification exam fees, and the realistic timeline from enrollment to first paycheck. The gap between when you start a program and when you receive your first salary check is usually six to twelve months longer than program brochures suggest. Another factor that gets ignored is the licensing jurisdiction. Healthcare licenses are state-specific in almost every category. If you complete your training in Texas and your family moves to New York, you are looking at a credential evaluation process that can add four to eight months and cost several hundred dollars. Some states have reciprocity agreements, most do not. Verify this before you apply to a program. Here is the thing most guides will not tell you about the data scientist track in healthcare: the entry-level job market is more saturated than the growth numbers suggest. Every bootcamp graduate is applying to the same postings. The people who actually land roles are those who can demonstrate they have worked with real clinical data, not just public datasets. If you can get experience through a healthcare employer in any capacity, even as a medical scribe or clinical data entry specialist, and then pivot internally into a data role, your odds improve dramatically. I watched two candidates with identical credentials get hired for the same department. One had six months of clinical data entry experience. The other did not. The difference was not subtle.
If you are already in healthcare and looking to pivot internally, shadowing is more useful than you might think. A single week observing a nurse practitioner in an outpatient clinic will tell you more about whether that role suits you than any career assessment quiz. The work is less glamorous than most people assume. Lots of documentation, frequent interruptions, and the emotional labor of delivering difficult news is built into the daily routine. But the compensation and autonomy are substantially better than many entry-level clinical roles, which is why the growth is so high. The regulatory environment changes frequently. Scope-of-practice laws get revised, certification requirements shift, and new specialized roles emerge regularly. The data I am referencing is based on projections that assume current policy conditions hold. If you are making a multi-year commitment, budget for the possibility that your target role may evolve differently than expected. The field adapts faster than most people anticipate.