What You Actually Need to Know Before Buying a Light Therapy Device for Dry Eyes
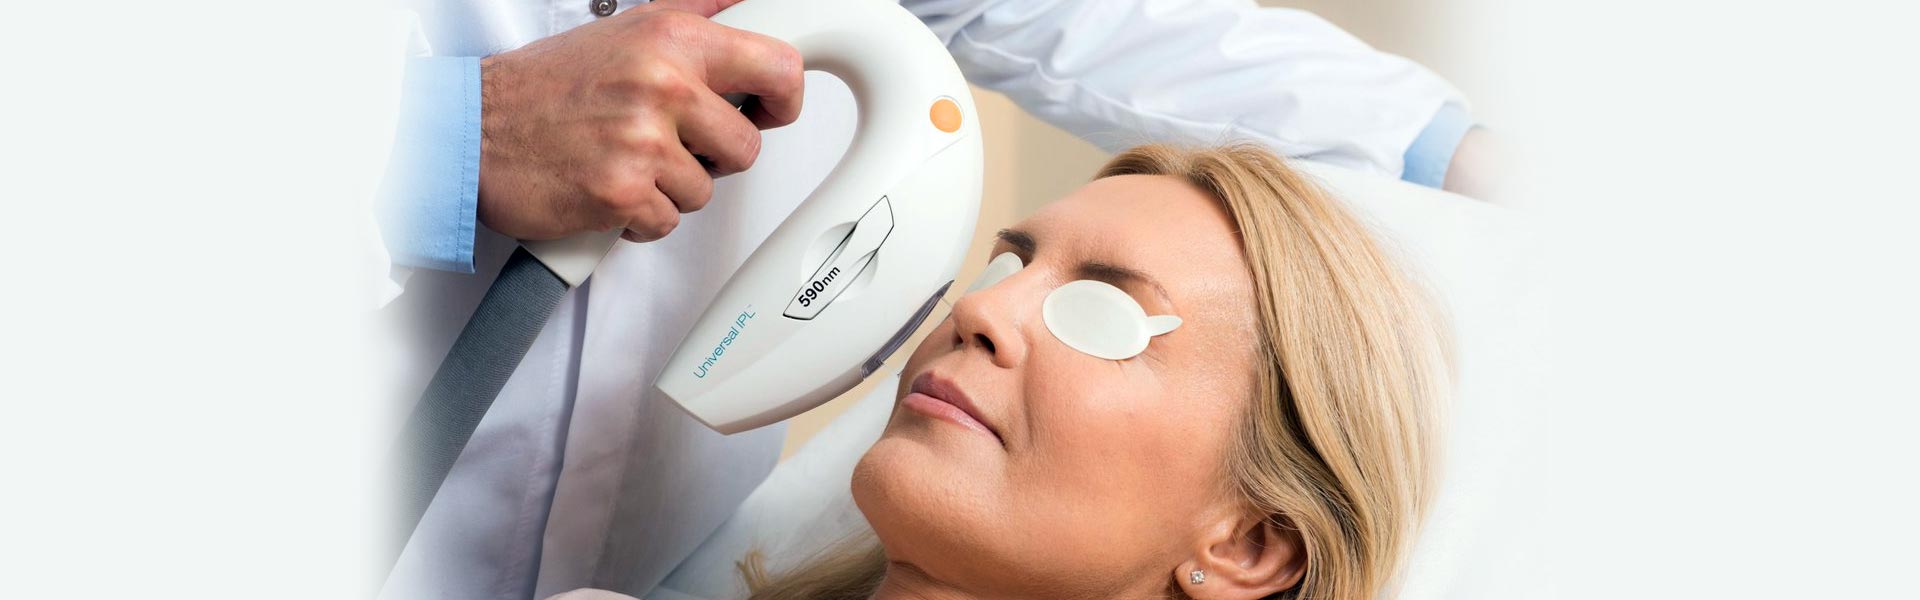
Intense pulsed light (IPL) therapy has been around for ophthalmology for a while now. The FDA cleared the first device specifically for meibomian gland dysfunction — the most common cause of evaporative dry eye — back in 2019. Since then, a handful of other systems have followed. If you've been recommended IPL by your eye doctor or you're researching it on your own, the landscape is messier than the marketing materials suggest. IPL works by targeting the abnormal blood vessels around the eyelid margin and the periorbital skin. These dilated vessels carry inflammatory mediators into the meibomian glands. When you reduce that inflammation with controlled pulses of broad-spectrum light, the glands can start producing healthier oil again. The heat from the light also temporarily softens the obstructing secretions, which is why manual expression usually follows each pulse. A typical course involves four sessions spaced about three to four weeks apart, with maintenance sessions every few months after that. The devices that carry FDA clearance are almost exclusively intended for use by trained medical professionals in clinical settings. You won't find an FDA-approved home unit for IPL. The Atomy Mela no.6 and similar LED masks you see on Amazon use low-level light, not intense pulsed light, and they don't have the same FDA designation for dry eye treatment. There's a meaningful difference between the two, and confusing them is a common mistake.
One thing nobody tells you: IPL is not a first-line treatment for everyone. If your dry eye is purely aqueous-deficient — meaning your lacrimal glands aren't producing enough water — light therapy won't do much. It only addresses the meibomian gland side of things. I worked with a patient last year who had been told she was a good candidate based on a quick screen. She'd already done two rounds of preservative-free artificial tears and a topical cyclosporine without relief. After imaging, it turned out her gland dropout was minimal and her issue was almost entirely inflammatory and aqueous. We paused the IPL talk and shifted to a combination of punctal plugs, an oral doxycycline course, and lid hygiene. Her comfort improved in about six weeks. She'd been wasting time and money otherwise. The other nuance is skin tone. The light energy is absorbed by melanin, which means patients with darker skin tones (Fitzpatrick IV through VI) carry a higher risk of post-inflammatory hyperpigmentation or burns if the settings aren't adjusted carefully. Most clinics use cooler fluences or skip IPL altogether for these patients, opting instead for thermal pulsation devices like LipiFlow, which don't rely on melanin absorption. It's not a dealbreaker, but it's something to ask about before committing to a full course.
How the Treatment Actually Goes
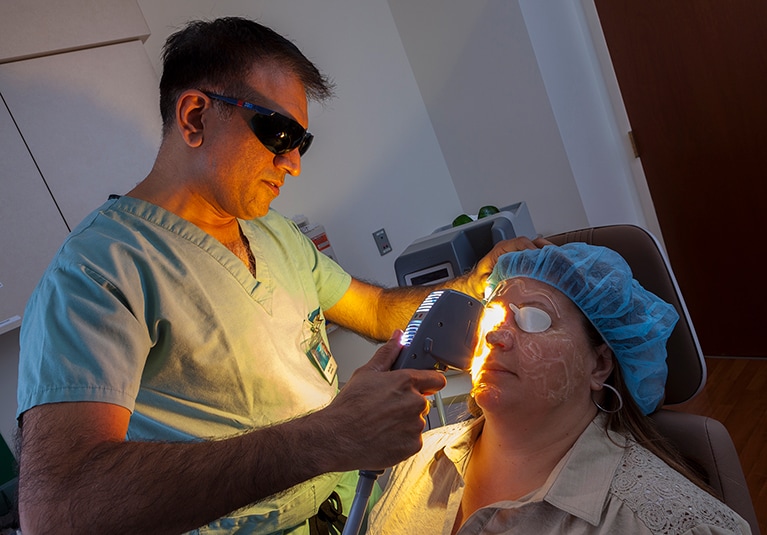
You'll arrive with a clean face. No makeup, no sunscreen, no creams near the eyes. The technician places protective shields over your eyes and applies a conductive gel to the lower eyelid and cheek area. Each pulse lasts about half a second. You feel a sharp warmth — sometimes described as a rubber band snap against the skin. The number of pulses per session typically ranges from 15 to 30 per side, depending on the device and your skin response. The whole appointment takes about 20 to 30 minutes. Immediately after, your eyes will be watery and your eyelids may look slightly flushed. This is normal and subsides within a few hours. Most people drive themselves to and from the appointment. You'll be asked to apply cold compresses for ten minutes afterward and to avoid heavy exercise, saunas, or hot yoga for 48 hours. The expression part comes right after the light — the technician presses along your eyelid margins with specialized tools to clear out the softened meibum. Some clinics include photobiomodulation or red-light therapy as an adjunct to further reduce inflammation. That's a separate mechanism and not part of the core IPL process. Results aren't immediate in the sense that you'll feel dramatically better after the first session. Most patients notice a gradual improvement over two to three treatments. A study published in the Journal of Clinical and Experimental Ophthalmology found that approximately 70 to 80 percent of patients with moderate to severe MGD reported significant improvement after a complete four-session course. But "improvement" here usually means reduced dependence on artificial tears and less burning in the morning. It doesn't mean you'll never need drops again.
Get the Full Details

What You Should Expect About Cost and Access
Each session typically runs between $200 and $600 depending on location and provider. Many clinics package the four-session course at a discounted rate, bringing the total to somewhere in the $800 to $2,000 range. Insurance rarely covers it because the FDA coding for dry eye and the FDA coding for IPL came from different indications. Some practices offer financing through third-party programs. If cost is a concern, ask whether they have a demonstration or trial session before you commit to the full bundle. Not all eye doctors offer it. Ophthalmologists who specialize in cornea and external disease are the most likely to have the equipment, but many optometrists with a dry eye focus now carry it as well. If you're unsure whether your provider is experienced, ask how many courses they've completed and what their typical follow-up protocol looks like. A provider who does twelve courses a year will give you a noticeably different result than one who brings the machine out occasionally.
Common Pitfalls and Realistic Limitations
The biggest issue I see is patient selection. People walk in expecting a cure. It's a management tool, not a cure. If you have advanced gland atrophy where the glands have physically disappeared, light therapy can't regenerate them. It can only improve the function of glands that are still there but inflamed or obstructed. Lipid screening or meibography should always precede treatment to confirm you have recoverable glands. Another pitfall is stopping too early. Four sessions is the standard protocol, but some patients feel good after two and cancel the rest. The anti-inflammatory effect builds cumulatively. Stopping at session two often means the improvement plateaus and then fades within a couple of months. If you commit to the course, commit to the course. Maintenance sessions every three to six months are usually needed to sustain results. There's also a rare but real complication I want to flag. I once encountered a patient who developed a small area of telangiectasia — permanently visible dilated capillaries — on her cheek after a session where the fluence was set too high for her skin type. It was subtle but permanent. This is why choosing an experienced provider matters more than choosing the cheapest option. The technology is safe when used correctly, but it's not harmless by accident.
Alternatives exist if IPL isn't right for you. Thermal pulsation (LipiFlow or iLux) applies heat directly to the glands from both the inside and outside of the eyelid without using light energy on the skin. Brimidine is a newer prescription drop that targets inflammation differently than cyclosporine. For severe aqueous deficiency, autologous serum drops or a scleral lens can provide relief that light therapy simply can't. The best approach usually combines more than one modality rather than relying on a single treatment.