Understanding the Current State of TCR-Based Cancer Therapies
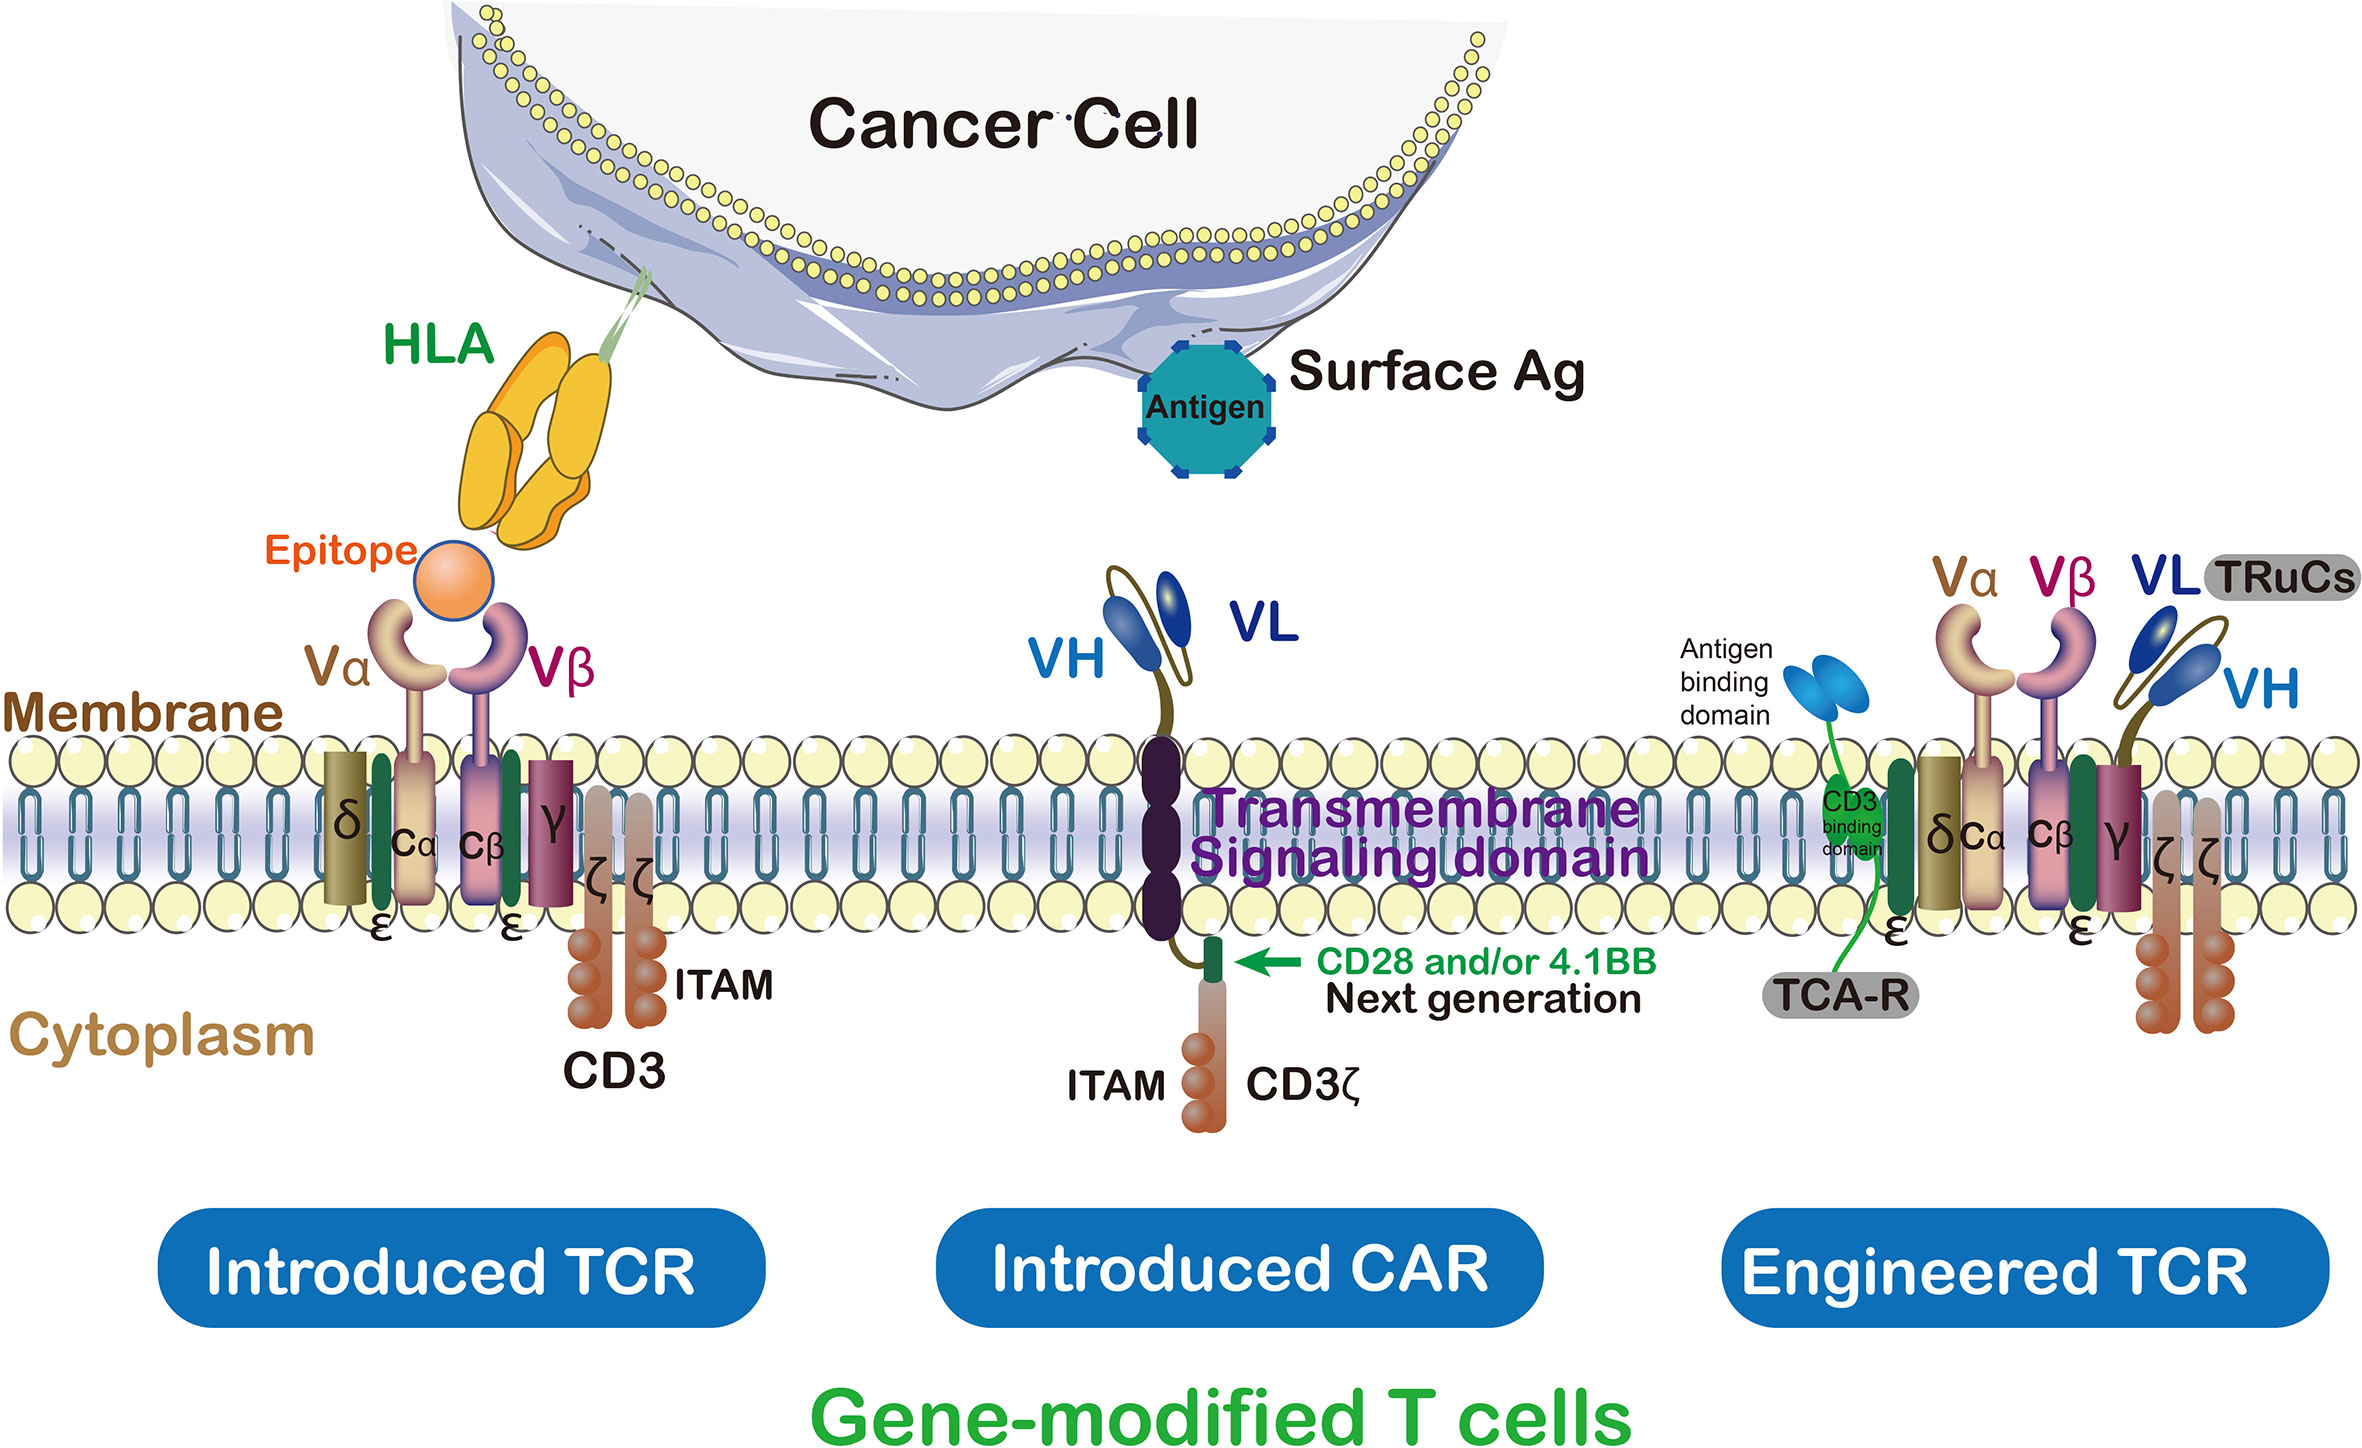
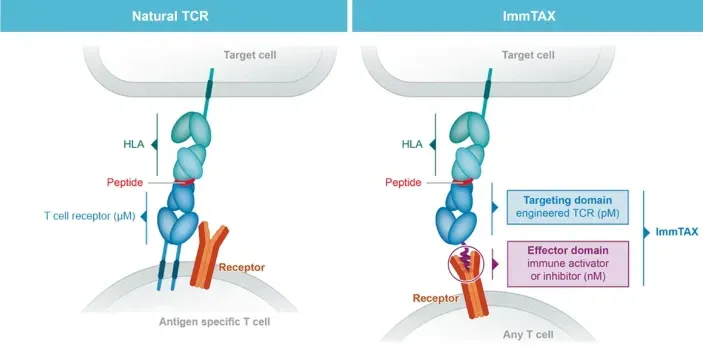
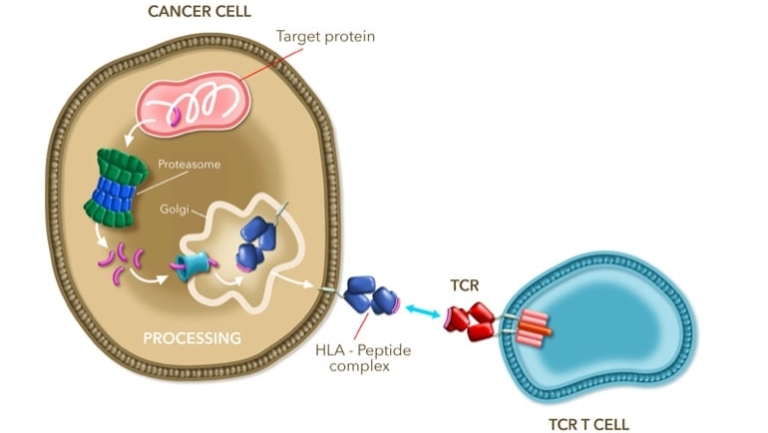
TCR stands for T-cell receptor, and TCR therapy is a form of adoptive cell therapy where patient T-cells are genetically modified to express receptors that recognize specific tumor antigens. Unlike CAR T-cell therapy, which adds receptors that bind surface antigens independently of MHC, TCR therapy enables recognition of both intracellular and surface antigens presented through MHC molecules. This is a meaningful distinction because it expands the range of druggable targets beyond what surface-only binding allows. The landscape here is narrower than most people expect. As of my last review, there are very few TCR therapies with full FDA approval compared to the growing number of CAR T-cell products. The FDA has approved several CAR T therapies — Kymriah, Yescarta, Tecartus, Breyanzi, Abecma, Carvykti — but these are all CAR-based, not TCR-based. A TCR-T therapy targeting NY-ESO-1 (beremagene geperpavec and related programs) has received approval in Japan and conditional approval pathways exist in other regions, but FDA approval for a dedicated TCR-T product remains an active area of regulatory review rather than settled ground. There is also talimogene laherparepvec (T-VEC), an oncolytic herpes virus approved for melanoma, which engages T-cells but is not classified as a TCR therapy in the genetic engineering sense. People frequently conflate these categories because they fall under the broad umbrella of immuno-oncology. They are mechanistically distinct.
For the record, if you are looking at clinical trials, the major ongoing TCR-T programs include ones targeting NY-ESO-1, KRAS mutants, and MART-1 across melanoma, sarcoma, and lung cancer indications. These are mostly Phase 2 or Phase 3 at this point. The pipeline is real. The approvals are not yet widespread in the United States.
How TCR Therapy Actually Works in Practice
The process starts with a leukapheresis procedure that collects the patient's T-cells. These cells are then shipped to a manufacturing facility where they are transduced with a retroviral or lentiviral vector carrying the gene for a tumor-specific TCR. The modified cells are expanded over roughly two to three weeks before being frozen and shipped back. The patient receives lymphodepletion chemotherapy — typically fludarabine and cyclophosphamide — followed by infusion of the engineered T-cells. The key technical detail that most summaries skip is HLA matching. Because TCRs recognize peptide-MHC complexes, the patient must be positive for the specific HLA allele that presents the target antigen. A patient who is HLA-A02 negative cannot receive a TCR targeting an A02-restricted epitope, period. This restricts the eligible population significantly. In my experience reviewing trial data, approximately 30 to 40 percent of patients with a given cancer type will be HLA-compatible for any single TCR target. Another practical detail: the manufacturing process is not trivial. I worked through a case where the T-cell expansion failed due to a poor baseline CD4-to-CD8 ratio in the apheresis product. The lab had to extend the culture period and supplement with additional cytokine stimulation. It added eight days to the timeline and the final product had reduced central memory phenotype markers, which likely affected durability. This is not a common failure mode, but it is real and it matters when you are dealing with heavily pretreated patients whose cells are already exhausted.
Get the Full Details

Common Misconceptions and Where the Data Falls Short
One persistent misunderstanding is that TCR therapy is interchangeable with CAR T-cell therapy. They share a delivery model — autologous cell engineering, lymphodepletion, infusion — but their target spaces and failure modes differ substantially. CAR T-cells can target undocumented surface proteins and do not require HLA matching. TCRs can access intracellular targets but are constrained by HLA type and can cause off-target reactivity if the chosen TCR cross-reacts with healthy tissue expressing the same peptide-MHC complex. The gravest risk specific to TCR therapy is on-target off-tumor toxicity. If the target antigen is expressed at low levels on normal tissue, the engineered T-cells will attack it. This has been observed in early trials with TCRs targeting NY-ESO-1, where severe pneumonitis occurred in a small number of patients. It is rare but serious enough that manufacturers include extensive monitoring protocols in their investigational new drug applications. Another hard truth: response rates are not uniform. In melanoma trials, objective response rates for TCR-T therapy targeting NY-ESO-1 have hovered around 25 to 30 percent in heavily pretreated populations. That is meaningful for patients who have exhausted standard options, but it is not a cure rate. Some responders maintain durable remissions. Others relapse within months, often through antigen loss or MHC downregulation — mechanisms that allow the tumor to escape TCR recognition entirely.
If you are evaluating this for a clinical decision or a research project, the most practical approach right now is to look at ongoing clinical trials rather than approved products. The FDA has not yet granted full approval to a TCR-T therapy for any indication in the United States. You can search ClinicalTrials.gov using terms like "TCR-T," "gene-edited T cells," and the specific antigen target you are interested in. Most of these trials provide free screening for HLA compatibility, which is the first gatekeeper step. The technology is advancing. Gene editing approaches using CRISPR to knock out endogenous TCR chains and HLA class I are reducing rejection risk and allowing off-the-shelf allogeneic products. These are still in early-stage trials. But the direction is clear. The gap between where TCR therapy is and where it could be in the next few years is substantial.