What actually moves the needle in feeding therapy
Most people walking into a feeding clinic have been at this for months. The kid tolerates purees but won't touch anything with texture. Or they sit at the table, refuse every bite, and meltdown happens somewhere around fork number three. I've been doing this long enough to stop being impressed by the textbook models and focus on what actually changes behavior at the table. Feeding Therapy Techniques aren't one protocol you apply and walk away from. They're a collection of evidence-based strategies pulled primarily from applied behavior analysis, sensory integration frameworks, and pediatric OT principles. The real work is in sequencing them so the child isn't overwhelmed at any single step.
Core Feeding Therapy Techniques That Actually Work
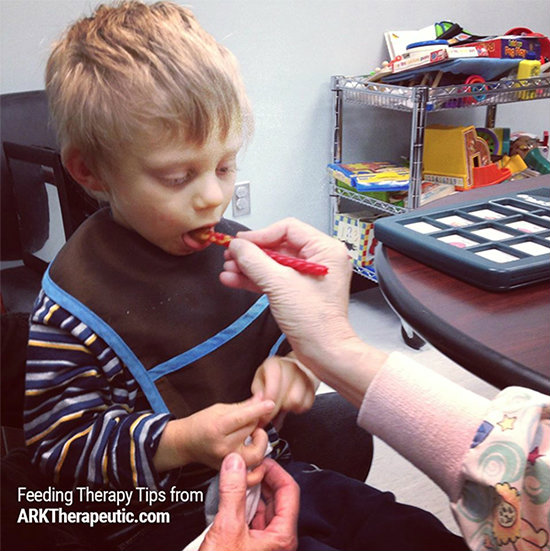
Let me walk through the ones I reach for most often, in roughly the order I use them. Sensory desensitization comes first for the kids who gag at the sight of food. This isn't about forcing them to eat. It's about building tolerance through non-contingent exposure. A child sits at the table with a plate that has a single pea on it. They don't have to touch it, taste it, or acknowledge it. The therapist just leaves it there across multiple sessions while doing something neutral like reading a book aloud. Over maybe six to eight sessions, the presence of the food loses its threat value. I've seen timelines stretch to twelve weeks with highly reactive kids, and honestly that's fine. The alternative is rushing and resetting the whole process back to zero. Systematic desensitization builds on that foundation. Now you introduce a food ladder. The ladder is constructed from the child's current accepted foods and extended one attribute at a time. If they accept smooth apple sauce, the next step might be applesauce with a tiny bit of pulp mixed in. Not diced apples. Not a raw slice. One attribute changed, tested, accepted or rejected, before moving forward. The key insight most beginners miss is that the ladder shouldn't be pre-built by the therapist. It has to be built with the child present, testing each step live. A ladder that looks logical on paper will fall apart the moment a kid refuses step three because the color changed slightly.
Food chaining is where this gets practical. You identify the child's current accepted foods and chain from there by changing one property at a time. Accepted: plain white rice. Chain: add a tiny pinch of salt. Then a trace of butter. Then a spoon of plain pasta. Then pasta with a little marinara on the side. Each link in the chain is a new food that shares 90 percent similarity with the previous one. I once worked with a seven-year-old who only ate chicken nuggets from a specific fast-food chain. We spent three weeks chaining from that exact nugget to a different brand, then to breaded chicken strips, then to plain grilled chicken cut into the same shape. The entire chain took about six weeks. The parent wanted faster results, but going quicker would have meant the child regressed. It usually takes between four and eight weeks per successful chain depending on the child's flexibility threshold. Positive reinforcement is the engine, but most people use it wrong. The mistake is reinforcing the eating instead of the approach. If a child puts a bite in their mouth and you give them iPad time, you're teaching them that eating is the transaction, not exploring. The reinforcement should target the behavior you want repeated: touching the food, smelling the food, licking the food, accepting a smaller bite. The actual swallowing is the final step, and it should come naturally, not be bargained for. I've seen therapists accidentally create food hoarders by using high-value rewards contingent on swallowing. The kid learns to hold food in their mouth for twelve minutes rather than ever trying new textures. Fixing that takes a separate protocol entirely. Parent-mediated intervention changes outcomes more than anything else I've seen. A therapist seeing a family once a week for forty-five minutes has almost no impact compared to the hours the family actually spends at meals. The evidence is clear: when parents are trained in the techniques and implement them consistently during regular meals, progress accelerates significantly. The challenge is making sure the parent doesn't accidentally undermine the work by giving in to demands or using food as a comfort tool outside of structured sessions.
Get the Full Details
The edge case nobody talks about
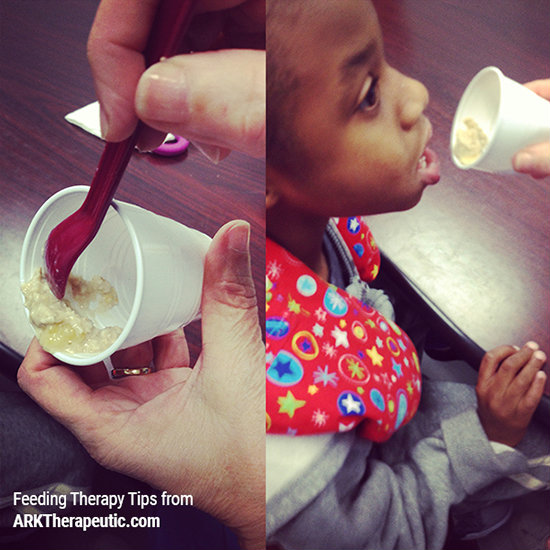
Here's a specific problem I ran into last year that made me reconsider how rigidly I was applying the food ladder approach. I had a nine-year-old who accepted twenty-three different foods, all of them carb-heavy and beige. The standard protocol would have been to build a ladder from his accepted foods and expand from there. That took about three weeks with zero expansion. He'd touch the new food, then immediately gag on his own saliva. Not because of the food. Because the act of touching it triggered an oral motor response that felt threatening to him. The workaround was to skip the food ladder entirely and go straight to oral motor desensitization using non-food tools. A silicone tooth picker. A small vibration massager on the cheeks and gums. A textured lip brush. We spent two full sessions just doing facial massage and oral motor play with zero food present. Then we reintroduced food only after his oral sensory threshold had visibly shifted. He accepted his first textured food four sessions later. The standard approach would have burned four to six weeks on a ladder that wasn't going anywhere. Sometimes the gatekeeper isn't the food. It's the oral motor system itself.
What doesn't work and when to pivot
Forced feeding works about as well as you'd expect. It produces compliance in the moment and increases avoidance behavior long-term. There is almost never a clinical scenario where it's appropriate. If a therapist recommends it, find a different therapist. Empty plates with no accepted foods to chain from are a bottleneck. I've had parents bring in a kid who accepts only baby food jars and ask what to do next. The answer is to first build acceptance of spoon-fed mashed foods using texture variation within that category, then move to soft finger foods, then to the ladder. Jumping from jarred puree to family meals is like trying to run before you can walk. It's not motivational. It's just a guaranteed meltdown. Some children with oral motor delays, severe autism, or gastroesophageal reflux will not make progress through behavioral feeding therapy alone. In those cases, the feeding therapist should be referring out to a speech-language pathologist for oral motor assessment, or to a GI specialist for medical evaluation. Pushing a behavioral protocol on a child whose gag reflex is physiologically heightened is like trying to fix a leaky pipe with duct tape. It might look like it's working for five minutes.
The timeline is another area where expectations need recalibrating. A typical feeding therapy case involving moderate picky eating and texture refusal runs eight to twelve weeks with weekly sessions and consistent home practice. Severe cases with multiple rejected food groups and established mealtime conflict can take six to eighteen months. If a program promises results in two weeks, they're selling something else.

What to look for in a competent feeding therapist
A BCBA with feeding specialization, an SLP with pediatric feeding certification, or an OT trained in sensory integration and oral motor therapy. Ask about their typical session structure, their home program requirements, and how they handle regression. The best therapists will tell you exactly what will go wrong before it goes wrong. That's not pessimism. That's experience. The techniques I've outlined here are grounded in published research from the Journal of Applied Behavior Analysis, the American Journal of Speech-Language Pathology, and the research base behind ABCs of Feeding and the Spaghetti Bowl method. But the research only tells you what works on average. The actual execution, the reading of the child's signals, the decision to push or retreat on any given bite, that's where the skill lives. It's harder than it looks and it requires more patience than most parents are prepared to give themselves.



