Reproductive System Functionality in Practice
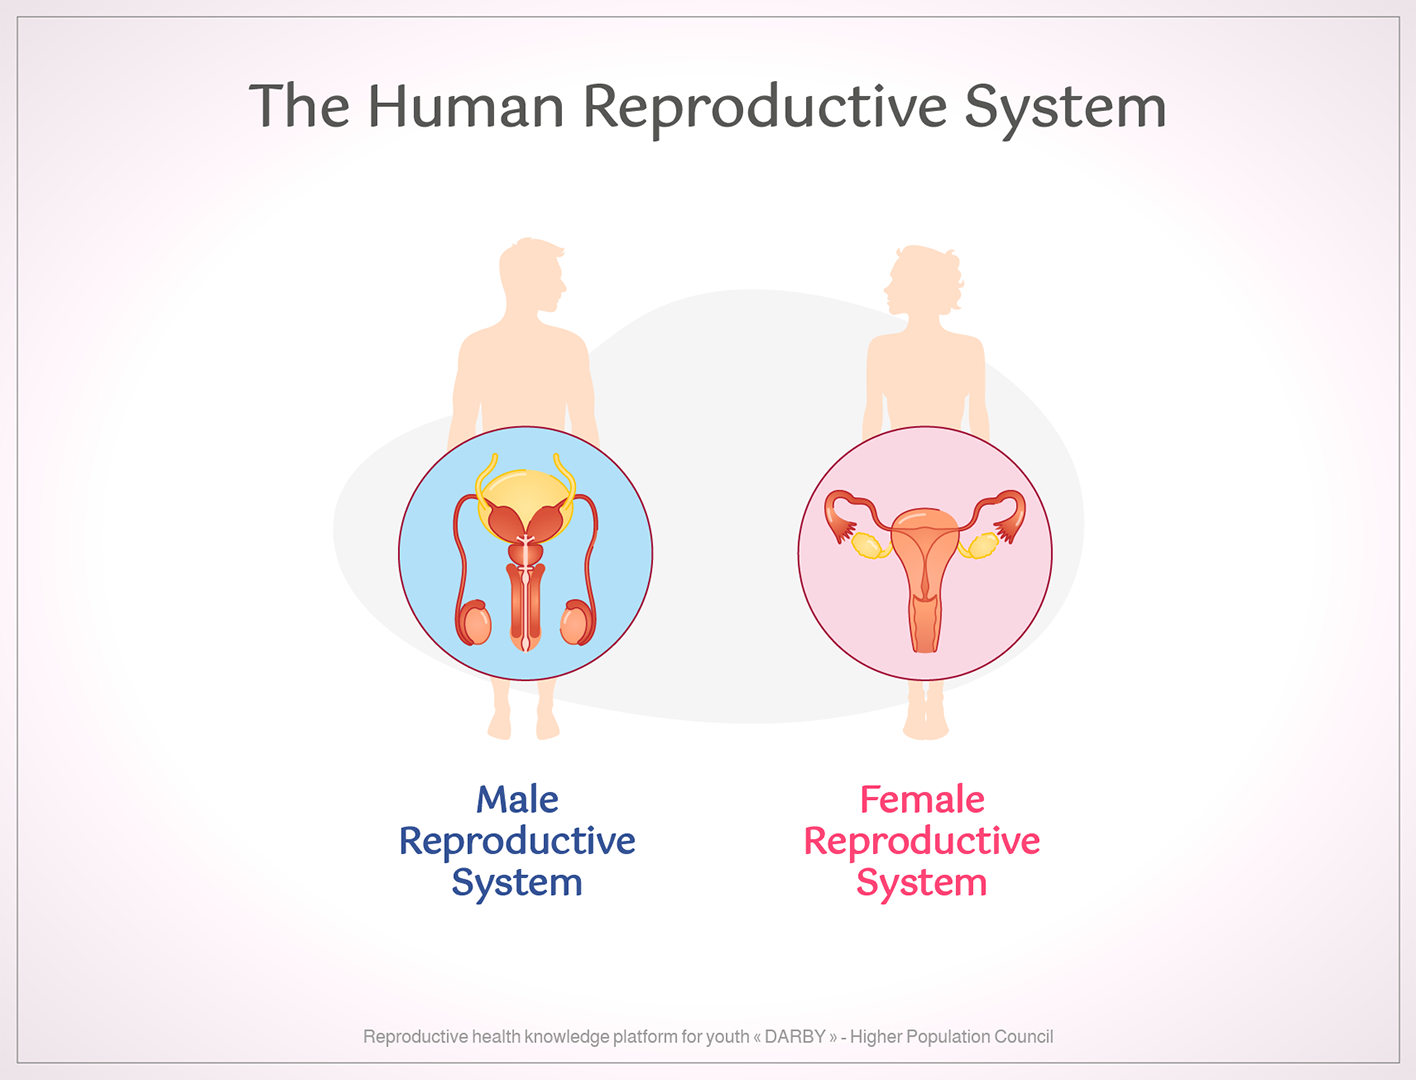
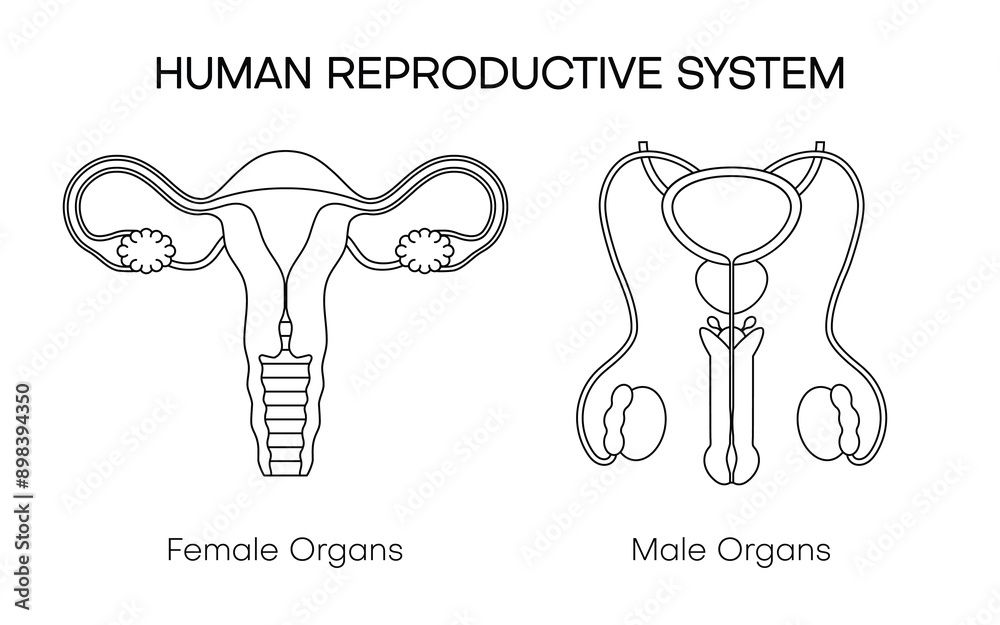
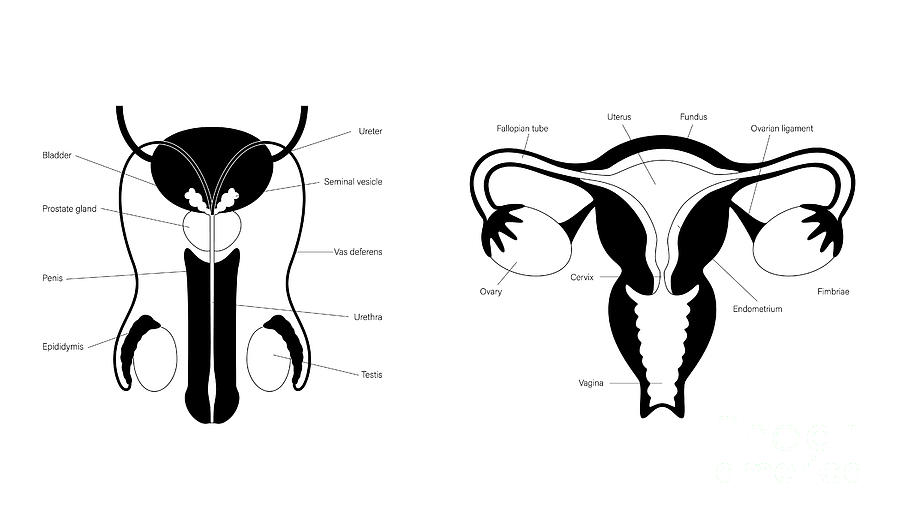
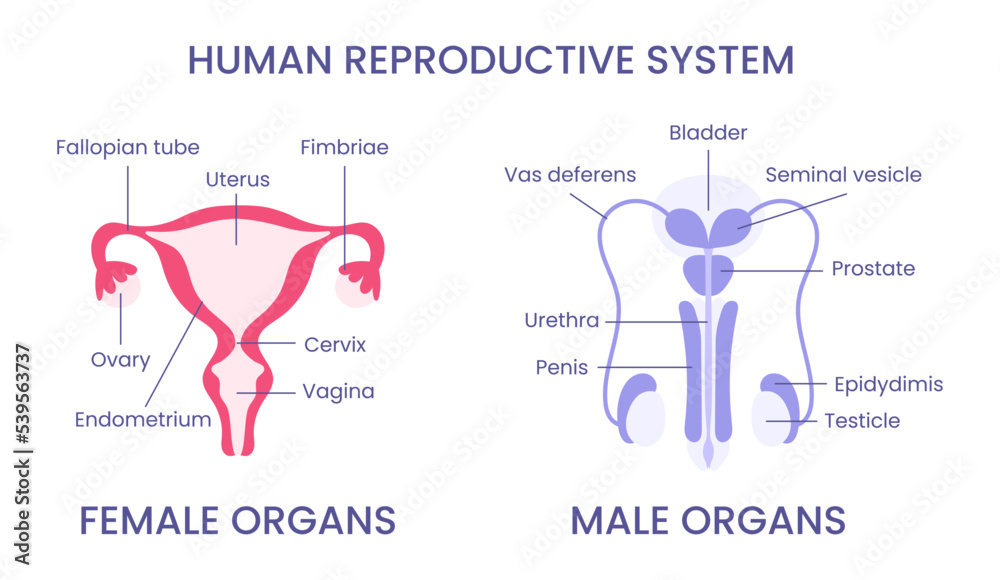
The human reproductive system operates through a series of hormonal feedback loops that most people don't actually understand, even though they've been taught about it in high school biology. I spent several years working in a clinical fertility lab, and what I learned there was significantly different from what gets taught in textbooks. The Female And Male Reproductive systems are often discussed separately in education, but they share surprising physiological parallels that become obvious once you understand endocrinology at a deeper level.Let me start with something most people get wrong about spermatogenesis. The common understanding is that sperm production happens continuously once puberty begins, which is technically true but misses the entire point about timing and variability. A single spermatogenic cycle takes approximately 64 to 72 days in humans, meaning any environmental stressor, illness, or medication change you experience today won't show up in your semen analysis until roughly two and a half months later. I had a patient in 2019 who was furious when his sperm count dropped after a bout of influenza. He couldn't understand why a two-week fever was destroying his numbers months later. Explaining the timeline to him did very little to calm his anxiety, but understanding that delay is probably the single most useful piece of knowledge for anyone tracking their reproductive health. The hypothalamic-pituitary-gonadal axis works almost identically in both sexes. The hypothalamus releases gonadotropin-releasing hormone in pulsatile fashion, the pituitary responds by secreting follicle-stimulating hormone and luteinizing hormone, and the gonads produce sex steroids. The difference isn't in the architecture, it's in the downstream effects and the negative feedback patterns. In males, testosterone provides negative feedback primarily at the pituitary level on LH secretion and at the hypothalamus on GnRH pulses. The system is designed for steady-state output with modest fluctuation. Semen quality varies day to day but the baseline remains relatively stable throughout adult life, though it does decline gradually after age 35 to 40. Free testosterone decreases roughly one percent per year after thirty, and sex hormone-binding globulin increases over the same period, which means total testosterone might look normal while free testosterone drops.
In females, the feedback loop is far more dynamic. Estrogen switches from negative to positive feedback depending on its concentration and duration. Low-to-moderate levels suppress gonadotropins, but sustained high estrogen around mid-cycle flips the switch and triggers the LH surge that causes ovulation. This is not a minor distinction. It's the reason why women can ovulate on certain days and not others, and it's also why hormonal contraception works the way it does—by maintaining a constant exogenous hormone level that keeps the hypothalamus and pituitary locked in negative feedback mode. I once worked through a case involving a woman who was having irregular cycles despite taking her birth control pill consistently. She was using a generic formulation of ethinyl estradiol and levonorgestrel, and she reported perfect adherence. The issue turned out to be that she was also taking rifampin for a urinary tract infection, which induces CYP3A4 enzymes and accelerates the metabolism of the contraceptive steroids. Her hormone levels were subtherapeutic, her negative feedback was breaking down, and her pituitary was firing LH and FSH pulses again. This interaction between antibiotic metabolism and oral contraceptive efficacy is something that rarely gets emphasized in patient education materials, and it's one of those edge cases that can waste weeks of someone's time if you're not looking for it.
Practical Considerations Around Fertility Tracking
Basal body temperature charting has a reputation for being unreliable, and honestly, it's mostly deserved if you're using it alone. The post-ovulatory temperature rise is real—typically a shift of about 0.3 to 0.5 degrees Celsius—but it only confirms that ovulation already happened. By the time you see the temperature elevation, the fertile window has closed. The practical application here is retrospective confirmation, not forward prediction. I'd recommend combining it with cervical mucus observation, which actually gives you a predictive signal since fertile-quality mucus appears one to two days before ovulation. For men tracking fertility, semen analysis parameters have changed significantly over the past decade. The World Health Organization revised its reference values in 2021, lowering the normal sperm concentration threshold from 15 million per milliliter to 16 million per milliliter and adjusting total motility expectations. These changes reflected a broader understanding of population-level trends rather than arbitrary revision. Sperm concentration has been declining globally at an estimated rate of roughly one percent per year since the 1970s, according to a major meta-analysis published in 2017. That trend matters because it means the reference ranges that clinicians use were established on populations that may no longer represent the current baseline. When I helped a colleague set up a basic at-home semen testing protocol for a research study, we found that even with strict abstinence periods and proper collection techniques, the coefficient of variation between consecutive samples in the same individual was around 30 to 40 percent. That's a huge variance. A single semen analysis is essentially a snapshot. Two or three samples collected at least three weeks apart give you a much more reliable picture. Most clinics do one test and call it definitive, which I think is lazy and occasionally misleading.
Get the Full Details

Common Pitfalls in Understanding Reproductive Physiology
One persistent misconception I encounter repeatedly is the idea that reproductive health is purely a biological question. It isn't. Stress, sleep quality, and psychological state all exert measurable effects on both axes. In women, severe caloric restriction or excessive exercise can suppress GnRH pulsatility enough to cause functional hypothalamic amenorrhea. I've seen competitive athletes miss periods for months despite having no structural abnormality. In men, chronic psychological stress elevates cortisol, which dampens GnRH and LH output and can reduce testosterone production in the Leydig cells. The effect is usually moderate but real, and it gets overlooked because nobody tests cortisol alongside a standard androgen panel. Another thing people don't appreciate is the role of the blood-testis barrier. Sertoli cells form tight junctions that create an immune-privileged environment inside the seminiferous tubules, keeping developing sperm isolated from the immune system. If this barrier breaks down—due to infection, trauma, or surgery—anti-sperm antibodies can develop and attack sperm motility and function. This is a well-documented cause of unexplained male infertility, and standard semen analysis won't necessarily flag it. You need a specific antibody test, which most general practitioners don't order unless they've exhausted the more obvious explanations first. On the female side, the luteal phase is another area where assumptions cause real problems. The textbook says the luteal phase is a consistent 14 days, but in practice it ranges from about 9 to 16 days across healthy women, and it can vary from cycle to cycle in the same person. A short luteal phase of less than 10 days can impair implantation because the endometrium isn't properly primed by progesterone for long enough. Women who struggle with early miscarriage sometimes have this issue, and it's treatable with progesterone support, but it requires recognizing the pattern through cycle tracking rather than waiting for a clinic visit.
The reproductive system is a network of interconnected feedback loops, not a set of independent parts. Understanding how those loops work in practice—the delays, the variances, the interactions with medications and lifestyle factors—makes a meaningful difference in how you interpret what's happening in your own body or in a clinical context. Most people never get that level of detail, and that gap between textbook knowledge and real-world application is where things tend to go wrong.