
What Actually Works When Kids Struggle With Zippers
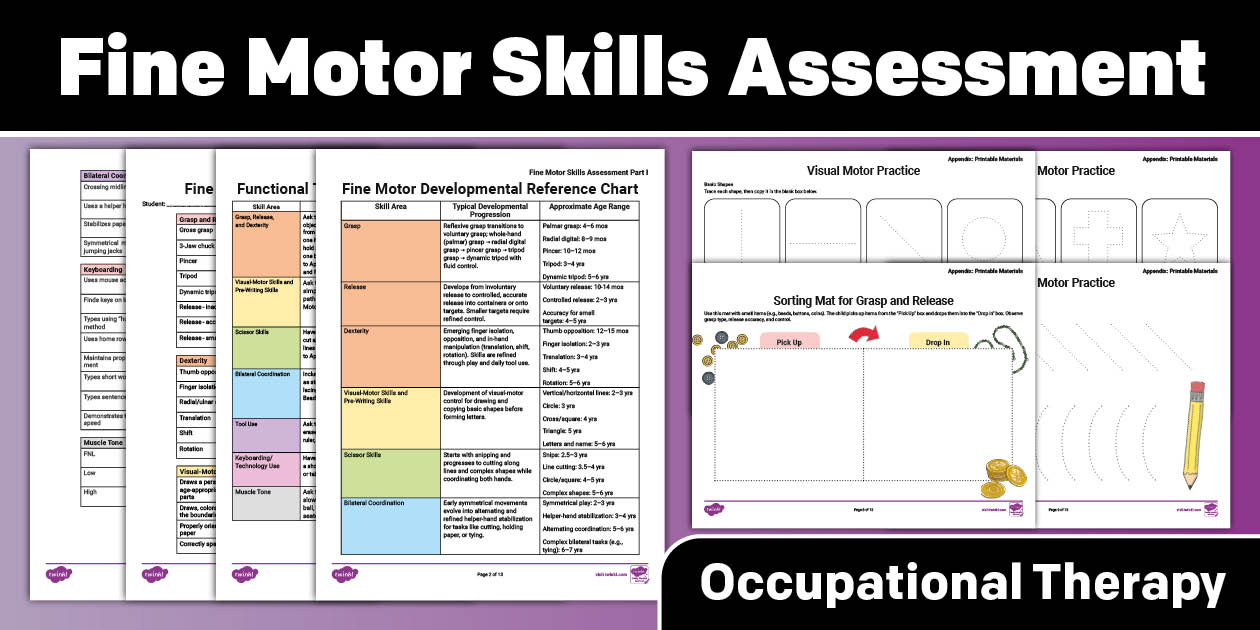
I spent eight years in pediatric OT before moving into consulting, and the thing nobody tells you is that fine motor intervention looks nothing like those Pinterest therapy game boards. Real work happens when a kid can't manage their lunchbox strap, or when they give up on shoes before they even get to the house. The assessments are standard, but the execution is where most programs fall apart. Most people picture bead threading and scissor worksheets. That's not wrong, but it's only the surface. Fine motor skills in therapy cover grip patterns, bilateral coordination, finger isolation, hand strength, and the coordination between what your hands see and what your hands do. We're talking about the difference between a mature tripod grasp and a palmar grasp that hasn't migrated up the fingers yet. That migration typically happens between eighteen months and three years, and when it doesn't, everything downstream gets harder. The evaluation phase usually involves standardized tools like the PEDI or BOT-2, but honestly, watching a kid actually try to button a shirt tells you more than any scoring rubric. I've seen kids score "average" on paper tests and still be unable to open their own snack bags at home. The gap between standardized scores and functional ability is where parents get confused, and where therapists need to be honest about it.
The Tools That Show Up in My Clinical Bag
Here's what I actually use, not what the catalogs advertise. Pegboards are fine for initial assessment of pincer grasp, but they don't transfer to real life. A kid who can place forty pegs in two minutes still can't pick up a pea with chopsticks. That's why I moved toward activities with friction and variable resistance. Lid puzzles where the pieces have different shapes and weights teach the hand to adjust grip based on object properties. I use wooden knob puzzles with progressively smaller knobs, starting at two centimeters and dropping to eight millimeters over six to eight weeks. The grindy part is that some kids hit a wall around the twelve-millimeter mark where their extrinsic finger flexors just won't cooperate without significant upper trunk stabilization. That's when you stop pushing the puzzle and start working on core engagement. Clothing pins on the edge of a cardboard box, button boards, and ziplock bag opening practice form the daily routine for most kids I see. The ziplock bag thing sounds ridiculous until you watch a seven-year-old stare at a sealed snack bag like it's a bomb defusal kit. That's a real fine motor deficit masked as frustration or behavioral refusal.
Edge Case I Wish More People Understood
Last year I had a nine-year-old boy who could write legibly, tie his shoes with a modified knot, and handle utensils fine, but he could not manipulate a key in a door lock. Not because his fingers were weak. His grip strength was solid. The problem was that his right hand would pronate involuntarily the moment the key approached the lock, and his left hand wouldn't stabilize the keyway at all. He'd fumble the key against the metal, get frustrated, and then his mom would just open the door for him. Standard fine motor intervention wasn't touching this. The workaround was building a practice lock on a wooden board using an old cam lock from a hardware store, then having him approach it from multiple angles while I placed a light tactile cue on his right forearm to remind him to maintain supination. We did thirty seconds of this between activities, four times a week, for six weeks. He got it. Not perfect, but functional. The point is that fine motor problems don't always present where you expect them to.
Get the Full Details
Common Pitfalls That Waste Months
Therapists sometimes overload on grip strengthening with putty and grippers before addressing the underlying coordination issue. A kid with poor proprioceptive feedback who gets twenty minutes of hand therapy putty daily will build finger flexor strength but still can't feel whether their pencil lead is touching the paper. The sensation gap remains, and now you've got a stronger kid who can't do the same task. This combo tends to show up when kids have mild sensory processing differences alongside their motor challenges. Another trap is assuming that if a child can imitate a motor action once during assessment, they've mastered it. They haven't. Motor learning requires repetition across varied contexts over weeks, not a single successful trial while the therapist is holding their hand. I tell parents that visible improvement typically shows up after four to six weeks of consistent practice, and that consistency matters more than intensity. Twenty focused minutes daily beats ninety minutes on Saturday.
What Parents Can Actually Do at Home
The single most effective thing is embedding practice into existing routines rather than creating separate therapy time. Let the kid open their own food containers. Make them pull the zipper on their own coat, even if it takes longer. Play dough is fine but only if it's actually resistant enough to require effort. Soft store-bought modeling clay does nothing for finger strength. Self-hardening clay or dense play dough is what you want. Using tweezers to sort small objects, picking up beans with chopsticks, and threading large needles are all legitimate exercises. Don't call them exercises. Call them whatever keeps the kid engaged. Chopstick practice with puffy corn snacks works better than chopstick practice with rice for beginners because the weight and size give more tactile feedback. Fine Motor Skills Occupational Therapy programs that involve parents in the actual strategy tend to produce results in half the time compared to programs where therapy stays entirely in the clinic. The carryover problem is real and well-documented. What happens in the office doesn't leave the office unless someone builds a bridge between the two environments.
When to Worry and When to Wait
If a four-year-old cannot hold a crayon with any recognizable pattern, if a five-year-old refuses to use utensils and still necks food, or if a six-year-old cannot manage basic fasteners on their clothing independently, those are concrete reasons to seek evaluation. Don't wait to see if they grow out of it. Fine motor delays don't self-correct the way some speech delays do. That said, not every kid who struggles with handwriting needs intensive therapy. Some just need adapted grips and proper seating. The writing fatigue many kids experience comes from poor proximal stability first, not weak fingers. If their hand cramps after five minutes of writing, check their posture before you check their grip. There's no universal program download or app that fixes this. The closest thing to a resource I can point to is the Handbook of Occupational Therapy Techniques by Susan Yee, which has structured progressions for most common deficits. Outside of that, it's mostly clinical judgment and seeing enough kids to recognize patterns.




