Why People Get Flunked Before They Even Get Hosed
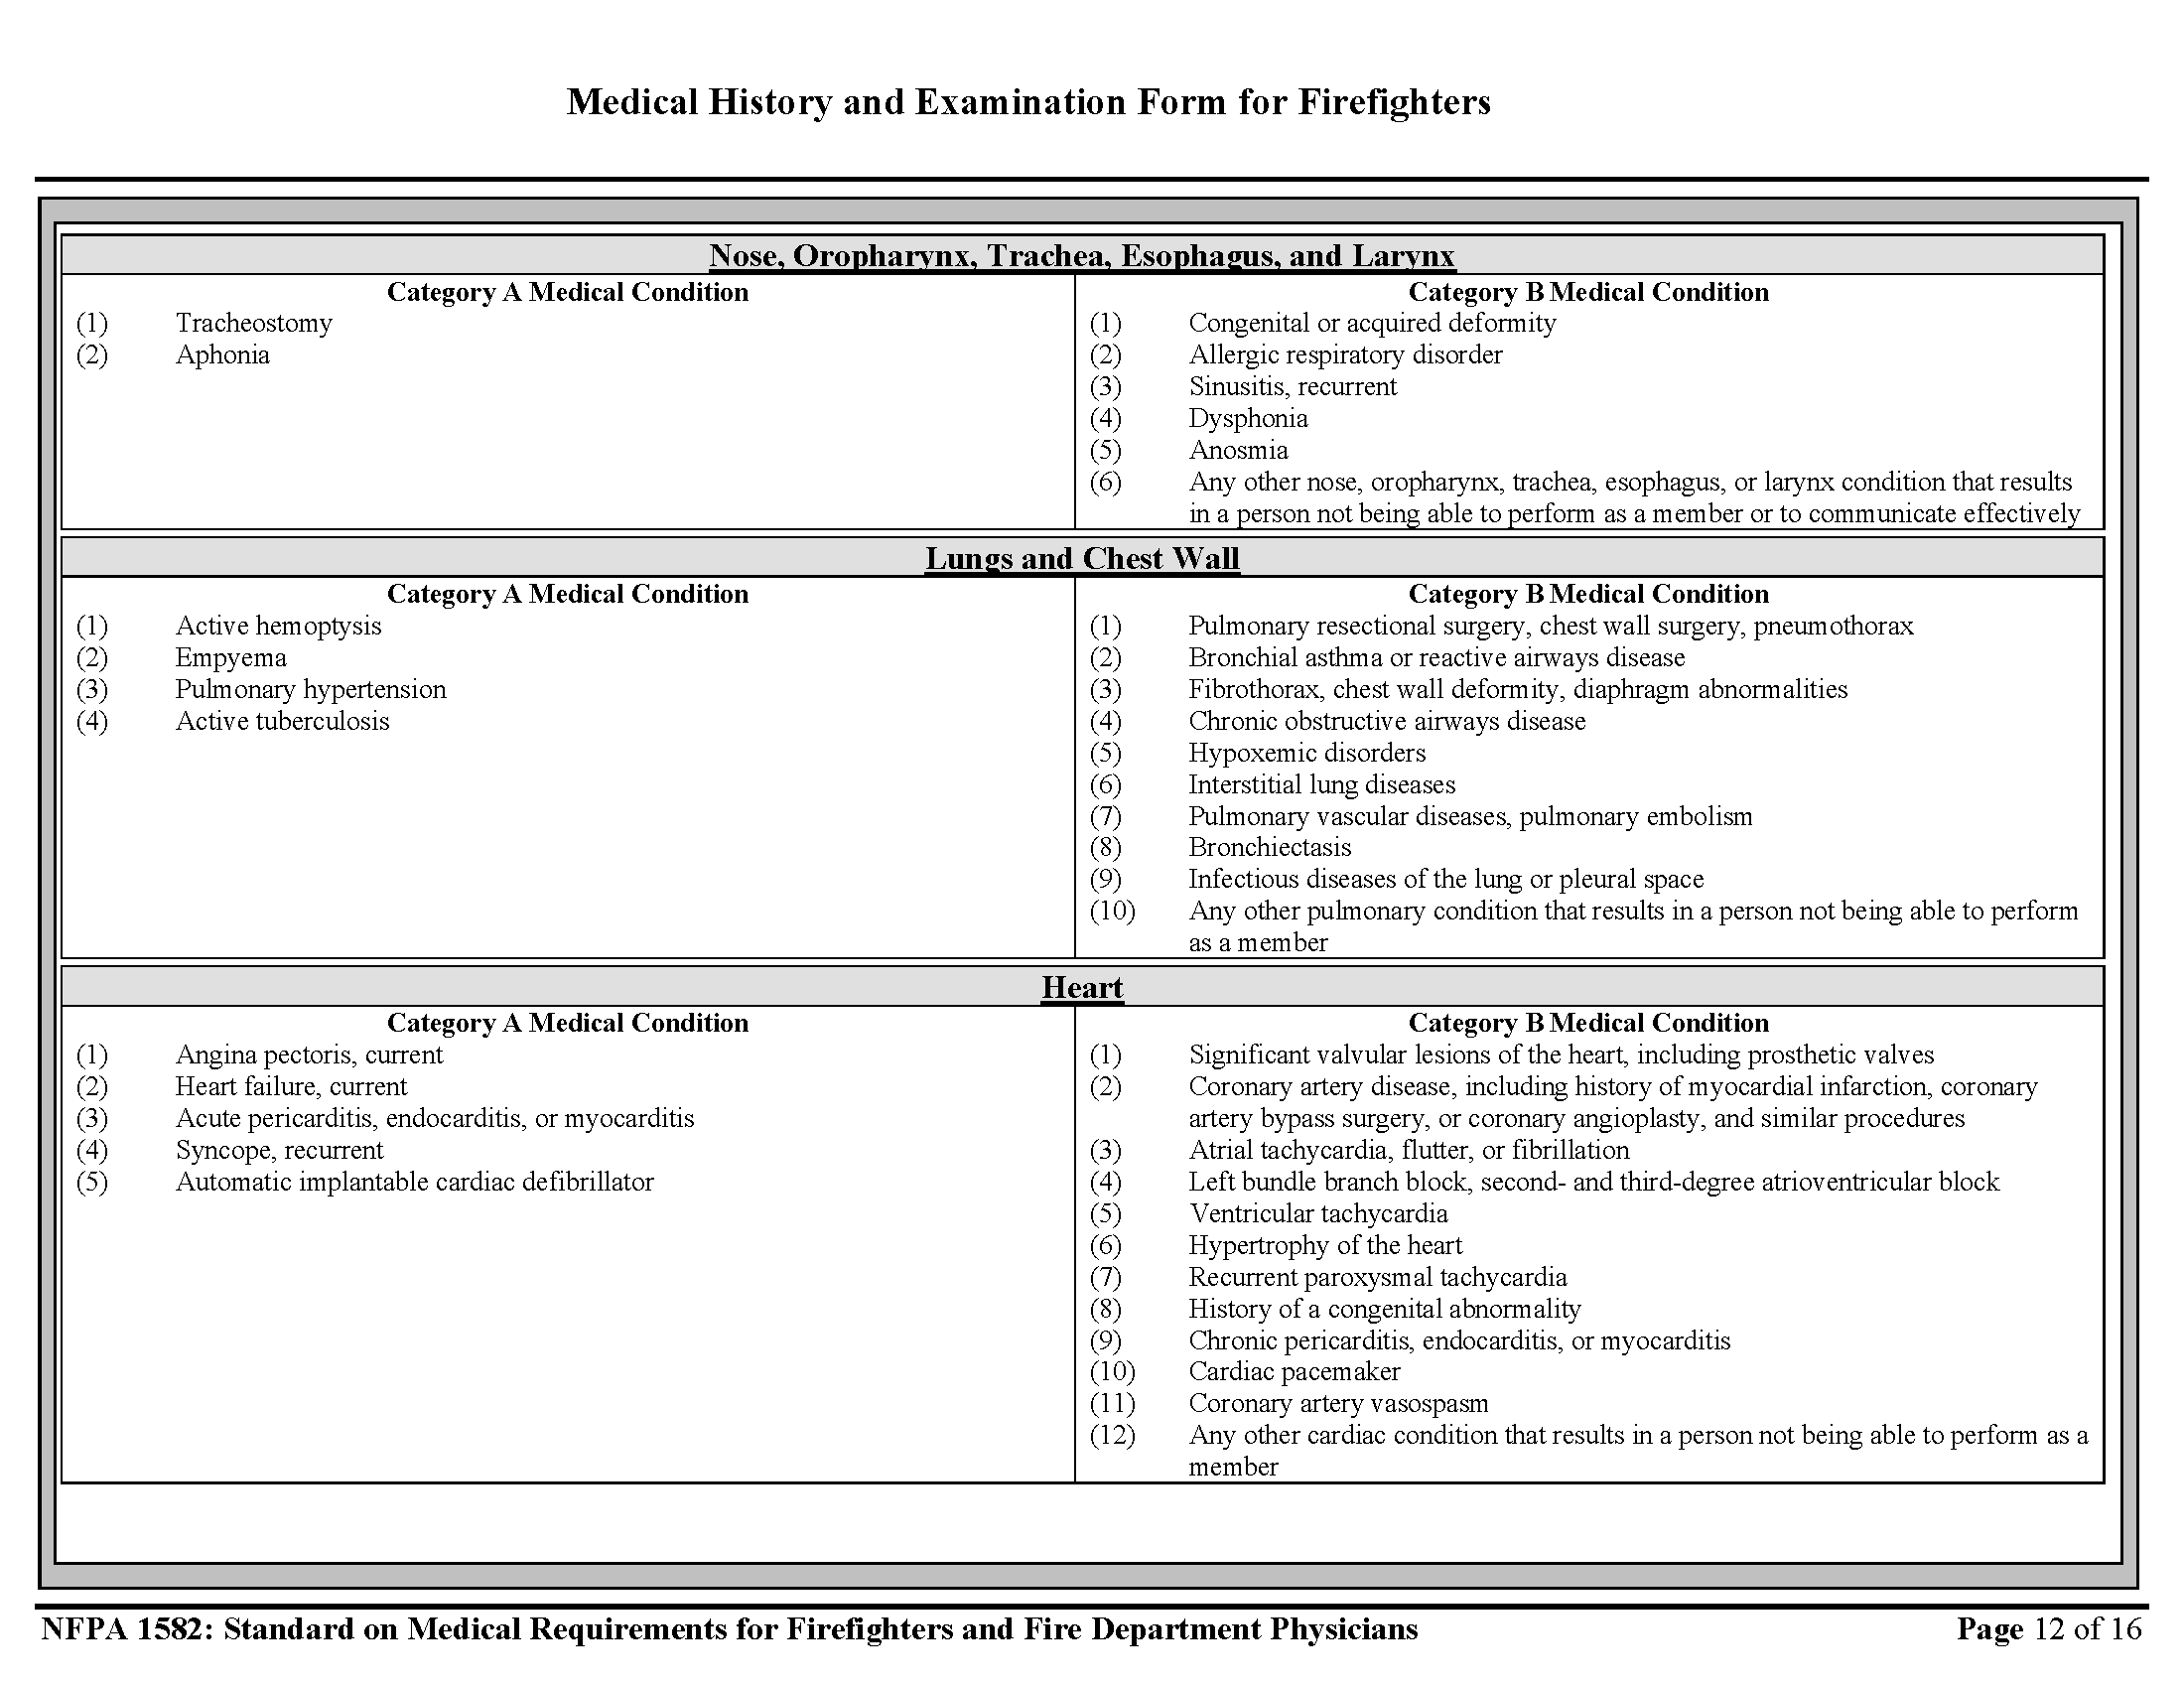
The fire department medical exam is not some casual checkup where they glance at your vitals and wave you through. It is a gate. I have watched candidates who could run a four-minute mile get handed a letter saying their blood pressure was too high. It happens constantly. Most of the time, the disqualification has nothing to do with being unqualified for the job and everything to do with a single data point on a form falling outside a cutoff range that was never designed with modern firefighters in mind. Here is how this actually works. The exam generally follows IAFF and IFSTA guidelines plus whatever your local jurisdiction or hiring agency has adopted. You will encounter a cardiovascular screen, pulmonary function test, vision and hearing standards, a drug and urine screen, a physical agility portion, and a general medical history review. The disqualifying conditions show up across all of those sections. Cardiovascular issues are the number one source of automatic referrals. Hypertension that stays above the threshold on multiple readings, uncontrolled arrhythmias, a history of myocardial infarction, or structural heart disease will flag you. Some departments use a 130 over 80 cutoff. Others go by NFPA 1582 thresholds. The exact number depends on who wrote your job posting. Either way, I have seen plenty of perfectly healthy applicants fail because they were nervous and their systolic spiked past 140 on the spot.
Pulmonary function tests catch people with exercise-induced asthma, undiagnosed COPD, or even poor effort. If your FEV1 comes back under 80 percent predicted and the bronchodilator reversibility test is negative, you are going to be referred for further evaluation. That does not always mean a permanent disqualification. It means you need a pulmonologist to clear you, and that takes weeks or months. The process stalls your entire application. Vision standards vary but most departments require 20/40 corrected or better in each eye, plus normal color vision. Color blindness is more disqualifying than people realize. A candidate cannot distinguish red from green on a Watson lantern test and the department says no. No exceptions. I know because I sat in a waiting room with a guy who failed the color vision test and had zero recourse. He was otherwise a perfect candidate. Hearing is similar. A pure tone average above a certain threshold across key frequencies, usually 500, 1000, and 2000 hertz, and you are out. Some departments allow hearing aids. Some do not. Check your specific job announcement before you even book the exam.
Metabolic conditions like uncontrolled diabetes mellitus requiring insulin will disqualify you in most departments. Uncontrolled hypertension is the same category. Epilepsy or a seizure disorder is an automatic rejection in nearly every agency. This is not about discrimination. It is about the fact that a seizure while handling a hoseline or operating a chainsaw is a lethal situation for everyone around you. Skin conditions matter more than you would guess. Extensive psoriasis or chronic dermatitis that interferes with wearing protective gear, breathing apparatus seals, or turnout coat liners can be a disqualifier. It sounds minor until you are trying to seal a SCBA mask against compromised skin. Psychiatric conditions like uncontrolled bipolar disorder, active substance abuse, or certain personality disorders are on the list. Depression and anxiety disorders treated with medication are a gray area. Some departments accept them if you are stable and cleared by a psychiatrist. Others treat any psychiatric diagnosis as a red flag. You need to know your department's policy before you walk in.
Get the Full Details

The physical agility test is where a lot of people who passed the medical screen still get cut. It is not technically a medical disqualification but it functions the same way. You cannot pass a stair climb with a weighted vest and a cardio load test if you have untreated sleep apnea and your oxygen saturation drops to 85 percent at rest. I saw this exact situation twice in one hiring cycle. Renal issues such as a history of kidney stones causing recurrent infections, or chronic kidney disease past stage 2, will disqualify you. Liver disease with cirrhosis is an automatic fail. Active hepatitis B or C may or may not disqualify you depending on the department, but expect a lengthy review. Orthopedic limitations are common and often overlooked. A prior shoulder rotator cuff repair with residual weakness, a fused spine from old injuries, or a knee replacement that limits crawling and lifting will come up. The test is whether you can perform the essential job functions with or without reasonable accommodation. Most fire departments do not accommodate structural orthopedic limitations because the job inherently requires full body function in unpredictable environments.
I had a candidate once who was cleared by his own doctor on every metric except he had a minor congenital heart valve abnormality. The department physician wanted a cardiology stress echo before making a decision. We obtained the echo, it came back normal with no regurgitation, and he was cleared two weeks later. The workaround was straightforward documentation from a board-certified cardiologist stating that the condition posed no risk during high exertion. That is the pattern I see repeatedly. The first examiner says no. A specialist says yes. The department accepts the specialist opinion if it is thorough enough. One thing nobody tells you about the pre-employment medical is that the drug screen often catches people off guard. If you use prescription ADHD medication without declaring it, or if your homeopathic supplements contain banned substances, you will test positive. I had an applicant who took a weight loss supplement with stimulants and failed his amphetamine screen. He had no idea. He brought a copy of the ingredient label and his prescribing physician signed off that it was not performance-enhancing in the way the test was designed to catch, but the department still rejected him. The policy was binary. Positive result means disqualification regardless of explanation. Here is a counter-intuitive point that most candidates miss. The blood draw itself can ruin your chances if you are dehydrated or have a venous issue. Some departments require a fasting glucose and lipid panel. If you are severely dehydrated, your hematocrit goes up and your kidney function markers look worse than they are. I have seen people fail the renal screening portion on a single bad draw and then have a follow-up test the next week come back perfectly normal. Do not skip water the day before. Just follow the fasting instructions exactly.
Another thing: the exam is not a pass-or-fail binary at the clinic. It is a referral system. You will receive a status like qualified, qualified with restrictions, or referred for additional testing. If you are referred, do not ignore it. The clock is ticking on your application. Many departments will move to the next candidate if your referral drags past a certain deadline. I have seen applications expire because the candidate waited four months for a specialist appointment and never followed up with the department coordinator. The sleep apnea issue deserves its own attention. Obstructive sleep apnea is increasingly common in the age group that applies for firefighting. If you are diagnosed but not using CPAP consistently, or if your Apnea-Hypopnea Index is above a certain threshold, you may be disqualified. Some departments will accept you with documented CPAP compliance over 90 percent usage and a follow-up sleep study showing controlled AHI. Others reject any history of sleep apnea. There is no universal standard here. You must read your specific hiring document. There is also a hidden disqualifier that catches a lot of people. Tattoos or scars that interfere with medical equipment placement. If you have extensive chest tattoos or surgical scars in the area where ECG leads need to attach, the technician may not be able to get a clean reading. This can trigger a referral for an alternative cardiac screen, which delays things. I learned this the hard way when a candidate had a full chest tattoo and spent an extra hour at the clinic getting manual palpation assessments instead of standard ECG leads.

The practical steps to avoid disqualification are mundane but most people skip them. Get your own primary care physician to run a baseline panel two to three months before the department exam. Check your blood pressure at different times of day. Know your numbers. If your BP is borderline high, address it with your doctor before the exam. It is much easier to manage a borderline reading at home than it is to appeal it after a department exam. Bring all your current medication lists and prescriptions to the exam. OTC supplements count as medications. Bring the bottles. Bring your specialist letters. Bring copies of any prior cardiac stress tests, pulmonary function reports, or sleep studies if you have them. The examiner is not going to dig through old records for you. You need to provide the documentation that answers the questions they are about to ask. If you receive a disqualification, request the written rationale immediately. The department is required to provide it. Then determine whether the disqualification is final or whether it can be appealed through a designated physician review. Most jurisdictions have an independent physician who can overrule the department's initial examiner if the evidence supports it. This is not a guarantee. It is a process that takes time and proper documentation.
The hardest truth about firefighter medical exam disqualifications is that many of them are not about whether you can actually do the job. They are about liability and paperwork. A department would rather reject a candidate with a borderline condition than litigate the decision later. Understanding that dynamic changes how you approach the entire process. You are not just proving you are healthy. You are building a documented trail that leaves no room for ambiguity.