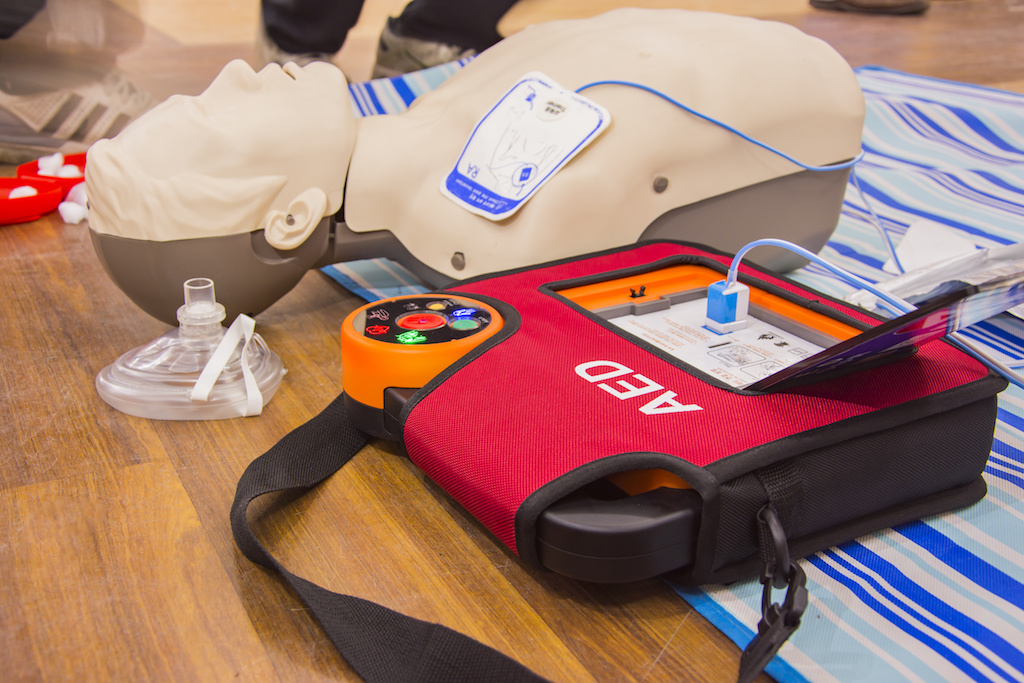
What actually happens when someone collapses
You hear a thud. Someone is on the floor, not moving. Your first instinct is to panic because that is a normal human response. The person who wrote the guidelines for CPR knew this, which is why they structured everything around simple steps that someone can follow while their heart is pounding out of their chest. First Aid Cpr And Aed covers the full chain from recognizing cardiac arrest to getting someone back to a stable rhythm, and understanding how these pieces connect matters more than memorizing individual steps. Cardiac arrest means the heart has stopped pumping blood effectively. It is not the same as a heart attack, which is a circulation problem caused by a blocked artery. In cardiac arrest, the electrical system of the heart goes haywire, usually into ventricular fibrillation or ventricular tachycardia. The brain starts dying within four minutes without oxygenated blood. That is why immediate action is the single most important factor in survival rates.
The First Aid Cpr And Aed Response
Start with scene safety. I have seen too many would-be rescuers walk into situations where they become the second victim. Check for hazards before you touch anyone. Then check responsiveness by tapping the person's shoulders and shouting, "Are you okay?" If there is no response, shout for help and have someone call 911 while you grab an AED if one is nearby. If you are alone, call 911 yourself first, then begin CPR. Check breathing. Look for chest rise and fall for no more than ten seconds. If the person is not breathing normally or is just gasping, that is agonal breathing and it means cardiac arrest has occurred. Gasping is not adequate breathing. Start chest compressions immediately. Place the heel of one hand on the center of the chest, right on the lower half of the sternum. Put your other hand on top and interlock your fingers. Keep your arms straight and your shoulders directly over your hands. Push hard and fast at a rate of 100 to 120 compressions per minute. Push at least two inches deep for adults, but no more than two point four inches. Allow the chest to recoil completely between compressions. Do not lean on the chest.
If you are trained in rescue breaths, give two breaths after every thirty compressions. Tilt the head back, lift the chin, pinch the nose shut, and give each breath over ten seconds, watching for chest rise. If you are not trained or unwilling to give rescue breaths, do continuous compressions only. Hands-only CPR is effective and eliminates the hesitation that kills people in real emergencies. When the AED arrives, turn it on and follow the voice prompts. The AED will analyze the heart rhythm and tell you whether a shock is needed. If it says "shock advised," make sure no one is touching the person, press the shock button, then immediately resume CPR starting with compressions. If it says "no shock advised," resume CPR right away. Do not check for a pulse after a shock. Just go back to compressions for two minutes before the AED prompts you to reanalyze. One thing that surprises most people: the AED is safe to use on anyone, including children and infants. For children under eight years old or weighing less than fifty-five pounds, use pediatric pads if available. If you only have adult pads, make sure they do not touch each other. If they would overlap on a small chest, place one pad in the center of the chest and the other on the center of the back. This anterior-posterior placement works fine and delivers the shock effectively.
Get the Full Details

Common mistakes that reduce survival
Interrupting compressions is the biggest killer of outcomes. Every time you stop to check a pulse or give breaths, blood flow drops to near zero and it takes several compressions to rebuild pressure. Minimize interruptions to under ten seconds. If you are doing CPR alone with no AED yet, do cycles of thirty compressions and two breaths without stopping to feel for a pulse. Another mistake is compressing too shallowly. People tend to be gentle when they are afraid of hurting someone. You need to push harder than you think. Two inches minimum. If you are not breaking a sweat, you are probably not doing it right. Fatigue sets in quickly, which is why two-rescuer CPR is preferable when possible. Switch compressors every two minutes or sooner if the rescuer is tired. I once responded to a call where the AED was stuck in a glass case behind a keypad in a school hallway. By the time someone found the key and opened it, we had been doing CPR for nearly five minutes without defibrillation. That delay likely cost the patient a chance at survival. This is why you should always know where the nearest AED is in any building you frequent, and whether it is accessible without special equipment. Many facilities now have AEDs mounted openly with break-glass cases that do not require keys.
Here is a nuance most people miss: obesity changes everything. Compressing a chest on a person who weighs three hundred pounds requires significantly more force to achieve the recommended two-inch depth. If you cannot achieve adequate depth, consider recruiting help to take turns pushing, or brace your shoulders differently. Some studies suggest that in morbidly obese patients, even maximum effort compressions may not reach two inches. In those cases, the priority remains high-quality compressions at the correct rate, even if depth is suboptimal, because some blood flow is infinitely better than none. There is also the issue of medication implants. If the person has a pacemaker or ICD, you will feel a hard lump under the skin, usually in the upper left chest. AED pads should be placed at least an inch away from the device. Do not place a pad directly over it. The device itself may deliver a shock, which is why the AED will analyze and advise accordingly. If the ICD fires on its own during your resuscitation attempt, that is actually a good sign, but you still continue CPR as directed.
Post-resuscitation and when to stop
If the person starts breathing on their own and has a pulse, roll them into the recovery position on their side. Keep them warm and monitor their breathing until emergency services arrive. Do not leave them alone. Even if they seem fine, they need medical evaluation because the underlying cause of the arrest still needs treatment. Continue CPR until one of these happens: the person shows signs of life, an AED is available and advises no shock after two minutes of CPR, trained EMS personnel take over, you are too exhausted to continue, or the scene becomes unsafe. There is no moral obligation to stop early because you feel like you tried hard enough. Cardiac arrest resuscitation is physically demanding and can last twenty minutes or longer. The reality of First Aid Cpr And Aed is that no amount of training prepares you for the stress of actually doing it. Your hands will shake. You will second-guess your compression depth. The AED may say "check patient" because motion artifact confused the analysis. This is normal. Keep going. The data shows that bystander CPR doubles or triples survival rates from cardiac arrest. An AED used within three to five minutes of collapse can increase survival to seventy percent or more in cases of shockable rhythms. Those are not theoretical numbers. They come from real incidents with real people.

If you want to learn properly, take a certified course through the American Red Cross or the American Heart Association. Both offer in-person and hybrid programs that include hands-on practice with manikins and AED trainers. Practice annually. Skills degrade within three to six months without reinforcement. The guidelines change periodically, so recertification keeps you current on compression ratios, breath volumes, and AED protocols. Don't skip it because you took a class five years ago and feel confident. You are not as confident as you think.



