What Actually Happens When Someone Gets Shocked
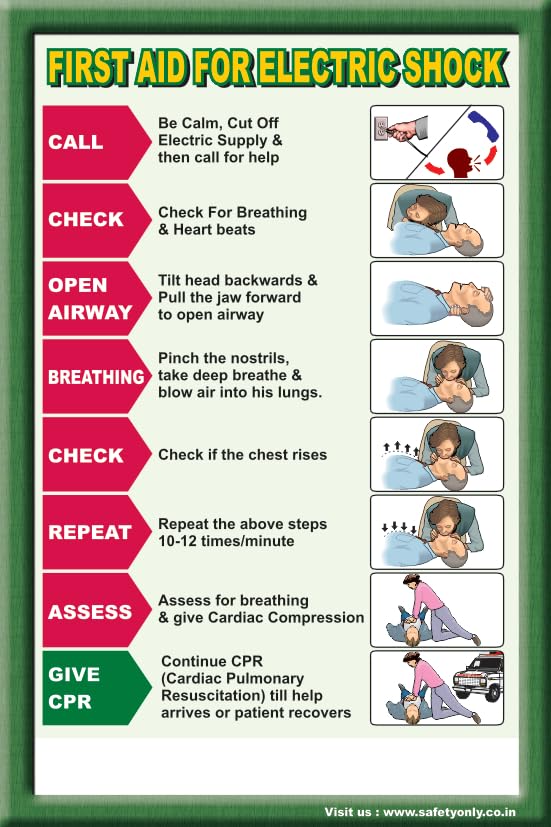
The moment someone takes an electric shock, your first instinct should be to figure out if you can safely approach them. That matters more than anything else on this page. I've seen people get knocked unconscious by second shocks because they ran straight in without checking the scene. The current doesn't stop flowing just because a person is touching it. If you touch that person while they're still energized, you become part of the circuit and now you have two patients instead of one. Here's the practical sequence. Find the power source. Flip the breaker, pull the plug, or use a non-conductive object to separate the person from the energized conductor. A dry wooden broom handle works fine for low-voltage situations. Nylon rope or a thick cotton jacket can work in a pinch. I've used a fiberglass ladder at a job site when I couldn't kill the power fast enough. Dry wood and fiberglass don't conduct electricity under normal conditions. Wet wood does. Don't assume anything is non-conductive without checking it first.
When You Can't Cut the Power: First Aid Procedures For Electric Shock in the Field
Sometimes you can't reach the disconnect. Maybe it's down a hallway or upstairs in a panel you can't access in time. In those cases, you're working with what you have on hand. The priority shifts to protecting yourself while you extricate the victim. Once the person is clear, check responsiveness. Tap their shoulders and shout. If they're not breathing normally, start CPR immediately. The 2020 AHA guidelines emphasize high-quality chest compressions at 100 to 122 per minute, pushing hard and fast at least two inches deep for adults. Don't stop unless you see obvious signs of life or trained responders take over. An automated external defibrillator, or AED, should be used as soon as one is available. Electric shocks can disrupt the heart's electrical system, causing ventricular fibrillation, which is often fatal without prompt defibrillation. AEDs are designed for public use. They talk you through every step. I learned the hard way about a subtlety that most first aid courses gloss over. During a residential rewiring job, a coworker gripped a live 120-volt wire. His hand clamped shut around it. He couldn't let go. The "no-let-go" threshold for alternating current at 60 hertz is roughly 15 milliamps for an average adult male. A typical household circuit can deliver hundreds of milliamps. His grip was strong enough that a standard dry rope wouldn't break the contact. What finally worked was a sharp yank on a dry hemp rope looped around his upper arm and torched against a framing stud. The friction heated the hemp, and the burn created enough slack to pull him free. It was messy. Nobody got hurt beyond the initial shock. But it taught me that sometimes the textbook instruction to "pull the victim clear" is too vague for real-world conditions where muscles are locked in tetany.
What to Check After the Immediate Rescue
Electric current causes internal damage that isn't always visible. Entry and exit wounds are the standard teaching point, but the damage between those points can be severe. Myositis, or muscle inflammation from thermal injury, can develop within hours. Compartment syndrome is a real risk when deep tissue heating causes swelling inside the fascial compartments. Rhabdomyolysis, the breakdown of damaged muscle tissue, can flood the kidneys with myoglobin and cause acute renal failure within 24 to 72 hours. Even if the person looks fine, they need medical evaluation. Cardiac monitoring for at least four hours is the standard recommendation for any significant shock, especially if the current path crossed the chest. Arrhythmias can be delayed. The heart doesn't always protest immediately. I once saw a homeowner who was electrocuted by a faulty garage door opener. He shook it off, went back to work, and collapsed at home six hours later with a lethal arrhythmia. He didn't make it. The lesson is simple: any shock that caused muscle contraction, loss of consciousness, or visible burns warrants an emergency department visit and cardiac monitoring. Don't argue with dispatchers about whether it's "bad enough." Let them decide. For minor shocks where the person is fully alert and has no burns, you still need to monitor them. Watch for confusion, headache, vision changes, or irregular heartbeat over the next several hours. These can indicate delayed neurological or cardiac effects. Keep the person calm and still. Avoid unnecessary movement, especially if there's any chance of spinal involvement from a fall during the shock.
Get the Full Details

Common Mistakes That Make Things Worse
The biggest mistake I see is people waiting too long to call emergency services. Every minute without CPR decreases survival chances by roughly 10 percent. For witnessed cardiac arrest from electric shock, immediate CPR and early defibrillation are the strongest predictors of survival. Don't wait to assess for a pulse if the person is unresponsive and not breathing normally. Start compressions. Check for a pulse only if you're trained and comfortable doing so within 10 seconds. Another frequent error is applying ointments or butter to electrical burns. Do not do this. It introduces infection risk and interferes with medical assessment. Cover the burn with a clean, dry, non-stick dressing. Loose gauze works well. Don't wrap it tightly. Electrical burns often track along tissue planes deeper than the surface wound suggests, so tight wrapping could compromise circulation to already injured tissue. Don't move the victim unless there is immediate danger. Spinal injuries can accompany electric shock, particularly if the person was thrown. If you must move them, try to maintain spinal alignment. Roll them as a unit if possible. I've pulled people from live equipment in industrial settings where staying put meant certain death from arc flash or secondary ignition. In those cases, the risk of staying outweighs the risk of movement, but I make it a point to support the head and neck during the drag.
Special Cases That Change the Approach
High-voltage encounters, generally anything above 600 volts, require a completely different mindset. At those levels, arc flash distances can be several feet. The air itself can ionize and conduct current to someone standing too close. I worked on a substation project once where the utility company enforced a minimum approach distance of ten feet for 15-kilovolt lines. Arc flash boundaries can extend well beyond that depending on fault current and clearing time. If you encounter someone down near high-voltage equipment, stay behind the boundary and call professionals. You cannot safely extricate them yourself. Underwater shocks are another category where the standard advice breaks down. Water conductivity varies wildly depending on whether it's fresh or salt water, but even freshwater significantly lowers skin resistance and increases current flow through the body. If someone is in contact with water and an electrical source, treat the water as energized. Assume anything metal in the water is also live. Shut off power at the source before approaching. GFCI-protected circuits on boats, pools, and outdoor outlets are your best defense here, but they don't eliminate risk entirely. Children and people with pacemakers or implantable cardioverter-defibrillators deserve special mention. A child's smaller body mass means current density is higher for the same voltage, causing more severe tissue damage. People with cardiac implants may need device interrogation after any significant shock event. The electromagnetic pulse from the shock can temporarily inhibit or trigger device function. Emergency departments should be informed of the implant type and manufacturer so they can arrange proper programming checks.
What to Keep in Your Kit
A basic first aid kit for electrical work doesn't need to be expensive or complicated. Non-conductive gloves rated for the voltage you're working around are essential. Leather work gloves over insulating gloves add abrasion protection. A Class H non-conductive helmet protects against overhead hazards. Polyethylene-coated hooks for pulling wires away from live contacts save time and fingers. A quality flashlight with spare batteries is worth more than any gadget you'll buy. For actual first aid on site, include a barrier device for rescue breaths. A pocket mask or face shield removes the hesitation many people feel about mouth-to-mouth. Tearing open a package under stress takes longer than it should. Keep it pre-opened in its packaging or have it ready to grab. Add a compact AED if you're running a crew that works in areas more than a few minutes from emergency medical services. The cost has dropped significantly, and survival rates improve dramatically when a defibrillator is on site rather than waiting for an ambulance that may take fifteen to twenty minutes in rural areas. Documentation matters more than people expect. Note the voltage if known, the duration of contact, the current path through the body, and the time of incident. This information directly affects how aggressively the medical team pursues certain diagnoses and treatments. A two-second 120-volt household shock and a ten-second 480-volt industrial shock are completely different clinical scenarios, even though both involve "electric shock." The details you provide upfront help clinicians triage appropriately.