Understanding Brain Fissures: What You Actually Need To Know
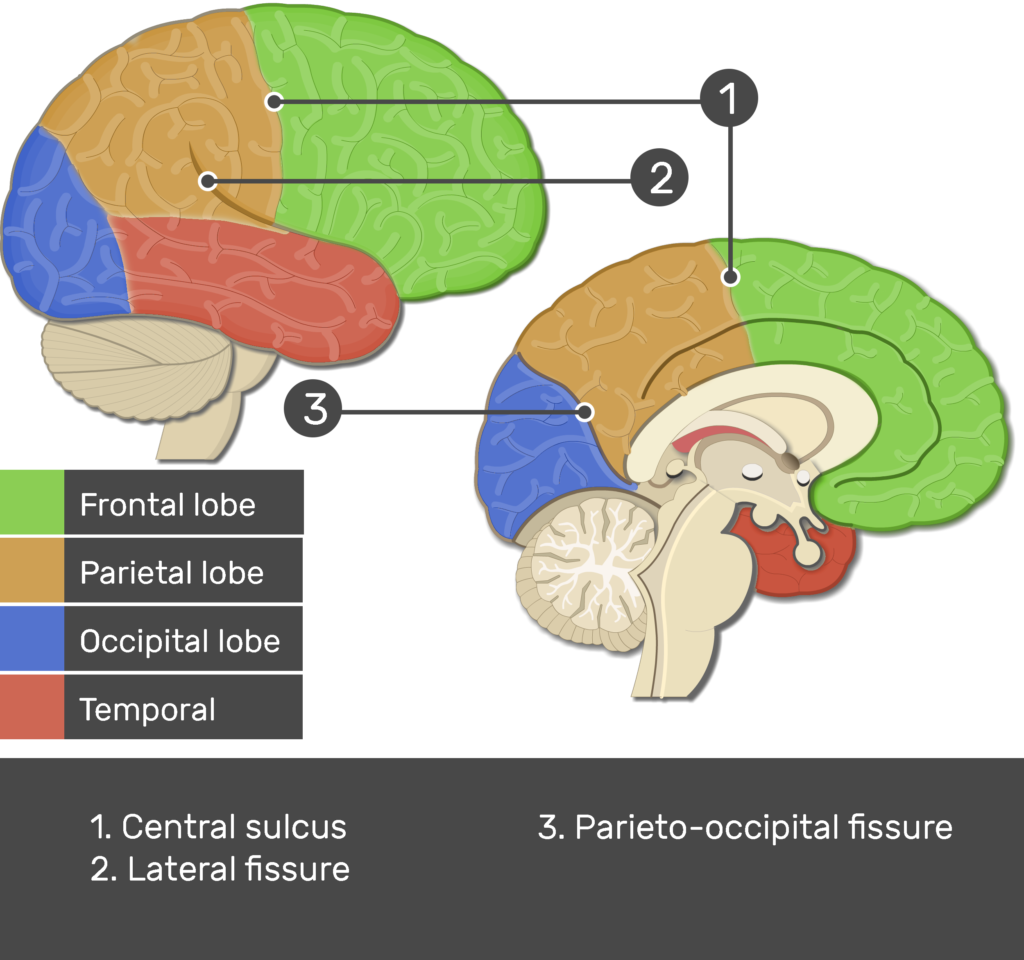
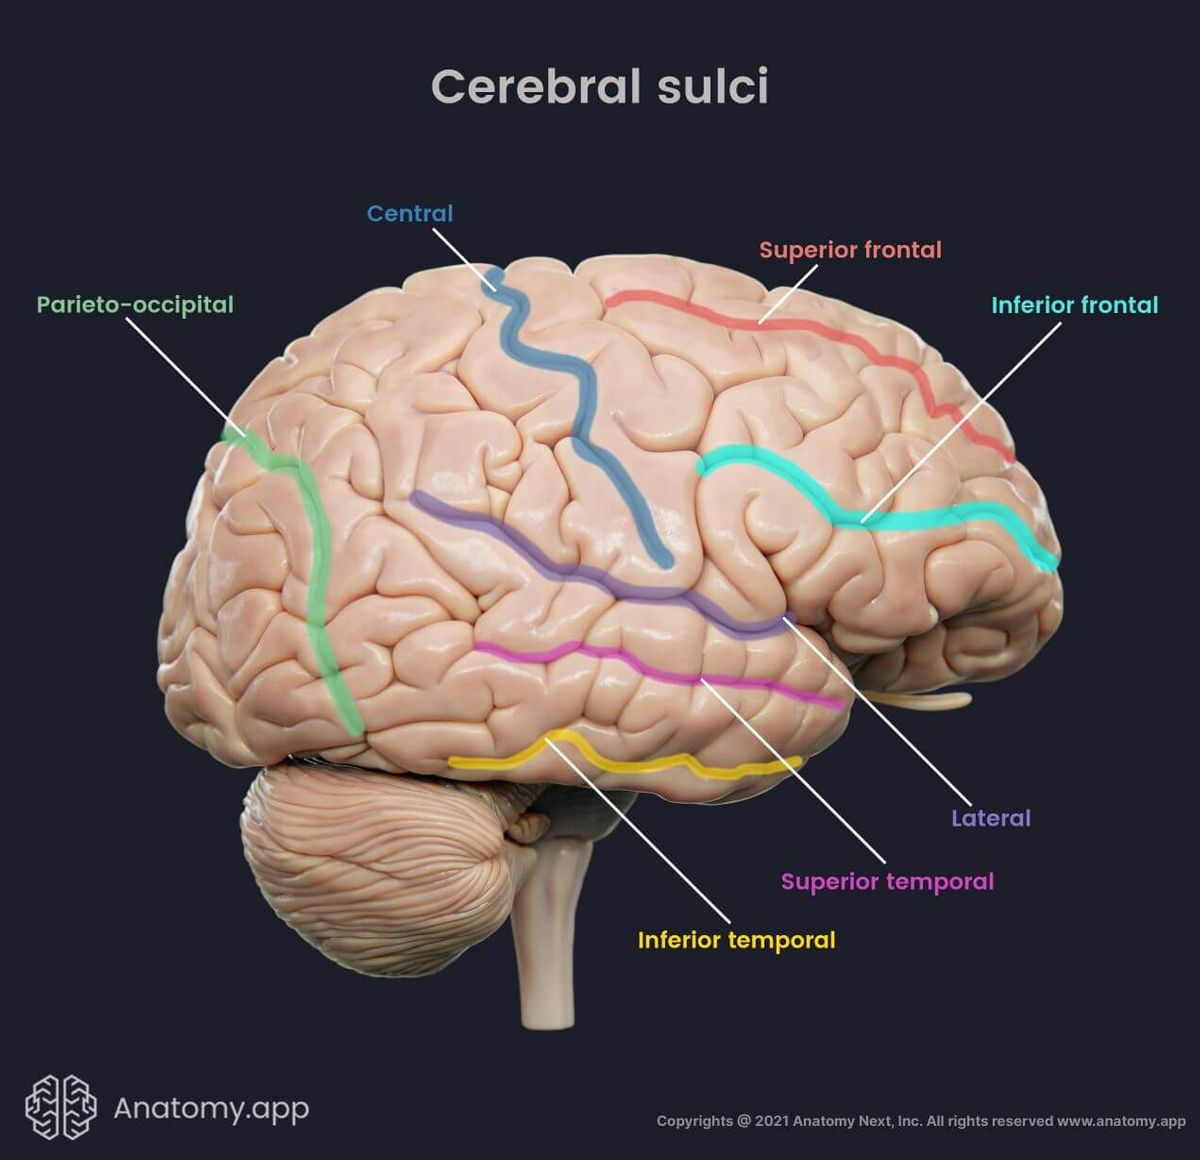
The brain surface is covered in folds. Those deep grooves are fissures, and they divide the brain into lobes and distinct functional areas. Most people learning neuroanatomy or working in radiology, surgery, or neuropsychology need to know where these landmarks sit. The terminology is straightforward, but the practical application is where things get messy. Fissures are the most prominent sulci on the cerebral cortex. In neuroanatomical terms, a sulcus is any shallow groove, while a fissure is typically a deep, complete cleft that separates major regions. The lateral fissure, for example, is deep enough that it practically carves the temporal lobe away from the frontal and parietal lobes above it. That is why it is also called the Sylvian fissure—named after the 16th-century anatomist Andrea Sylvius, not because it looks like a Greek god. The five fissures you will encounter repeatedly are the longitudinal fissure, the lateral/Sylvian fissure, the central/Rolandic fissure, the parieto-occipital fissure, and the calcarine fissure. Each one serves as a boundary marker. In surgical planning, these boundaries tell you where not to cut. In radiology, they are the first landmarks you use to orient yourself on an axial slice.
How To Identify Them On Imaging
If you are looking at a CT or MRI and trying to find your way around, start with the longitudinal fissure. It runs vertically between the two hemispheres and is usually the easiest structure to spot because it contains the falx cerebri, a dural fold that shows up clearly on imaging. Once you have that, move laterally to find the lateral fissure. On an axial slice at the level of the sylvian fissure, you are looking at the same horizontal plane as the external auditory meatus. That is a reliable landmark. The central fissure is trickier. It separates the frontal lobe from the parietal lobe, but it does not always run perfectly perpendicular to the longitudinal fissure. In some brains it angles slightly posteriorly. The key identifier is the precentral and postcentral gyri—the central fissure sits between them. If you cannot see the gyri clearly, look for the hand-knob region on the lateral wall of the central sulcus. That bump is usually visible and marks the motor cortex area for the hand. For the parieto-occipital fissure, go to the medial surface. It is roughly in the middle of the occipital lobe on the medial wall, and it marks the boundary between the parietal and occipital lobes. The calcarine fissure is just below it, also on the medial surface, and it separates the cuneus above from the lingual gyrus below. This fissure contains the primary visual cortex, which is relevant if you are doing anything near the posterior pole.
Here is a practical workflow: on an axial MRI, identify the lateral ventricles first. Then trace the posterior horn of the lateral ventricle forward to the parieto-occipital fissure. Work anteriorly to find the central fissure using the hand knob. From there, you can map the rest of the brain by lobe. This sequence usually takes me about twenty minutes when I am orienting a new scan, depending on image quality.
Get the Full Details

A Real Problem I Hit And How I Got Around It
I was working with a patient whose brain had a significant atrophy pattern, mostly frontal and temporal. The lateral fissure was so widened that it looked almost like a separate cavity rather than a fissure. When I tried to use it as a landmark to delineate the temporal lobe for a surgical plan, the boundaries were completely ambiguous. The usual relationship between the sylvian fissure and the superior temporal gyrus was gone. The workaround was to switch to a coronal view and use the insular cortex as my anchor. The insula is deep to the lateral fissure and tends to hold its shape better in atrophy. I traced the opercula folding over the insula to reconstruct where the temporal and frontal lobes actually ended. Then I cross-referenced with the patient's functional MRI to confirm language and motor areas. It added about forty-five minutes to the prep work, but it was the only way to be confident about the margins.
Counter-Intuitive Things Beginners Miss
Most people learn that fissures are fixed landmarks. They are not. The degree of folding varies enormously between individuals. Some brains are lissencephalic by nature—smooth—with very few fissures, and others have extreme polymicrogyria. Even in normal brains, the central sulcus can vary in depth and branching pattern enough that it is nearly unrecognizable on low-resolution scans. Assuming every brain follows the textbook diagram is a reliable way to make a mistake. Another thing: the parieto-occipital fissure is not always a single continuous groove. In about thirty percent of brains, it has a anterior extension that curves upward toward the superomedial border. If you are looking for it on a single axial slice and do not see it, you may just be scanning through the wrong level. Move a few slices up or down and check the medial surface again.
Where This Knowledge Breaks Down
Fissure-based anatomy becomes unreliable in pathological states. Tumors, strokes, and traumatic injuries can distort the normal topology. A mass effect can push the central sulcus forward or backward by several centimeters. Relying solely on fissure position in those cases is dangerous. In surgical practice, I always confirm landmarks with intraoperative navigation or functional mapping when there is any structural abnormality nearby. Fissures are a starting point, not an endpoint. If you are studying for exams, this approach works fine. If you are applying this in clinical practice, especially in neurosurgery or interventional radiology, you need additional data. Diffusion tensor imaging for white matter tracts, functional MRI for cortical activation, and sometimes direct cortical stimulation are necessary complements to gross anatomical landmarks. No single fissure map is going to keep you safe when you are working inside someone's brain.