
What You Actually Need to Measure
I got asked about Fitness Assessment For Type 2 Diabetes last week by a client's son who wanted to set up his dad on a gym plan without wrecking anything. The first thing I did was pull up the last three HbA1c results and a fasting glucose log, because none of the fancy stuff matters if your blood sugar is bouncing around like a pinball. Type 2 changes the risk profile enough that you can't just hand someone a generic fitness template and walk away. The assessment breaks into four buckets: cardiovascular clearance, metabolic control status, musculoskeletal baseline, and neuropathy screening. You go through them in that order because if the heart isn't stable, the rest is academic.
Starting a Fitness Assessment For Type 2 Diabetes Properly
Let me walk through what actually happens in practice, not the textbook version. I see a lot of people skip straight to body composition and start talking about rep ranges before they know whether the guy can safely raise his heart rate above 120. That's backwards and it's how injuries happen. Step one is always metabolic status. Pull the most recent HbA1c. If it's under 7%, you're working with someone who has reasonable control. Between 7% and 8.5% means you need to be careful about intensity stacking. Over 8.5% and I don't touch the person without endocrine sign-off on their medication schedule, because exercise at that level can push glucose into dangerous territory depending on whether they're on insulin or sulfonylureas. Then check fasting glucose and postprandial readings if available. A fasting number over 180 mg/dL tells you the liver is dumping glucose right now, and pushing hard cardio on top of that isn't smart. Blood pressure comes next. Type 2 and hypertension travel together about 60% of the time. If resting BP is above 140/90, you're looking at someone who needs medical clearance before any moderate-to-vigorous work.
The Parts People Mess Up
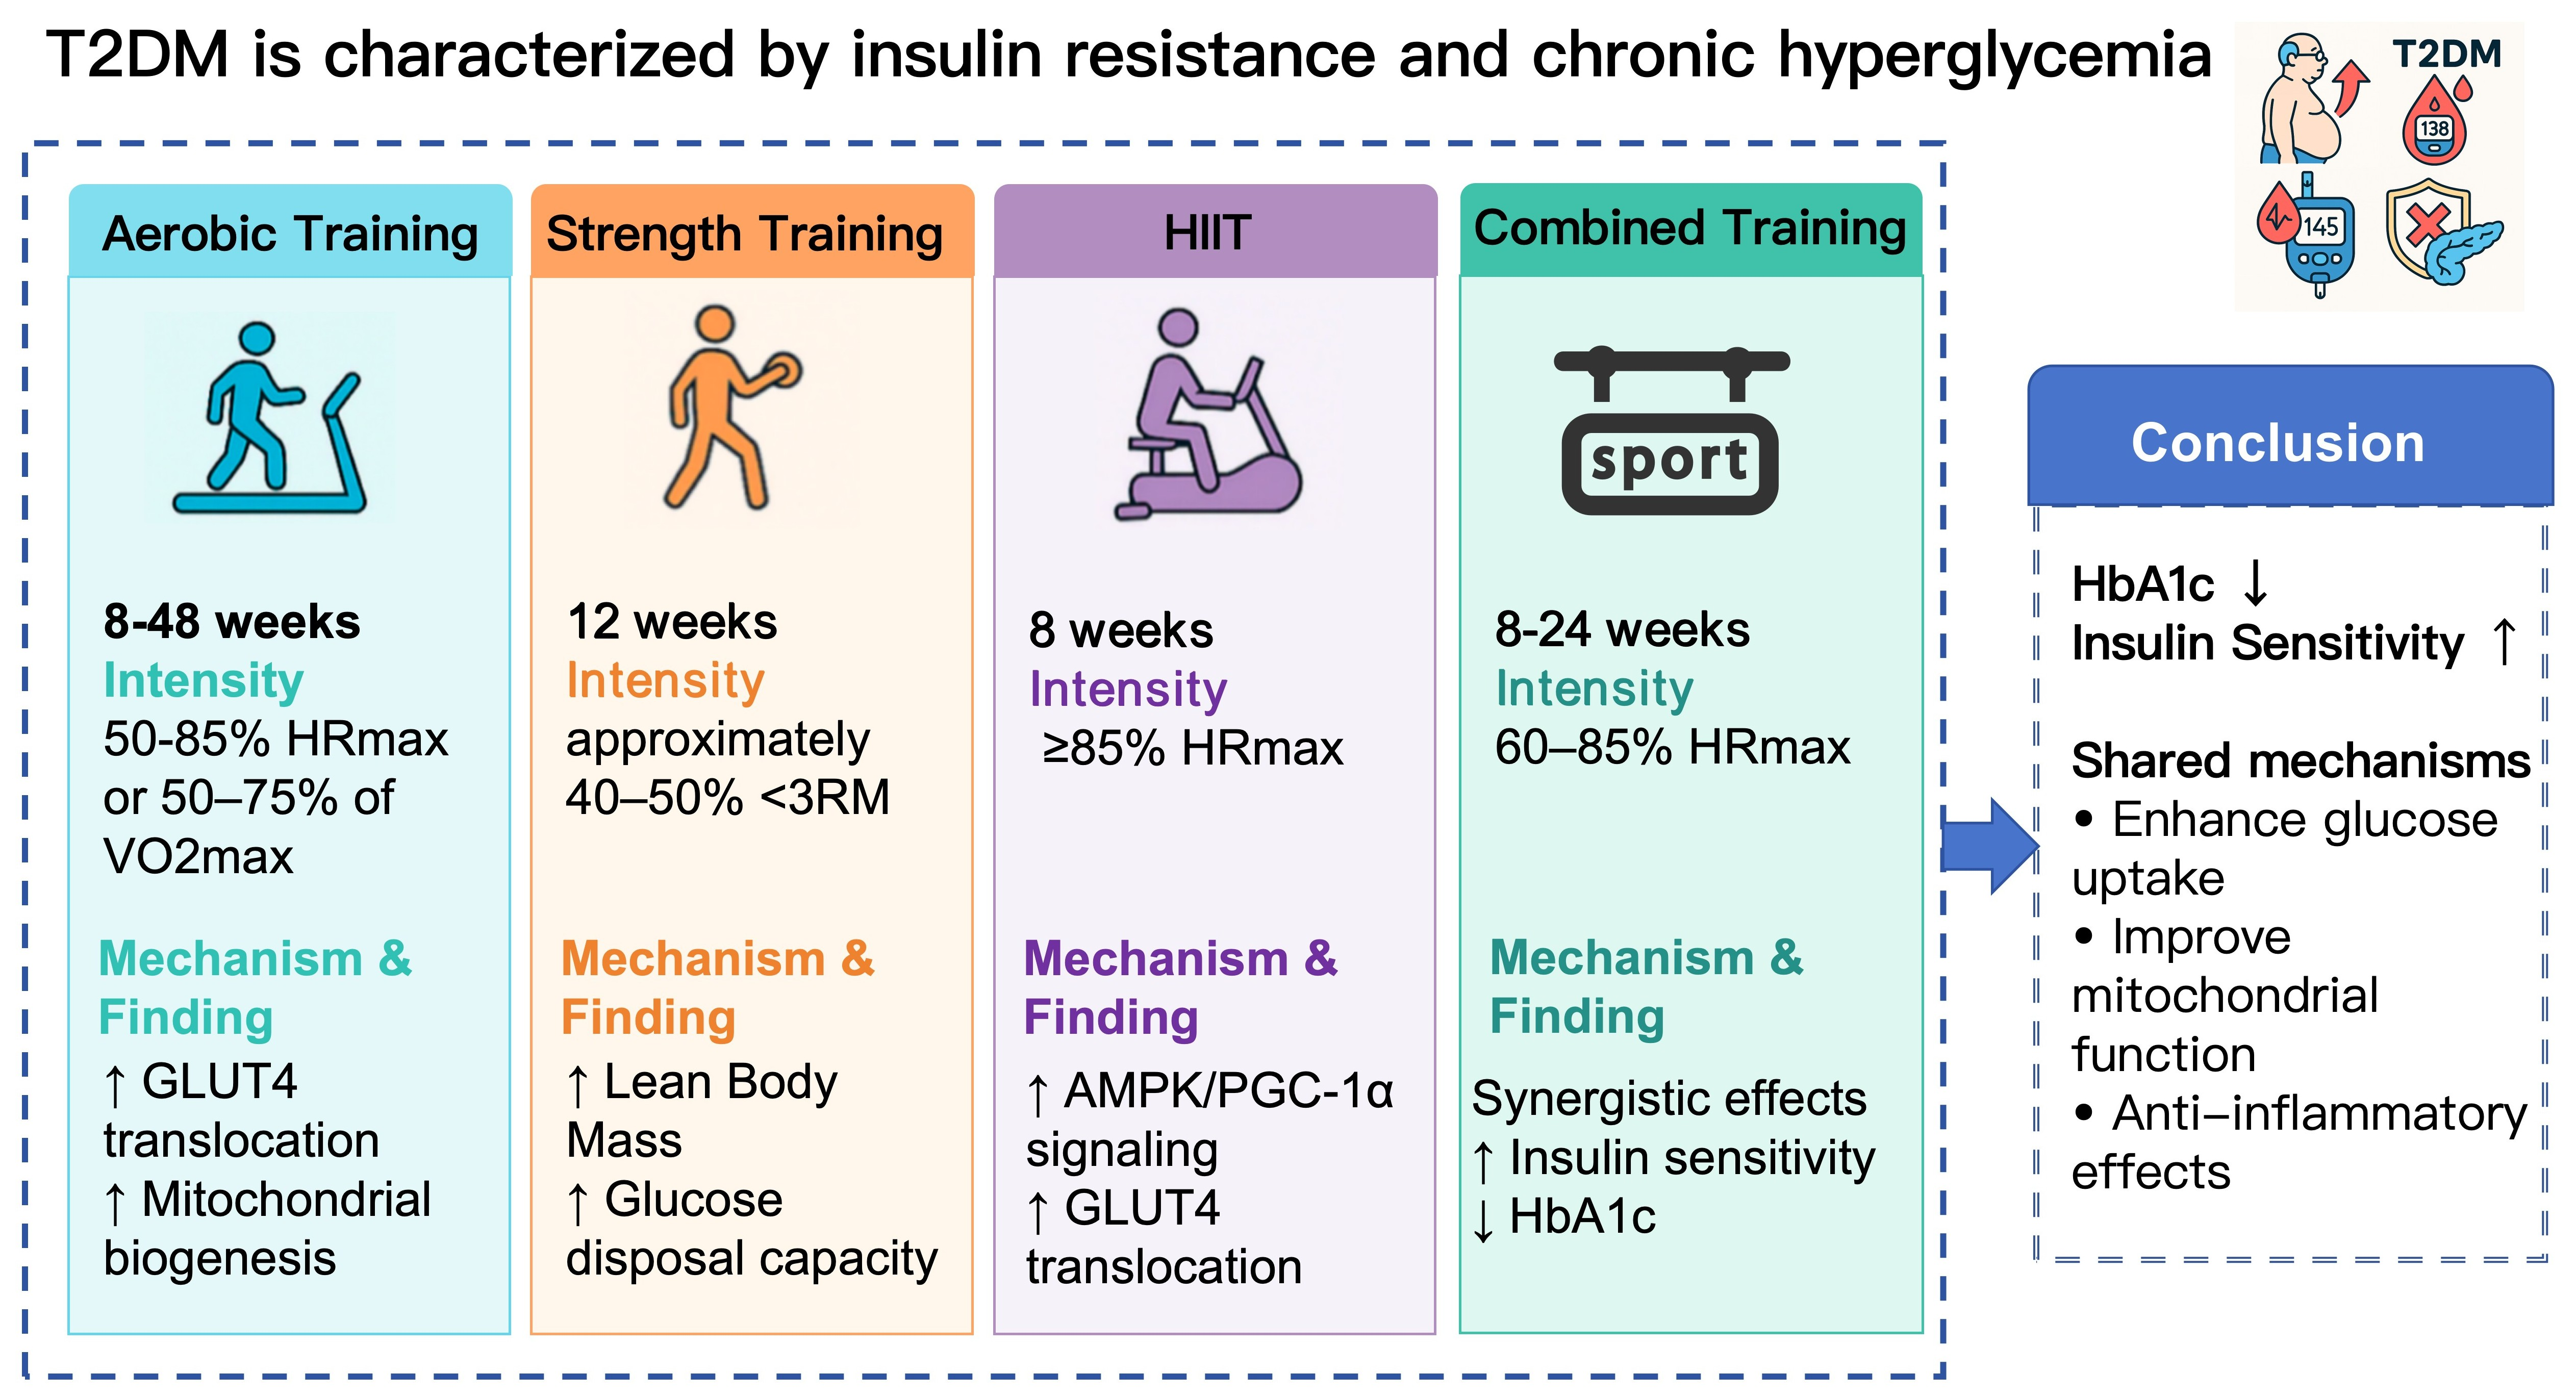
Here's where I've seen good intentions go wrong. The first mistake is ignoring foot screening. Type 2 neuropathy doesn't care how fit someone looks. I had a client who was doing station cycling for three months, felt great, lost fifteen pounds, and then came in with a plantar ulcer he didn't feel because his sensation was gone from the toes up. That ulcer took six weeks to heal and nearly cost him a toe amputation. After that, every assessment includes a monofilament test and a quick visual inspection of the soles. It takes forty-five seconds and it saves careers. The second mistake is assuming all cardio is equal. With Type 2, resistance training actually matters more than people think for glucose disposal, but it also spikes blood pressure differently than steady-state work. I recommend a hybrid approach, but the ratio depends on the person's cardiovascular baseline. If their resting heart rate is under 70 and BP is controlled, you can push harder on the resistance side. If not, you stay in the Zone 2 cardio range until those numbers improve. Here's a counter-intuitive point: people with well-controlled Type 2 diabetes often have lower resting heart rates and better VO2 max than sedentary controls, but their heart rate recovery after exercise is slower. This is a subtle autonomic marker that most general trainers miss. I started tracking one-minute HR recovery after every session, and it became one of my earliest warning signals when someone's metabolic control was drifting without their HbA1c showing it yet.
Get the Full Details

What the Assessment Actually Looks Like
I run a roughly forty-five-minute initial assessment. The first fifteen minutes are paperwork and vitals: HbA1c, fasting glucose, BP, resting HR, weight, BMI, and waist circumference. Waist matters more than most people realize because visceral fat drives insulin resistance independently of total body weight. A waist over 40 inches in men or 35 in women changes the exercise prescription even if BMI looks fine. The next ten minutes are movement screening. Not a full functional movement screen, just the essentials: ankle dorsiflexion, hip hinge pattern, overhead squat attempt, and a single-leg balance test. Type 2 people often have tighter hips and ankles from years of sitting, and if you stack heavy squats on top of that without addressing the mobility first, you're asking for lower back issues. Then comes the cardio baseline. I use a talk test plus a submaximal walk or cycle, targeting 60% of max HR. Max HR calculation here is tricky because some diabetes medications affect heart rate response. Beta blockers blunt the HR response, so someone on metoprolol might have a resting HR of 55 and never go above 100 even at hard effort. In those cases, I rely more on perceived exertion and talk test than raw HR numbers. This is another nuance beginners miss completely.
The final twenty minutes are education and plan building. I show the person what their numbers mean, set two or three measurable goals, and build a starting template that they can follow for four weeks before coming back for reassessment. Most people respond well to the four-week cycle because it's short enough to stay motivated but long enough to see real change in fasting glucose and body composition.
Edge Cases That Change Everything
I want to mention one specific problem I ran into recently that isn't in any textbook. A client of mine with Type 2 was on basal-bolus insulin, and his fitness assessment showed excellent cardiovascular status, great mobility, and solid baseline numbers across the board. Standard protocol would have been to clear him for everything. But when I asked about his meal timing relative to workouts, he said he usually trained in the afternoon without eating beforehand because he didn't want to spike his glucose. That's the trap. Training fasted on basal-bolus insulin, especially with a rapid-acting mealtime component still active from lunch, can send glucose into the basement within forty-five minutes of moderate effort. I rewrote his plan to include a small carbohydrate snack before sessions and switched his afternoon insulin to a slightly lower bolus on training days. His A1C dropped from 7.8% to 6.9% over three months, and he never had a single hypoglycemic event during exercise. The assessment caught something a standard fitness test would have missed entirely. Another edge case: diabetic nephropathy. If someone has Stage 3 or higher CKD, heavy resistance training with Valsalva maneuver can spike intrathoracic pressure in ways that stress the kidneys. I learned this the hard way with a client whose creatinine jumped after a particularly intense lower body session. After that, anyone with known nephropathy gets a modified resistance protocol that emphasizes higher reps at lower load, no breath-holding, and closer monitoring of post-session hydration status.
What Doesn't Work
Be honest about the limitations. Fitness assessment for Type 2 diabetes doesn't replace medical management. No amount of good exercise data overrides poorly controlled blood sugar. If someone's HbA1c is 10%, the first conversation is about getting their medication and nutrition in line before you start building an exercise program. Exercise at that level is secondary, and pretending otherwise does nobody any favors. Also, standard fitness assessments miss the psychological layer. Type 2 diagnosis carries a lot of guilt and shame that most trainers aren't equipped to handle. People who are stressed about their health numbers often underreport their actual behavior, which skews your assessment data. I factor this in by asking open-ended questions about daily routine before diving into numbers, and I've found that the real picture usually emerges in the third or fourth conversation, not the first. The biggest bottleneck is continuity. Most people do one assessment, get a plan, and never come back for six to eight weeks. During that gap, their condition changes, their medications change, and the original plan becomes outdated or even risky. I recommend a four-week reassessment cadence for anyone newly diagnosed or recently changed on medication, and an eight-week cycle for stable long-term clients. This isn't optional, it's basic risk management.
If you're looking for a structured template to run your own assessments, the core components are: metabolic panel review, cardiovascular screening, movement baseline, neuropathy check, and a four-week reassessment trigger. You can build this from scratch or find existing frameworks, but the framework is only as good as the person implementing it and how honestly the client reports their situation.



