Why Memorizing The Strata Isn't Enough
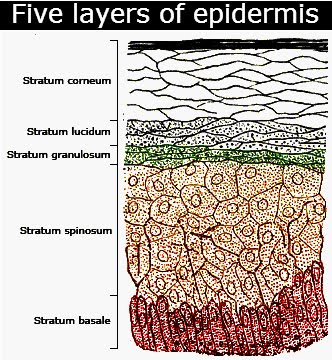
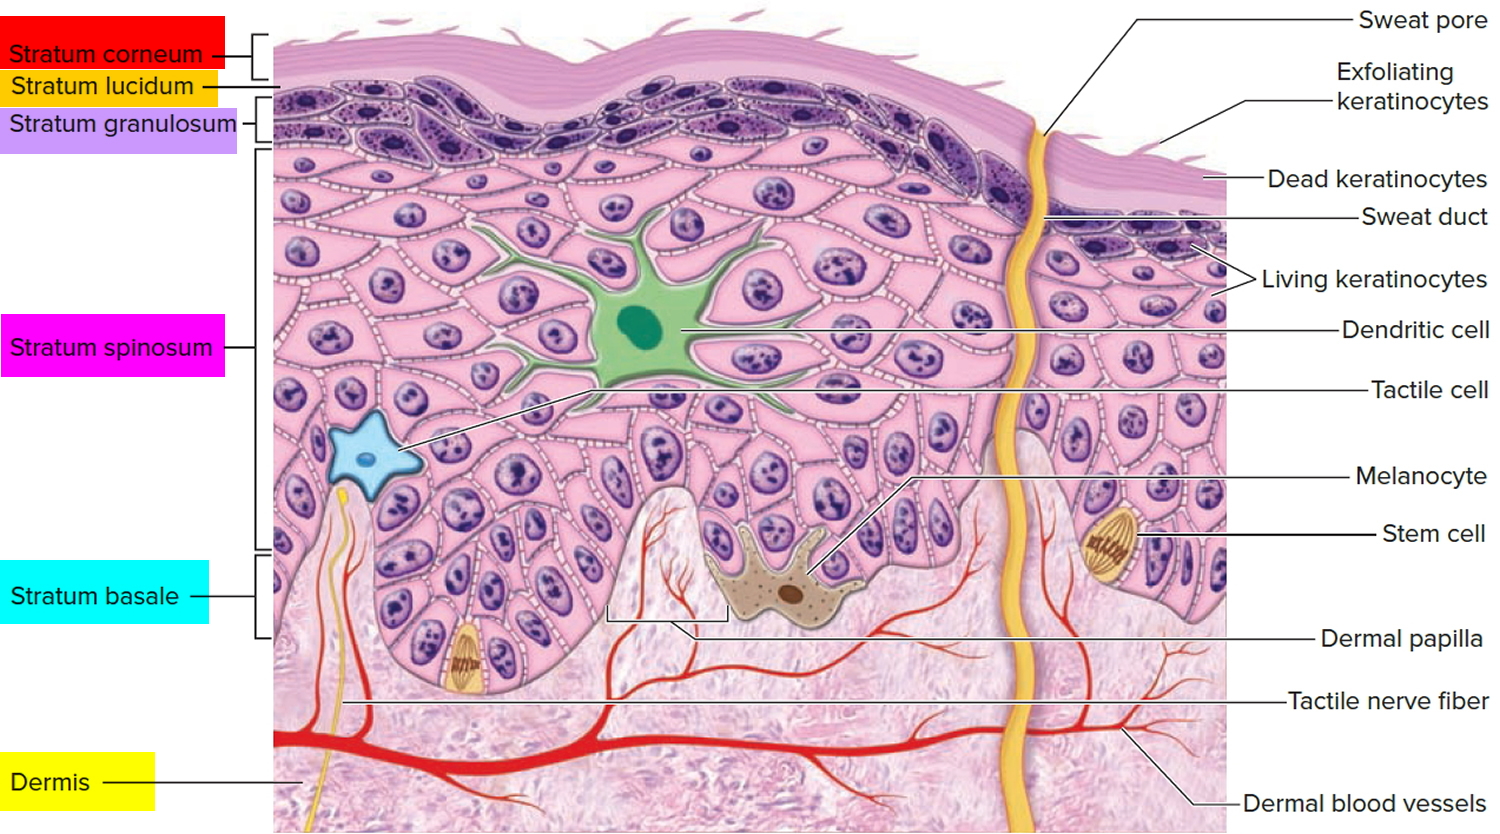
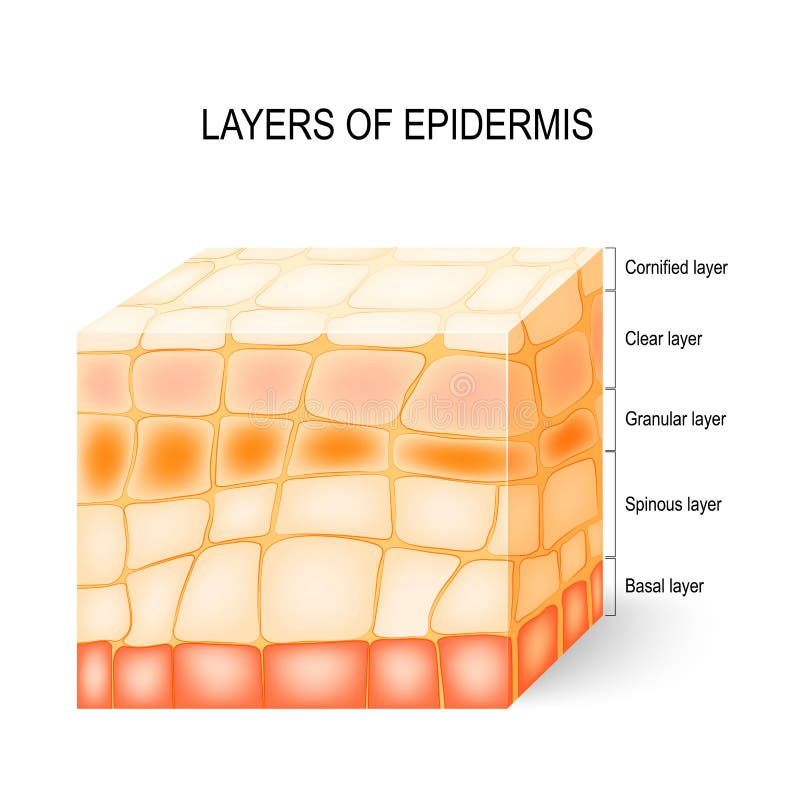
You can memorize the order — stratum basale, spinosum, granulosum, lucidum, corneum — and still have no idea what happens if you scrape your knee on concrete. I learned that the hard way during my first dermatology rotation. The textbook describes the Five Layers Of The Epidermis as a neat little ladder, but in practice, they behave more like a shifting workforce. Each layer has a different turnover rate, a different vulnerability, and a completely different response to trauma or chemical exposure. When you're actually treating a wound or interpreting a biopsy, the difference between those layers is the difference between knowing what's healing and what's about to fail. The stratum basale sits right above the basement membrane and that's where the whole show starts. Basal keratinocytes divide there, pushing new cells upward. These cells are cuboidal, tightly packed, and full of keratin filaments called tonofilaments. If you've ever watched a healing abrasion under magnification, you'll notice the basale is the only layer that actually reproduces. Everything above it is already committed to its fate. I've seen cases where a superficial burn only damaged the upper layers and the patient was told they'd heal fine, but the basale was compromised too. The skin didn't regenerate properly and ended up with significant scarring. Knowing which layer was hit matters more than you'd think. From there you move into the stratum spinosum. These cells are polyhedral and connected by desmosomes, which gives them that spiny appearance under a microscope — not that it matters much clinically. The spinosum is where Langerhans cells live. They're your immune surveillance team in the skin, antigen-presenting dendritic cells that catch pathogens before they get deeper. This is also where the cell-to-cell adhesion is strongest. If you're dealing with any condition that weakens desmosomal bonds, like pemphigus vulgaris, the spinosum is the first place you'll see acantholysis — cells pulling apart from each other and creating blisters. I had a patient whose oral blisters were misdiagnosed as canker sores for months. The histology showed suprabasal split with acantholytic cells, classic pemphigus. A simple immunofluorescence test would have caught it weeks earlier.
The stratum granulosum is the transition zone. Keratinocytes here start producing keratohyalin granules and lamellar bodies. The granules contain filaggrin, which aggregates keratin filaments and helps form the protein matrix of the final barrier. Lamellar bodies secrete lipids that fill the space between cells — these are the mortar in the brick-and-mortar analogy you'll see everywhere. When the granulosum is disrupted, water loss skyrockets. I worked with a neonatal ICU where premature infants lacked sufficient lamellar body production. Their transepidermal water loss was so severe that standard humidity therapy wasn't enough. We had to apply lipid-rich topical emollients every four hours and monitor electrolytes constantly. It wasn't glamorous but it was the difference between survival and systemic dehydration. The stratum lucidum is a thin, translucent layer found only in thick skin — palms and soles. It's essentially a condensed version of the granulosum where cells are packed with eleidin, an intermediate protein that converts to keratin. Most people don't have it elsewhere on their body. If you're reading a histology slide and can't find the lucidum, that doesn't mean something is wrong. It just means the sample came from thinner skin. I once had a med student insist there was a missing layer on a forearm biopsy because she couldn't locate the lucidum. She'd been taught the five-layer model as universal and was genuinely confused. The real issue was her expectation, not the specimen. Finally, the stratum corneum. This is the outermost barrier, made up of 15 to 20 layers of corneocytes — dead, flattened, anucleate cells filled with keratin and surrounded by a cornified envelope. These cells are embedded in those lamellar body-derived lipid layers. Together they form the skin's actual physical and chemical barrier. The corneum is what keeps things out and keeps water in. It's also the layer that determines how effectively topical medications penetrate. If a drug can't get through the corneum, the rest of the epidermis is irrelevant. I've seen prescription compounding pharmacies waste thousands on formulations that looked perfect on paper but never got past the stratum corneum in real patients. Particle size, vehicle selection, and occlusion strategy matter far more than the active ingredient concentration in most cases.
What Nobody Tells You About Epidermal Layers
The biggest misconception is that the layers exist as distinct, separate bands. They don't. There are no clean borders between them. The transition from basale to spinosum is gradual, the shift from spinosum to granulosum happens over several cell divisions, and the corneum blends imperceptibly into the surface debris you see as flaky skin. When pathologists describe "loss of the granulosum," they usually mean the granular cell population is significantly reduced, not that the entire layer has vanished like a floor getting demolished in a movie. Another thing that trips people up is the assumption that all five layers are always present in every sample. Thick skin and thin skin differ dramatically in their layer composition. Thin skin — which covers most of the body — may have a well-developed granulosum but a very thin or virtually absent lucidum. Thick skin has all five but often with a corneum that's hundreds of cells deep. Comparing a palmar biopsy to a dorsal hand biopsy and expecting them to look similar is a fast track to misdiagnosis. Here's something I wish had been drilled into me sooner: the turnover time from basale to corneum to shedding is roughly 28 to 42 days in healthy adult skin, but that clock speeds up dramatically when the skin is injured or under stress. In psoriatic plaques, the turnover can be as fast as 3 to 5 days. The cells never fully mature before they're pushed to the surface, which is why psoriatic scales are thick, silvery, and filled with parakeratotic cells — nucleated corneocytes that should have lost their nuclei long before reaching the surface. I spent weeks trying to understand why a particular patient's topical steroid wasn't working on their scalp psoriasis. The issue wasn't the steroid strength. It was the turnover rate. The medication was being sloughed off faster than it could penetrate. Adding a keratolytic like salicylic acid to thin the scale first changed everything. The steroid then had actual access to the viable epidermis below.
Get the Full Details
A practical consideration most people overlook is how the layers respond differently to the same insult. Sun exposure damages the basale first — that's where the DNA mutations accumulate and where most sun-induced malignancies originate. But the clinical signs, the thickening and leathery texture of actinic cheilitis or solar elastosis, are visible in the corneum and spinosum. By the time you see the damage, the basal layer has been accumulating mutations for years. This is why sunscreen recommendations targeting the surface are actually about protecting the deeper germinative cells that you can't see. It's counter-intuitive but critical. If you're studying this for an exam, focus on function over memorization. Knowing that the basale divides, the spinosum adheres and surveils, the granulosum produces barrier lipids and keratin precursors, the lucidum exists only in thick skin, and the corneum is the actual barrier will serve you better than repeating the layer names in order ten times. When you understand what each layer does, you can deduce the consequences of damage to each one. That's the skill that actually transfers to clinical practice. One more thing worth noting: the epidermis isn't static. Its thickness varies by body region, age, hormonal status, and mechanical stress. A callus on your heel is literally the corneum and spinosum thickening in response to friction. Pregnancy alters melanocyte activity in the basale, which is why the linea nigra appears. Aging thins the entire epidermis, especially the basale and spinosum, which is why older patients bruise more easily and heal slower. The five-layer model is a useful framework, but it's a snapshot of a system that's constantly adapting.