What You Actually Need to Know About NPWT for Necrotizing Fasciitis
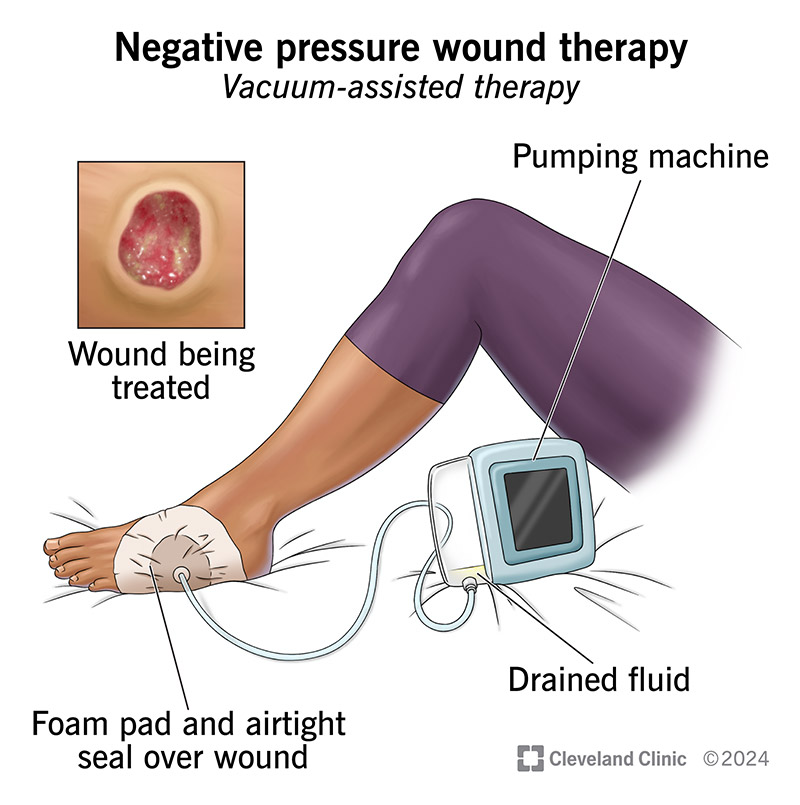
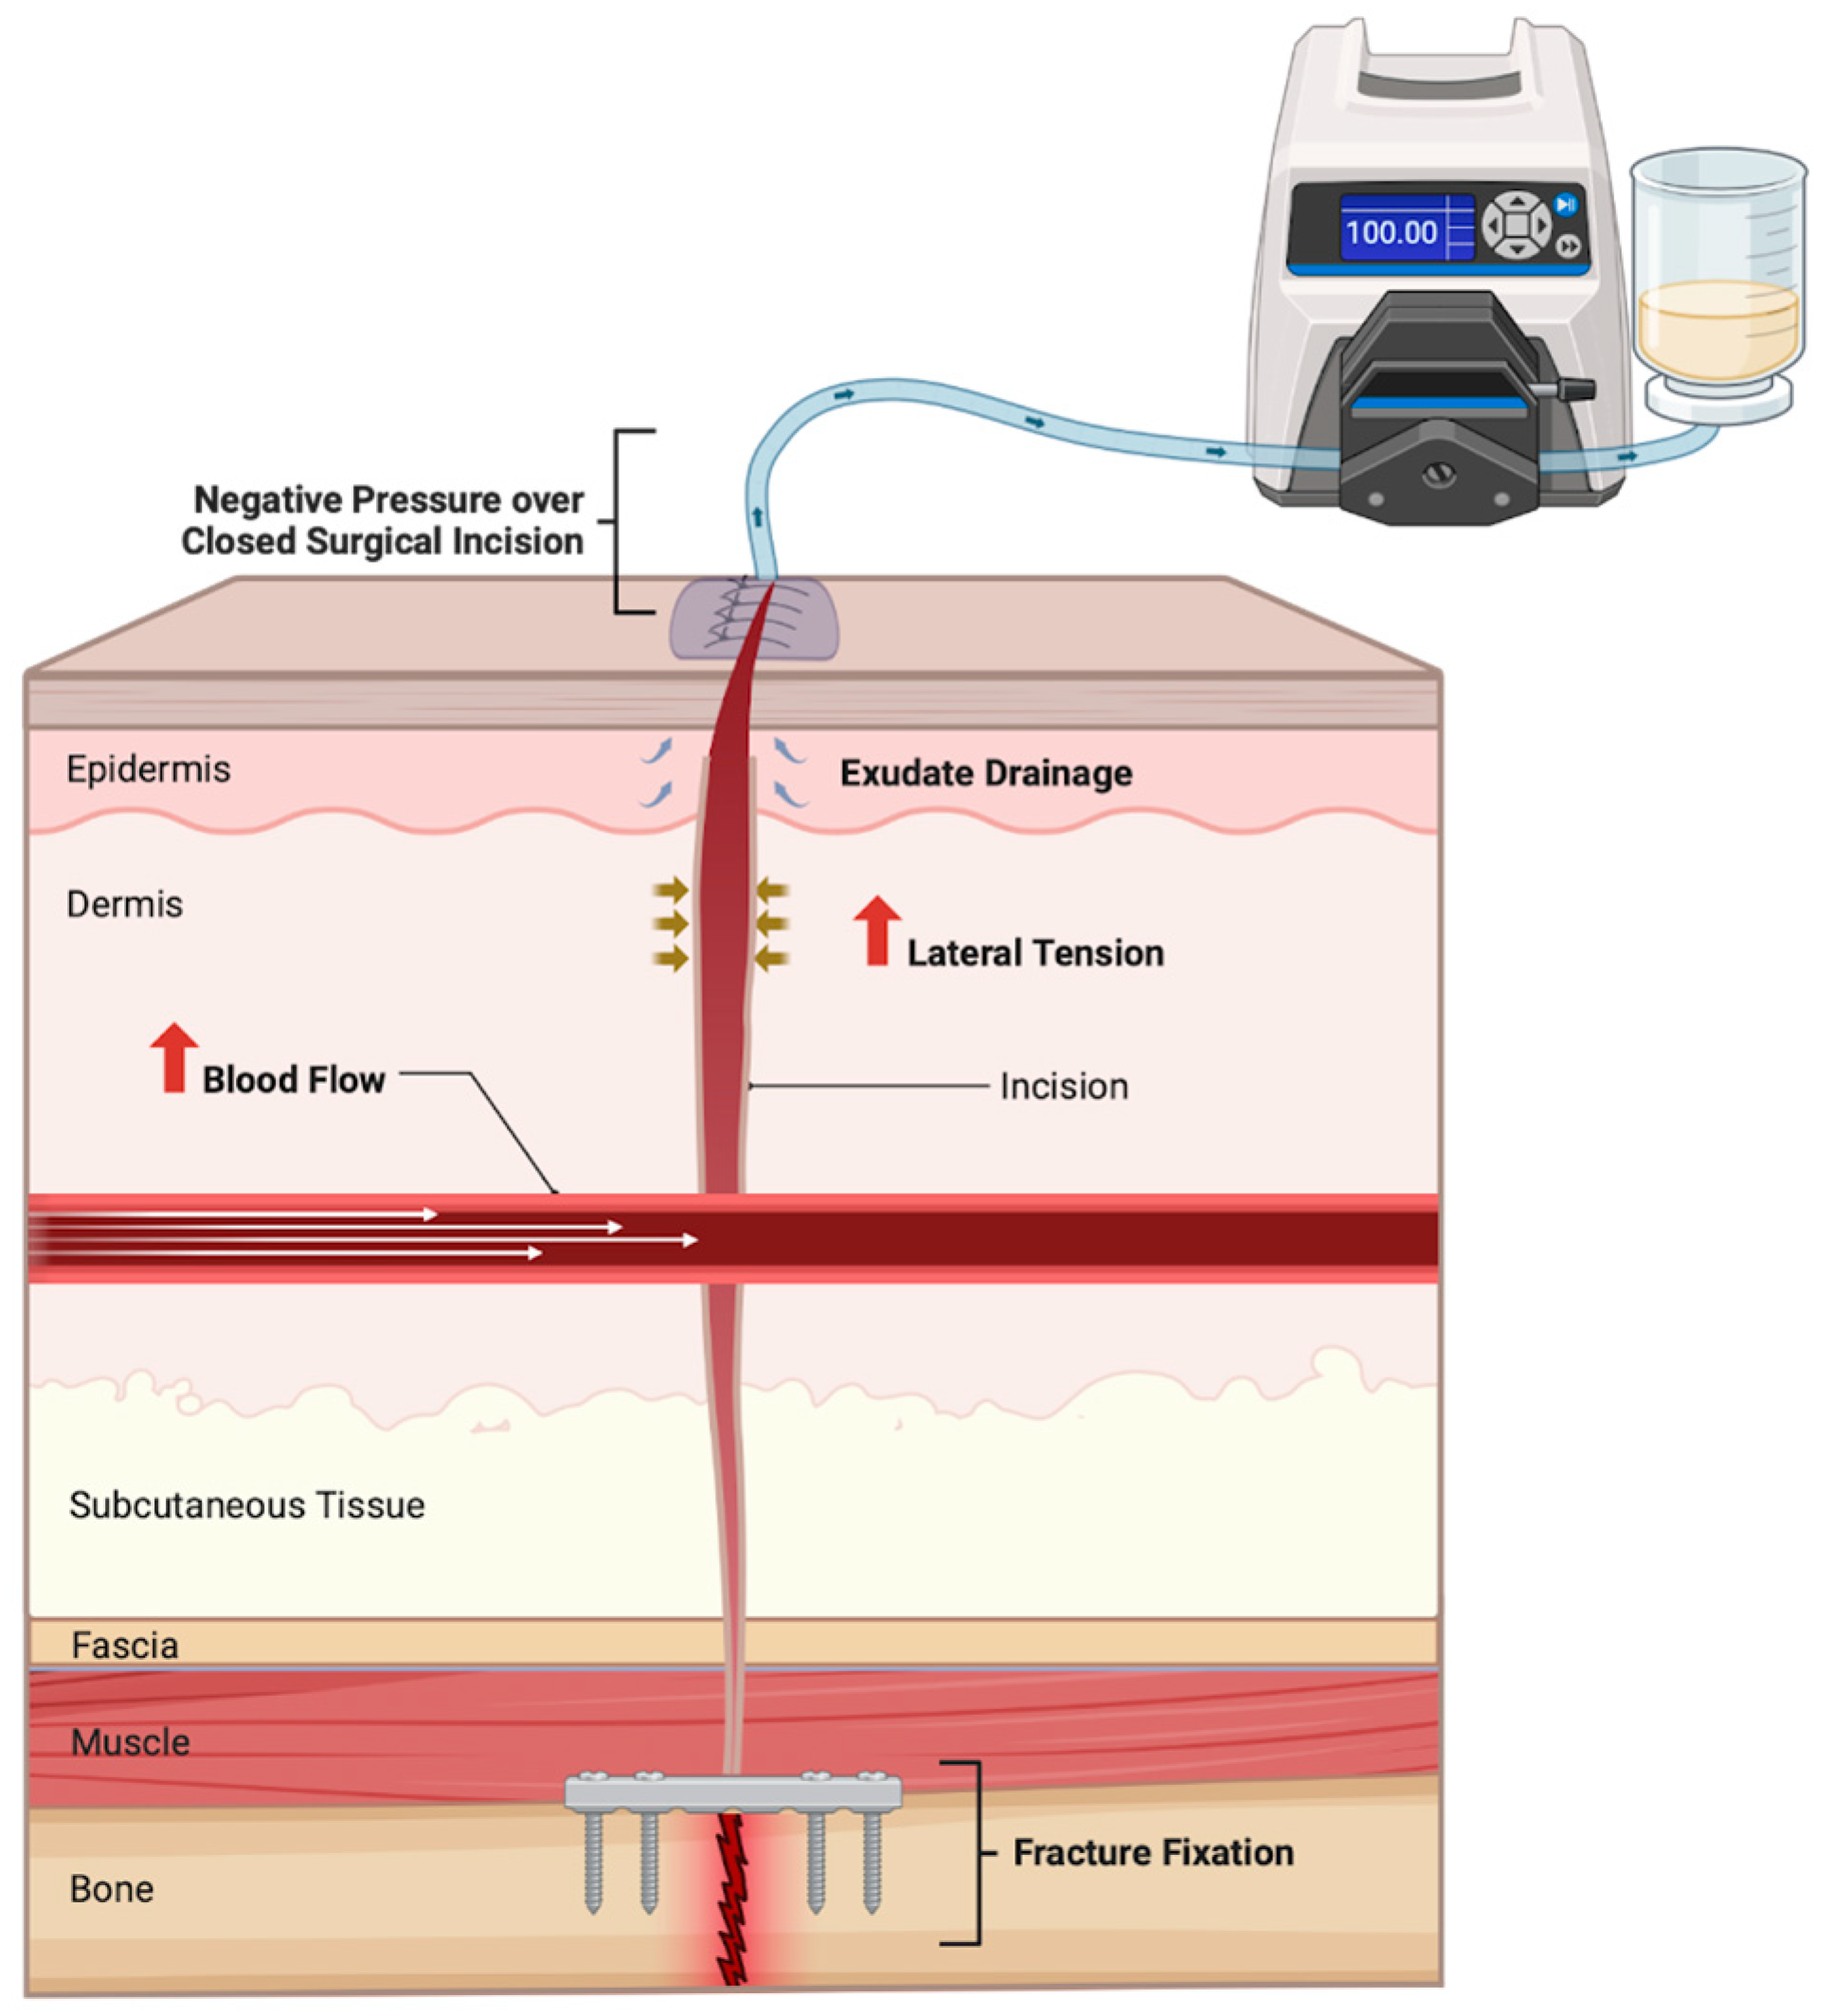
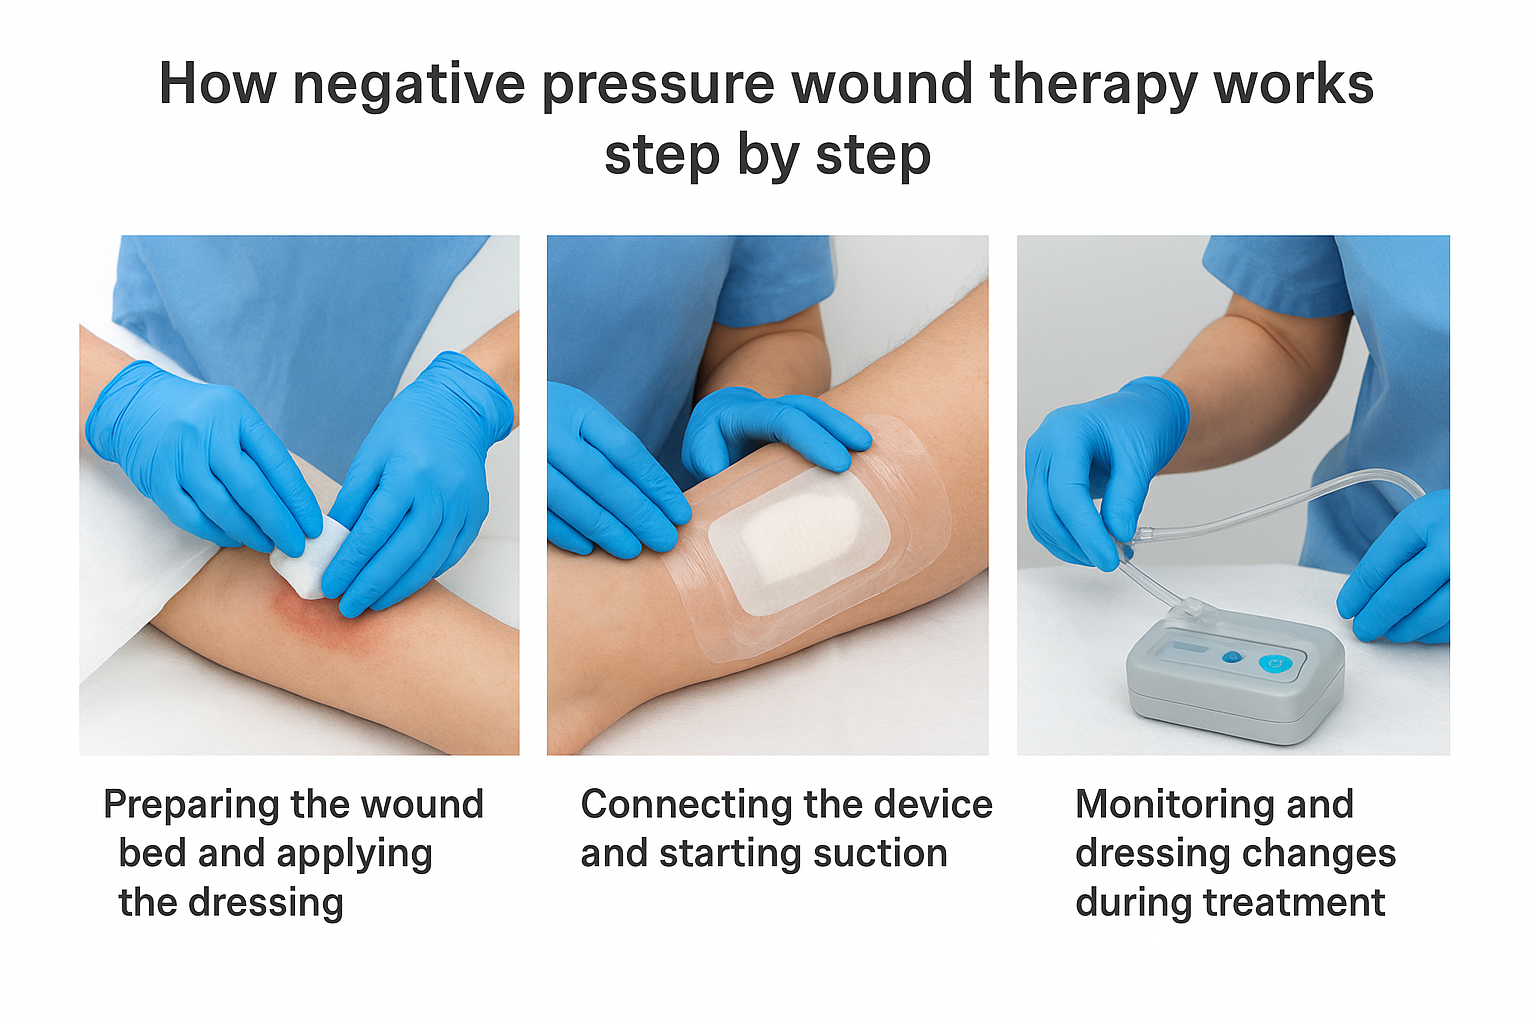
Necrotizing fasciitis is a surgical disease first and foremost. Negative pressure wound therapy is a wound management tool that comes into play after the surgeons have already done the hard part. I have seen too many people conflate the two. They are not the same thing. If you are reading this because you or someone you know has been diagnosed and you are looking for a magic bullet in a wound vac, you need to understand where the therapy actually fits in the treatment pathway. The standard protocol for necrotizing fasciitis begins with emergent surgical debridement. This is not elective. The surgeon cuts out dead and dying tissue until they reach bleeding, viable tissue. Often this requires multiple return trips to the operating room over several days. Once the surgical team determines the wound bed is clean and the infection is controlled, that is when NPWT becomes relevant. The device applies controlled subatmospheric pressure through a sealed dressing to promote granulation tissue formation, reduce edema, and manage exudate. It accelerates wound healing by mechanical strain on the tissue, which upregulates certain growth factors and increases local blood flow. The typical settings I see used are between 125 and 175 mmHg in continuous mode for large soft tissue defects. Intermittent mode at similar pressures can sometimes be better tolerated by the patient. The foam type matters. Open cell polyurethane foam is standard for most NPWT applications because it collapses under negative pressure, drawing the wound edges together. Closed cell foam has a semi-permeable membrane on one side and is used in different clinical scenarios. For a necrotizing fasciitis wound that has required extensive debridement across the chest or abdomen, open cell foam is almost always the choice.
Here is something most patient education materials do not emphasize. NPWT does not treat the infection itself. It manages the wound after infection control has been achieved surgically. If there is still viable infected tissue in the wound bed, putting a negative pressure device on top of it is dangerous. The sealed environment can actually promote bacterial proliferation if the source control is incomplete. My rule of thumb has always been straightforward: no granulation tissue yet, no NPWT. Period. I ran into a specific problem with a pelvic and perineal wound after extensive debridement for Fournier's gangrene, which is a form of necrotizing fasciitis. The standard rectangular foam dressing would not maintain a seal because of the anatomical contours. Every time the patient sat up, the dressing lifted and the vacuum was lost within minutes. The wound vac alarm went off constantly. What worked was cutting a custom-shaped piece of foam to fit the perineal region, using a combination of adhesive barrier rings around the entire perimeter, and applying the drape in a tension-free figure-eight configuration rather than a simple flat drape. This took about twenty minutes of adjustment that initial providers had not anticipated. I also switched to a smaller canister-based portable unit instead of the wall-mounted pump because patient mobility through the house was becoming impossible with the floor unit. There are real limitations to this therapy that deserve blunt acknowledgment. NPWT is expensive. A single change of dressings runs roughly $800 to $1,500 depending on wound size and insurance negotiations. Sessions typically last three to seven days before the dressing needs to be changed, but some complex wounds require changes every 48 hours. The therapy is contraindicated in wounds with untreated osteomyelitis, malignancy in the wound bed, or exposed blood vessels and organs without protective coverage. Some studies suggest a possible increased risk of bleeding if the negative pressure disrupts newly formed fragile vasculature during dressing changes. The literature on NPWT specifically for necrotizing fasciitis is still limited compared to other wound types, and most evidence comes from case series rather than randomized controlled trials.
A counter-intuitive point that beginners miss: NPWT can sometimes mask ongoing infection. The dramatic reduction in wound drainage that occurs within the first 24 to 48 hours of application can create a false sense of security. The vacuum is literally removing exudate, so less drainage does not necessarily mean less infection. You still need serial clinical assessments, inflammatory marker tracking, and a low threshold for returning to the operating room if the patient becomes clinically deteriorated regardless of what the wound vac is showing. For patients who are candidates, the typical timeline looks like this. After the final debridement surgery, once the wound is deemed clean, NPWT is applied. Dressing changes occur every 48 to 72 hours initially. As granulation tissue fills the defect, the interval between changes may extend. Once the wound is sufficiently healed, either split-thickness skin grafting or secondary intention healing takes over. The entire process from initial surgery to definitive closure usually spans several weeks to a few months depending on the original extent of tissue loss. If you are managing this condition, the single most important factor remains early and aggressive surgical intervention. NPWT is a supportive modality, not a replacement for adequate source control. The wound care team, infectious disease specialists, and surgical teams need to be working in parallel from day one. Nothing about this condition allows for hesitation or second-guessing in the acute phase.
Get the Full Details