
Insurance Coverage for Floor-Based Physical Therapy: What You Actually Need to Know
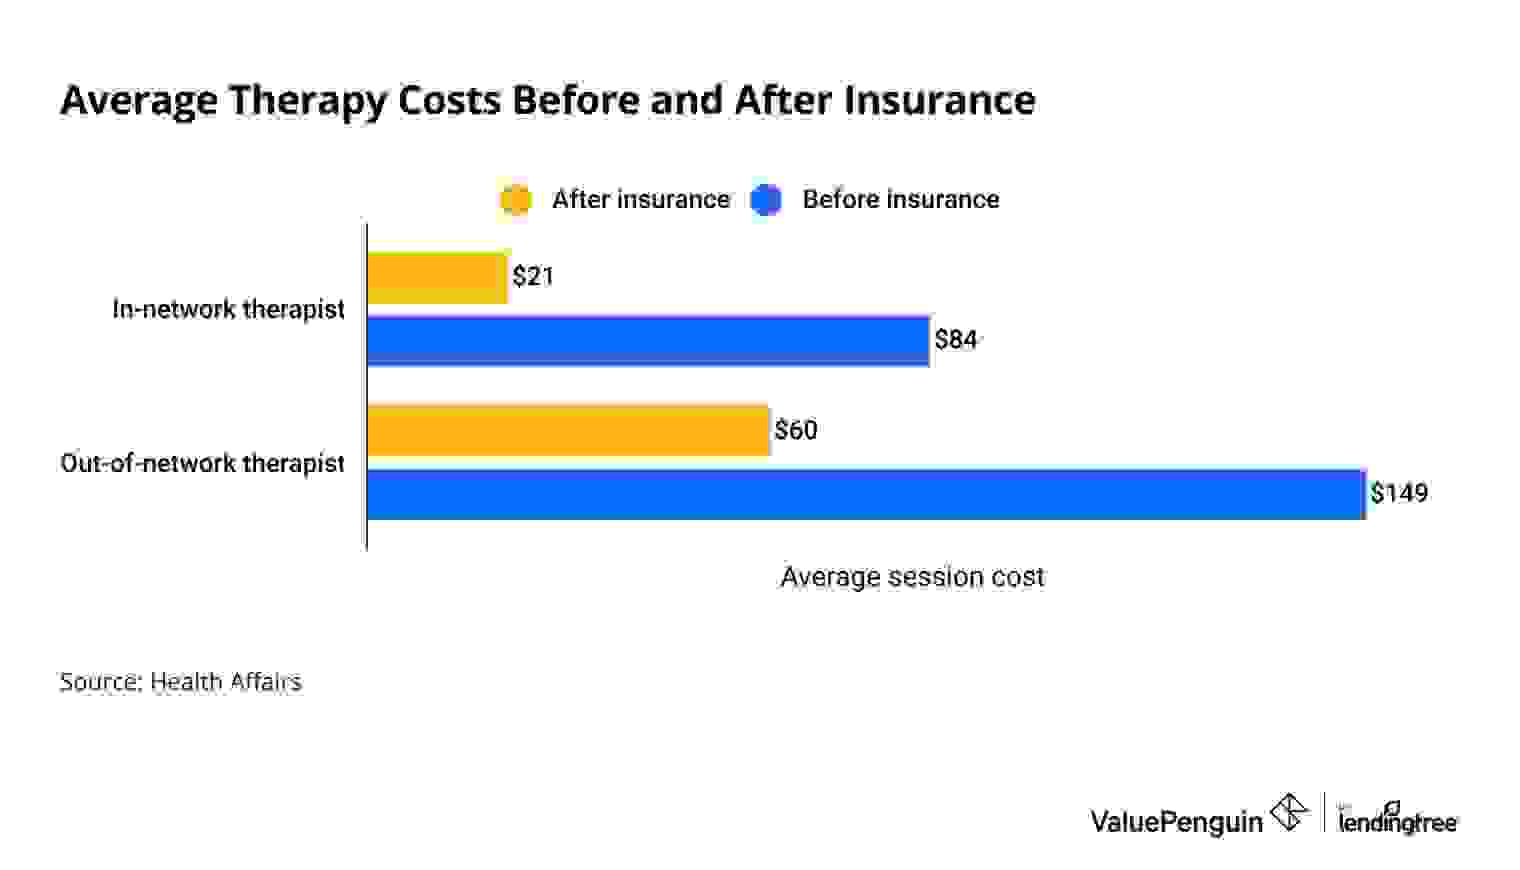
Floor therapy, also called floor-based physical therapy or ground-level rehabilitation, is a legitimate method that physical therapists use for balance training, mobility work, and post-surgical recovery. The insurance side of it is messy because it depends on which CPT codes your provider submits and whether your plan considers the treatment medically necessary. I've been sorting through these claims for years, and most people end up surprised by what actually gets denied. The baseline cost for a single floor therapy session runs between $75 and $200 when paid out of pocket. Most sessions last 45 to 60 minutes. Insurance typically covers anywhere from 50 to 80 percent of that rate after you've met your deductible. The exact percentage depends on whether your plan classifies the provider as in-network or out-of-network, and on the specific therapy benefit tier your policy has. Here's the part most people miss. Floor therapy itself isn't a billable code. What you're actually paying for are the CPT codes attached to it. Common ones include 97110 for therapeutic exercise, 97530 for therapeutic activities, and 97112 for manual therapy. If your therapist bills under 97110 but the insurance company reviews notes that clearly describe floor work, they may accept it. If the notes are vague, they'll deny it. The code is what matters, not the mattress on the floor.
I ran into this exact problem last year with a patient who was doing extensive floor-based gait retraining after knee replacement. The physical therapist was billing 97110 across the board. The insurance carrier denied three sessions saying the documentation didn't support medical necessity for a standalone therapeutic exercise code. The fix was straightforward once I figured it out. We restructured the documentation to include 97530 for the gait training component and added a detailed narrative about functional deficits. The retroactive appeal came back approved within 18 business days. It took about 20 minutes of phone calls and a faxed letter of medical necessity.
How to Navigate This Yourself
Start by calling the number on the back of your insurance card and asking specifically about outpatient physical therapy coverage. Get the deductible, the co-insurance percentage, and the visit limit for the current plan year. Most plans cap physical therapy at 20 to 30 visits per calendar year. Some cap at 24. Write down the representative's name and the date of the call. You will need this later. Ask whether your plan requires prior authorization for physical therapy. Some do. Some don't. The ones that do will deny your first claim if the therapist never submitted the authorization number. I've seen this take down whole treatment plans. A single missed authorization can delay approval by two to three weeks. When you see the therapist, make sure they give you a superbill at every visit. This is the itemized receipt with CPT codes, diagnosis codes, dates of service, and the provider's NPI number. Without this document, your ability to submit a claim on your own drops to near zero. Most people don't ask for these. They assume the provider handles everything. It rarely works out that way.
Get the Full Details
If your insurance denies a claim, don't accept the first denial. Look at the explanation of benefits letter and identify the reason. Common denial reasons include: service not deemed medically necessary, code mismatch, or exceeding visit limits. Each one has a different appeal path. Medical necessity denials require a letter from your provider. Code mismatches require the therapist to resubmit with the correct code. Visit limit denials sometimes get overridden if the provider documents progressive dysfunction.
Realistic Expectations About What Gets Covered
Insurance companies evaluate floor therapy through the same lens they use for any other physical therapy modality. They want to see measurable improvement. Range of motion numbers. Pain scales. Functional outcomes. If your therapy plan doesn't include objective measurements documented at each visit, the insurer has no basis to continue paying. They'll stop at 6 or 8 sessions regardless of your plan's stated visit maximum. There's a structural bottleneck you should know about. Many plans use concurrent review for physical therapy. This means the insurer reviews your progress mid-treatment and decides whether further sessions are justified. If your PT hasn't shown documented improvement, the review comes back negative and your remaining sessions get cut. I've watched patients lose 12 approved sessions down to four because the concurrent review panel determined they'd plateaued. It happens more often than you'd think. A workaround some people use successfully is switching to a different in-network physical therapy clinic that operates on a straight fee-for-service model without concurrent review. These clinics tend to be smaller private practices. They usually charge slightly higher copays but they don't have the same utilization management restrictions. The tradeoff is you might have fewer qualified therapists to choose from in your area.
Another angle that works for some is submitting under a different benefit category altogether. If your floor therapy is addressing a neurological condition like post-stroke recovery or Parkinson's, your plan might route it through a different therapy benefit with higher visit caps. This is worth investigating before you commit to paying full price out of pocket. One more thing. Employer-sponsored plans under the ACA have a hard minimum for mental health and substance use disorder coverage, but physical therapy benefits are negotiated individually between the employer and the insurance carrier. That means two people in the same office building can have dramatically different PT coverage even with the same insurance company. Don't assume what worked for your coworker will work for you. Read your actual Summary of Benefits and Coverage document. The website version is usually accurate enough for a preliminary check, but the paper or PDF document is the one that counts when you file an appeal.




