Understanding Floor Therapy Cpt Code
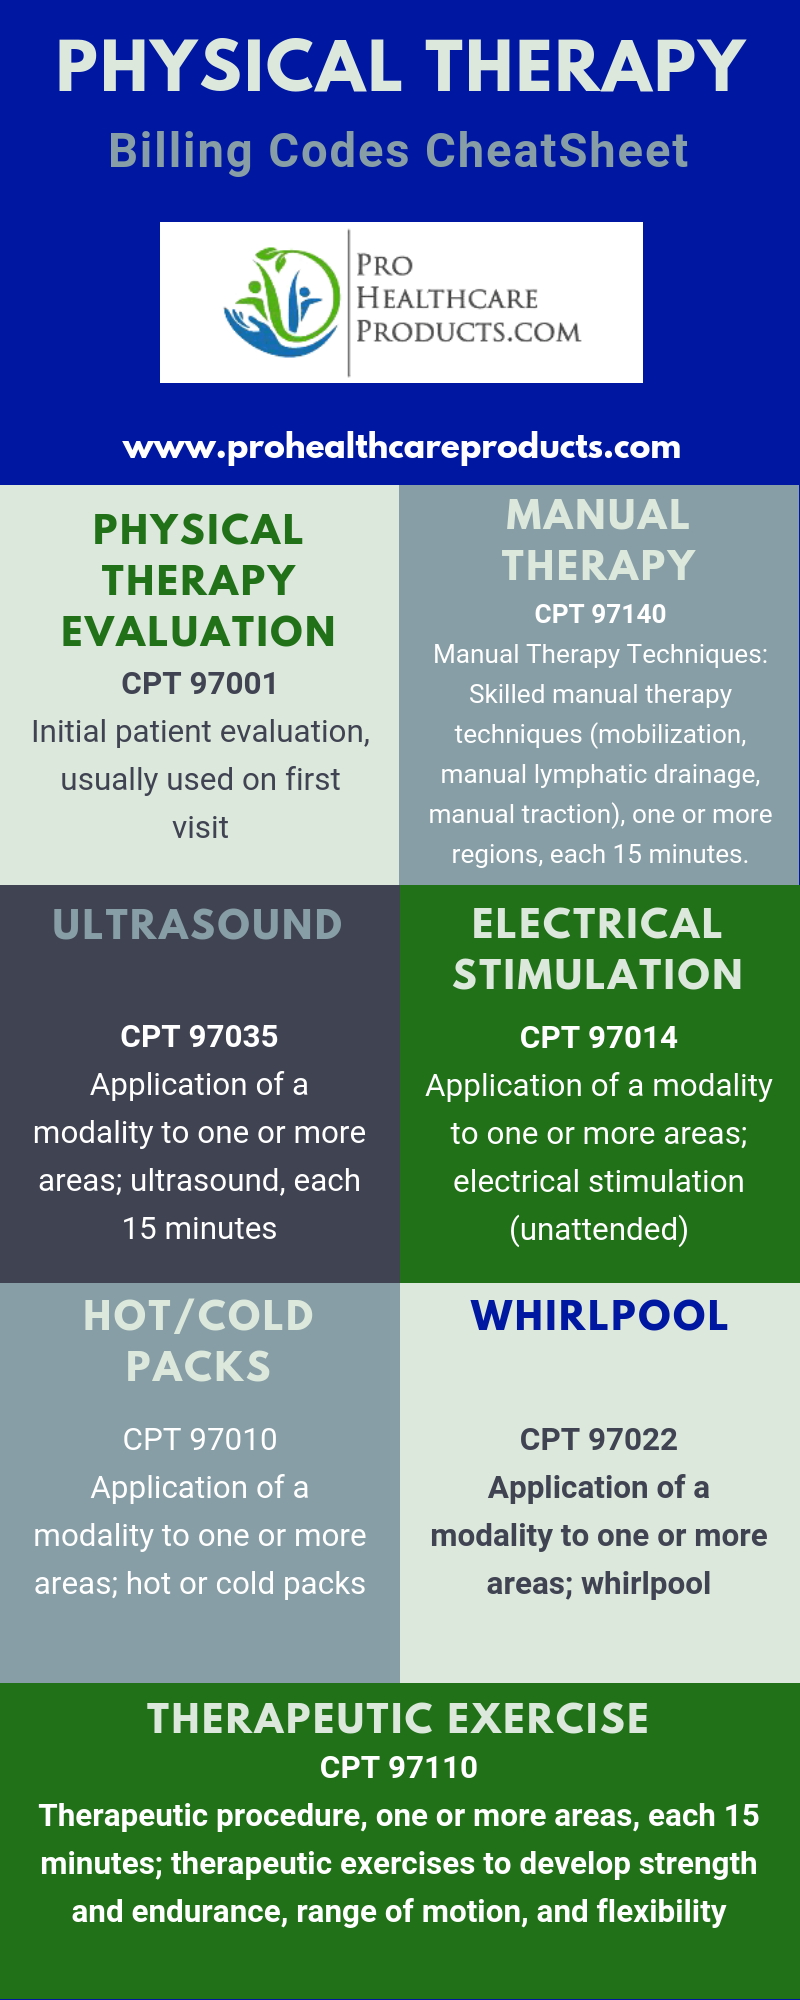
Most clinics don't actually have a single unique CPT code that says "floor therapy." What you're looking at is a collection of standard codes that describe the work being done, regardless of whether the patient is on a plinth or on a mat on the floor. The confusion comes from the fact that CPT doesn't bill by surface — it bills by intervention type. The codes you will actually use when documenting floor-based treatment fall into a few well-known buckets. 97110 — Therapeutic Exercise. This is your bread and butter. Any strengthening, stretching, range of motion work you do while the patient is prone, supine, or seated on the floor goes here. I see a lot of therapists trying to stretch this code into something it isn't, which is where the trouble starts. If you are doing hands-on assisted stretching while the patient is on the floor, that's not 97110 anymore. That is 97140. Mixing them in the same unit block without separating them is an audit trigger.
97140 — Manual Therapy. Myofascial release, mobilization, manipulation. This applies whether you are working on a table or on the floor. I ran into a specific problem last year where a payer denied a claim because I documented "manual therapy to the lumbar spine in prone" without specifying the technique. The documentation had the body part and position but none of the hands-on method. I had to resubmit with "grade III oscillatory mobilization applied to L4-L5 in prone position" and it cleared within three business days. The exact technique name matters more than you think. 97530 — Therapeutic Activities. This is for functional tasks — balance work, gait training, transfer practice. If the patient is doing squats or balance drills on the mat, this is your code. The line between 97530 and 97110 is where most people get tripped up. The difference is functional carryover. Squatting to pick up objects and working on sit-to-stand mechanics is 97530. Strengthening the quads with a resistance band in the same position is 97110. The movement looks identical. The intent is what changes the code. 97112 — Neuromuscular Re-education. Balance, coordination, proprioception work. This one is heavily underused. Motor control drills on the floor — weight shifts, controlled rocking, bilateral coordination patterns — this is 97112, not 97110. A lot of us default to 97110 out of habit because it is easier to justify. It is also easier to audit. If your notes don't show why the exercise was about motor control versus strength, you should expect pushback.
There is a nuance that nobody warns you about. Time-based billing for 97110 and 97140 uses the 15-minute unit rule, and you can combine them on the same encounter. But if you stack too many 97140 units without clear time documentation per technique, reviewers will flag it. I learned this the hard way when a Medicare Administrative Contractor requested my time records for six consecutive months. I had documented 4 units of 97140 on a 30-minute session with no per-technique time breakdown. The request was legitimate, and I was missing the data. Since then I add a note like "MFR L2-L4, 8 min" directly in the narrative instead of leaving it implied. Another thing worth noting — and this is not obvious from the code descriptions — 97110 and 97530 both require direct face-to-face contact with the therapist. If you are leaving a patient on the floor doing an exercise while you step away, that is not billable time for either code. It might qualify as unsupervised home exercise instruction, but that is a different conversation entirely. I have seen people lose 40 percent of their documented time because they were counting observation periods as billed time. Watched does not equal treated. The codes above cover roughly 90 percent of floor therapy documentation in outpatient orthopedic settings. The remaining 10 percent involves add-ons like 97010 for electrical stimulation if you are doing modalities on the mat, or 97750 for self-care management instruction if you are teaching positioning and body mechanics while the patient is on the floor. Neither is common, and both require separate time documentation if you are billing them alongside the exercise codes.
Get the Full Details
If your payer has prior authorization requirements for 97140 — and many do for more than four units in a ten-day window — make sure you are tracking that separately. The authorization check should happen before the session, not during the audit. I keep a running list in my scheduling software now. It took about twenty minutes to set up and saves me from chasing retro auth every month.