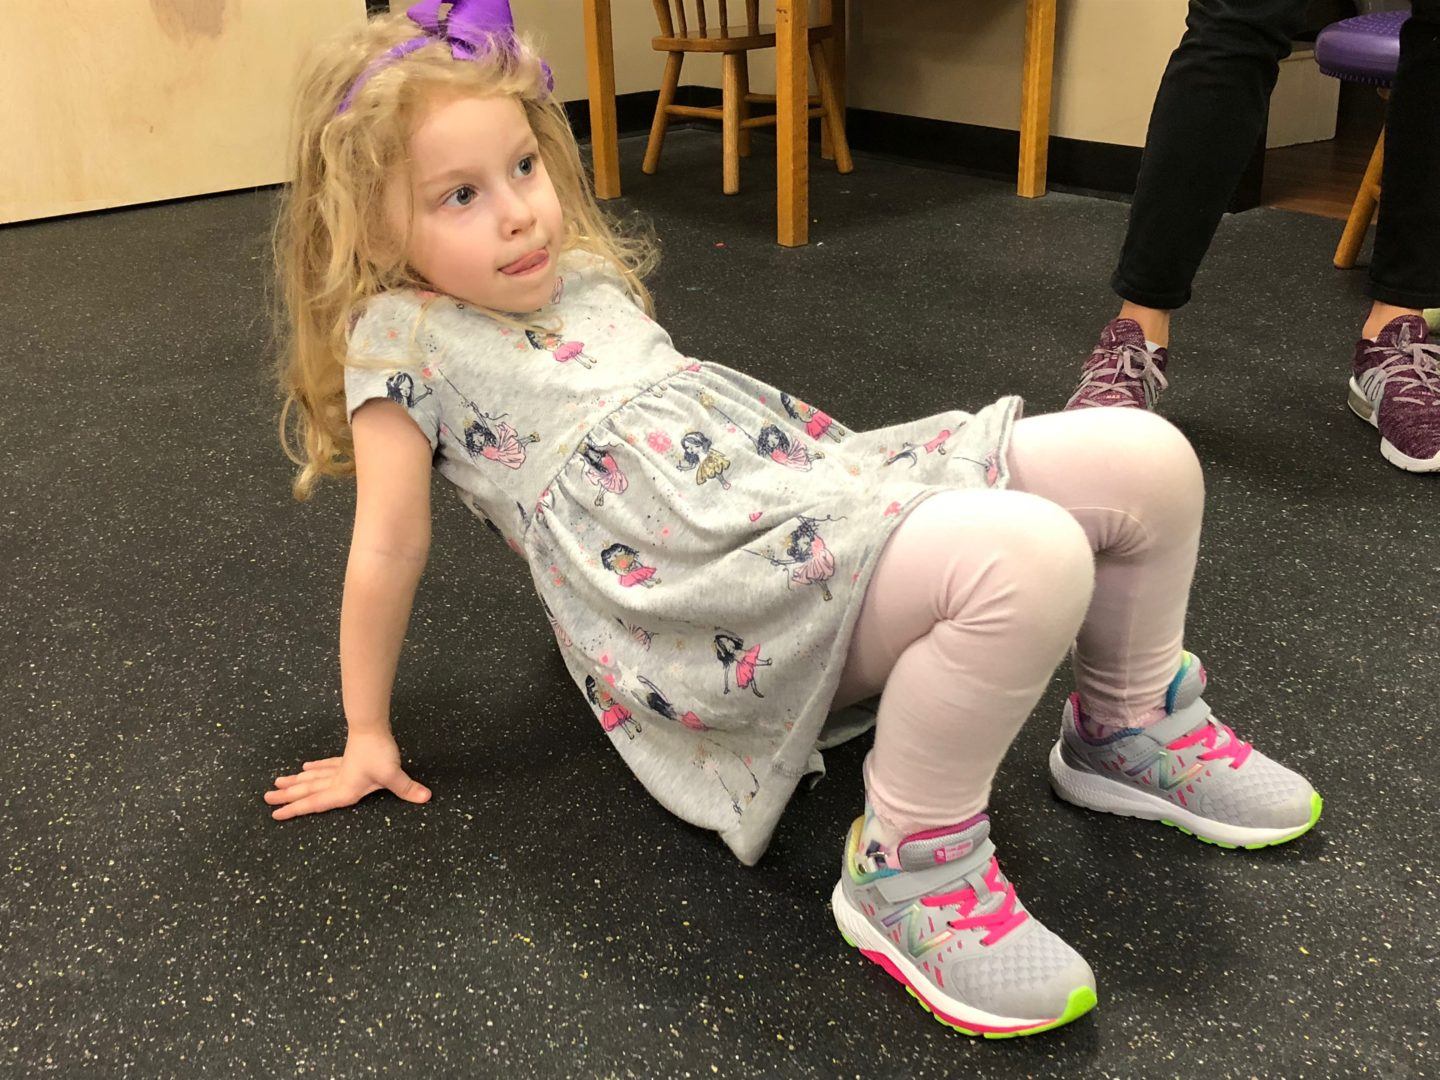
What Floor Therapy Actually Looks Like in a Pediatric Clinic
Floor Therapy Pediatric is exactly what it sounds like — children work on physical, occupational, or sensory goals while lying, sitting, crawling, or standing directly on a padded floor surface rather than using traditional equipment like therapy balls, tables, or parallel bars. It sounds straightforward until you've spent six months trying to get a child with severe proprioceptive defensiveness to tolerate any surface below a raised table. That's when you learn that the floor can be both the most effective tool and the biggest bottleneck in a therapy plan. The basic setup involves a foam mat or interlocking puzzle foam tiles, sometimes with textures layered on top, placed in a quiet corner of the clinic or a home space. You don't need expensive equipment. A standard 4x8 foot foam mat from a sporting goods store works. The difference between floor-based and table-based work isn't just about the child being closer to the ground — it changes the entire proprioceptive and vestibular input profile. When a child is on their hands and knees on a firm surface, they're generating bilateral coordination demands, weight-shifting, and core stabilization simultaneously without any of the artificial support a table provides. This is where progress actually happens for kids who plateau on seated tasks. I spent two years watching kids who could stack blocks at a table but couldn't cross the midline when pushed onto all fours on the floor. The floor doesn't give you the option to prop a forearm and disengage. It forces engagement. That's the whole point.
How to Structure a Session
Start with the child's baseline tolerance. Some kids will immediately drop to the floor and crawl. Others will stand on the edge and refuse to sit. I keep a timeline of roughly 15 to 20 minutes for the active floor portion, with breaks built in every five to seven minutes depending on sensory load. The sequence usually goes like this: first, passive exposure — the child sits or lies on the mat while you introduce textural tools like brushes, textured rollers, or fabric strips without demanding any motor response. Then you add movement: rolling, bear walks, crab walks, or commandos. Finally, you layer in cognitive or language tasks — following directions while maintaining the position, naming objects during a crawl pattern, or doing simple math problems while balancing on knees. What most people miss is that the order matters more than the duration. Pushing a child into active motor work before they've had thirty to forty-five seconds of passive tactile exposure on the surface will trigger a defensive response in about seventy percent of the kids I work with. I learned that the hard way with a six-year-old named Marcus who had Grade 3 tactile defensiveness. He'd bolt every time I rolled him across the foam mat. The workaround was simple but not obvious: I put his favorite weighted lap pad on him first, had him kneel and press his palms flat against the mat for ten seconds while I counted down from twenty, and only then introduced the rolling. That twenty-second prep step turned a failed session into a functional one. It still took him three weeks of consistent work before he tolerated the mat without the weighted pad.
Common Mistakes That Waste Time
The biggest error I see therapists make is treating Floor Therapy Pediatric as a single activity instead of a graduated system. You wouldn't throw a child who can't hold their head up independently into bear walks. Same logic applies here. The progression should follow: supine positioning, prone on elbows, prone on hands, all fours, kneeling, half-kneeling, and then standing. Each stage holds for as long as the child's regulation allows — sometimes two minutes, sometimes twenty. You move forward only when the current position no longer produces defensiveness or motor compensation patterns. Another mistake is using overly soft surfaces. A thick plush rug or memory foam gives zero proprioceptive feedback. The child's joints stop sending clear signals about position and pressure. Interlocking EVA foam tiles at least half an inch thick are the standard for a reason. They compress slightly but maintain resistance. If the child's ankles collapse inward or their wrists buckle when they bear weight, the surface is too soft and you need to switch to a firmer mat or a low-density rubber gym tile underneath.
Get the Full Details

What It Can't Fix
Floor Therapy Pediatric is not a standalone solution for gait abnormalities, spasticity from cerebral palsy above GMFCS level II, or significant hip subluxation. I've seen clinics market it as a comprehensive intervention for those conditions and it simply doesn't hold up. The therapy works best as an adjunct — something layered into a broader plan that includes standing frames, gait training, orthotics, or constraint-induced movement therapy depending on the diagnosis. For children with developmental coordination disorder or mild hypotonia, it can replace thirty to forty percent of the traditional table-based time without any loss of outcome. For kids with more complex neuromuscular involvement, expect it to handle maybe fifteen to twenty percent of their therapy load at best. If a child has severe avoidant behavior around floor-level work that hasn't responded to desensitization over four to six weeks, stop pushing it. Switch to a low therapy table with incline work for a while and reintroduce the floor later. Forcing it during that window usually sets progress back by two or three sessions.
Equipment List and Sourcing
You need: interlocking foam floor tiles (minimum 48 by 72 inches coverage), a few textured rollers or therapy brushes, a weighted lap pad or vest in child-appropriate weights (typically five to ten percent of body weight), and optionally some bolsters for positioning. Total cost for a basic setup runs between eighty and two hundred dollars depending on where you buy. Amazon, therapy supply companies like APG or Pronto Medical, and even Walmart's gym section all carry suitable foam tiles. Avoid anything labeled "play mat" — those are usually thinner and degrade within months of daily use.