Understanding the Practical Reality of Fluid Balance Tracking
A fluid balance chart is just a structured log where you record every milliliter going into a patient and every milliliter coming out, ideally on a shift-by-shift basis. The "chart" part doesn't need to be anything fancy. It can be a printed grid, a spreadsheet, or a paper form your ward uses. What matters is that the data is legible, traceable, and updated in real time, not backfilled at the end of a 12-hour shift when everyone is exhausted and the numbers are wrong. I've worked through enough of these to know that the single biggest source of error isn't the math—it's the missing entries. Someone forgets to log the 50ml of water the patient sipped with their evening meds. Or the urine output from a nighttime empty gets estimated instead of measured. Over 24 hours those small gaps add up to enough to make a clinical decision based on a flawed picture.
Building a Basic Fluid Balance Chart Template
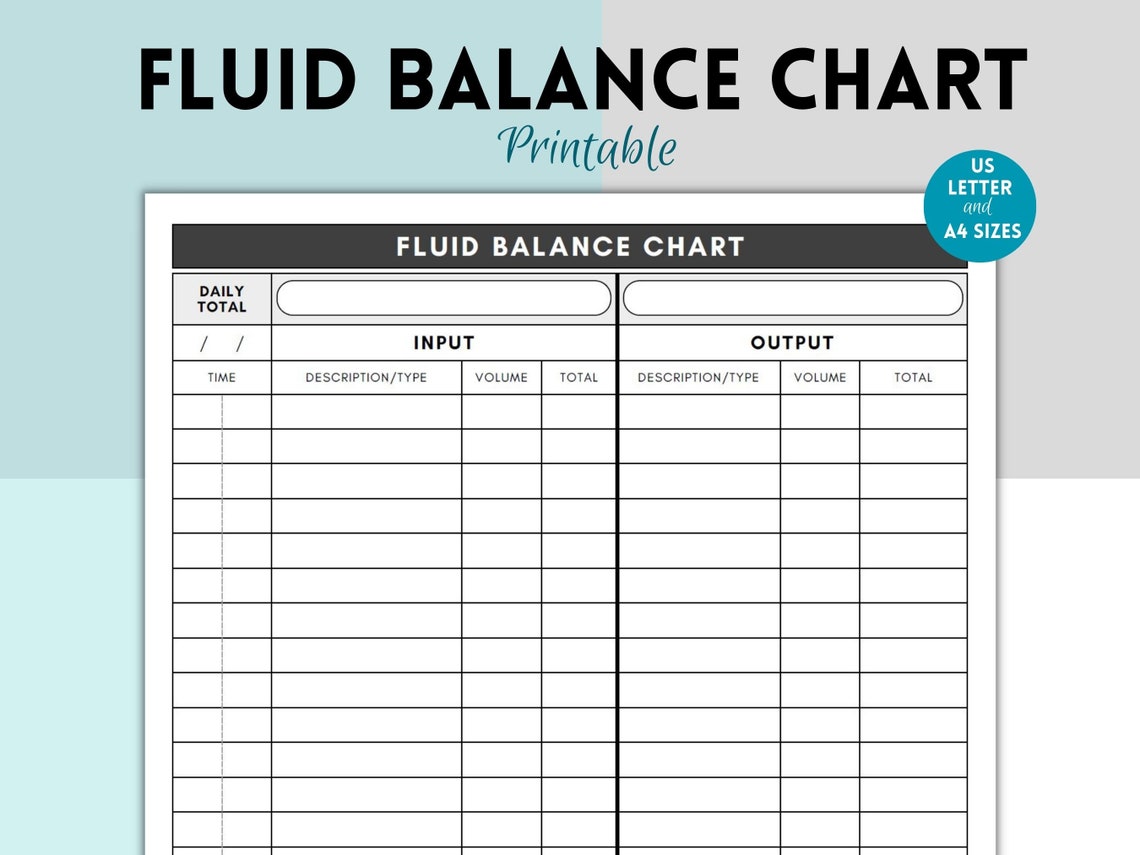
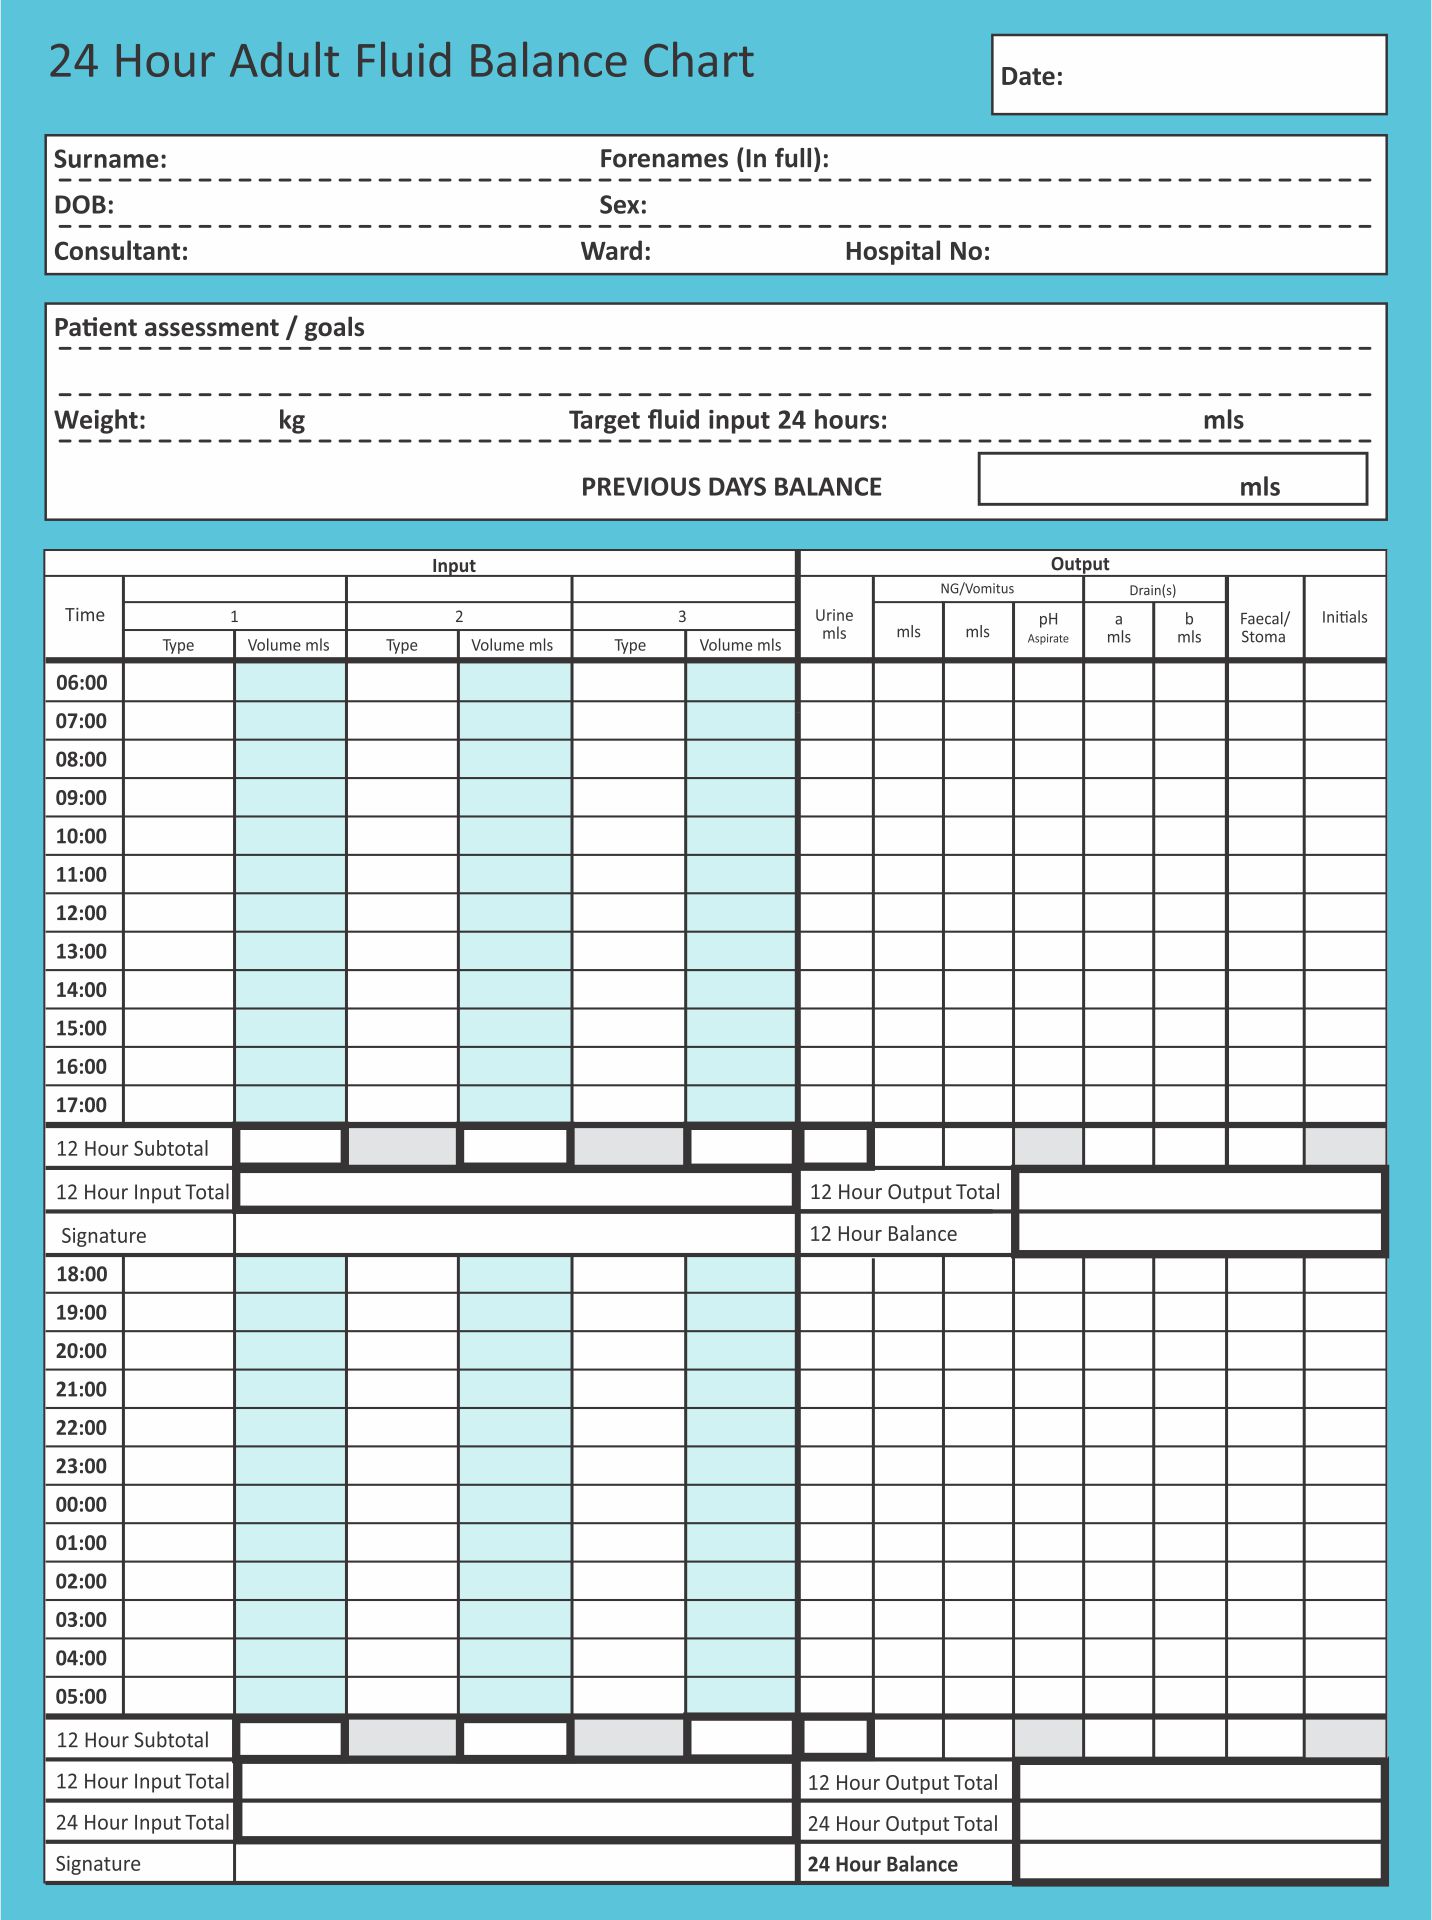
Here's what I actually use and recommend. The structure is simple because it has to be: clinicians don't have time to decode a complicated form during a busy handover. Header section: Patient name, MRN, date of birth, ward/bed number, admitting diagnosis, prescribed fluid limits if any, and the start date for the current balance period. Put the prescriber's name and contact number somewhere visible so you can clarify orders quickly.
Grid columns (reading left to right): Time, Intake IV (mL), Intake Oral (mL), Intake Enteral/Feed (mL), Output Urine (mL), Output Stoma/Drainage (mL), Other Output (mL), Net Balance (mL), Notes/Events. Keep it to one page per 24 hours if you're doing paper. Two pages max for complex ICU-level tracking. The net balance calculation:
Get the Full Details

Net = Total Intake - Total Output for each time block, then running cumulative totals at the bottom of each 8-hour shift. Don't make people pull out calculators. Either pre-print the formula at the top of the grid or build it into a spreadsheet so it updates automatically.
How It Actually Works in Practice
Let me walk through a realistic entry. A postoperative abdominal surgery patient, 68kg, fluid restricted to 2.5L/day. Morning shift starts at 0700. 0700: IV fluid started at 100mL/hour via 0.9% saline. Logged as 100mL in the IV column for that hour block. Patient takes nothing by mouth yet—NPO status. 0800: Oral intake 120mL water, 80mL nutritional supplement. Both logged separately in their columns. Net for the hour: +200mL intake, 0 output.
0900-1100: IV continues, 200mL in. Bladder scan shows residual of 150mL but nothing voided. Output column stays zero. Net for the two-hour block: +200mL. 1200: Urine output 450mL. Also 30mL nasogastric output logged under drainage. Net: -420mL for that hour. By 1500, the cumulative balance is +280mL for the shift. Running total at the bottom of the grid reflects that. If the daily limit is being approached, that gets flagged in the notes column with a call to the registrar.

The key detail people miss: IV medications and flushes count. A 10mL heparin flush every 8 hours is 30mL a day. In a fluid-restricted patient that's not trivial. Same with antibiotic volumes—if someone is running ceftriaxone in 100mL bags every 12 hours, that's 200mL of fluid sitting in the IV column that needs to be accounted for. I've seen charts where the antibiotic volume was completely omitted because the nurse assumed it was included in the maintenance rate. It's not, unless the order explicitly says 100mL/hr includes the med.
The Edge Case That Broke Me Once
There was a patient on the ward who had a continuous renal replacement therapy circuit running alongside their standard IV fluids. The CRRT machine displays its own input and output numbers, but those numbers include the replacement fluid and the ultrafiltration rate. If you just copy the machine readout into a standard balance chart, you get double-counting. The machine's "output" already factors in the replacement fluid on the input side. My workaround was straightforward but not obvious from the template alone: I added a separate line item on the chart labeled "CRRT" (net ultrafiltration from CRRT) and only entered the difference between the machine's prescribed replacement rate and the actual collected output, cross-referencing the nephrology nursing protocol. The standard template didn't account for this at all. I had to modify it on the fly, which is why I keep a note in my ward template about rare extracorporeal circuits and where to plug those numbers in.
Where These Templates Fail
Here's the blunt truth: a fluid balance chart template does nothing by itself. It's a documentation tool, not a decision support system. If the person filling it out doesn't have access to accurate intake and output data, the chart produces garbage. Period. Common failure points: - Estimating urine output instead of measuring it. Graduated collection containers exist for a reason. Guessing "about a cup" introduces 100-200mL of error per void.

- Ignoring insensible losses in hot environments or febrile patients. The chart records what you can measure, not the full physiological picture. A patient with a temperature of 39°C can lose an extra 500-700mL/day through skin and respiration that the chart simply doesn't capture. - Not reconciling with pharmacy records. IV fluid bags are dispensed in known volumes. If the bag inventory doesn't match what's documented on the chart, someone is either documenting incorrectly or there's a waste/spillage issue that needs investigation. For wards where manual charting is consistently unreliable, the alternative is integrating fluid balance into the electronic health record with smart alerts. Automated IV pump feeds, barcode-scanned oral intakes, and connected urine output collection systems eliminate the documentation gap. The trade-off is cost and setup time. A paper or spreadsheet template can be deployed in a day. An integrated system requires IT involvement, staff training, and ongoing maintenance.
Fluid Balance Chart Template Download
I don't host files directly, but the structure I described above can be replicated in any spreadsheet program in about 10 minutes. Set up columns as listed, lock the header rows, and add a simple SUM formula for the net column. If you need a ready-made version, most hospital trusts and medical supply companies offer printable versions, and the Royal College of Nursing publishes guidance on fluid balance documentation that includes template layouts. The principle is always the same: legible, real-time, and comprehensive enough that another clinician can pick it up at handover without asking five clarifying questions. The bottom line is that the template is only as good as the discipline behind it. A perfect grid filled with estimates is worse than a messy handwritten one that captures the real numbers. Decide which matters more on your ward before you decide which format to use.