Reading A Peripheral Blood Smear Without Losing Your Mind
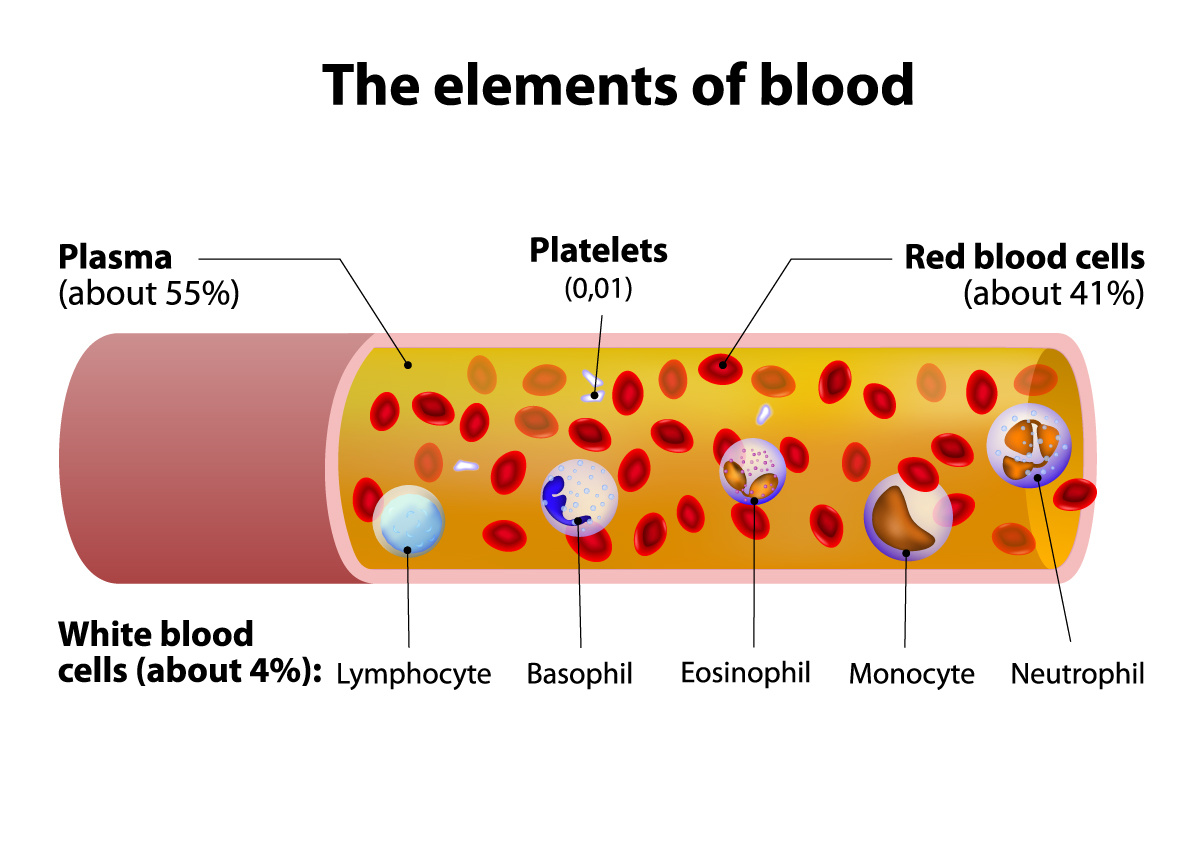
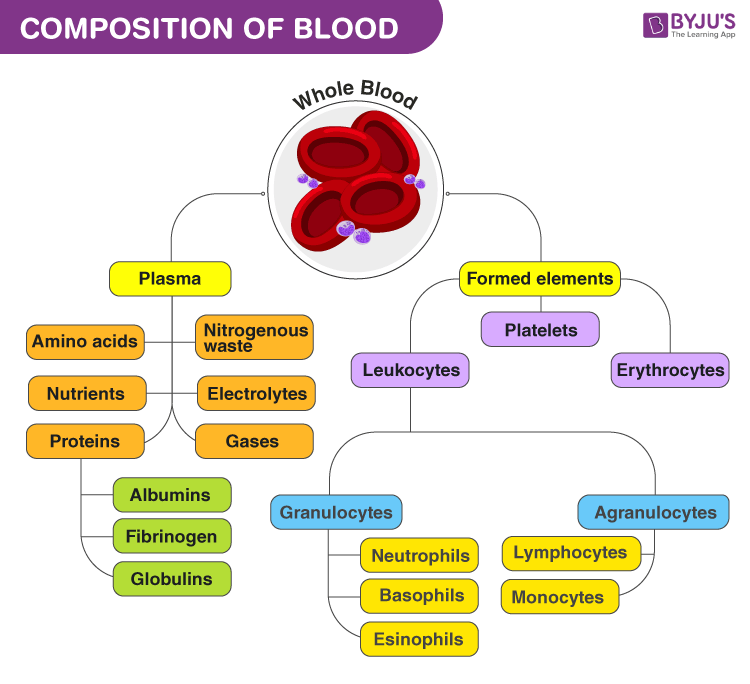
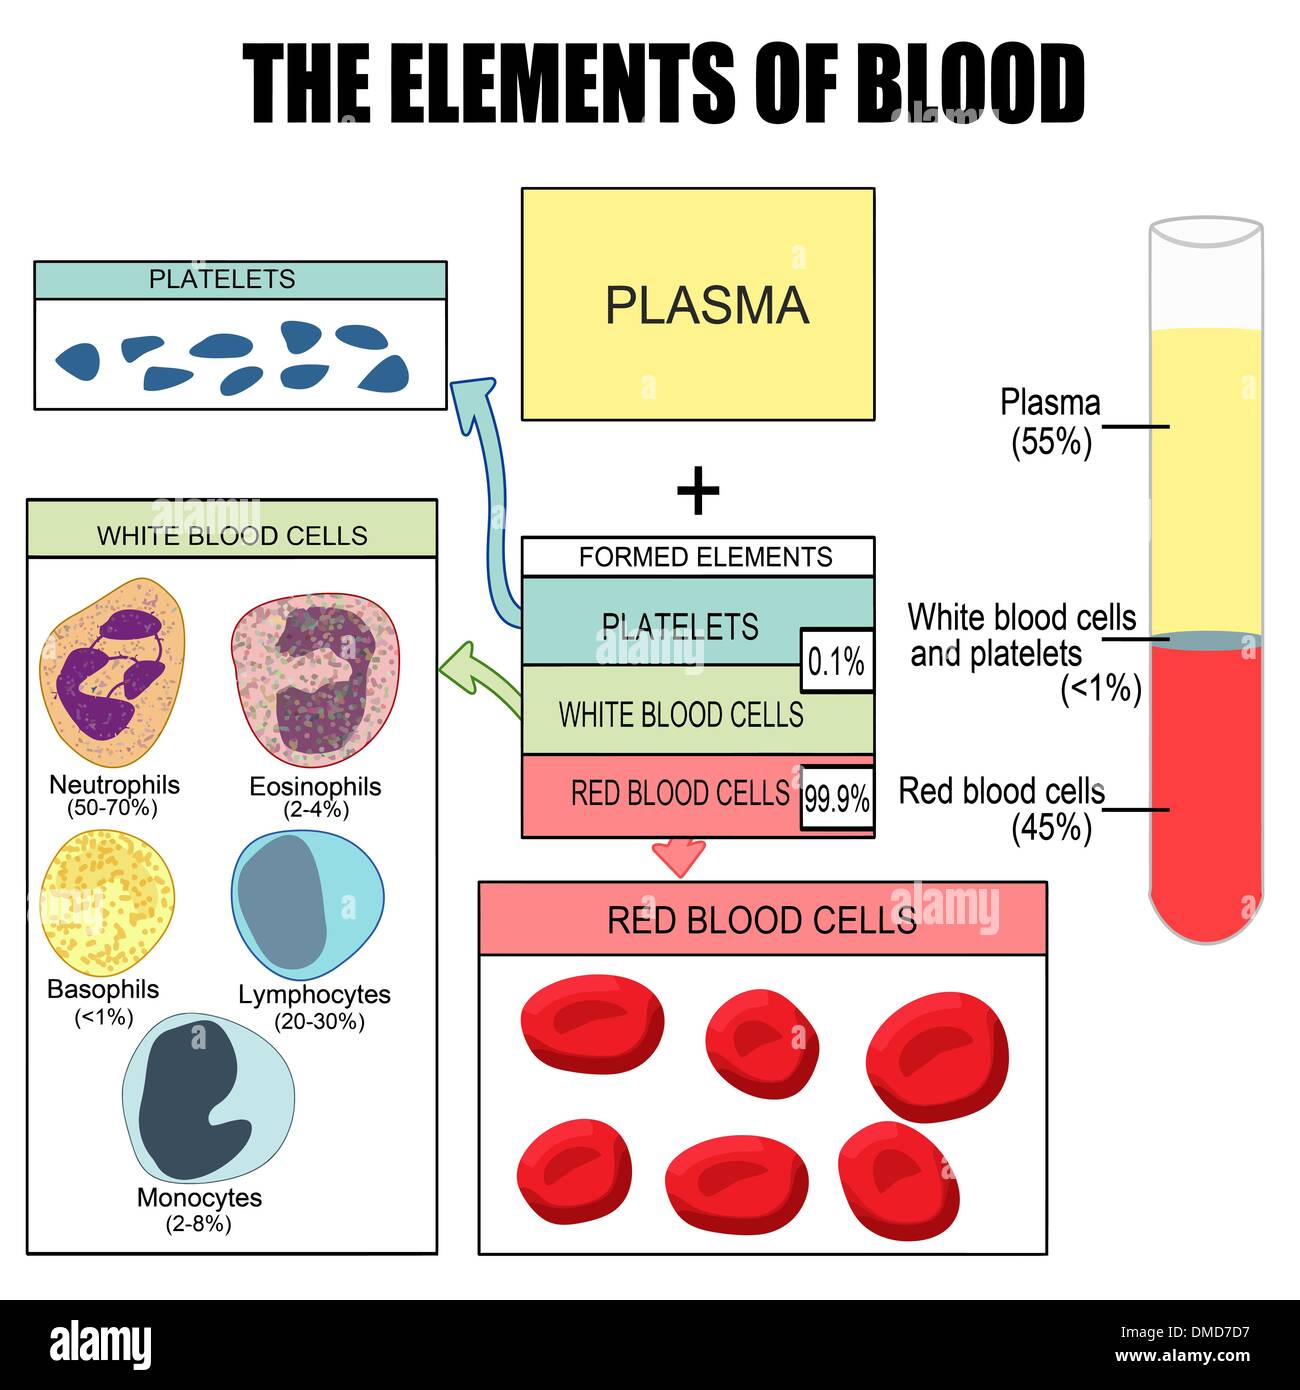
The first thing you need to understand about the formed elements of blood is that they are not just textbook diagrams floating in plasma. They are messy, variable, and will lie to you if you let them. When I started running hematology assays, I treated the smear like a puzzle. It is not. It is a snapshot of someone's physiology at a specific moment, and it only tells the truth if you know where to look and what to ignore. There are three categories. Erythrocytes carry oxygen and dominate the field visually. Leukocytes handle immune response and come in five distinct types, each with their own morphological signature. Platelets are cell fragments involved in clotting and are easily missed or confused with artifacts if you are not paying attention. Here is something most introductory courses skip: the relative proportion matters more than individual cell counts when you are doing manual differentials. A typical smear shows roughly 600 to 800 red blood cells for every white blood cell. Platelets sit somewhere in between numerically but are far smaller. If your smear looks dominated by large pale cells, you are either looking at a leukemic scatter or you spread the slide wrong. Those two scenarios produce very similar visual chaos but require completely different next steps.
The Practical Workflow
I usually start by examining the smear under low power to assess distribution before committing to oil immersion. You want a monolayer region where red blood cells are touching but not overlapping. If they are piling up, your differential numbers will be garbage. I have ruined whole batches because I was too impatient to scan for the right zone first. Under 100x oil, the process goes systematically. Scan the body of the smear in a zigzag pattern while counting leukocytes. Note the ratio. Then switch to reviewing erythrocyte morphology separately. Platelets get their own focused pass because they clump and aggregate quickly once the slide dries or sits too long. If you are working with EDTA samples, platelet clumping is common and can make thrombocytopenia look worse than it actually is. I resolve that by making a fresh thin smear from a non-clotted aliquot or by checking the autometer flag for giant platelets that the machine misclassified.
Common Pitfalls That Cost You Points On Exams And Errors In The Lab
The biggest mistake people make is conflating nucleated red blood cells with lymphocytes. An NRBC has a condensed pyknotic nucleus and pink cytoplasm. A lymphocyte has a round nucleus with clumped chromatin and a thin rim of blue cytoplasm. They show up in similar size ranges under lower magnification. If you miscategorize an NRBC as a lymphocyte, your white count inflates and your differential skews. Correct the automated count using the standard formula by subtracting the NRBCs from the total WBC before reporting. Another issue is toxic granulation in neutrophils. It looks dramatic under the microscope and beginners often report it as a primary finding. In practice, it is a reactive change seen in severe infection or inflammation. It does not change the differential percentage but it changes the clinical interpretation entirely. Flag it properly and move on. I also want to mention a specific problem I ran into with cold agglutinin disease. The red cells were forming rouleaux and true agglutinates that looked like platelet clumps at first glance. The autometer reported a falsely low platelet count and a spuriously elevated MCHC. I confirmed it by warming the sample to 37 degrees Celsius for twenty minutes and remeasuring. The platelet count normalized and the MCHC dropped to a physiologically plausible range. Without that step, the results would have been clinically misleading.
Get the Full Details

Advanced Morphology To Actually Use In Daily Work
Schistocytes indicate microangiopathic hemolysis. They are fragmented RBCs with angular shapes, not just distorted cells. You need at least two or three to call it significant, and you need to rule out artifact from a difficult draw. A single split cell on a thick smear means nothing. Hypersegmented neutrophils, defined as five or more lobes, point toward megaloblastic anemia. This is one of the few morphological findings that directly guides treatment. Catching it early prevents unnecessary workups for other causes of macrocytosis. Blast cells are the red flag. Any immature precursor with fine chromatin, nucleoli, and a high nuclear-to-cytoplasmic ratio should trigger an immediate referral for flow cytometry. Do not attempt to classify the blast lineage manually unless you have formal cytogenetics support. Morphology alone cannot reliably distinguish myeloid from lymphoid blasts in many cases.
When Manual Methods Fall Short
Automated hematology analyzers handle most routine differentials faster and with better precision than a human eye. The problem is that they use impedance and light scatter, which means abnormal cells, clumps, and lipemic samples can confuse the algorithms. The instrument flags are helpful but not infallible. I cross-reference any flagged result with a manual smear before signing out, especially when the clinical picture does not match the numbers. For rare conditions like paroxysmal nocturnal hemoglobinuria or chronic lymphocytic leukemia, flow cytometry and specialized staining are necessary. A basic blood smear will show changes suggestive of these conditions but will not confirm them. Knowing the limit of what morphology can tell you is as important as knowing what it can detect. The formed elements of blood remain a foundational skill because machines miss context. A good smear review connects the cellular data to what is actually happening in the patient. It takes time, patience, and a willingness to admit when you are unsure. Everything else is just technique.