Understanding The Four Layers Of The Alimentary Canal
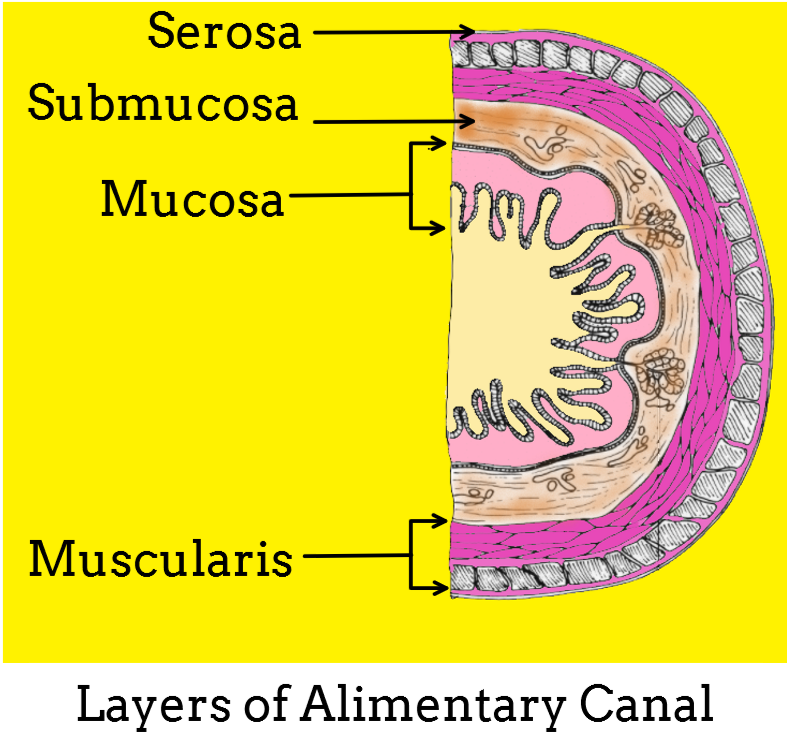
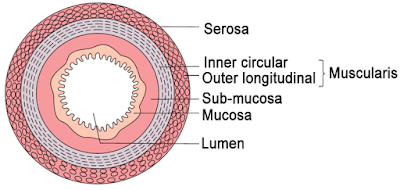
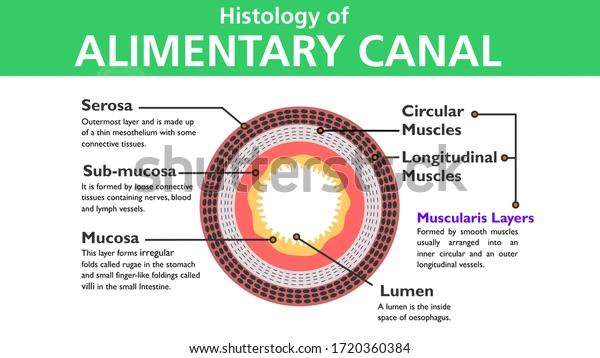
I first learned about this topic in undergrad anatomy, which was a long time ago. Since then I have worked with it repeatedly in histology labs, surgical prep courses, and clinical discussions. The concept is straightforward until you try to apply it, at which point things get messy fast. The alimentary canal wall is built from four distinct layers, each with a specific structural role. They are, from the inside out: mucosa, submucosa, muscularis externa, and serosa (or adventitia, depending on location). The mucosa is the innermost layer. It has three components: epithelium, lamina propria, and muscularis mucosae. The type of epithelium changes depending on what part of the tract you are looking at. The esophagus has stratified squamous epithelium because it needs to handle abrasion from food. The stomach has simple columnar epithelium with mucous cells because it needs to survive acid. The small intestine has simple columnar with villi and microvilli for absorption. This is not arbitrary; it is a direct correlation between location and function.
Beneath the mucosa sits the submucosa. This is connective tissue packed with blood vessels, lymphatics, and the submucosal nerve plexus (Meissner's plexus). The submucosa is where most of the autonomic control of glandular secretion happens. If you are studying the regulation of digestive enzyme release, this is the layer you should be focusing on. The muscularis externa is usually two layers of smooth muscle: an inner circular layer and an outer longitudinal layer. Between them is the myenteric nerve plexus (Auerbach's plexus), which controls peristalsis. The circular layer constricts the lumen; the longitudinal layer shortens the tract. Together they produce the wave-like contractions that move contents along. There are exceptions. The stomach has a third layer, an inner oblique layer, which is why it can churn food rather than just push it forward. The upper esophagus has skeletal muscle instead of smooth muscle, which is relevant if you are dealing with voluntary swallowing disorders. The outermost layer is either serosa or adventitia. Serosa is a visceral peritoneum covering found in organs suspended within the peritoneal cavity. Adventitia is fibrous connective tissue found in areas not covered by peritoneum, like the esophagus in the thorax and the rectum in the pelvis. The distinction matters surgically. If you are dissecting around the ascending colon, you are working with serosa. Around the retroperitoneal pancreas, you are working with adventitia. The planes of dissection are different, and the bleeding risk differs accordingly.
I ran into a practical problem a few years ago while preparing a gross anatomy specimen for teaching. The submucosa of the small intestine had been overstretched during preservation, making it nearly impossible to distinguish from the muscularis layer on basic light microscopy. What I ended up doing was using a Masson's trichrome stain instead of the standard H&E. The connective tissue in the submucosa stains blue with trichrome, while the smooth muscle stains red. It took about twenty minutes longer per slide, but it made the layer boundaries unmistakable. Standard H&E works fine for fresh or properly fixed tissue. Preserved specimens that have been through repeated handling are another matter entirely. There are a couple of things that beginners consistently miss about these layers. One is that the thickness of each layer varies dramatically along the length of the canal. The mucosa in the duodenum is thick with dense villi and Brunner's glands in the submucosa. By the time you reach the ileum, the villi are shorter and the Peyer's patches in the submucosa become prominent. If you are trying to identify a tissue section and you only memorize a single "textbook" version of each layer, you will struggle with real specimens. Another counter-intuitive point is that the mucosa is not the strongest layer. Despite being the most metabolically active, it is also the most vulnerable. This is why ulcerative colitis, which primarily affects the mucosa and submucosa, rarely causes perforation. Crohn's disease, which is a transmural inflammation affecting all four layers, has a much higher risk of fistula formation and perforation. The depth of involvement correlates directly with clinical severity, not just symptom intensity.
Get the Full Details

There is also a common misconception that the four layers are the same everywhere. They are not. The esophagus uses stratified squamous epithelium, the stomach has gastric pits and glands in the mucosa, the small intestine has the absorptive apparatus, and the large intestine lacks villi but has abundant crypts and goblet cells. Even the muscularis externa changes. The external longitudinal muscle bundles in the colon form three distinct bands called taeniae coli, which give the colon its characteristic segmented appearance. Most students learn about this once and forget it exists until they see it on an exam. If you need to practice identifying these layers in tissue sections, there are multiple publicly available slide libraries online. The University of Michigan Digital Atlas of Digital Pathology and the Histology Guide at the University of Leeds both offer free whole-slide images with labeled regions. Neither requires an account or a payment. I usually work through the labeled sections first, then test myself on unlabeled slides from the same collections. This method cuts my preparation time significantly compared to guessing from textbook diagrams alone. The Four Layers Of The Alimentary Canal is a foundational concept, but it is also one of those things that looks simple until you actually have to apply it under exam conditions or in a clinical context. The variations along the tract are where most mistakes happen, and the difference between serosa and adventitia is the kind of detail that separates adequate answers from complete ones. Don't skip over the exceptions. They are almost always the thing being tested.