Why Memorizing The Four Layers Of The Gi Tract Got You Nowhere
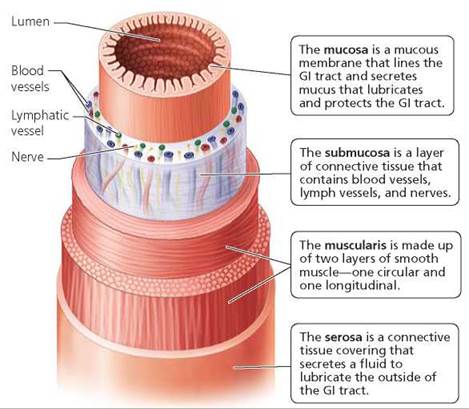
I spent three weeks trying to teach this to med students before realizing the standard lecture format doesn't actually help anyone retain it. Everyone knows the mnemonic. "Learn Not To Eat Greasy Food" or whatever variant you picked. That doesn't mean they can identify a layer in a histology slide under time pressure, which is what matters on exams and in practice. The four layers are mucosa, submucosa, muscularis externa, and serosa (or adventitia in places). That's the list. The problem is that the list is almost useless without understanding what each layer actually does and why they're arranged the way they are. Let me explain this from the ground up.
Four Layers Of The Gi Tract
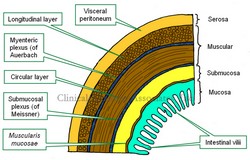
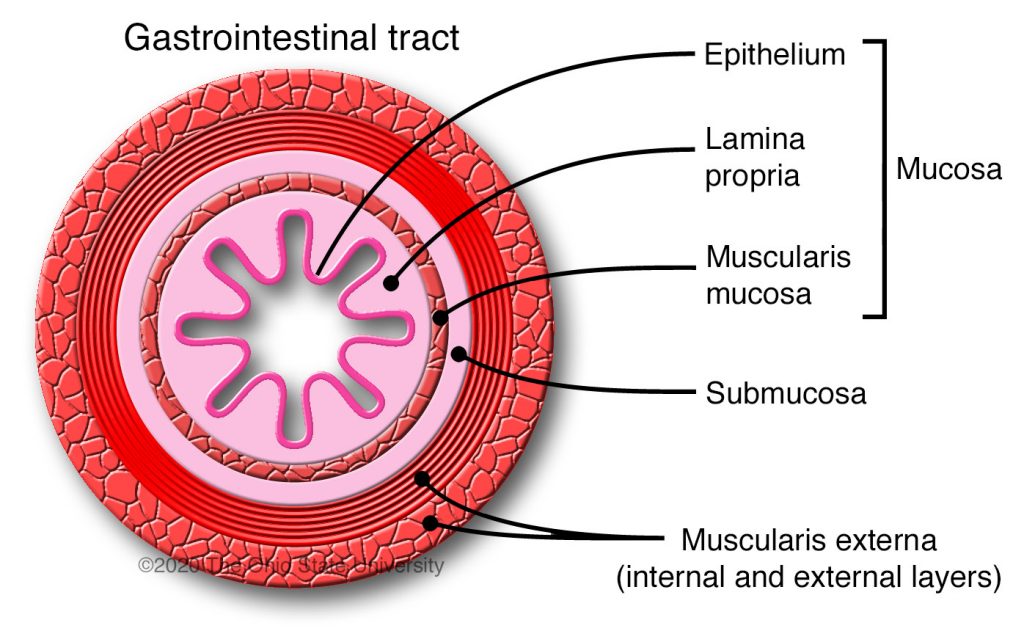
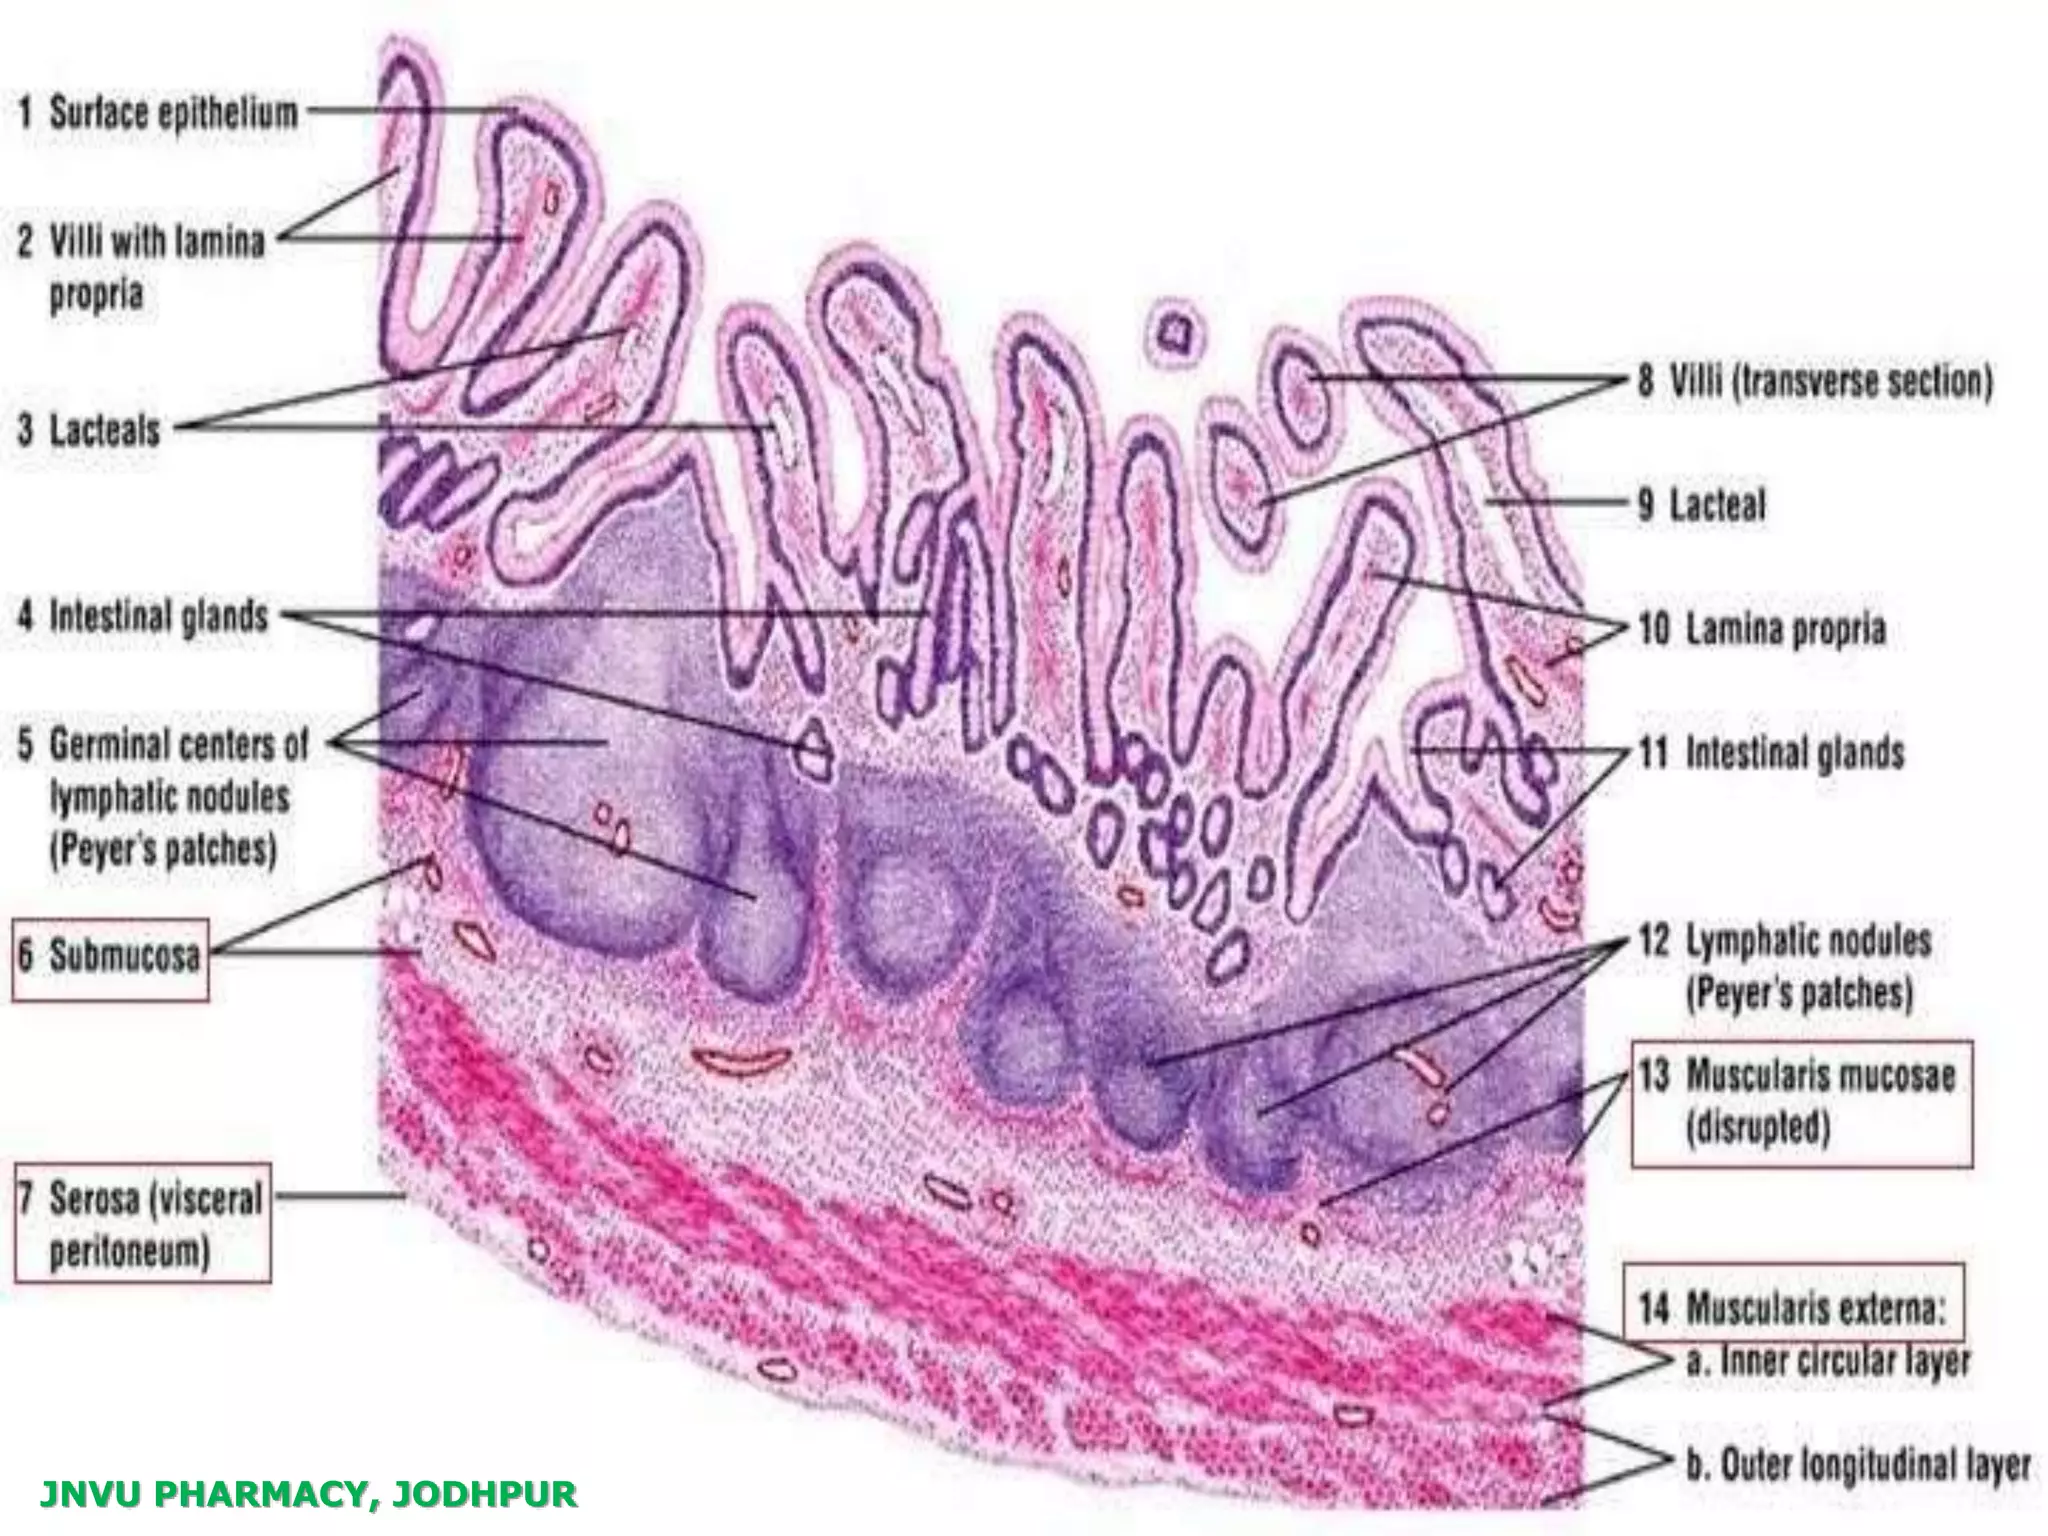
Mucosa is the innermost layer and it has three sub-components: epithelium, lamina propria, and muscularis mucosae. The epithelium changes depending on where you are in the tract. Oral cavity and esophagus use stratified squamous because friction is the main concern. Stomach uses simple columnar with lots of mucus-secreting cells because acid is the threat. Small intestine uses simple columnar with villi and microvilli for absorption. Rectum transitions back to stratified squamous. You cannot memorize this as one uniform layer. It varies significantly by region. The lamina propria is loose connective tissue containing blood vessels, lymphatics, and immune cells. GALT (gut-associated lymphoid tissue) lives here. This is why you get immune responses in the gut. The muscularis mucosae is a thin smooth muscle layer that creates local folding and movement of the mucosal surface. It's separate from the main muscularis externa and is often overlooked in diagrams but matters functionally. Submucosa is dense irregular connective tissue. It contains the submucosal (Meissner's) plexus, which is part of the enteric nervous system. Blood vessels, lymphatics, and nerves run through it. In the duodenum specifically, you'll find Brunner's glands in the submucosa. These secrete alkaline mucus to protect against gastric acid. If you see glandular tissue in the submucosa on a slide, think duodenum. That's a high-yield identification point.
Muscularis externa is where things get interesting. Most of the GI tract has two layers of smooth muscle: inner circular and outer longitudinal. The interstitial cells of Cajal act as pacemakers between these layers. They generate slow wave potentials that coordinate peristalsis. The myenteric (Auerbach's) plexus sits between the two muscle layers. This is the primary control center for motility. Some regions have specializations. The oral cavity and upper esophagus have skeletal muscle. The anal canal has both smooth and skeletal muscle. The stomach has a third oblique layer for churning. If you're identifying tissue and see three muscle layers, it's the stomach. Serosa versus adventitia depends on whether the organ is intraperitoneal or retroperitoneal. Serosa is connective tissue covered by mesothelium (simple squamous epithelium). It's a slippery surface that reduces friction. Adventitia is just connective tissue without the mesothelial covering. It anchors the organ to surrounding structures. Esophagus has adventitia. Most of the small and large intestine has serosa. This distinction matters for surgical approaches and for understanding how tumors spread. Here's what I ran into last year that nobody warns you about. A student was looking at a histology section of the appendix and couldn't identify the layers because the mucosa looked completely different from textbook images. The appendix has lymphoid follicles in the lamina propria that can almost completely obliterate the lumen in adults. The muscularis externa is also unusually thin relative to the rest of the tract. If you're doing slide identification and the lumen is small and full of lymphoid tissue, it's the appendix regardless of how compressed the architecture looks.
Get the Full Details

Another thing that trips people up: the muscularis mucosae and the inner circular layer of the muscularis externa can look nearly identical on low magnification. Both are smooth muscle. The difference is scale and location. Muscularis mucosae is thin and sits right under the lamina propria. Muscularis externa is much thicker and has a distinct outer longitudinal layer. Always check magnification and look for the outer longitudinal layer to confirm you're looking at the muscularis externa. The enteric nervous system deserves more attention than it gets. You have roughly 500 million neurons in your gut. That's more than in your spinal cord. The submucosal plexus controls secretion and blood flow. The myenteric plexus controls motility. These can function independently of the CNS. This is why you can have peristalsis after spinal cord injury and why stress affects digestion through the gut-brain axis. Understanding this changes how you approach motility disorders clinically. One limitation of the four-layer model is that it's a simplification. The GI tract isn't a uniform tube. Junctions between regions have abrupt changes. The gastroesophageal junction has a complete transition from stratified squamous to simple columnar epithelium over a very short distance. The pyloric sphincter has a dramatic thickening of the circular layer. At these transition points, the standard layered model breaks down and you need to understand regional specializations instead.
If you're studying for boards or histology practicals, focus on identification rather than memorization. Know what each layer looks like under the microscope. Know what distinguishes one region from another. The layers themselves are straightforward. The variations are what actually test you.