The Practical Way to Use The Four Quadrant Method In Clinical Settings
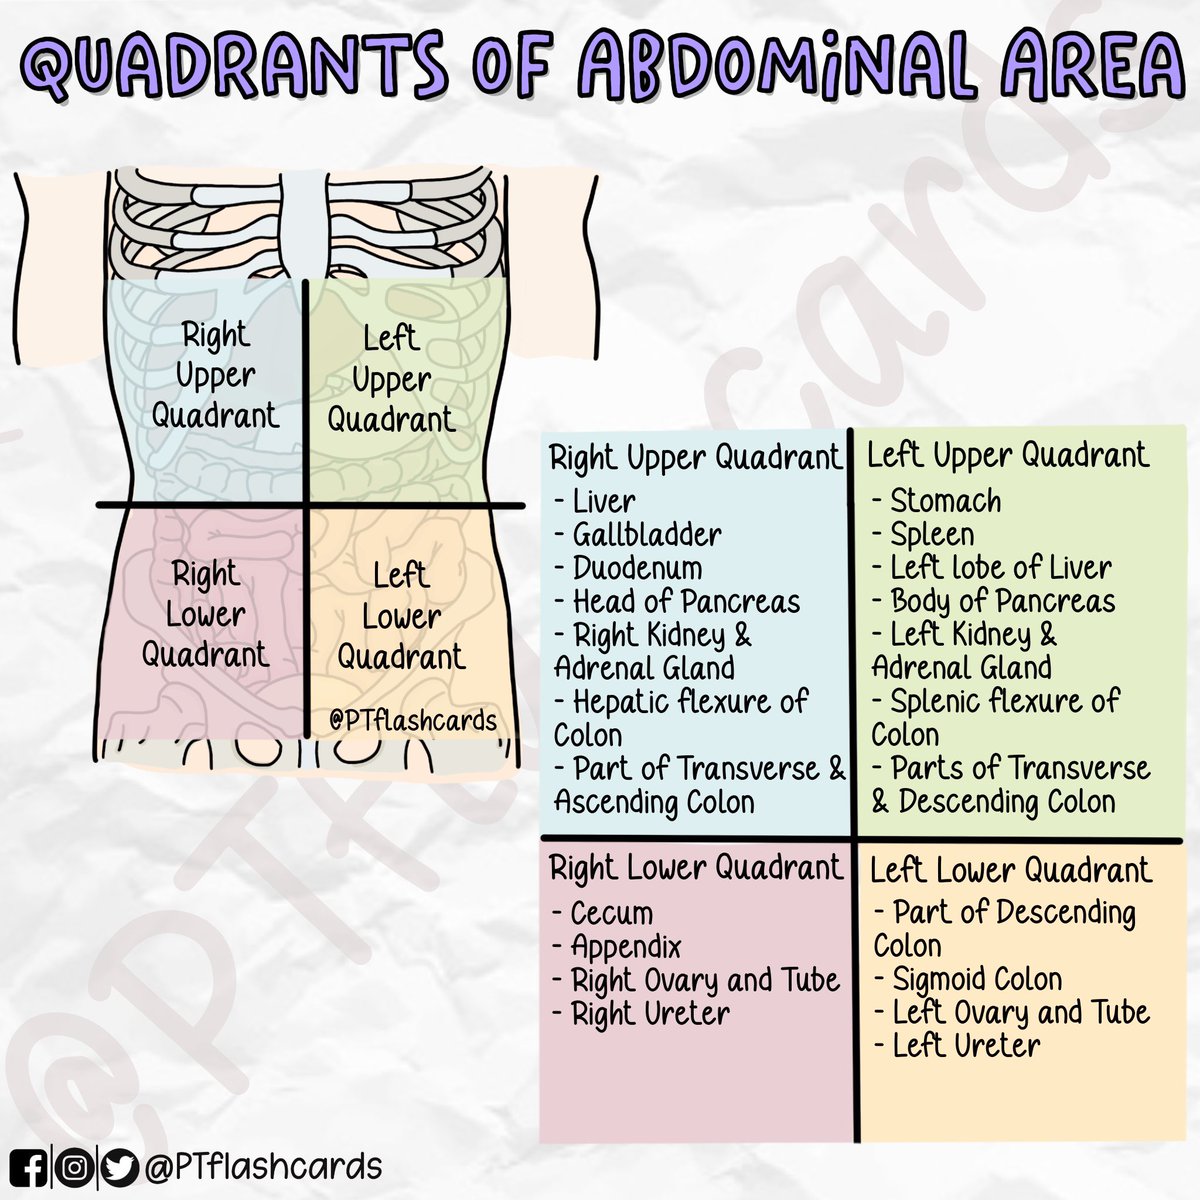
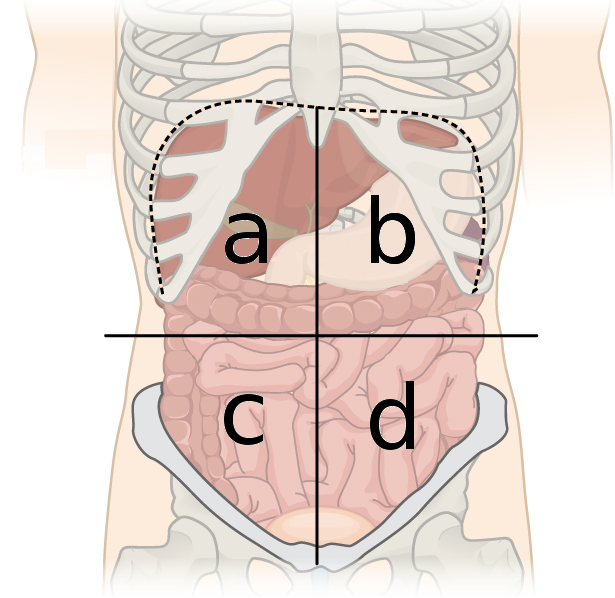
The four quadrant approach to abdominal assessment is standard practice in emergency medicine and general surgery rotations. It divides the abdomen into four sections using two imaginary lines: one transumbilical and one midline sagittal. Right upper, left upper, right lower, left lower. That's the textbook version. In reality it's messier than that. Students tend to press too hard in the upper quadrants and miss pathology in the lower ones because they get distracted by guarding. I spent three months working nights in a level 1 trauma bay before I stopped doing that.
Four Quadrants Of Abdomen: What You Actually Need To Know
The method itself is simple but the execution is where things fall apart. Here's how to do it properly. Start with inspection. Look at the patient's bare abdomen before you touch it. Distension, scars, visible peristalsis, skin changes. This takes about ten seconds and most people skip it. Don't skip it. A Cullen sign around the umbilicus showing up during inspection will save you from missing a ruptured ectopic or pancreatitis when palpation results are ambiguous. Then auscultate before you palpate. Bowel sounds first, in all four quadrants, each one held for at least thirty seconds. I've seen residents palpate the abdomen aggressively and then move straight to percussion, which alters bowel motility and makes the sounds unreliable for twenty minutes after. Just listen first.
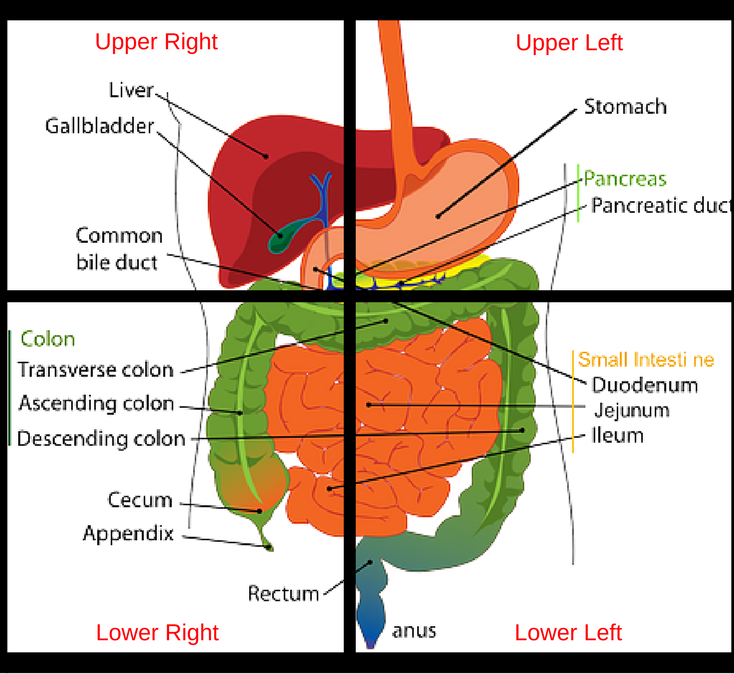
Palpation has two parts: light and deep. Light palpation uses about one centimeter of depression depth. Go quadrant by quadrant, systematically. Right upper quadrant first, then left upper, then right lower, then left lower. Note any areas of tenderness, guarding, or rebound. If the patient winces in one quadrant, come back to it last. You don't want them tensing up across the entire abdomen because you touched the painful spot too early. Deep palpation goes about five centimeters down and checks for organomegaly or masses. Liver edge in the right upper quadrant, spleen tip in the left upper, cecum and appendix area in the right lower. The left lower quadrant is usually where diverticulitis presents and where people stop paying attention because they think "oh it's just the left side." It's not. Percussion comes last. Generalized tympany suggests free air. Dullness over the liver edge tells you about hepatomegaly. McBurney's point percussion tenderness in the right lower quadrant is a classic appendix sign but it's unreliable on its own. I had a case last year where a woman with atypical appendicitis had zero percussion tenderness at McBurney's but significant deep palpation tenderness two centimeters higher than expected. CT confirmed it. Don't let a negative percussion test reassure you.
Get the Full Details
The Edge Case That Broke Me
Early in my residency I saw a patient with what looked like a straightforward right lower quadrant issue. Appendicitis was the working diagnosis based on tenderness in the right lower quadrant and a mild white count elevation. We prepped for surgery. Then on re-examination I noticed something I'd missed during the initial quick assess. The tenderness wasn't centered at McBurney's point. It was slightly medial and inferior, and there was a palpable mass that moved with respiration. I called off the appendectomy. Turns out it was an incarcerated femoral hernia, not appendicitis. A femoral hernia presents in the lower quadrant area but sits below the inguinal ligament. If you only think "right lower quadrant equals appendix," you miss this. The workaround is to always define exactly where the tenderness sits relative to anatomical landmarks rather than just labeling it by quadrant. Write down the coordinates, essentially. How many centimeters from the anterior superior iliac spine? From the umbilicus? From the pubic symphysis? It takes twenty extra seconds and it prevents exactly this kind of error.
Pitfalls That Beginners Keep Making
The biggest mistake is treating the four quadrants as isolated boxes. They're not. Pain from a single process can radiate across quadrant boundaries. A retrocecal appendix might cause minimal right lower quadrant tenderness but refer pain to the flank, which spills into the right upper quadrant on exam. A pelvic abscess can cause suprapubic discomfort that feels like it's in the left lower quadrant because the patient can't localize visceral pain well. Another trap is the assumption that quadrant localization equals diagnosis. It doesn't. Right upper quadrant pain could be biliary, hepatic, pulmonary (right lower lobe pneumonia referring pain), or even cardiac. Left upper quadrant pain could be splenic, gastric, pancreatic tail, or cardiac again. The quadrant tells you where to look, not what you're looking for. Body habitus matters more than textbooks admit. In obese patients, deep palpation becomes nearly impossible above three centimeters of depression before you're just pressing on subcutaneous fat. Superficial tenderness is still reliable but organomegaly detection drops significantly. In cachectic patients the opposite problem occurs. You can feel everything too easily and mistake normal anatomical structures for pathology. A palpable sigmoid colon in the left lower quadrant of an elderly thin patient is often normal, not a mass.
When The Method Fails Completely
The four quadrant abdominal exam has real limitations. It cannot reliably detect early peritonitis in elderly or immunocompromised patients who won't mount a typical inflammatory response. It misses up to forty percent of early appendicitis cases when used in isolation according to the literature. In pregnant patients the displacing uterus shifts organ positions so quadrant localization is essentially useless after the second trimester. And in obtunded or intubated patients the exam is reduced to palliative observation rather than diagnostic workup. For those scenarios the workaround is imaging. Ultrasound for biliary and gynecological pathology. CT for anything deeper or more ambiguous. The physical exam is a screening tool, not a definitive one. Using it as such is what causes diagnostic delays. If you're learning this for clinical rotations, focus on building systematic habits rather than memorizing quadrant-diagnosis pairs. The pairs are unreliable. The systematic approach of inspect, auscultate, palpate lightly, palpate deeply, percuss, and document precise locations is what actually translates to better patient outcomes.