What Actually Matters in a Mental Status Exam
A mental status exam is a structured snapshot of how a patient presents cognitively and emotionally at a single point in time. Most people overcomplicate it. The core domains are appearance, behavior, speech, mood, affect, thought process, thought content, perception, cognition, and insight. That is essentially the whole thing. Everything else is decoration. I spent years watching clinicians spend twenty minutes documenting that a patient was "cooperative" and had "normal gait" while completely missing disorganized thinking because they were too busy filling out checkboxes. Templates help you stay organized, but they can also trap you into treating a form like a diagnosis. A Free Mental Status Exam Template is useful only if you know how to actually read the patient behind it.
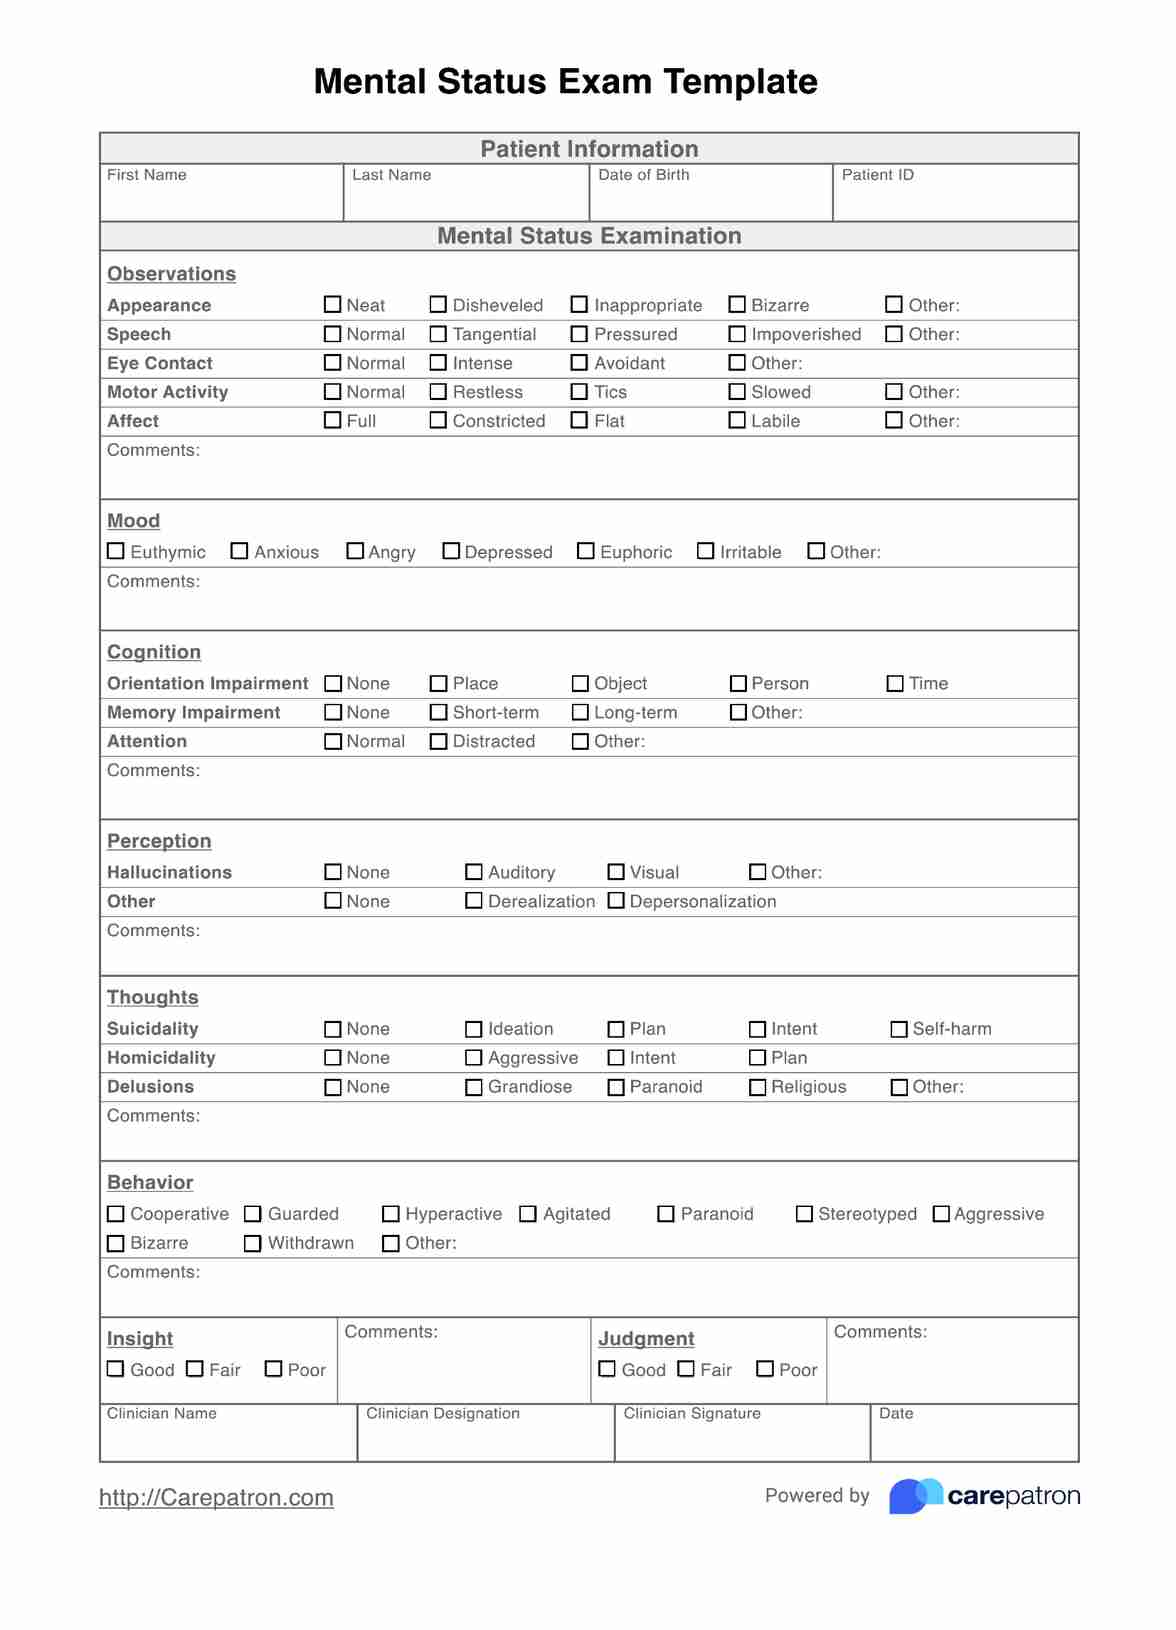
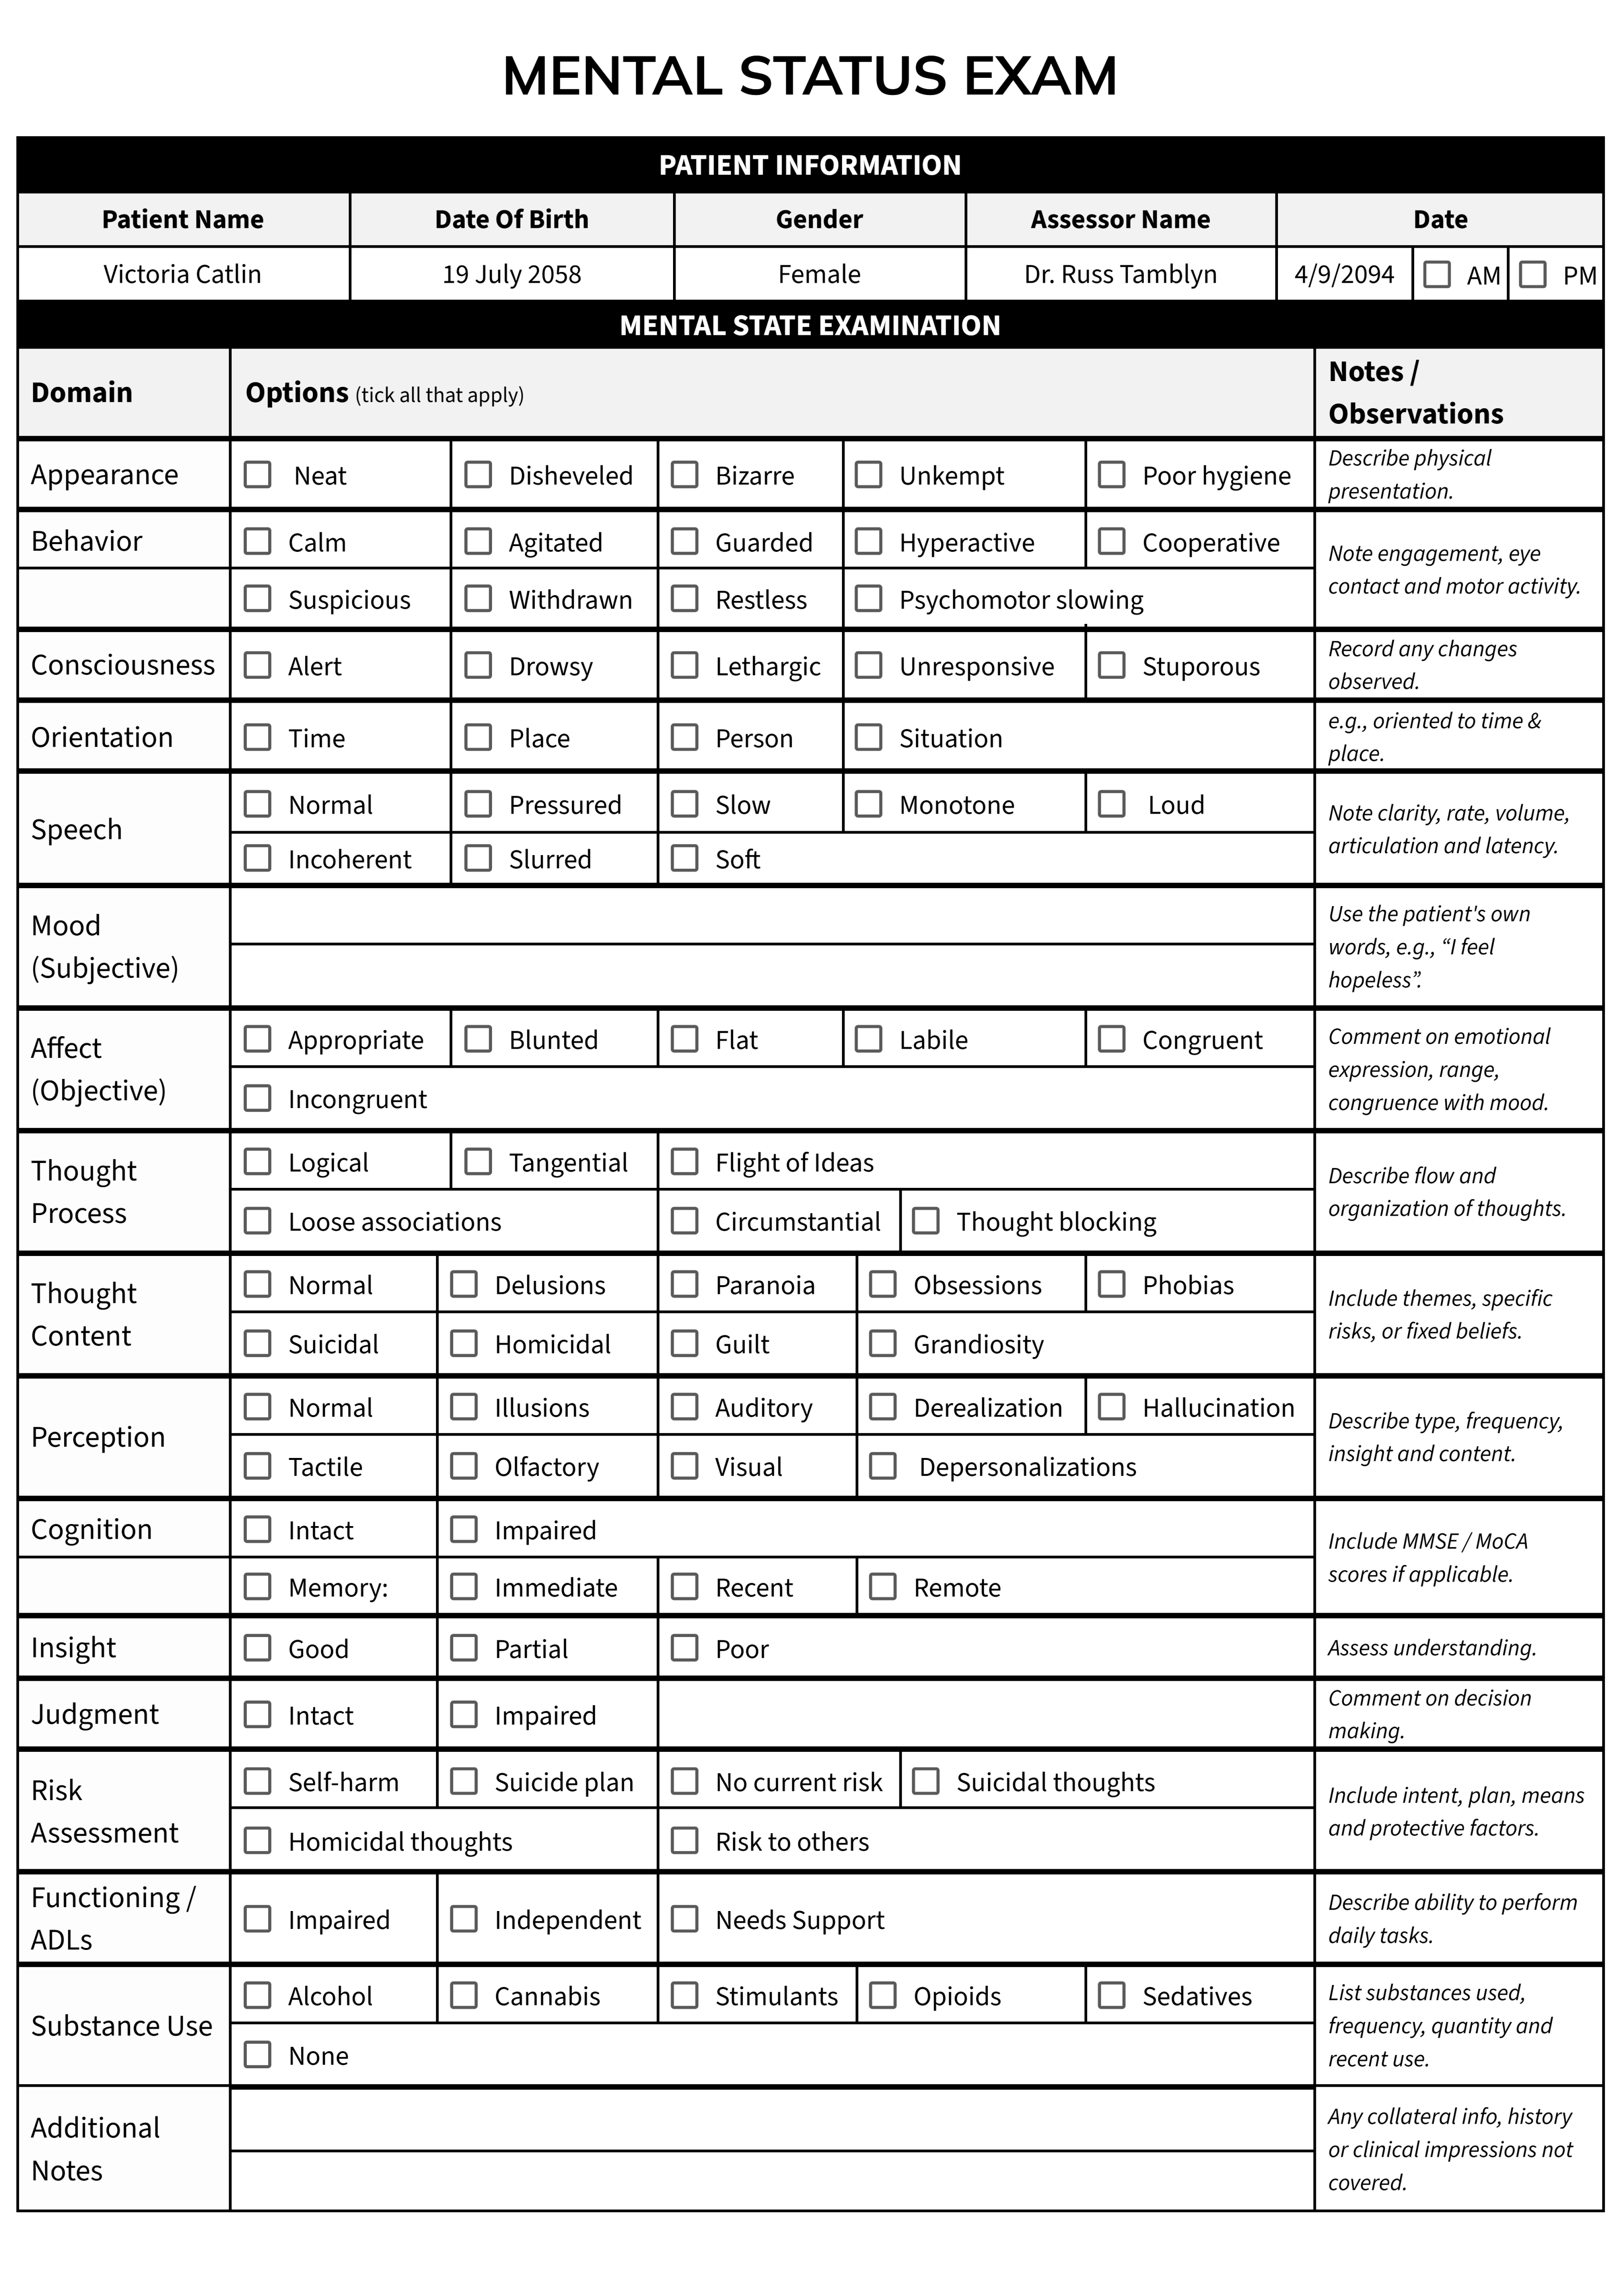
Free Mental Status Exam Template
The template I am about to walk through covers the standard domains. You can find many variations online, but most of them are copy-pasted from the same three sources. The one below is structured around what actually matters clinically, not what looks good on paper. You can paste this into your EHR or a Word document. It is basic by design. Basic works better when you are doing twelve intakes a day.
Template Structure
Appearance: Dress, hygiene, posture, visible scars or marks, apparent age versus stated age. Behavior/Motor: Psychomotor activity, eye contact, tremors, tics, catatonia, unusual movements. Speech: Rate, volume, tone, fluency, coherence, pressured, halting, muted.
Get the Full Details
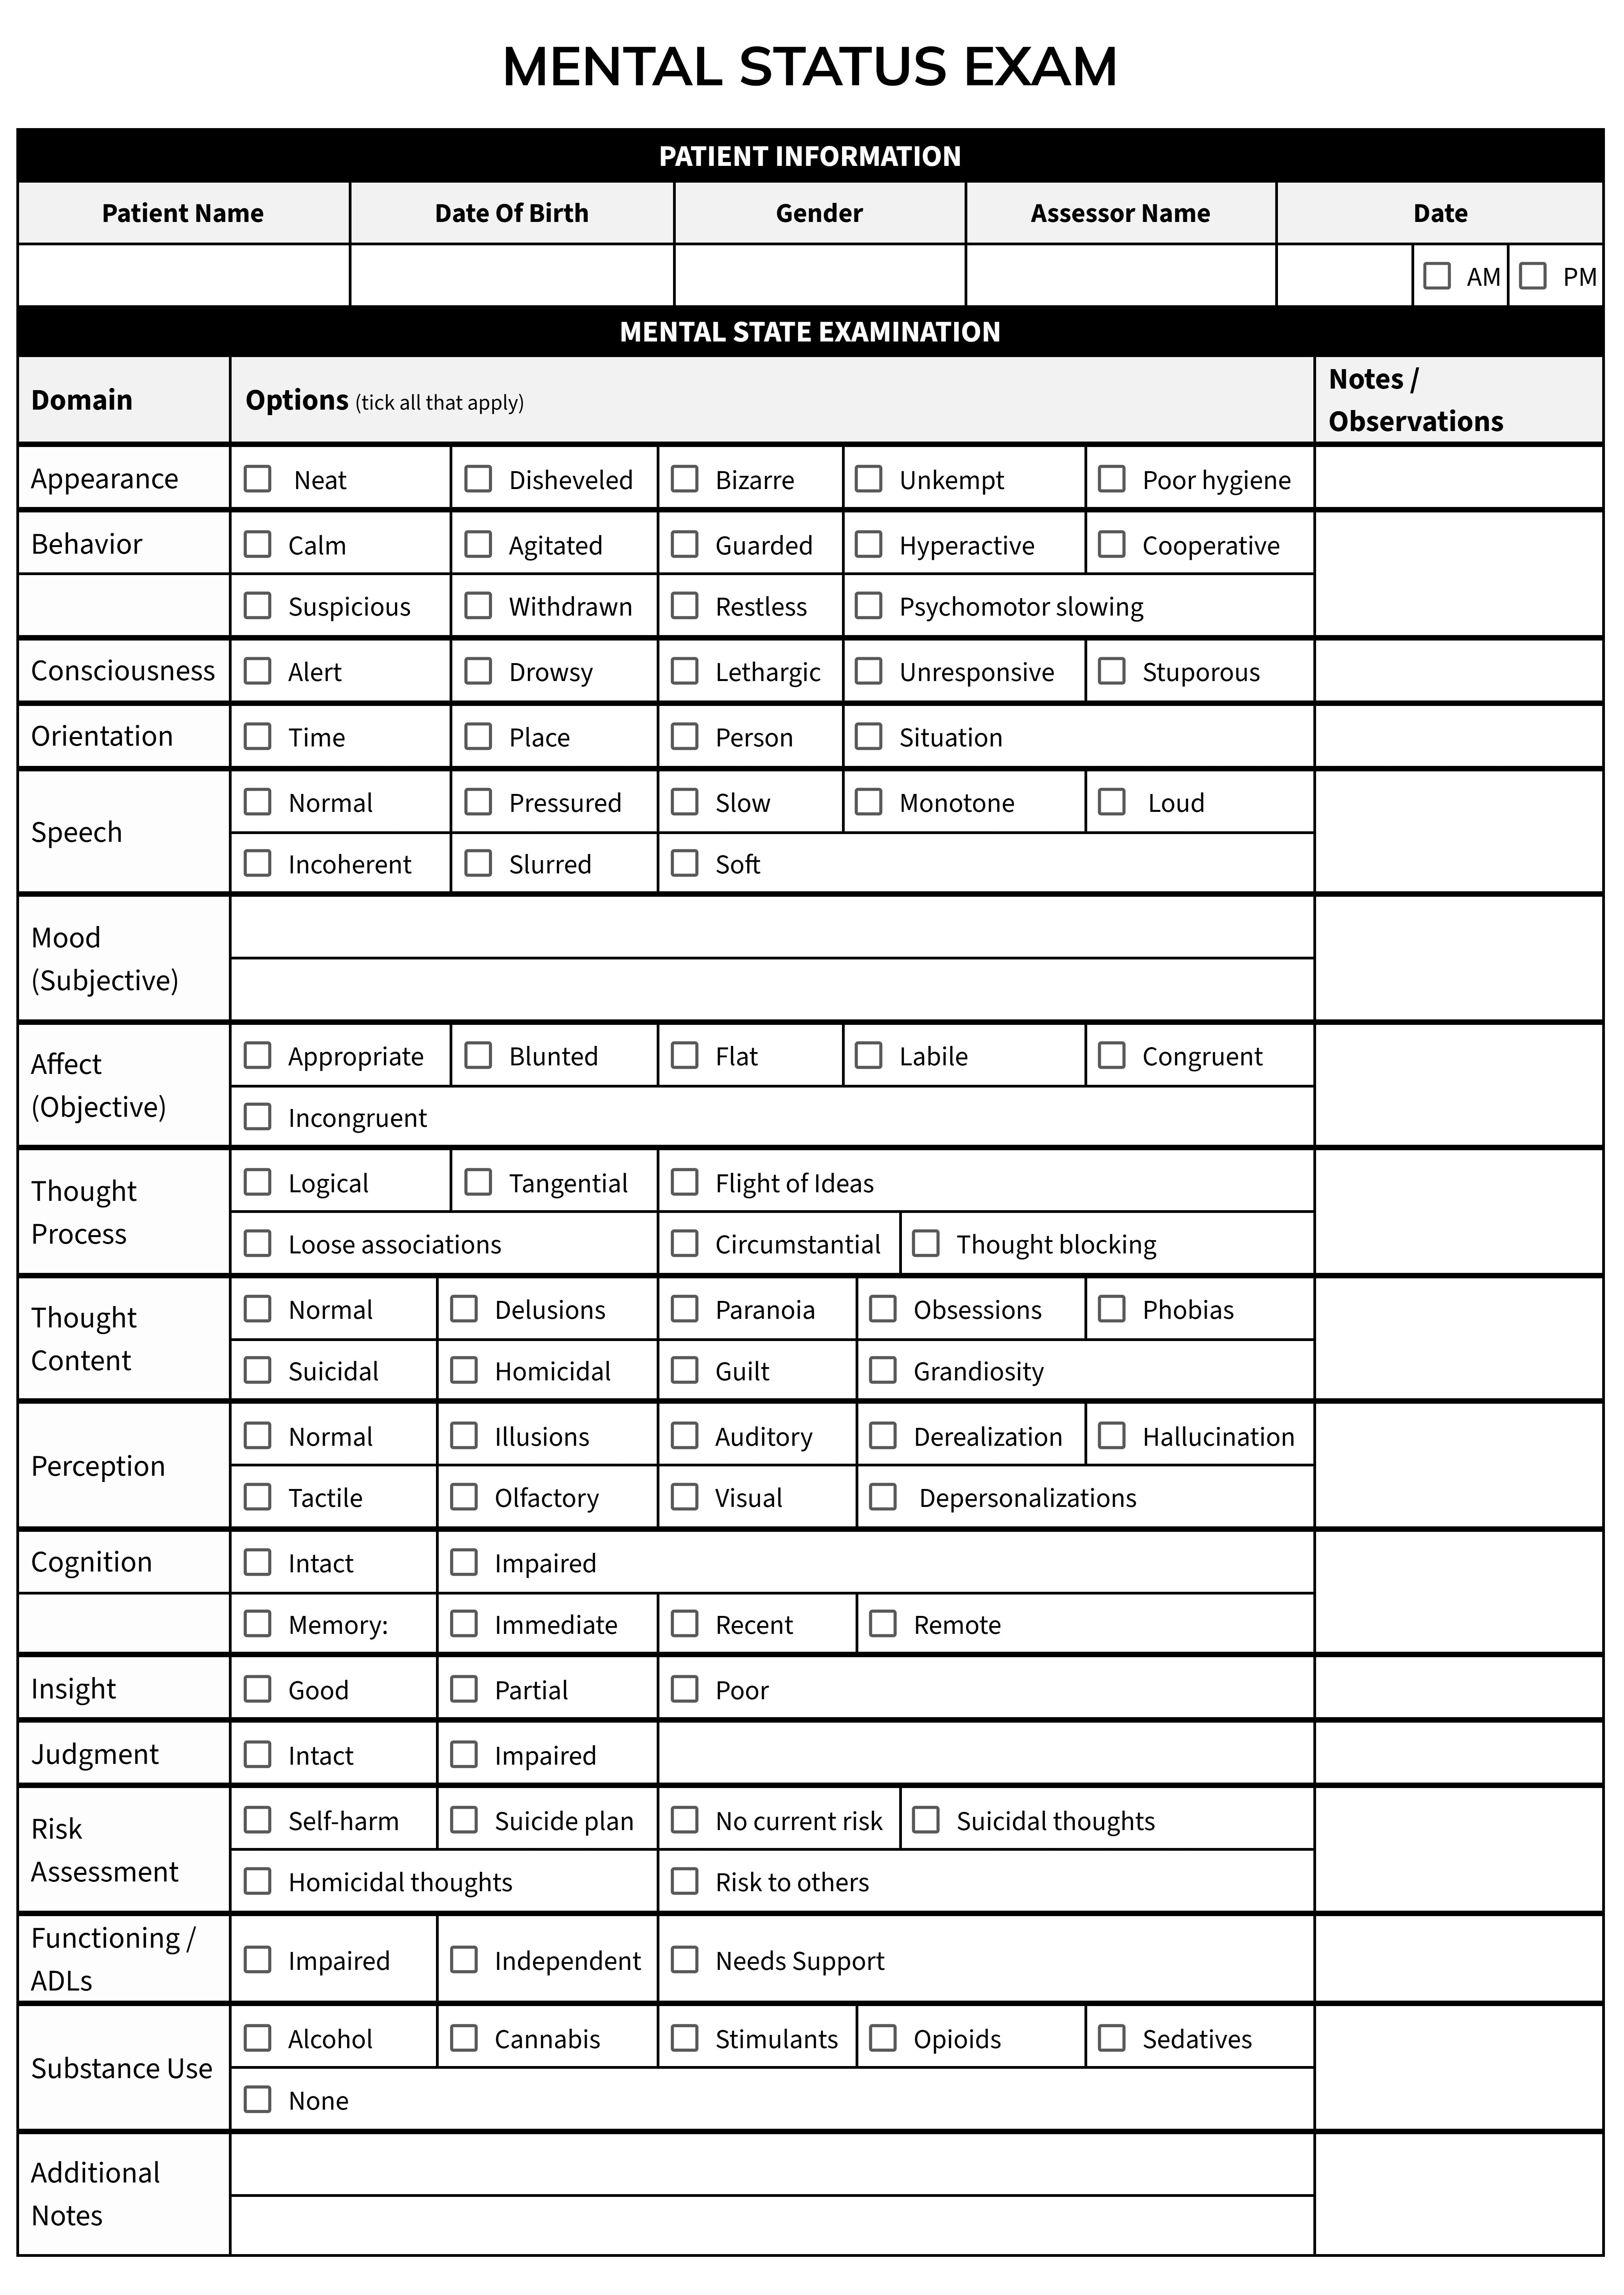
Mood: Patient's self-reported emotional state. Use their exact words when possible. Affect: Observed emotional expression. Range, stability, appropriateness, congruence with mood. Thought Process: Linear, tangential, circumstantial, loose associations, flight of ideas, thought blocking.
Thought Content: Delusions, obsessions, pre occupations, suicidal ideation, homicidal ideation, paranoia. Perception: Hallucinations, illusions, depersonalization, derealization. Cognition: Alertness, orientation, attention, memory, abstract reasoning, fund of knowledge.
Insight: Awareness of condition, acknowledgment of symptoms, understanding of need for treatment. Judgment: Ability to make sound decisions, especially in social and legal contexts.
How to Actually Use This Without Turning Into a Robot
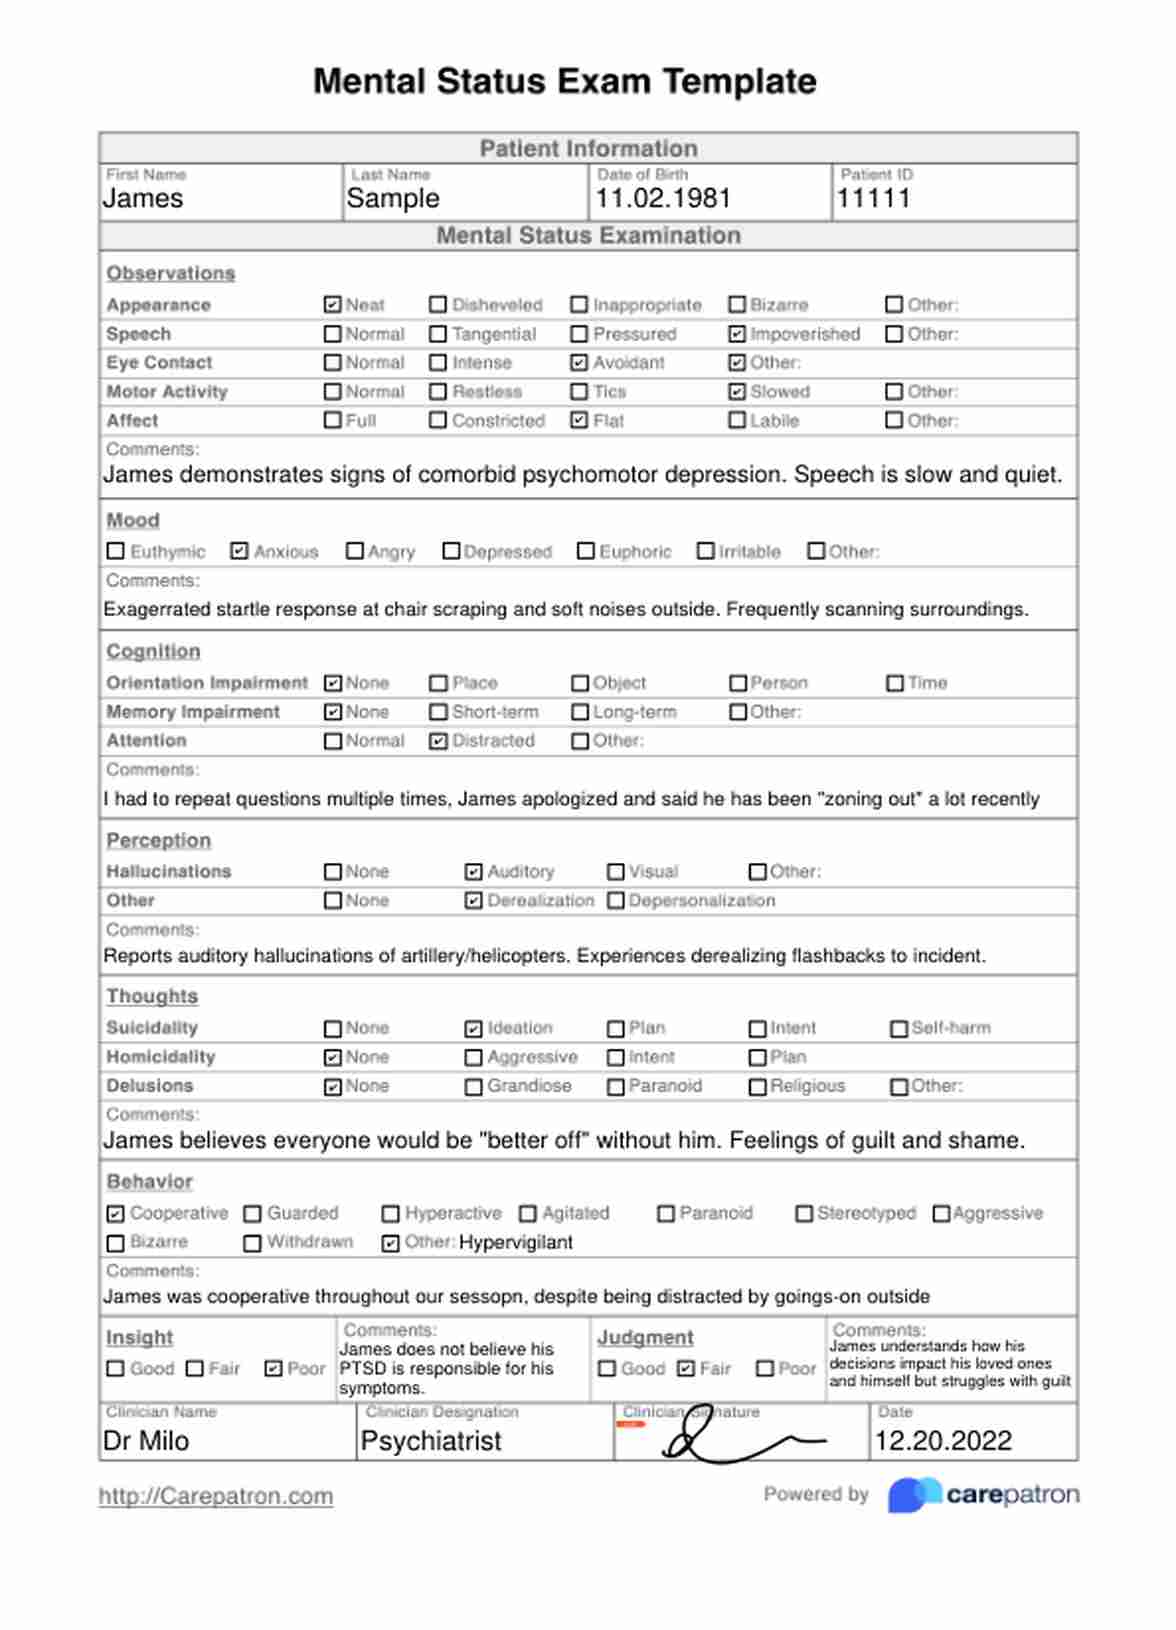
The biggest mistake I see is clinicians writing like they are describing a specimen, not a person. "Patient is well groomed with normal speech" tells you nothing useful. Specify what you saw. "Dressed in clean but layered clothing appropriate for season. Speech was clear, normal rate, occasional slight elevation in volume when discussing family." That is actual clinical data. Here is a realistic edge case I ran into last year. A patient presented with flat affect and minimal speech. The template boxes were screaming depression or schizophrenia. But they had been intubated the day before for pneumonia and were still recovering. Their cognitive slowing was metabolic, not psychiatric. If I had just filled out the template mechanically, I would have sent them down a completely wrong diagnostic path. The workaround was simple: I asked about recent medical events before starting the MSE. Two minutes of history saved a mislabeling that could have taken weeks to correct. This happens more often than you would think. ICU patients, post-op patients, anyone on anticholinergics, benzodiazepines, or recent steroid bursts can look psychiatrically abnormal on paper while having zero primary psychiatric pathology. The template does not account for that. You have to.
Common Pitfalls Beginners Miss
Confusing mood and affect is the most frequent error. Mood is what the patient says they feel. Affect is what you observe. They should roughly align, and when they do not, that misalignment is clinically significant. A patient saying they are "fine" while crying silently has a discordant mood and affect. Document that discrepancy. It matters. Another issue is documenting thought process without actually testing it. Saying "thought process is linear" is meaningless unless you can show evidence of it. Quote the patient or describe a specific exchange. "When asked about reasons for admission, patient stated 'I couldn't stop thinking about it. It just kept going and going until I couldn't take it anymore.' This suggested pressured, continuous thought flow without interruptions." Cognition assessments are where most templates fail. Most just list "oriented x4" and call it done. Orientation alone tells you almost nothing about actual cognitive function. A patient can be oriented to person, place, time, and situation and still have significant executive dysfunction. Include at least a basic serial sevens or months backward test if you are claiming to assess cognition. Three minutes of work adds real clinical value.
Limitations You Need to Accept
A static template cannot capture the full picture of a complex patient. It is a tool, not an assessment. The MSE is inherently limited to the moment of examination. A patient may present with flat affect in your office and have a completely different presentation at home. That does not make your documentation wrong, but it means you should note the setting and conditions under which you observed things. Structured templates also create a false sense of completeness. Filling every field does not mean you have conducted a thorough exam. I have seen clinicians check every box while the patient was actively hallucinating behind them because the clinician was too focused on formatting to notice. Speed reading a patient to match template fields is one of the fastest ways to miss critical information. For patients with severe aphasia, dementia, or psychotic disorganization, standard MSE templates become nearly useless. The domains still apply, but the ability to complete them reliably drops sharply. In those cases, collateral history from family or caregivers is not optional, it is required to fill the gaps your template cannot reach. Do not skip it because it is inconvenient.

Practical Workflow
Here is how I actually do this in practice. I start with observation before I say a word to the patient. Appearance and behavior are picked up immediately. Then I move through speech and motor while engaging the patient in simple conversation. Mood and affect emerge naturally during the interview. Thought process and content require active questioning. Perception needs direct inquiry about auditory or visual experiences. Cognition and insight come last when the patient is established enough to handle structured tasks. This takes about fifteen to twenty minutes for a standard adult intake. With a template already prepared, you are looking at maybe five minutes of actual writing time after the interview. The time savings come from having the structure memorized and the template ready, not from skipping steps. If you are new to this, practice on yourself first. Document your own mental status on different days and compare. You will immediately see how your appearance, affect, and thought process vary based on sleep, stress, and caffeine intake. It is the fastest way to understand why every field in this template exists and why each one deserves attention.
Download the Template
The template above can be copied directly into any document editor. I would recommend adding columns for date, time, and evaluator name if your facility requires charting compliance. Some practices also add a section for risk assessment, which is separate from the MSE proper but practically inseparable in real-world documentation. Do not over-engineer this. A clean two-page template that covers all domains without excessive sub-fields will serve you better than a twenty-page form that nobody fills out completely. I have worked in clinics where the mandatory MSE form was so detailed that clinicians started rubber-stamping fields rather than assessing them. The paperwork looked impressive. The clinical value was essentially zero. The Free Mental Status Exam Template linked here is intentionally sparse. It forces you to write actual observations instead of checking boxes. That is the point. Everything else is noise.