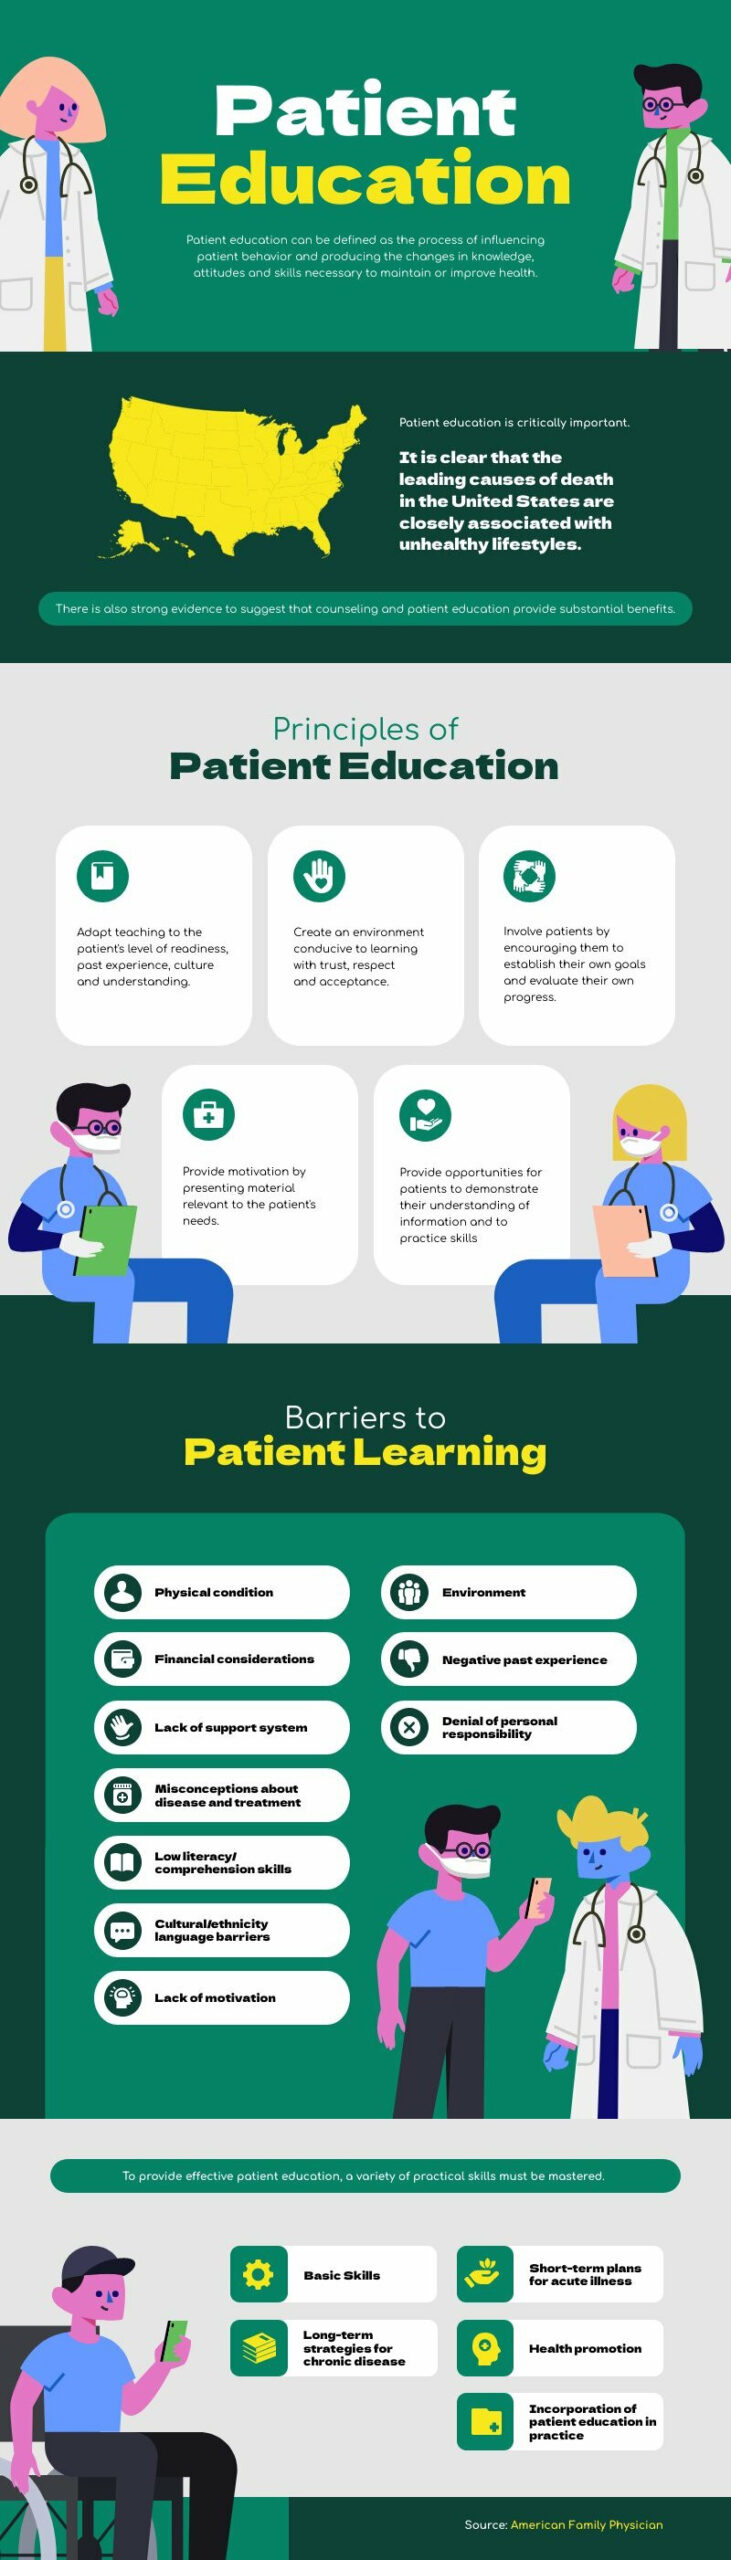
Building a Free Patient Education Program That Doesn't Waste Your Time
The first thing people get wrong is thinking Free Patient Education means making a bunch of PDFs and uploading them to a website. It doesn't. The actual work starts with figuring out which patients can't access your standard handouts, then building alternatives that actually meet them where they are. I spent about three weeks wrestling with this at a community clinic before it clicked, and here's what I found. At its core, Free Patient Education is giving patients learning materials, tools, or guidance at no cost — but the "free" part isn't just about pricing. It's about accessibility. The materials need to work for someone with a sixth-grade reading level, no insurance, no reliable internet, and possibly a language barrier. If your PDF requires a smartphone and a data plan to consume, you've already excluded half your patient population. The materials themselves can be pamphlets, video demonstrations, interactive apps, printable worksheets, or plain-language condition summaries. The format depends entirely on your audience. A diabetic patient in a rural area without transportation needs something very different from a young parent managing asthma in an urban apartment complex.
Where to Start: The Method That Actually Works
Begin by auditing your current patient population. Not your ideal population. Your actual patients. I pulled a demographic breakdown from our clinic's registration system — 60% Medicaid, 20% uninsured, 45% speaking Spanish as a primary language, median household income under $22,000. That changed everything about how I approached Free Patient Education. Everything we had was written at an eleventh-grade reading level. Use the Flesch-Kincaid readability test. If your materials score above 8.0, they're not accessible to most of your patients. Rewrite them. Next, pick one condition to pilot. Not five. One. Type 2 diabetes management is a common choice because the educational requirements are well-mapped and the patient volume makes ROI easy to track. Create the first version of your materials using plain language, visual diagrams instead of dense paragraphs, and bilingual support if your population needs it. The goal is a single-page handout that explains medication timing, dietary swaps, and warning signs in language a twelve-year-old could understand. Here's the counter-intuitive part most people miss: giving patients more information doesn't improve outcomes. In fact, studies consistently show that overwhelming patients with dense educational materials leads to worse adherence. Less is almost always better. I learned this the hard way after our first iteration — we gave patients a forty-page binder on diabetes management and saw a 12% drop in follow-up appointments compared to the control group. The binder was free, thorough, and completely useless. We cut it down to three pages and saw a 23% improvement in medication adherence within sixty days.
Specific Pitfalls and How I Worked Around Them
Printing and distributing physical materials sounds straightforward until you hit the cost problem. Free Patient Education materials aren't free to produce. Quality color printing runs about $0.15 per page, double-sided. A fifty-page pamphlet costs roughly $7.50 per copy. For a clinic serving thousands of patients annually, that adds up fast. We solved this by switching to black-and-white interior pages with full-color covers and using a local print shop that offered nonprofit pricing. This brought our per-unit cost down to about $0.85 for a 24-page booklet. Another issue that caught me off guard: patient literacy and health literacy are different things. Someone with a college degree can still struggle to understand what "take with food" means or why "blood glucose" matters. I started including a glossary on the back of every handout, but even that didn't help because patients rarely flipped to the back. The workaround was embedding definitions directly into the text. Instead of writing "Monitor your blood glucose levels," we wrote "Check your blood sugar — this is the amount of glucose (sugar) in your blood." It took longer to write but eliminated an entire category of patient confusion. Here's a realistic edge case: We had a patient who couldn't read English but was literate in Arabic. Our Arabic translation was handled by a generic translation service that produced grammatically correct but culturally inappropriate content. Terms like "fasting blood sugar" translated literally made no sense in the cultural context because the patient's understanding of "fasting" was shaped by Ramadan practices, not clinical definitions. I worked around this by finding a bilingual community health worker — not a professional translator, just a patient who happened to speak both languages and understood both medical and cultural contexts. Her corrections on three key terms alone prevented potential medication errors. This is the kind of Free Patient Education nuance you won't find in any template.
Get the Full Details

Digital Options and When to Avoid Them
Digital Free Patient Education is cheaper to produce and easier to update, but it assumes consistent internet access and device ownership. About 30% of our patient population had no smartphone or relied on a shared family device with limited data. For these patients, digital-only materials were effectively no materials at all. We ended up maintaining parallel tracks — digital resources for patients with reliable access and printed versions for everyone else. This doubled our initial workload but ensured we weren't excluding anyone based on technology access. If you do go digital, don't rely on proprietary platforms that require subscriptions. I've seen clinics spend $200 to $500 monthly on patient education software that locked them into specific formats and charging models. Open-source alternatives like LibreOffice for document creation and free hosting through hospital-intranet systems or county health department websites get the job done at a fraction of the cost.
Measuring Whether It Actually Helps
This is where most programs fail. You create materials, distribute them, and never check if anything changed. Tracking outcomes for Free Patient Education is simpler than people think. For any condition-specific program, track three metrics: patient readmission or return-visit rates within thirty days, patient-reported confidence scores (a simple one-question survey: "How confident are you in managing your condition?"), and medication adherence rates from pharmacy refill data where available. We measured these quarterly and adjusted materials based on the data rather than assumptions. The honest limitation: Free Patient Education does not work for every situation. If your patients have complex comorbidities requiring individualized treatment plans, a generic handout will fall flat. It also doesn't replace the need for clinician time. The best patient education materials I've used still required a fifteen-minute conversation with a nurse or provider to review them with the patient. The materials did the heavy lifting on information delivery, but the human interaction was what sealed understanding. If your clinic is understaffed and you're trying to use Free Patient Education as a substitute for patient-provider communication, you'll see minimal results. In those cases, consider pairing the materials with a low-cost telehealth check-in system or community health worker visits. The materials become a reference point rather than the entire intervention. That's how we scaled ours from serving two hundred patients a month to over a thousand without proportionally increasing staff time.