Why Your Clinic Is Still Paper-Stacking Instead of Digitizing Skin Checks
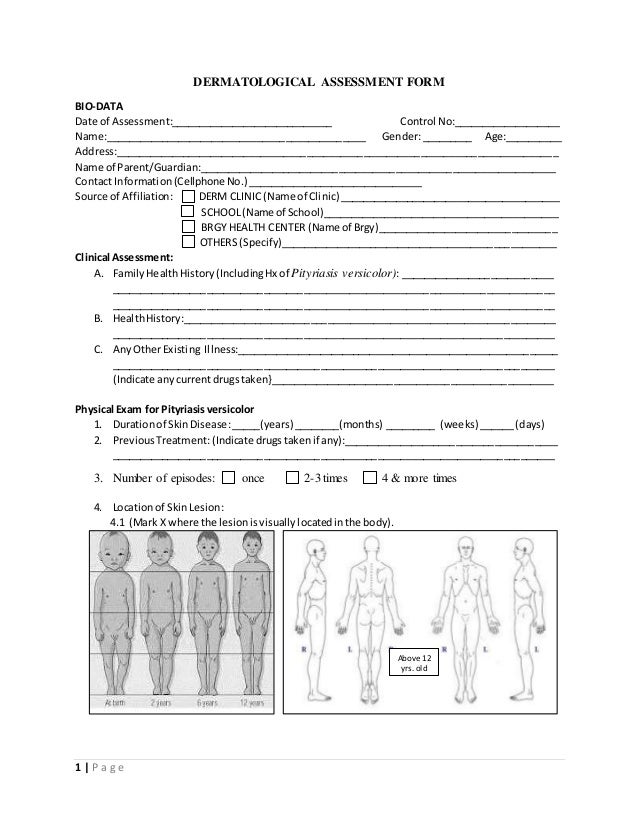
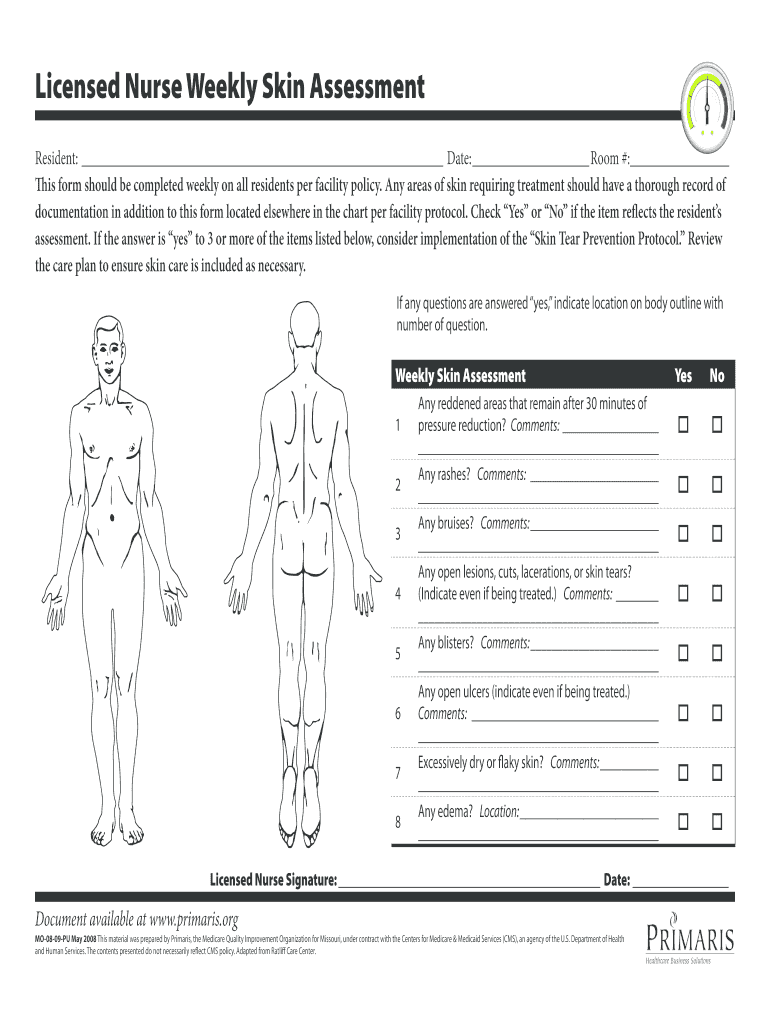
The first time I ran across a free printable skin assessment form, it was 2018, and I was working at a small outpatient wound care clinic that had somehow survived three EHR migrations by refusing to participate in any of them. The forms came from a state nursing board website. They were two pages long, formatted like something designed in Word 2003, and they had a column for "skin temperature" that offered no checkboxes or scales. Just a blank line. I stared at that line for ten minutes before realizing nobody had ever actually filled it out correctly. That line stayed blank on every single form we produced for the next two years. These are what they sound like: standardized templates for documenting skin condition, wound progression, or pressure injury staging that you can download, print, and fill out by hand. Some are plain PDFs. Some are Word documents you edit before printing. The quality ranges from "state health department official document" to "some nurse's daughter designed this in Canva and posted it on a parenting blog." The most useful ones you'll find typically include a body outline diagram, a staging section for pressure injuries (Braden or Clark system), space for lesion measurements in centimeters, a color scale for wound bed tissue type, and a notes field. The ones that skip the measurement grid and rely entirely on subjective descriptions tend to produce audit-ready documentation that would get laughed out of a wound care certification review.
I keep a folder on my desktop called "Forms." It contains about forty-seven different skin assessment templates, all collected over roughly a decade. Most of them gather dust. The ones I actually use consistently come from three sources: the National Pressure Injury Advisory Panel (NPIAP) staging guidelines PDF, a modified version of the Bates-Jensen Wound Assessment Tool that someone at a university hospital posted to their public resource page, and a simple one-page form from a state home health nursing association that I modified once to include millimeter gradation on the body diagram. The Bates-Jensen modification is where I learned the first real lesson about printable forms. The original tool has eleven items, each scored one through ten. It produces a total score that tracks wound healing over time. Very solid. But when I printed it out for home health visits, nurses were spending roughly six to eight minutes per assessment just writing down individual scores. For a patient with multiple wounds, that climbed to twenty-plus minutes per visit. The form itself wasn't the problem. The problem was that nobody had designed it for rapid clinical workflow. So I created a simplified version that combined the eleven items into a grid where each wound got its own row and the scoring columns were condensed. It dropped assessment time to about four minutes per wound, and the scores remained clinically comparable to the full tool because the underlying metrics hadn't changed. They just weren't presented as eleven separate bubbles anymore. That's the thing nobody tells you about printable skin assessment forms: the form doesn't need to be comprehensive. It needs to be completed. A shorter form with honest data beats a thorough form that gets half-filled because the nurse gave up partway through. I've seen documentation audits fail because the assessor wrote "stable" in a notes field instead of recording a numeric pressure injury score. The word "stable" is not a metric. It's a feeling.
What to Look for in a Form Before You Print Fifty Copies
The first thing I check is whether the form includes a date and time field for each entry. Without that, serial assessments lose their chronological anchor, and you cannot track wound progression reliably. A form with a date field but no time field is marginally better but still leaves ambiguity when wound exudate levels change between morning and afternoon dressing changes. Second, I look for a measurement system. Centimeters or millimeters, not inches. Wound care documentation standards have been metric for thirty years. If the form uses inches, I print it anyway and immediately draw a small "cm/mm" legend in the corner before distributing it. Nurses will adapt, but the adaptation takes time they don't have. Third, I verify that the pressure injury staging section matches the current NPIAP guidelines. The 2019 update reclassified unstageable pressure injuries and clarified the distinction between suspect deep tissue injury and actual stage 4. Forms that reference the older Clark staging system or list "stage 3 unstageable" as a single category are using outdated terminology. Printing an outdated form creates confusion during audits and gives regulatory reviewers ammunition they don't need to look for.
Get the Full Details
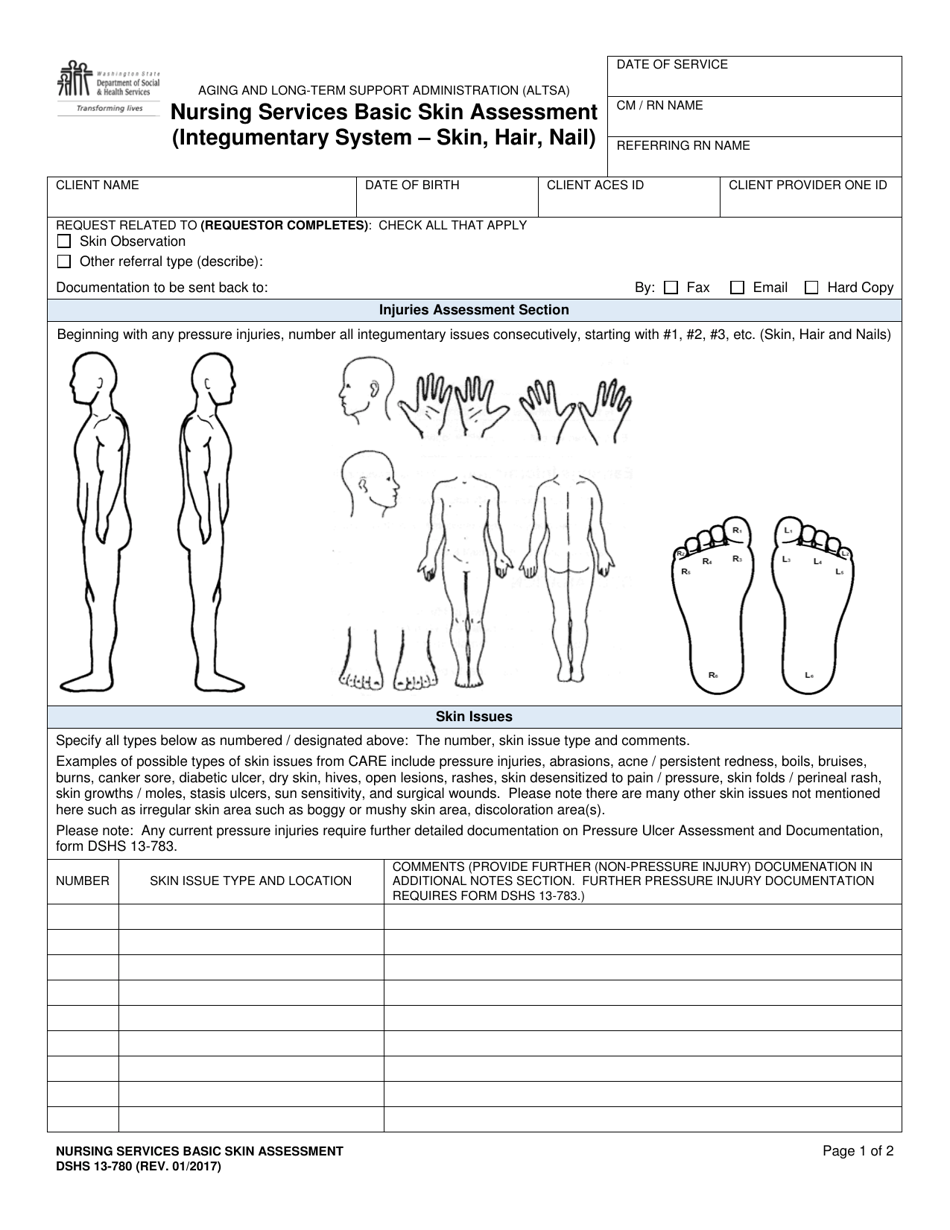
Here's an edge case that cost me about forty hours of corrective documentation: I once distributed a form that included a section for "skin moisture" with checkboxes for normal, dry, and moist. A resident at a skilled nursing facility developed a Stage 2 pressure injury on the sacrum. The form showed "normal" moisture selected on the previous assessment, but the wound developed over three days because the incontinence-related skin exposure wasn't captured by those three checkboxes. There was no option for "continent," "mildly incontinent," or "heavy incontinence with barrier cream." I replaced that form within a week and rewrote the moisture section to include incontinence status as a separate variable. The original form designer probably meant well. The three-checkbox system was just inadequate for a population that spends significant time with briefs and containment devices.
How to Actually Use These Forms Without Making Them Useless
Print them on standard letter paper. Do not print them on cardstock or specialty paper. The scanners at most reviewing agencies and the photocopiers at most insurance auditor offices are calibrated for 20-pound bond paper. Specialty stock jams machines and creates illegible copies. If you need durability, laminate a single reference copy. Don't laminate the actual assessment form. Inkjet smearing is a real problem with laminated paper exposed to wound exudate or alcohol swabs during documentation. Use a black ballpoint pen. Gel pens and fine-point markers create bleed-through on standard copier paper and produce inconsistent line widths whenphotocopied. Ballpoint ink transfers cleanly and reads consistently at 72 DPI, which is the scanning resolution most auditors use. I learned this the hard way during a CMS survey where the reviewer couldn't distinguish between a Stage 2 and a Stage 3 designation because a gel pen had bled through the page and blurred the tissue depth description. Record measurements immediately. Do not measure a wound and then walk across the room to fill out the form. The measurement drifts. The wound contracts, rehydrates, bleeds slightly. The numbers change. I timed this once: measuring a 3-centimeter sacral ulcer and then walking to the documentation cart took approximately forty-five seconds. When I measured the same ulcer after that interval, it read 2.8 centimeters in the longest dimension. That 0.2-centimeter difference looked like improvement on paper. It was actually just the wound doing what wounds do.
Take a photograph when the form allows it. Many printable forms now include a space or reference for clinical photography. The form itself is supplementary documentation. A calibrated photograph with a ruler in the frame provides objective evidence that a handwritten measurement cannot. I recommend placing the photo in the patient's electronic file with a reference to the printed form number so the two documents stay linked.
Where to Find Them and What to Avoid
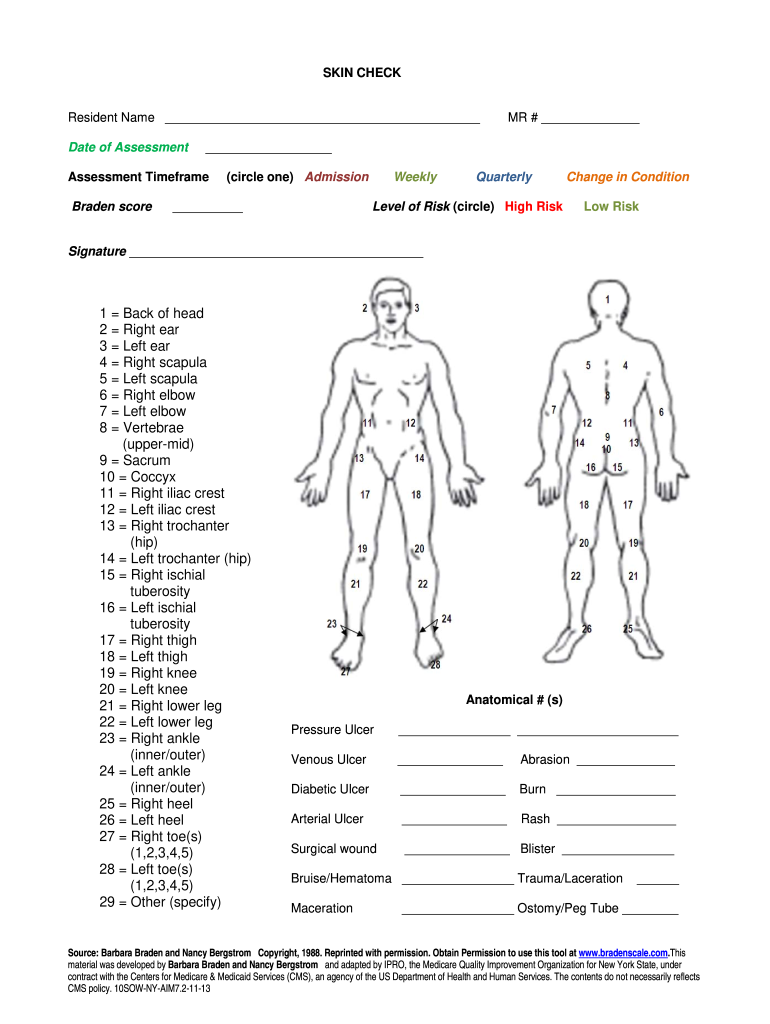
The NPIAP website offers free downloadable resources including staging guides and several assessment templates. The American Geriatrics Society publishes a pressure injury prevention packet that includes printable forms. State health departments often host wound care documentation tools on their public nursing resources pages. University hospital wound care centers sometimes publish adapted forms on their websites as educational materials. These are generally the most reliable sources because they come from organizations that update their content when guidelines change. Avoid forms found on random blog posts, Pinterest boards, or social media groups unless you can verify the author's credentials. I've seen a form circulating in a Facebook nursing group that listed "Stage 1: non-blanchable erythema of intact skin" and then had a checkbox for "blanchable erythema" as if blanchable erythema were a pressure injury stage. It isn't. Blanchable erythema is normal skin response to pressure. Marking it as a stage is clinically wrong and audit-unsafe. The person who posted that form had good intentions but clearly hadn't worked in wound care for more than a year, if that. There is also a practical limitation to keep in mind: printable forms cannot replace digital decision support. A paper form will not flag a Braden score below twelve as high risk. It will not remind you to reassess a stage 2 injury after fourteen days if it hasn't shown measurable improvement. It will not cross-reference a patient's lab values with their skin integrity data. If your facility handles more than fifty wound assessments per week, the printable form is a starting point, not a system. You'll still need a tracking mechanism, whether that's a spreadsheet, a clipboard log, or an actual EHR module.
The Bates-Jensen modification I mentioned earlier works well for settings that generate fewer than twenty assessments per day. Beyond that threshold, the time savings from a simplified form erode because you're managing physical paper storage, retrieval, and scanning. A shared digital template with mandatory fields prevents incomplete submissions the way a paper form never will. But for small clinics, home health rotations, school nursing programs, and correctional facilities where IT budgets don't exist, the printable form remains the only practical option. It's not elegant. It's not automated. It's functional.
One More Thing About the Blank Line
That blank line for skin temperature from the original state board form? I eventually learned what to do with it. Most community health settings don't have infrared thermometers at the point of care. So I added two options: "not assessed" and "normal." If the nurse doesn't have the equipment, she checks "not assessed" and moves on. If she does, she writes the reading. Neither answer is wrong. The problem was the original design forced a choice between writing a number or leaving it empty, and leaving it empty looked like negligence on an audit even when it was just a documentation gap. Adding the explicit "not assessed" option solved that. It told the reviewer exactly why the field was blank. Context matters more than completeness.