What a Free Psychosocial Assessment Form Actually Gets Done
Most free versions you find online are either too generic to use in a real clinical setting or they're missing the sections that actually matter—functional impairment tracking, cultural context notes, and risk stratification. I've spent years filling out assessments with clients across multiple settings, and the ones I rely on are the ones that force you to differentiate between someone who is struggling and someone who is in acute crisis.Free Psychosocial Assessment Form: Where to Find a Usable One
Government health sites like the UK's NHS Trust resources and state mental health department portals in the US tend to publish forms that are actually field-tested. The SAMHSA treatment improvement protocol documents have downloadable assessment templates. Those are worth starting with. Private practice consultants on forums sometimes share their cleaned-up versions too. Look for forms that break down into clear domains: biological, psychological, social, occupational, and spiritual. If it's just a long list of open-ended questions with no scoring guidance, skip it. A usable psychosocial assessment needs to capture the baseline before the intervention, so structure matters more than word count. I usually take a government template and layer my own section on top for environmental stressors and protective factors. That's where the real clinical signal lives, not in the standard demographic boxes.
How to Actually Fill One Out Without Wasting Afternoon Time
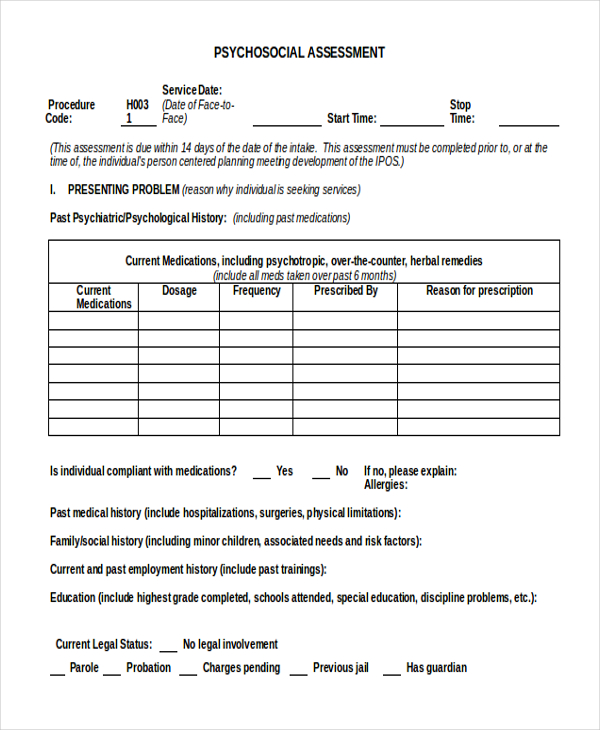
Start with presenting concerns and history before you touch anything else. Get the reason they're here in the client's own words when you can, then anchor it to timeline. Dates matter. I've had review panels ask me to justify a diagnosis three years later and the only thing I had was vague language like "recent changes." That doesn't hold up. A concrete timeline does. Next goes current functioning. Sleep, appetite, concentration, mood, daily activities. These aren't checkboxes. If someone says they're sleeping four hours but they've been doing it for six months, that's chronic insomnia, not acute stress. The distinction changes your treatment plan. I once worked with a counselor who marked "sleep disturbance" on a form because the client said they "don't sleep great." That's not enough. When I pushed for specifics—was it initiation? Maintenance? Early morning awakening? The answer revealed a separate anxiety cycle we'd completely missed. Then family dynamics, social support, substance use, trauma history, employment, and legal issues. Do those in order that makes sense for your conversation, not necessarily in the order the form lists them. I've restructured blank templates mid-session before. You can always transfer the answers later.
Edge Case That Will Surprise You
There's one problem I run into constantly that almost no free template addresses. Cultural expression of distress. A client from a collectivist background might describe physical symptoms—a headache, chest tightness, stomach pain—instead of saying "I feel depressed." The form I use now has a dedicated section for somatic presentation and culturally specific idioms of distress. Without it, you're coding everything as a medical complaint and sending the wrong referral. I adapted a template from a community health center in Toronto that included a field for "cultural formulation interview" notes based on the DSM-5's cultural concept of distress framework. It added about three minutes to the intake but it caught something I would have otherwise missed twice in my first year using the standard format.
Get the Full Details
Pitfalls Beginners Keep Making
The biggest mistake is treating the assessment as a one-time event. A psychosocial assessment is a living document. Update it at each major session change or at minimum quarterly. The form is useless if it's sitting at page one's intake data while the client's situation has shifted significantly. Also, don't conflate severity with acuity. Someone can have a severe but stable depression and someone else can have mild symptoms with high acute risk. They need different responses. Another common error is not documenting protective factors. Every free form I see focuses on problems. Risk of suicide isn't just about listing stressors—it's about what keeps someone from acting on suicidal thoughts. Social connections, religious beliefs, parental responsibilities, even a pet. These are clinically significant and they need space on the page.
Limitations You Need to Know
Free forms will not integrate with your EHR unless you build that bridge yourself. You'll be copying data between systems, which introduces transcription errors. If you're working in a small practice with minimal overhead, that's a manageable tradeoff. If you're in an agency doing fifty intakes a month, the manual data entry adds up fast and the error rate climbs. In that case, you're better off using a low-cost platform like TherapyNotes or SimplePractice, even for just the intake module. Also, free forms rarely include standardized scoring tools. If you need PHQ-9, GAD-7, C-SSRS, or similar validated instruments embedded with automatic cutoff scoring, you'll need to pull those separately. Some agencies print them as supplements. Just keep them organized so they travel with the assessment file.
Free Psychosocial Assessment Form: Where to Download
The best starting point is the official state health department websites. Search "[your state] department of mental health psychosocial assessment template." The California Health and Human Services Agency, the New York State OMH, and the CDC's mental health resource pages all publish downloadable PDFs. For broader templates, check Psychology Tools or the American Psychological Association's practice guidelines section. Some university counseling centers also post their intake forms publicly. The one I referenced earlier—the Toronto community health center adaptation with the cultural formulation section—is available through the Ontario Ministry of Health's publicly shared clinical resources. It's not a single-file download, more like a toolkit. But it's the version that has saved me from the most oversight errors in practice.