Understanding How Nephrons Actually Work
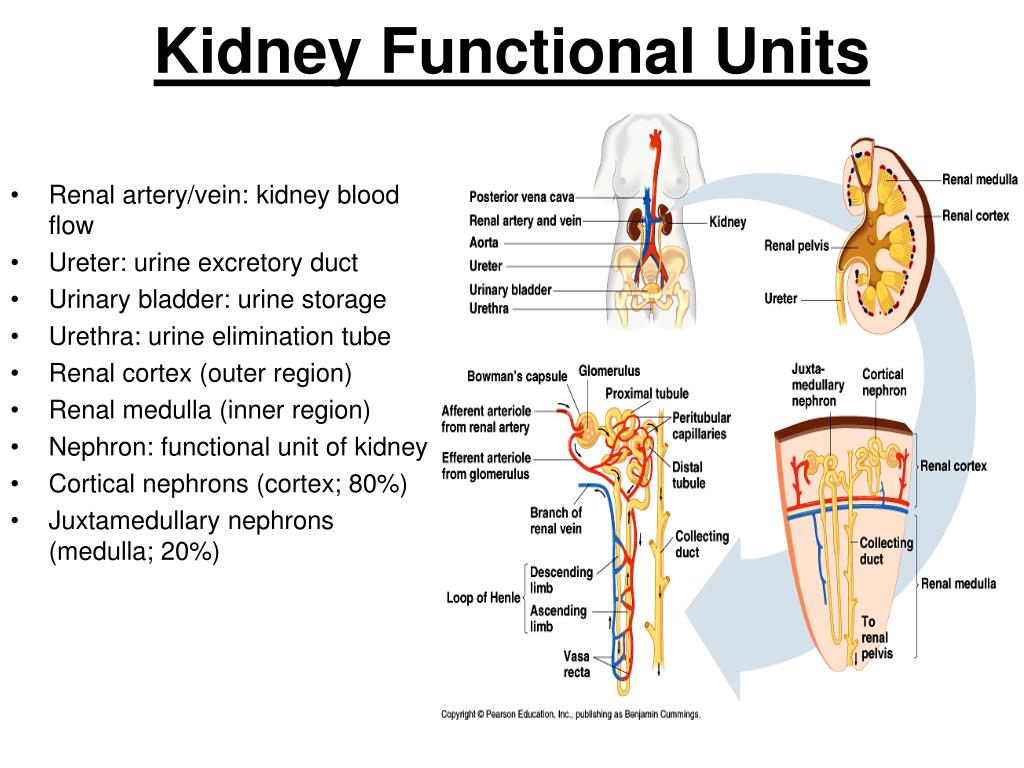
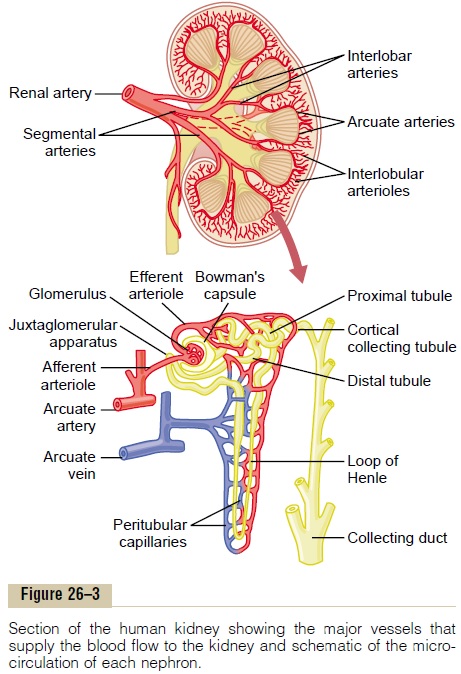
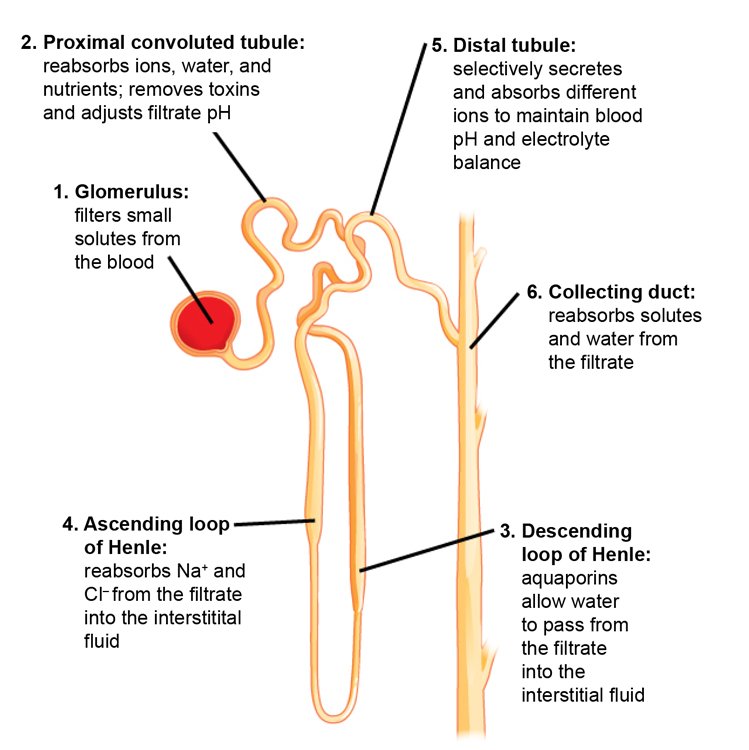
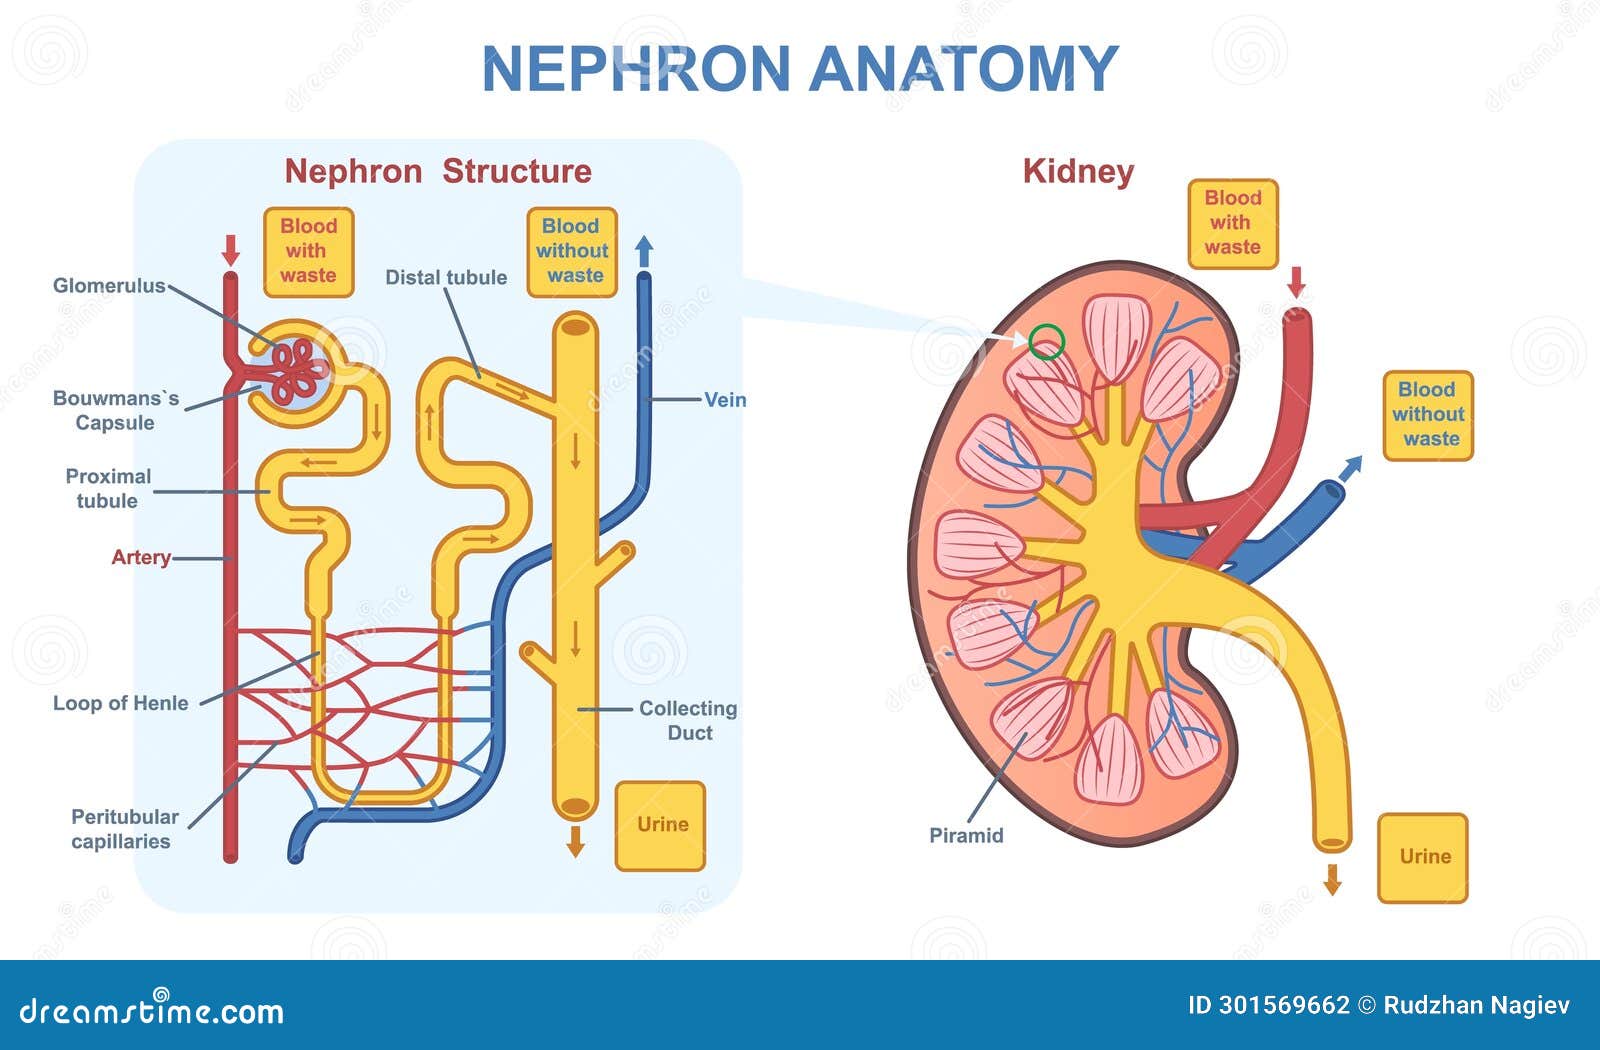
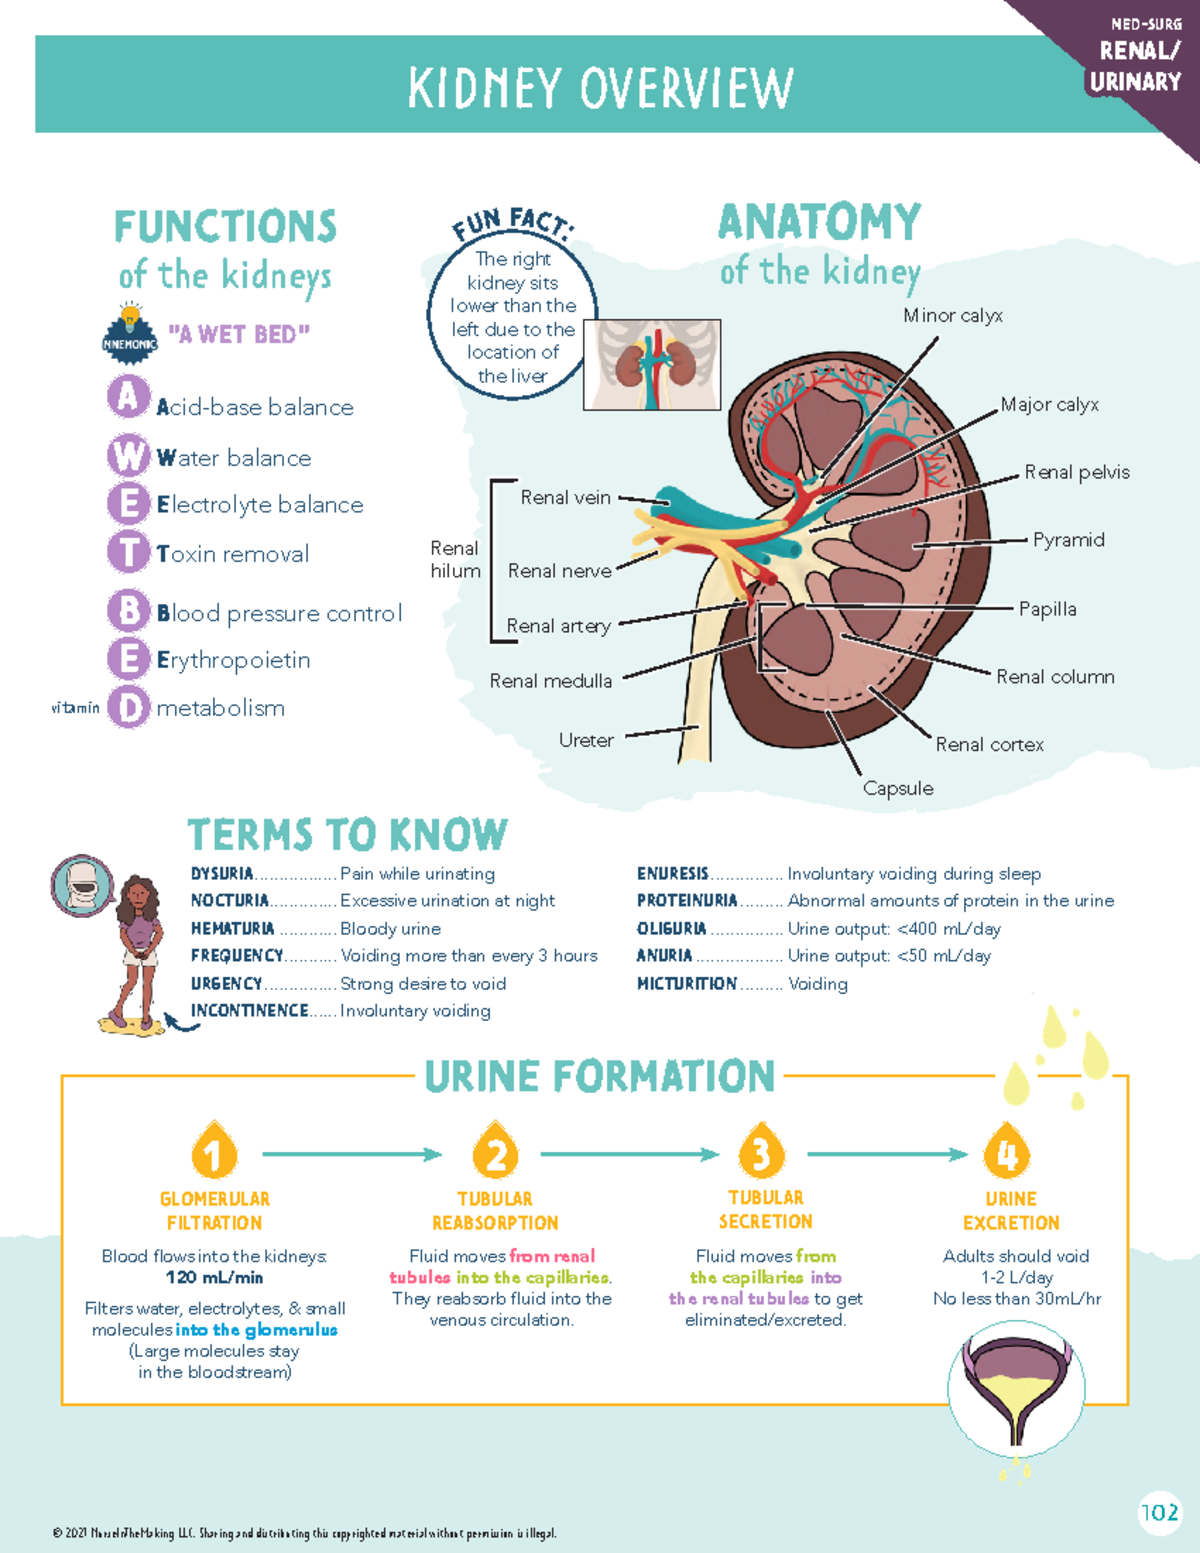
The kidney's functioning unit is called a nephron, and there are roughly one million of them packed into each kidney. They're not just simple filters. A lot of people think of the kidney as a strainer, but that's wrong. What's actually happening is far more complicated, involving multiple transport systems working in concert across different segments of each nephron. When you understand how they operate, you start seeing why kidney disease doesn't show up until significant damage has already occurred. A nephron consists of two main parts: the renal corpuscle, which handles filtration, and the renal tubule, which handles reabsorption and secretion. The renal corpuscle itself is made up of the glomerulus — a tangled ball of capillaries — and Bowman's capsule surrounding it. Blood enters through the afferent arteriole, gets filtered, and exits through the efferent arteriole. That efferent arteriole part matters more than most people realize. Unlike most capillary beds in the body, which drain into venules, the kidney's filter sits between two arterioles. This creates a high-pressure system designed specifically for bulk filtration. After filtration, the fluid travels through the proximal convoluted tubule, the loop of Henle, the distal convoluted tubule, and finally the collecting duct. Each segment does something different. The proximal tubule reabsorbs about sixty-five percent of the filtered sodium and water. It's basically the workhorse. The loop of Henle creates a concentration gradient in the surrounding tissue. The distal tubule and collecting duct are where fine-tuning happens under hormonal control. Aldosterone tells the distal tubule to reabsorb more sodium. Antidiuretic hormone tells the collecting duct to reabsorb more water. That's why dehydration makes your urine dark and concentrated.
The Filtration Barrier And What Goes Through It
The glomerular filtration barrier has three layers: the fenestrated endothelium, the glomerular basement membrane, and the podocyte foot processes. Size matters here, but so does charge. The basement membrane is rich in heparan sulfate, which repels negatively charged proteins. That's why albumin, which is negatively charged, doesn't usually show up in urine even though it's small enough to physically fit through the pores. When the charge barrier gets damaged — and this happens in conditions like minimal change disease — you get proteinuria even without visible structural changes under a light microscope. That's a key diagnostic point most textbooks gloss over. The filtration coefficient, or Kf, determines how much plasma gets filtered per unit of pressure. It depends on both the surface area available for filtration and the permeability of the barrier. In diabetes, the early change isn't just high blood sugar. It's glomerular hypertrophy and increased surface area, which initially raises Kf and causes hyperfiltration. Over years, that hyperfiltration damages the barrier. By the time you see declining GFR, the nephrons that weren't affected have taken on extra workload. They hypertrophy too. It's a vicious cycle.
Tubular Processing: Where The Real Work Happens
The proximal tubule reabsorbs glucose, amino acids, bicarbonate, and the majority of sodium and water. Sodium-glucose co-transporters (SGLT2) in the early proximal tubule handle about ninety percent of glucose reabsorption. SGLT2 inhibitors work by blocking this transporter, causing glucose to spill into the urine. That's the mechanism behind drugs like canagliflozin. But here's something people don't always connect: blocking SGLT2 also reduces the reabsorption of sodium, which decreases the osmotic drive for water reabsorption. The result is mild diuresis and a reduction in intravascular volume. That volume reduction signals the afferent arteriole to constrict, which lowers glomerular pressure. Lower pressure means less hyperfiltration damage. That's why SGLT2 inhibitors are now standard care for protecting kidney function in diabetics, independent of their glucose-lowering effect. The loop of Henle operates as a countercurrent multiplier. The descending limb is permeable to water but not salt. The ascending limb actively pumps out sodium, potassium, and chloride through the NKCC2 cotransporter, but it's impermeable to water. This creates the osmotic gradient that allows the collecting duct to concentrate urine when needed. Loop diuretics like furosemide block NKCC2. They're powerful because they disrupt the entire gradient. Once that gradient is gone, the kidney can't concentrate urine at all. Patients on chronic loop diuretics often have isotonic urine regardless of hydration status.
Get the Full Details
Practical Problems With Renal Function Testing
I've seen this issue repeatedly in clinical practice. Creatinine-based GFR estimation is the standard way to assess kidney function, but it's notoriously inaccurate in certain populations. Creatinine is freely filtered but also secreted by the proximal tubule. That secretion increases as GFR declines, which means creatinine-based estimates overestimate actual filtration rate, especially in advanced kidney disease. The CKD-EPI equation tries to correct for this with age, sex, and race adjustments, but it still has a margin of error of about thirty percent in many patients. The workaround I use is cystatin C. It's filtered by the glomerulus and reabsorbed by the proximal tubule, but unlike creatinine, it's not secreted. Cystatin C levels are less affected by muscle mass, diet, or inflammation. A combined creatinine-cystatin C equation is more accurate than either marker alone. I started using it routinely for patients whose creatinine-based GFR didn't match their clinical picture — like a low muscle mass elderly patient with a "normal" creatinine but clearly reduced kidney function. The cystatin C revealed Stage 3b CKD that creatinine alone was hiding.
Common Misunderstandings About Nephron Function
One persistent misconception is that nephrons regenerate after injury. They don't. Humans are born with their full complement of nephrons, and they don't multiply. Damage to one nephron means it's gone. The remaining nephrons compensate through hypertrophy and increased workload, but this compensation has limits. That's why protecting remaining nephron function is the entire focus of nephrology — there's no fixing lost units, only slowing the loss of the ones you have left. Another thing people get wrong is the idea that drinking lots of water flushes out the kidneys. In a healthy person, excess water intake simply suppresses ADH and produces dilute urine. The nephrons adjust without any real benefit beyond normal hydration. In someone with compromised kidney function, however, forcing fluids can be dangerous because the damaged nephrons can't excrete the free water load, leading to hyponatremia and volume overload. The one-size-fits-all advice to "drink eight glasses a day" doesn't account for varying nephron capacity across different patient populations. The autoregulation of renal blood flow is another concept that's frequently misunderstood. The kidney maintains relatively constant blood flow across a mean arterial pressure range of about seventy to one hundred seventy millimeters of mercury. This happens through myogenic mechanisms in the arterioles and tubuloglomerular feedback. When flow increases, the afferent arteriole constricts. When flow decreases, it dilates. Outside that range, autoregulation fails. That's why severe hypertension can acutely damage nephrons and why profound hypotension causes ischemic injury to the proximal tubule and thick ascending limb, which are the most metabolically active segments and therefore the most vulnerable to oxygen depletion.