Understanding What Bones Actually Do
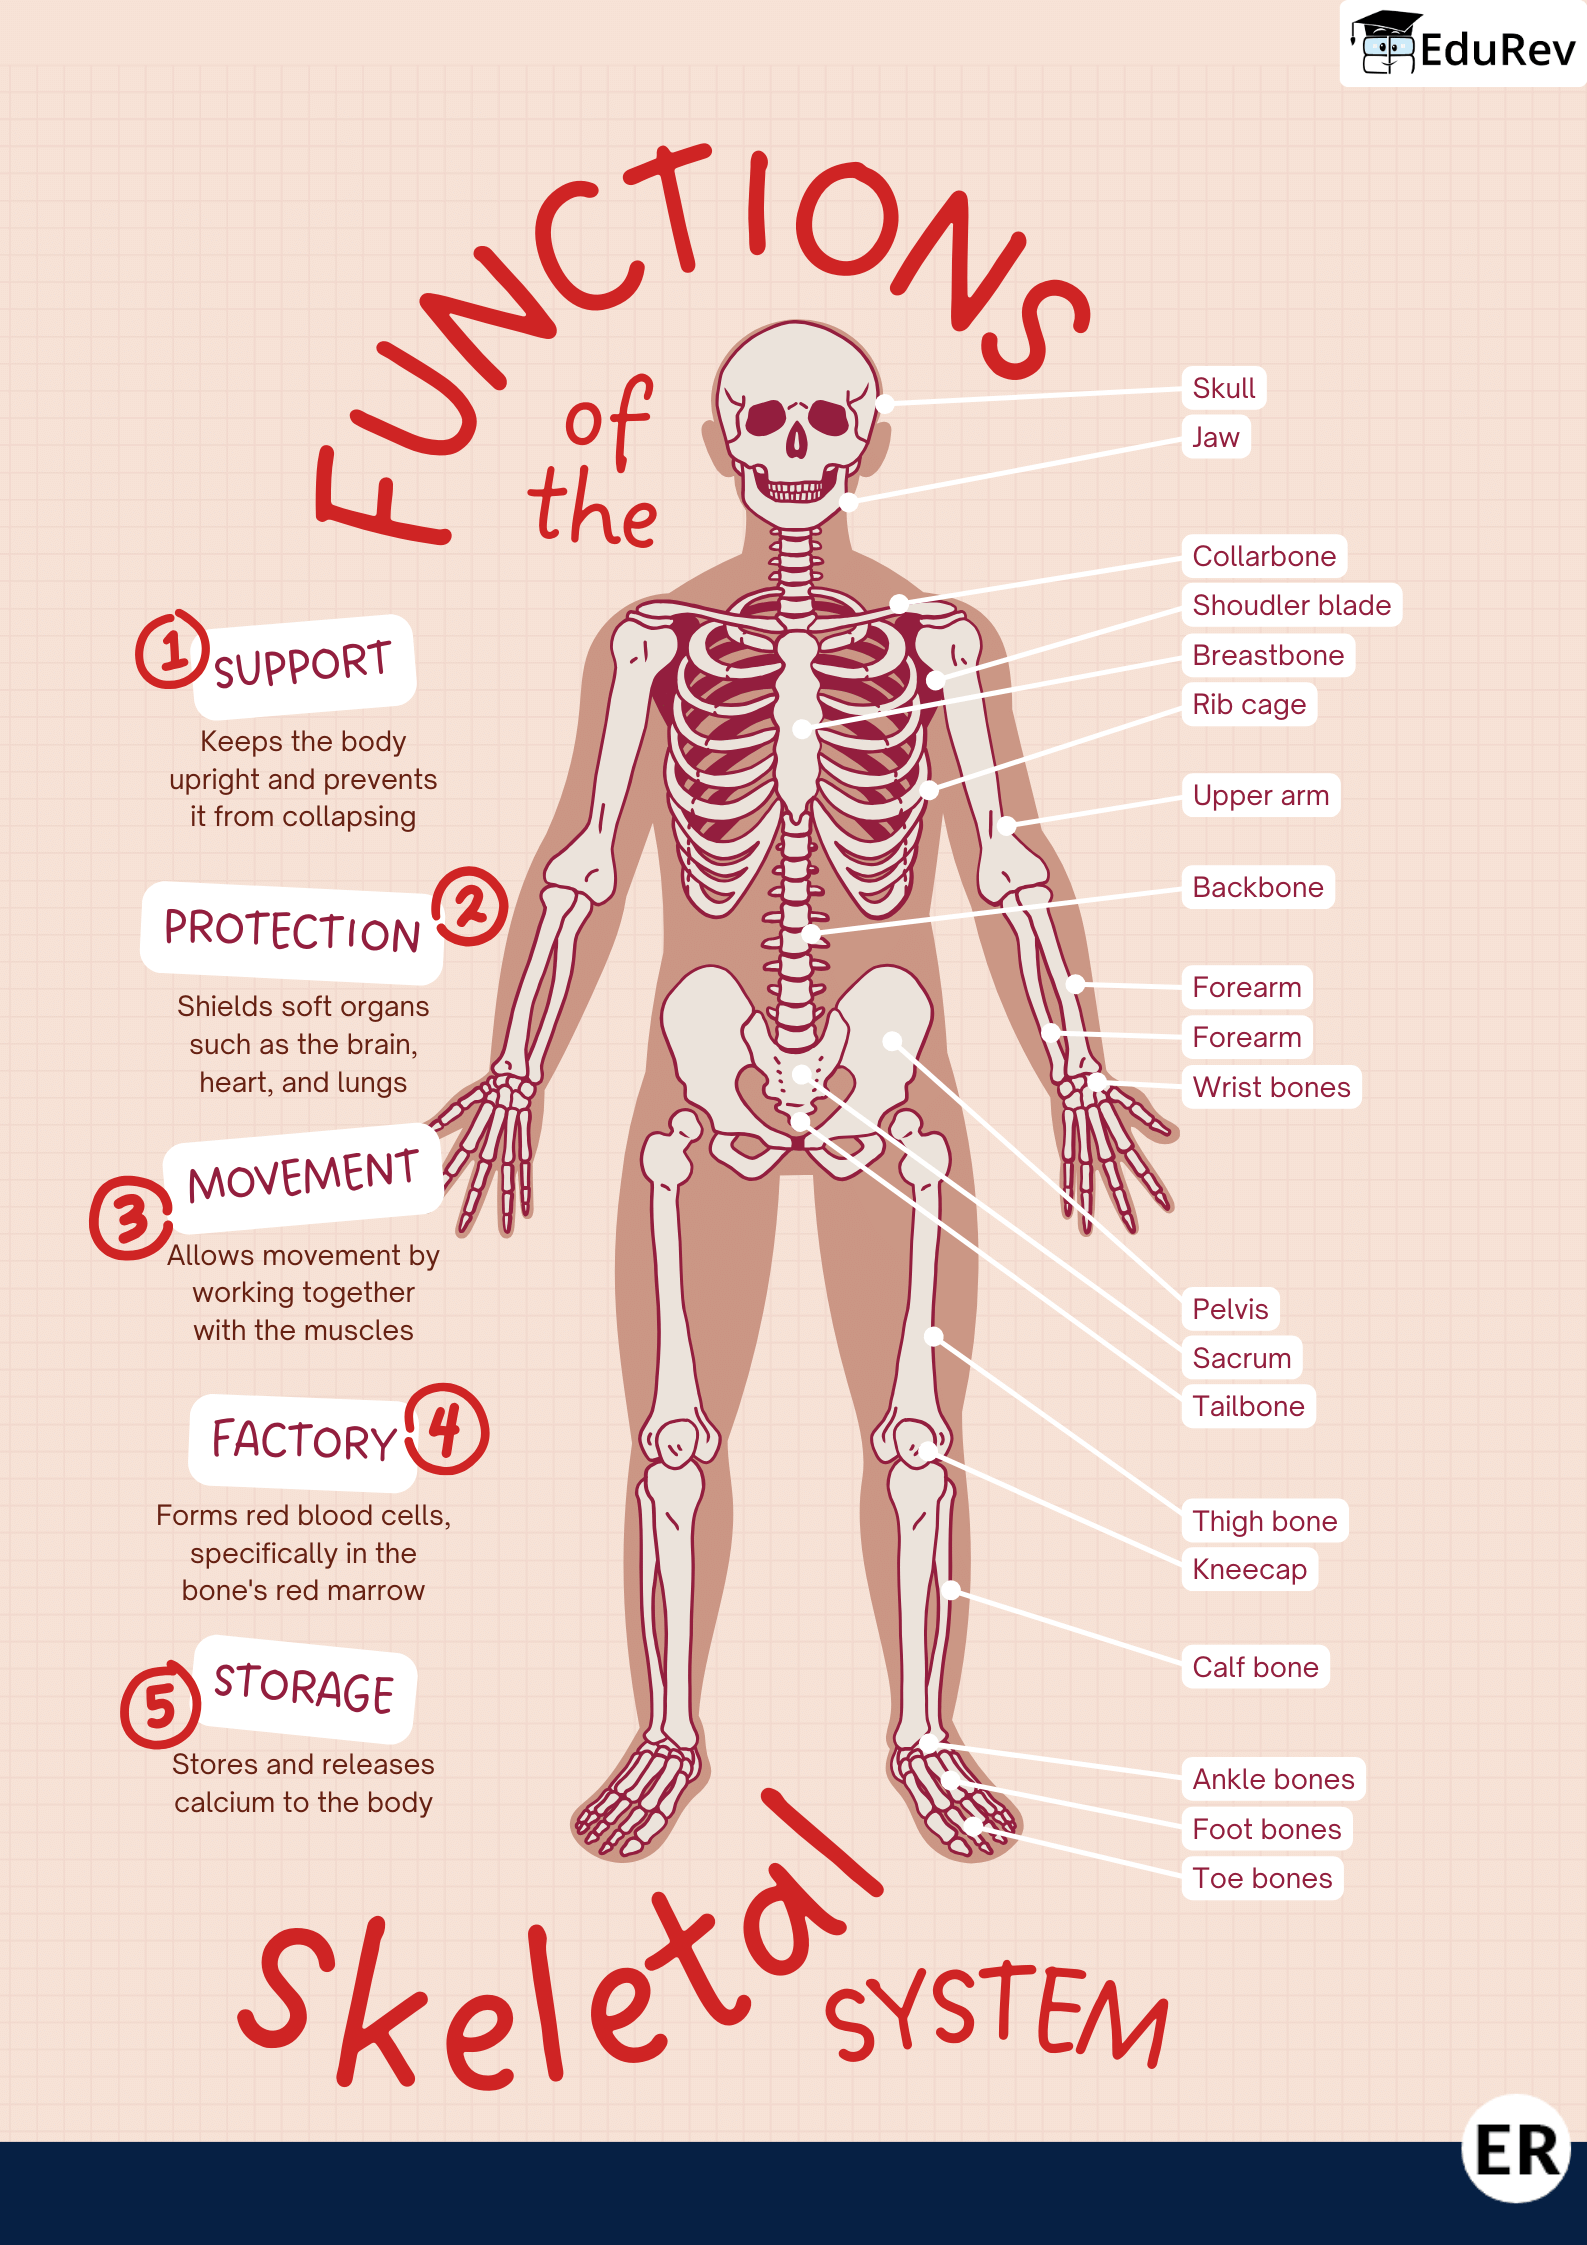
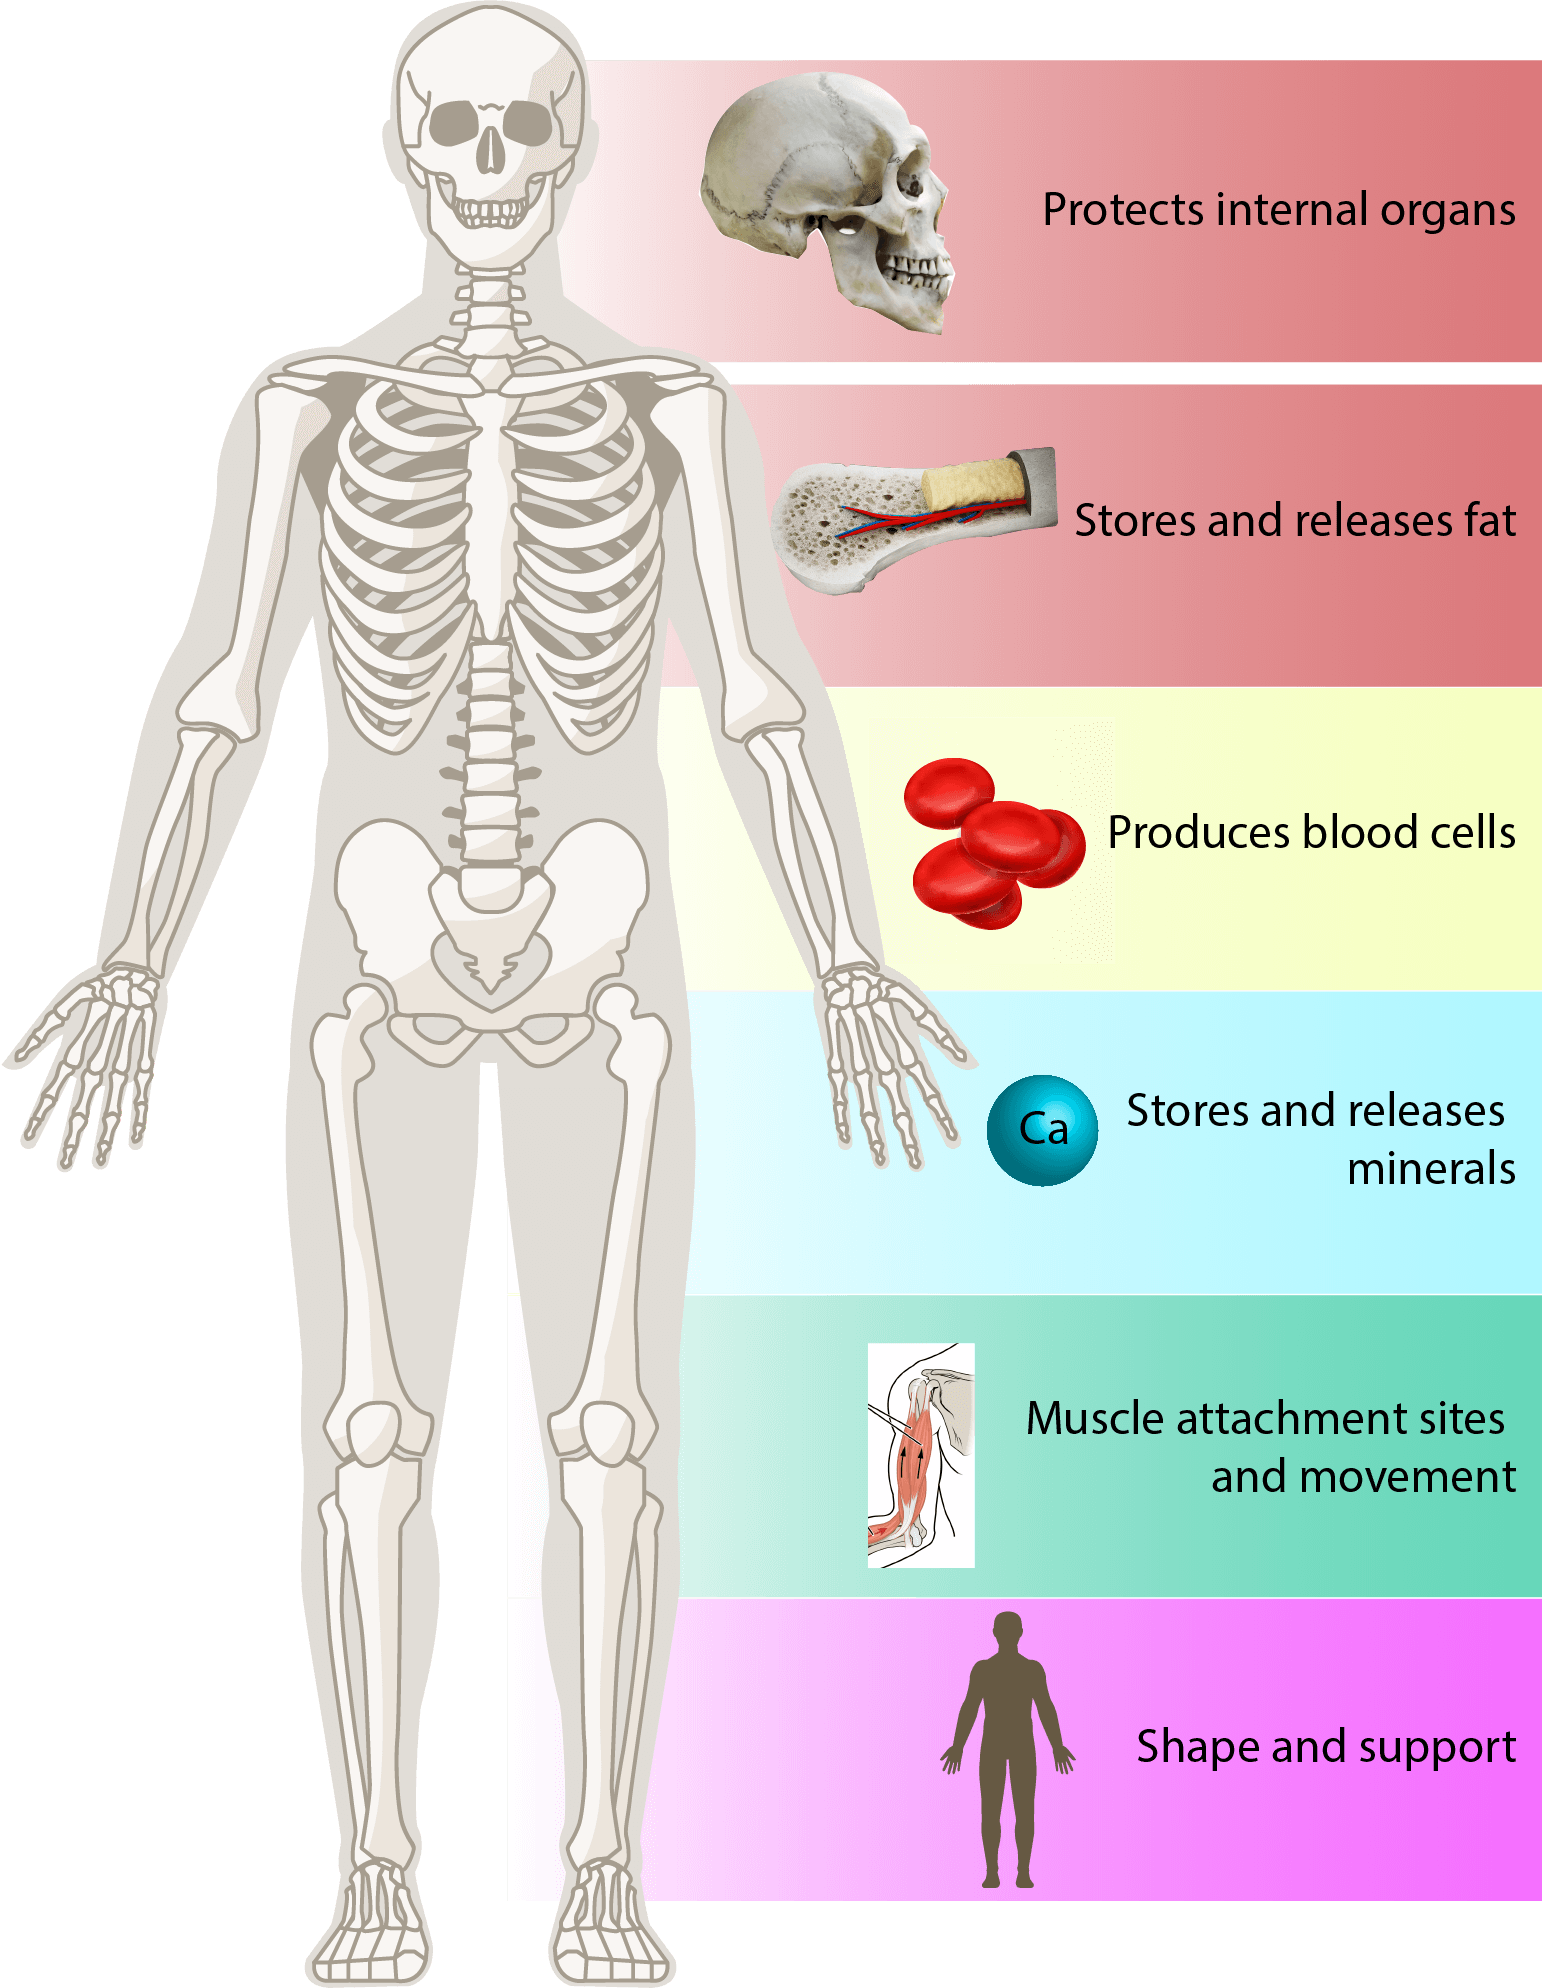
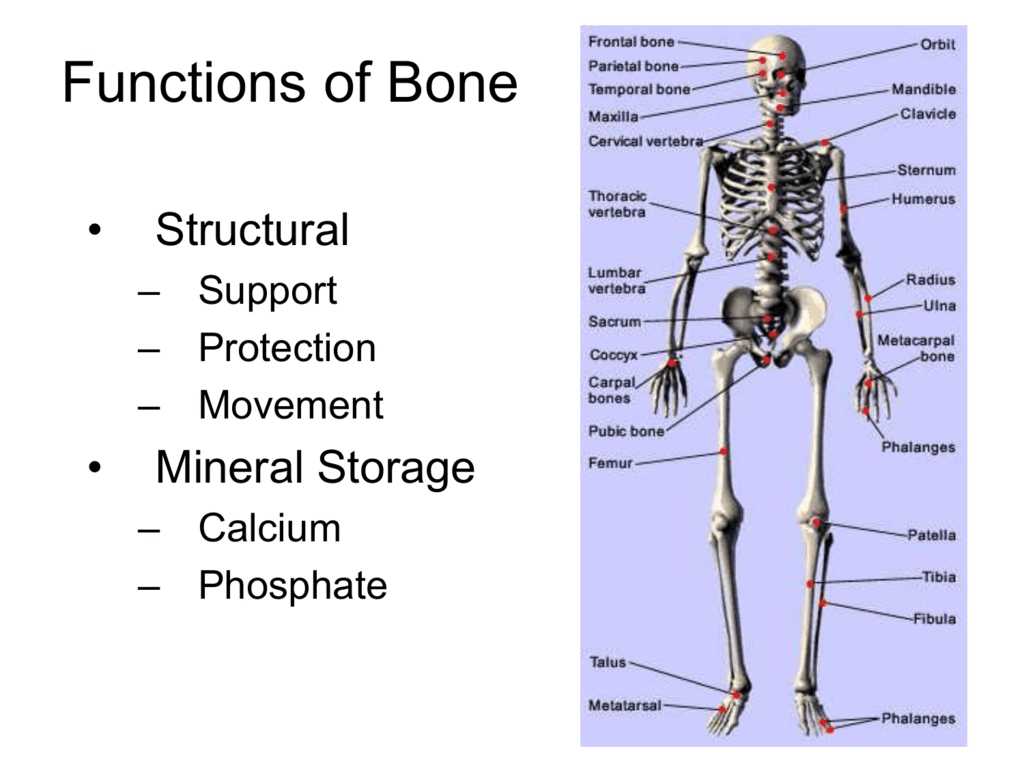
I spent about three years working in orthopedic research before switching to clinical practice, and honestly the stuff I learned in textbooks still didn't prepare me for how complex bone mechanics really are in living patients. You'd be surprised how many people think bones are just structural scaffolding, dead pieces of calcium arranged to keep us upright. The reality is way more complicated than that. Bones serve multiple critical purposes that go far beyond simple support. They store minerals like calcium and phosphorus, produce blood cells in the marrow, protect internal organs, enable movement through leverage points, and act as metabolic organs by releasing growth factors during healing. When you fracture a femur, your body doesn't just patch the break—it remodels the entire mechanical environment around that injury over months. The marrow function alone accounts for roughly 50% of red blood cell production in healthy adults, and that changes dramatically during disease states. I once treated a patient with myelodysplastic syndrome where the bone marrow was essentially producing dysfunctional blood cells. The imaging looked normal, but the cellular machinery inside those cavities was completely off. That's why biopsies matter more than CT scans in certain hematology cases.
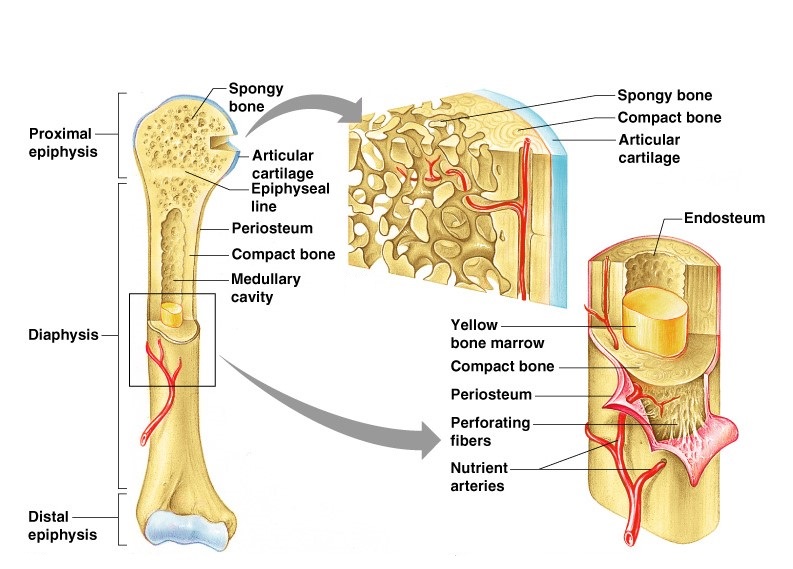
Key structural components include the cortical bone providing rigidity, trabecular bone handling compressive loads, and the periosteum containing progenitor cells essential for repair.How Bone Remodeling Actually Works
Wolff's Law isn't just textbook theory—it's the reason physiotherapists prescribe weight-bearing exercises after hip replacements. Bones adapt to mechanical stress through a process involving osteoblasts building matrix and osteoclasts resorbing it. The signaling pathways involve sclerostin, Wnt proteins, and RANKL that respond to strain within days. I remember dealing with a bedridden elderly patient whose bone density dropped 8% in just six weeks. The standard bisphosphonate protocol didn't reverse it fast enough, so we added teriparatide—a recombinant PTH analog that actually stimulates new bone formation rather than just slowing resorption. The difference in follow-up DEXA scans was noticeable within three months, though the full architectural recovery took nearly a year. The mechanical threshold for microdamage varies significantly between cortical and cancellous bone types. Trabecular bone in the vertebrae can handle cyclic loading better than static compression, which is why spinal fractures often occur from axial loads rather than bending forces in osteoporotic patients. This distinction matters when designing rehabilitation protocols after vertebral compression fractures.
Common Misunderstandings About Bone Health
Calcium supplements alone don't prevent fractures—that's probably the most oversold concept in preventive medicine. Without adequate vitamin D, magnesium, and mechanical loading, supplemental calcium just circulates until it gets excreted or deposits abnormally. I've seen patients taking 2,000 mg of calcium daily with no improvement in bone mineral density, while others who got weight training plus adequate protein showed significant gains with minimal supplementation. The timing of bone loss varies dramatically between men and women due to hormonal differences. Postmenopausal women lose roughly 20% of trabecular bone in the first five years, while men tend to lose cortical bone more gradually starting around age 50. This gender difference explains why fracture patterns differ—vertebral and wrist fractures dominate in women, while hip and pelvic fractures become more common in elderly men. DEXA scans measure BMD but miss architectural deterioration—that's the counter-intuitive part most patients don't understand. You can have a normal T-score but poor trabecular connectivity, which increases fracture risk independent of density measurements. The FRAX calculator attempts to incorporate clinical risk factors beyond BMD, but it still underestimates risk in patients with high fall exposure or previous fragility fractures.
Get the Full Details
When Standard Approaches Fail
Antiresorptive medications like alendronate work for most osteoporosis cases, but about 15% of patients show inadequate response or experience atypical femoral fractures after long-term use. The mechanism involves suppressing bone turnover to below physiological levels, which can impair microdamage repair over decades. I encountered a patient who developed lateral cortical thickening after seven years of bisphosphonate therapy—the classic "elephant leg" sign of suppressed remodeling. The dosing intervals for bisphosphonates vary significantly between oral and intravenous formulations. Oral alendronate requires strict fasting conditions and upright positioning for 30 minutes, while IV zoledronate delivers the full dose in 15 minutes but carries higher acute phase reaction risk. The bioavailability difference is dramatic—roughly 0.6% for oral versus 100% for IV administration, which explains the gastrointestinal side effect profile. Alternative approaches like denosumab offer different mechanisms but introduce their own complications. This RANKL inhibitor provides potent antiresorptive effects but causes rebound vertebral fractures upon discontinuation—a phenomenon I've seen multiple times when patients stop treatment without transition protocols. The half-life difference between these agents affects withdrawal management significantly, with denosumab's longer tissue binding requiring careful monitoring during the drug-free period.
Bone health optimization requires addressing nutrition, mechanical loading, hormonal status, and sleep quality simultaneously. Isolated supplementation shows diminishing returns after initial deficiency correction, while integrated protocols combining resistance training plus adequate protein intake produce additive effects on BMD preservation. The timeline for architectural recovery varies between cortical and trabecular compartments, with cancellous bone showing faster turnover but slower structural adaptation.