What Post-Fusion Rehabilitation Actually Looks Like
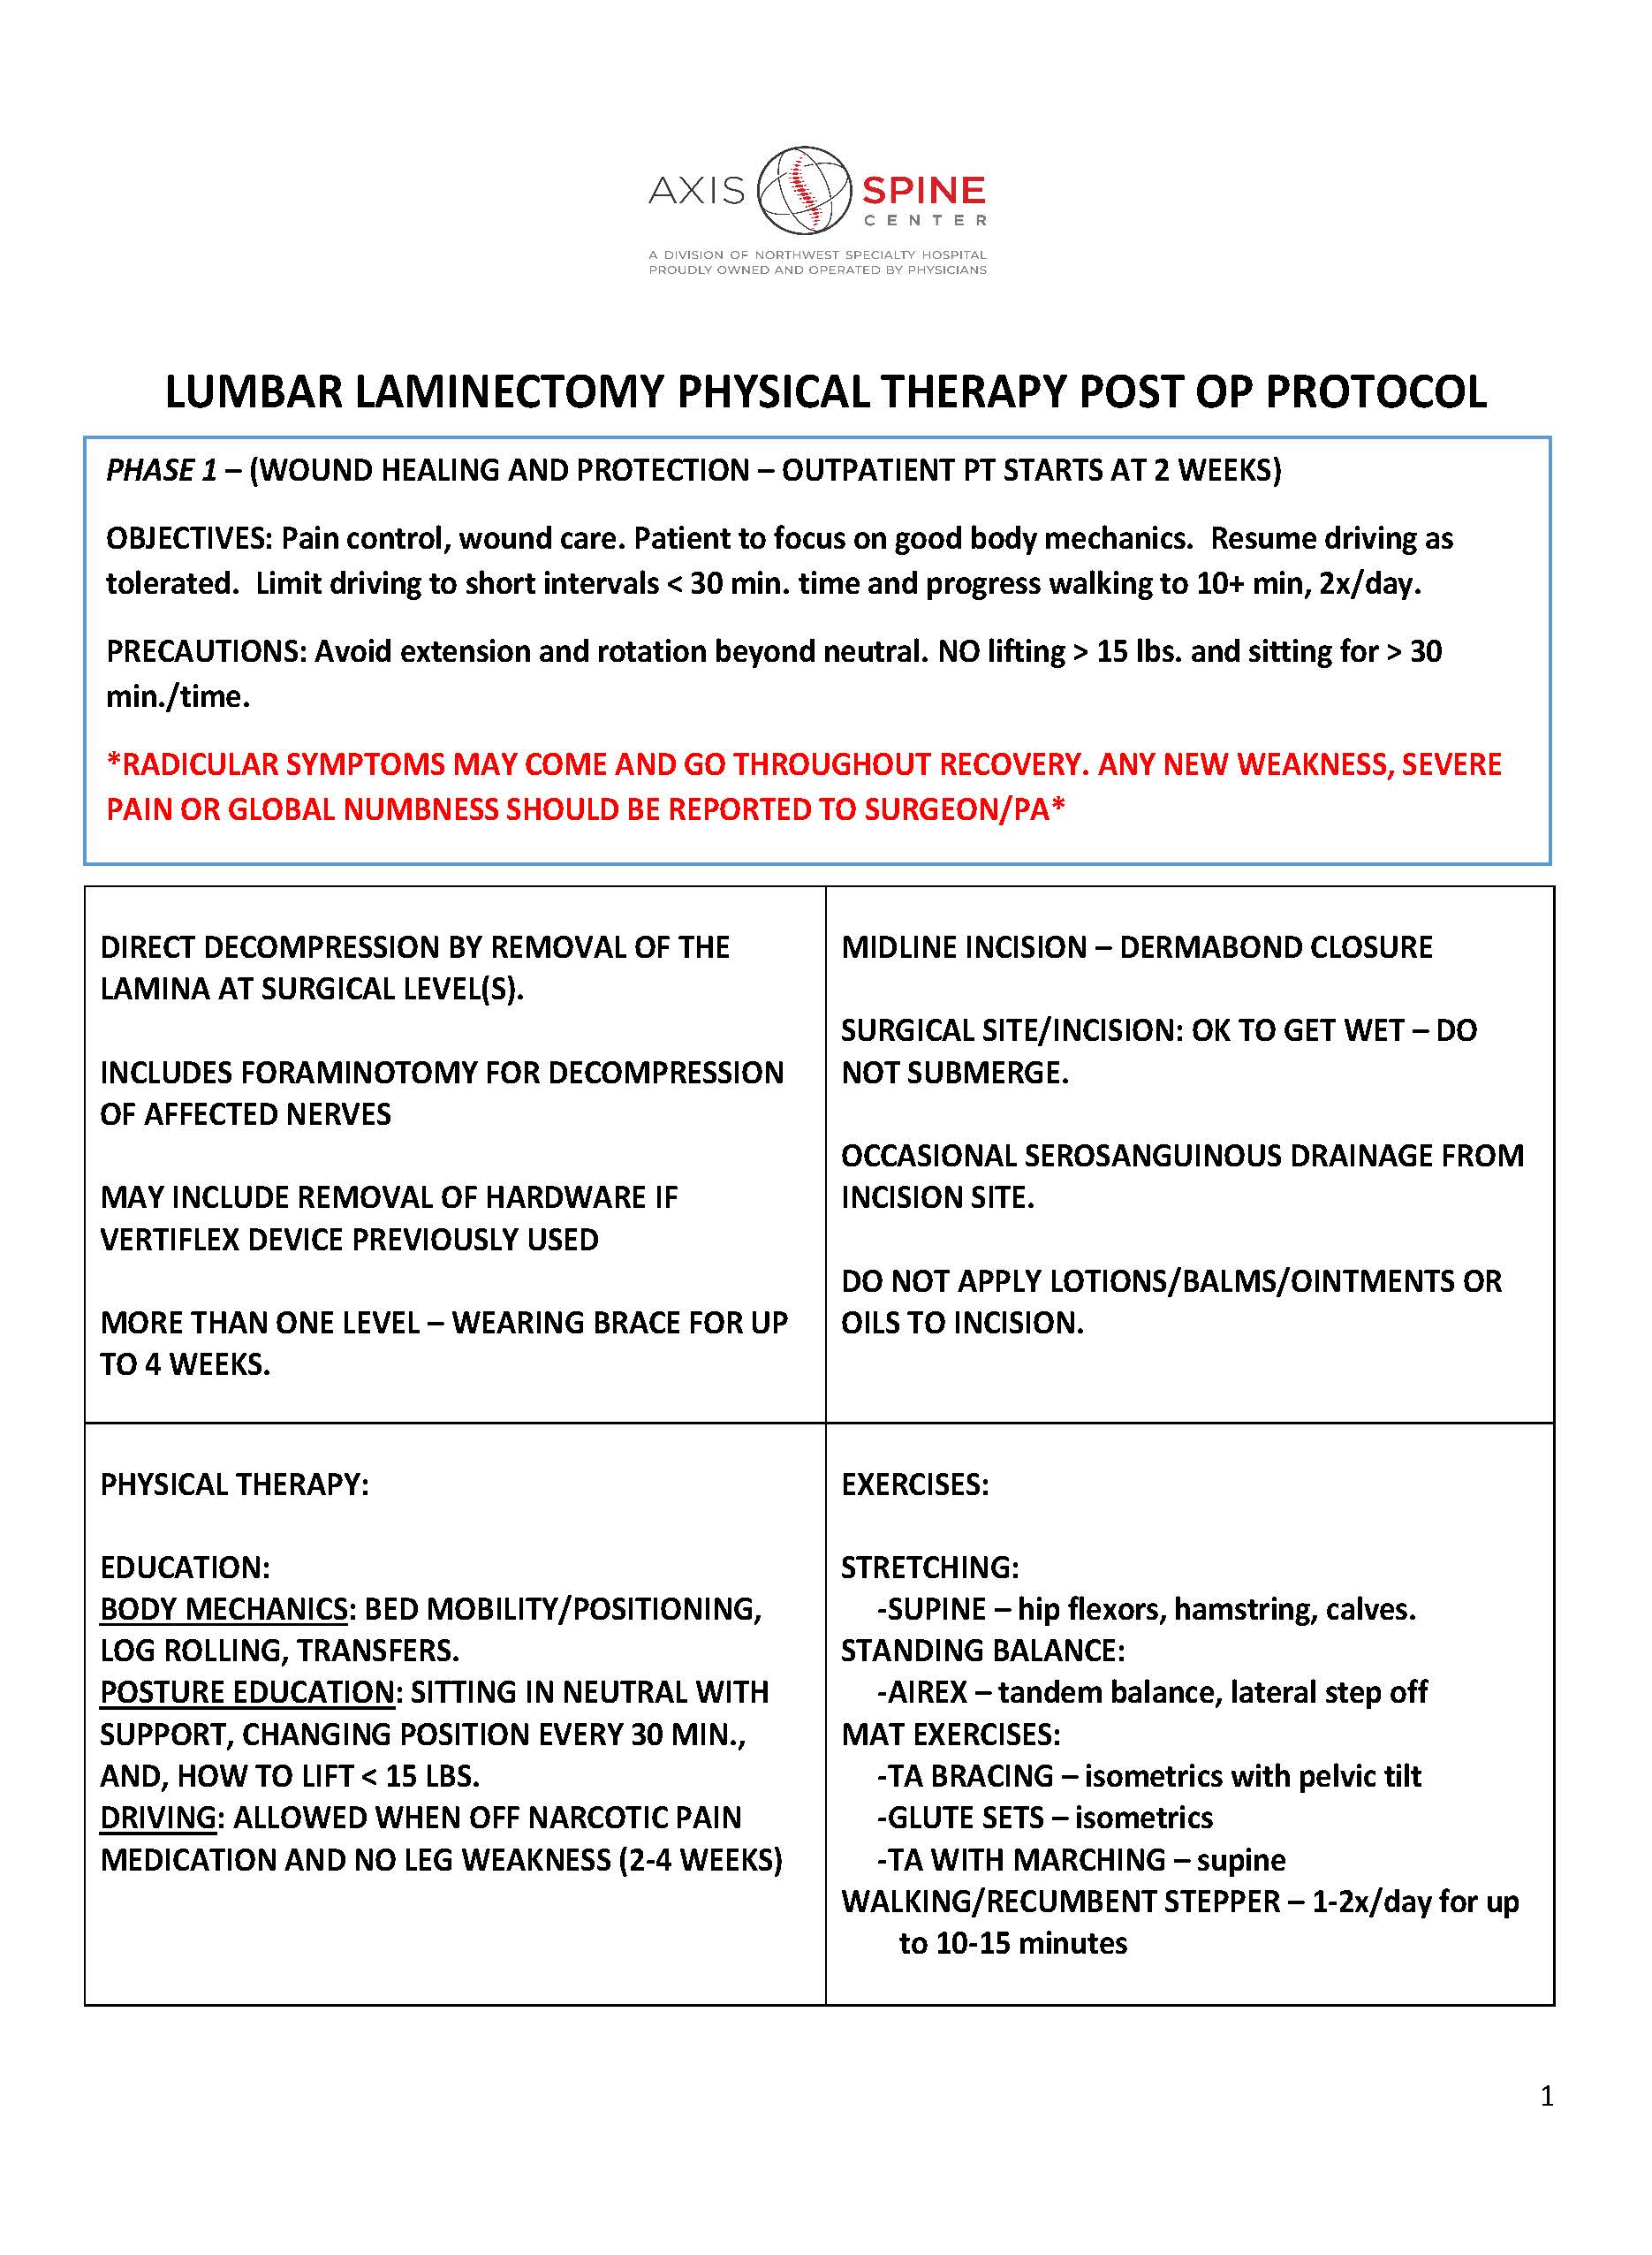
Fusion Protocol Physical Therapy generally refers to structured rehabilitation following spinal fusion surgery or, in some clinics, specific progressive loading programs designed around arthrodesis recovery. The term gets thrown around loosely in clinic marketing, so don't assume every "fusion protocol" document you find is identical. Different surgeons, different instrumentations, different patient profiles — they all shift the protocol. The core idea is straightforward: you protect the fusion mass while you restore function. That means early phases prioritize wound healing and neural mobility, middle phases build anti-gravity control, and later phases reintroduce rotational and shearing forces the spine originally couldn't tolerate. Most published protocols run 12 to 16 weeks for lumbar fusions, sometimes longer for multi-level constructs.
Fusion Protocol Physical Therapy in Practice
Here's how the timeline usually breaks down when I'm working with patients post-lumbar fusion: Weeks 0–2: Walking is the primary intervention. I keep it short and frequent — five to ten minutes, three to four times daily. No bending, no lifting more than five pounds, no twisting. The incision needs to close, the soft tissues need to settle, and the patient needs to prove they can move safely without guarding patterns that will haunt them for months. Most patients underestimate how much nerve irritation is still happening internally even when the incision looks fine. Weeks 2–6: This is where I see the most variation between protocols. Some clinicians introduce gentle core activation immediately. I tend to wait until at least week 3 for lumbar cases, depending on how the surgeon wired things together. Anterior approach? Different story than posterior. TLIF versus PLIF versus posterolateral — the restriction timeline changes. You need to know exactly what procedure was performed before you start prescribing anything past walking.
The first real intervention I introduce is diaphragmatic breathing with pelvic floor coordination. It sounds basic, but patients who've been splinting their core for weeks after surgery have completely lost the ability to separate rib cage movement from abdominal bracing. Until they relearn that separation, every core exercise they attempt is just a compensation pattern. Weeks 6–12: Progressive loading begins. Bird dogs, dead bugs, Pallof presses, side planks with modifications. I avoid loaded spinal flexion and rotation until the surgeon clears it — that's usually around week 8 to 10 for single-level lumbar fusions. Multi-level or thoracolumbar cases? Closer to 12 weeks before I touch those planes of motion. Weeks 12–16+: Return to sport and activity sequencing. This is where most generic protocols fall apart because they're written for average cases. Real patients have asymmetries, pre-existing conditions, and varying bone quality. A 55-year-old female with osteopenia recovers differently than a 35-year-old male with solid bone density. The protocol has to adapt.
Get the Full Details

One Specific Problem I Ran Into
I had a patient post-L5-S1 TLIF who passed all her milestone checks by week 10 — core activation, single-leg balance, progressive loading — but every time she transitioned from sitting to standing, she'd catch on her right L5 derivative. Not pain. Just a mechanical catch, like something was physically impinging during that movement. X-ray didn't show hardware issues. MRI showed expected post-surgical scarring. She wasn't grossly weak anywhere. The problem turned out to be that her right gluteus maximus was firing approximately 400 milliseconds too late during hip extension, which meant her lumbar spine was compensating by extending passively through the facet joint at L5-S1 before her glute could take the load. The fusion itself was fine. Her motor control pattern was the problem. The workaround was simple but non-obvious: I had her practice the sit-to-stand movement with a tempo cue — three seconds down, two-second pause at the bottom, then drive up while consciously squeezing her glute before her hip even started extending. We did 3 sets of 8 reps of that tempo drill before she did a single regular sit-to-stand. After about two weeks of that pre-activation sequence, the catch disappeared completely. The nerve was never the issue — it was timing.
Things Beginners Get Wrong
Most new clinicians treating post-fusion patients go too aggressive on mobility work in the early stages. They see stiffness and want to mobilize it. But after a fusion, stiffness in the adjacent segments isn't always bad — it's often your body's way of protecting the fresh construct. Aggressive stretching at week 4 can absolutely increase inflammation at the fusion site and set recovery back by weeks. Another common mistake is focusing exclusively on the surgical segment. The whole kinetic chain is affected after fusion. Hip flexor tightness from post-surgical positioning limitations will pull on the lumbar spine. Ankle dorsiflexion restrictions from reduced walking volume will alter pelvic positioning. If you only treat the spine, you're treating a symptom. There's also the issue of pain expectation management. Patients coming out of fusion surgery often expect to be pain-free. They're not. The fusion eliminates motion at one segment, but the adjacent levels are now absorbing forces they weren't designed for. Some continued discomfort is normal. Patients who aren't prepared for this either distrust the surgery or overexert themselves trying to "prove" it worked.
When Fusion Protocol Rehabilitation Doesn't Work
This approach has real limitations. Non-union rates, while low for single-level fusions at 3 to 5 percent, are significantly higher in smokers, diabetics, and patients on chronic NSAIDs. No amount of physical therapy will fix a pseudarthrosis — that requires surgical revision. PT can optimize the environment for healing, but it can't guarantee bone growth. Adjacent segment disease is another hard limit. Fusion Protocol Physical Therapy can strengthen supporting musculature and improve movement patterns, but it cannot stop degenerative changes at the segments above and below the fusion. That's a structural biomechanics problem, not a rehabilitation problem. I've seen patients do everything right for a year and still develop significant ASD at L4-L5 after an L5-S1 fusion. Nothing in the protocol addresses that directly. For patients with severe pre-existing osteoporosis, aggressive progressive loading — the cornerstone of any fusion rehab protocol — becomes genuinely risky. You have to modify the entire loading progression or defer it entirely until bone density is addressed medically. Standard protocols don't account for this, and patients with low BMD who follow them verbatim can end up with compression fractures at adjacent levels.

If a patient hasn't cleared basic walking tolerance by week 4, or if they're showing signs of dermatomal radiation that's worsening rather than improving, the protocol should stop and they should go back to their surgeon. Continuing standard rehab in those scenarios usually just delays identifying the actual problem. The best outcomes come from protocols that are written by the surgical team and shared with the rehab provider before the patient leaves the hospital. Generic internet protocols are a starting point at best. The specific instrumentation, approach, and surgeon's preferences should drive every decision after that.