Working With GPCR Ligands in Practice
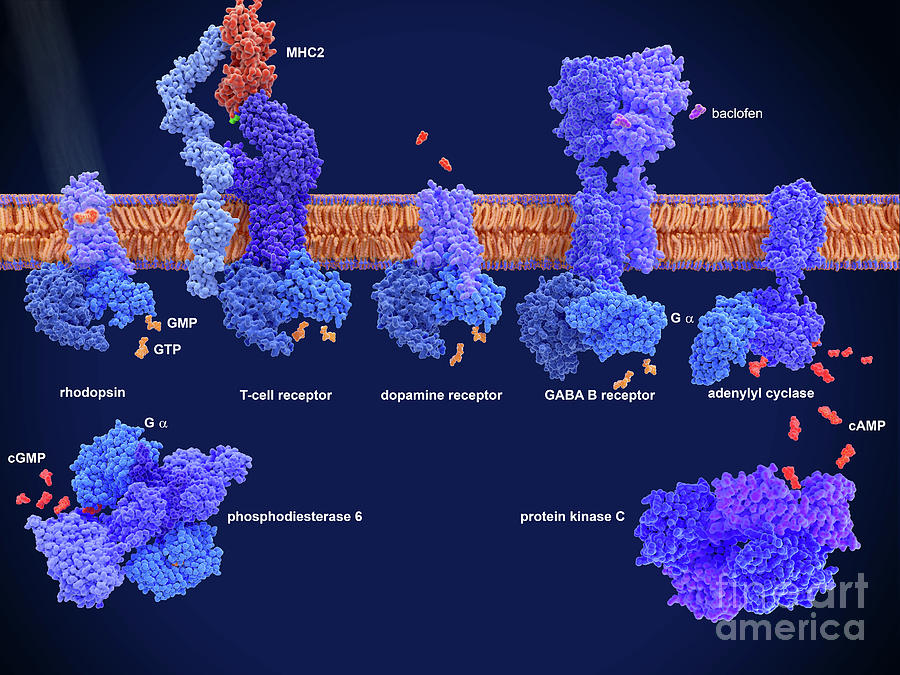
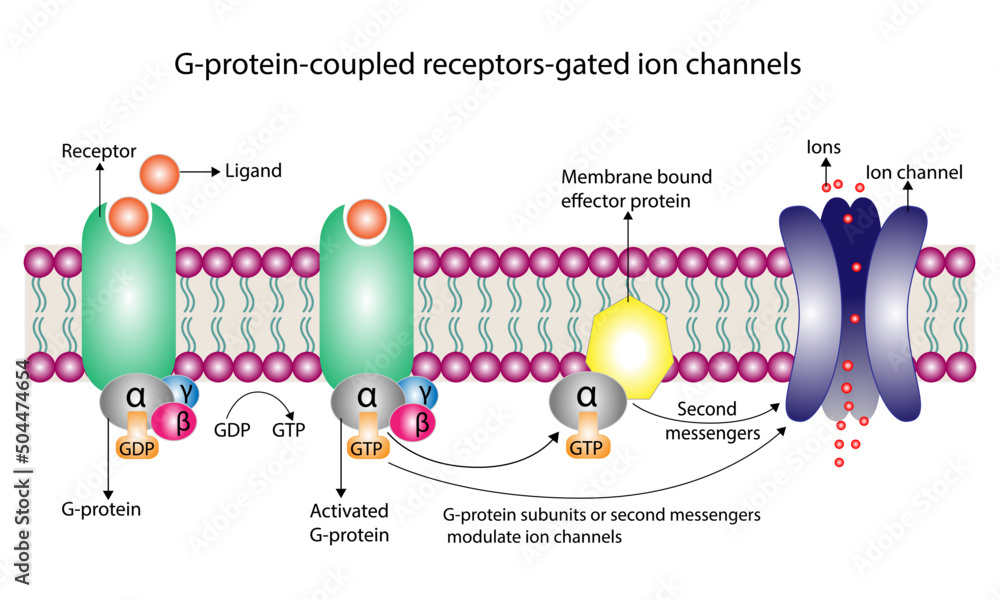
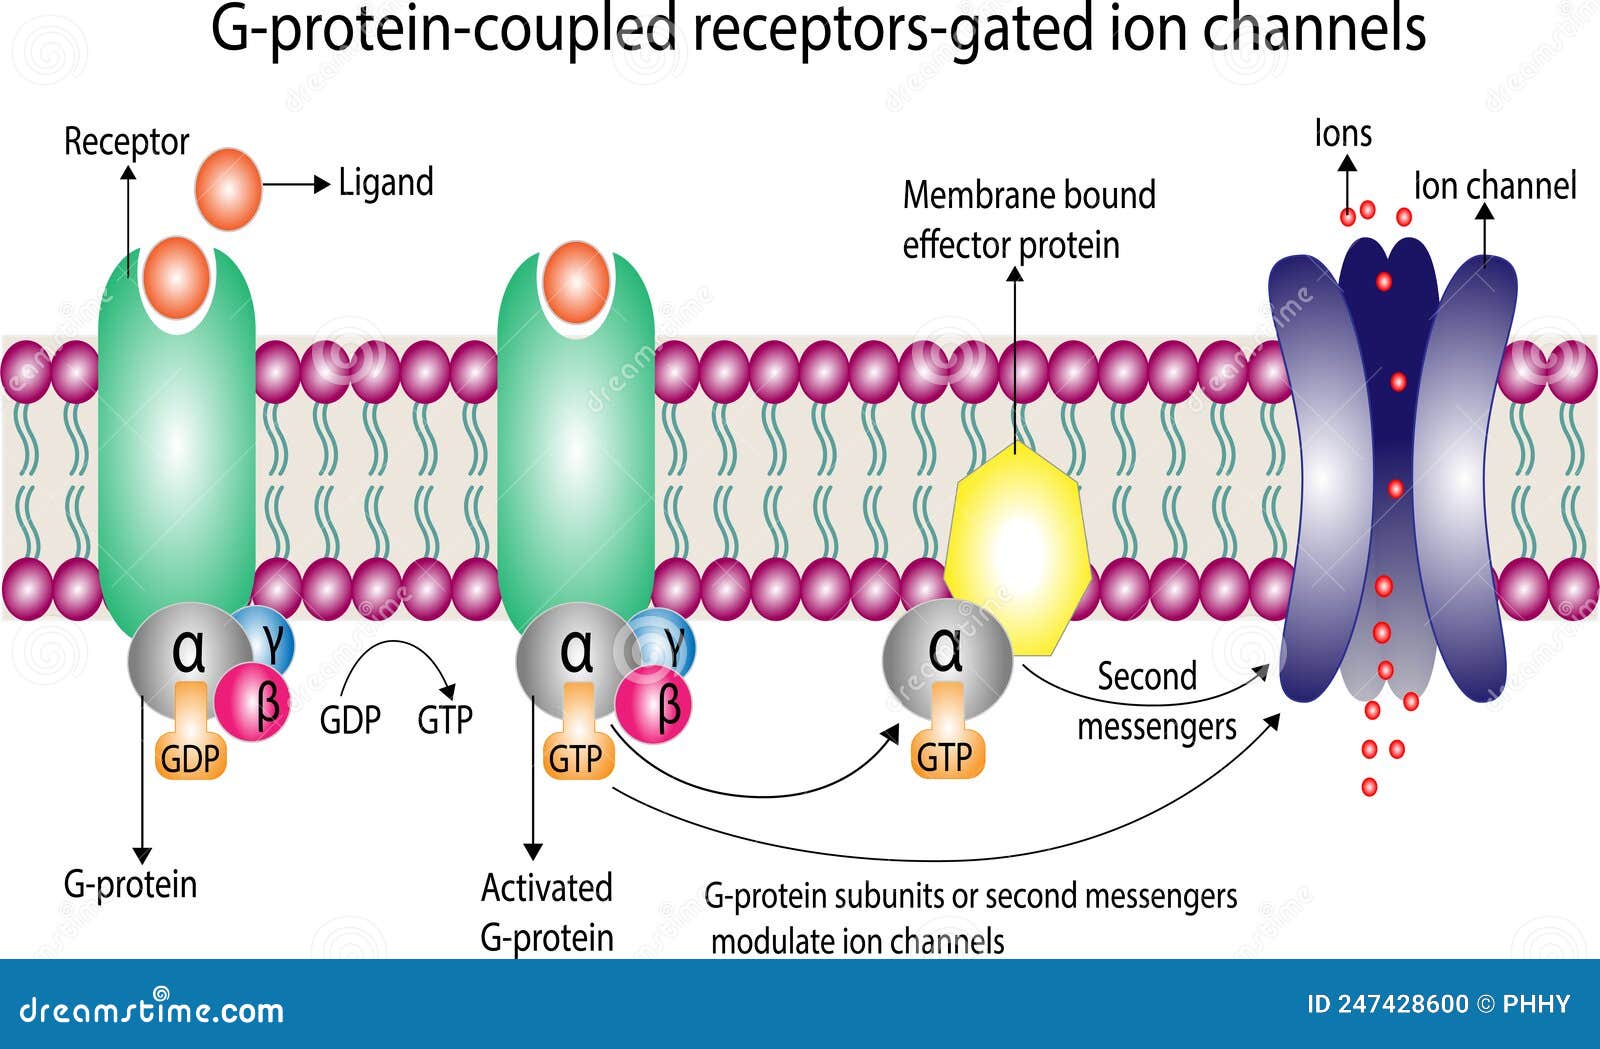
The receptor sits in the membrane with seven transmembrane helices bundled together. When a ligand binds to the extracellular side, the whole thing shifts conformation and the intracellular face presents a binding site for the heterotrimeric G protein. That is the textbook mechanism, but the actual work of dealing with these things involves a lot more than understanding the basic cycle. I have spent years optimizing assay conditions for various GPCR targets, and the complications start appearing almost immediately after you get past the initial binding data. These receptors are encoded by a large gene family spanning roughly 800 genes in the human genome. The orthosteric site can be buried deep within the transmembrane bundle for some ligands, while others bind at the extracellular domain or even at the lipid-facing interface. I learned this the hard way when working on a project involving a metabotropic glutamate receptor variant. The ligand was showing weak apparent affinity in a standard radioligand binding assay, but when I switched to a membrane potential fluorescent indicator assay using a different buffer composition, the EC50 dropped by roughly thirtyfold. The issue was not receptor expression or ligand quality. It was the specific lipid environment around the transmembrane helices affecting the conformational equilibrium. The standard approach involves recombinant expression in HEK293 or CHO cells, purification via tag-based chromatography, and functional readouts through calcium mobilization, cAMP accumulation, or beta-arrestin recruitment. Each of these methods has specific failure modes that are not well documented in the supplier protocols. I usually prepare test membranes first and quantify receptor density through saturation binding before committing to a full functional screen. If you skip this step, you will waste days optimizing an assay for a receptor that is expressed at half the concentration you estimated, and the dose-response curves will look noisy for reasons that are impossible to diagnose without the binding data.
Assay Selection and the Hidden Variables
Choosing the right detection method matters more than most people admit. A calcium flux assay might show robust signaling for one GPCR while the same receptor shows almost nothing in a cAMP assay, even though both pathways are genuinely coupled in vivo. This happens because the expression system, the membrane lipid composition, and the endogenous downstream machinery all interact in unpredictable ways. I had a client once who was frustrated that their Gi-coupled receptor was only producing a weak cAMP inhibition signal despite strong calcium responses. We swapped to a BRET-based GTP gamma S binding assay and found that the receptor was functioning normally through the intended pathway. The problem was specific to the cAMP readout in that particular cell line. Ligand bias is another factor that gets glossed over in most introductory materials. A compound might look like a pure agonist in a calcium assay but act as a partial agonist or even an antagonist in a beta-arrestin recruitment context. This is not a technical artifact. It reflects genuine biological reality where different conformational states of the receptor preferentially couple to different downstream effectors. I have seen drug candidates advance through early development based on a single functional readout only to fail later when the alternative pathway revealed different activity profiles. Testing at least two distinct signaling endpoints during lead characterization is now standard practice in most pharmaceutical groups, though smaller labs sometimes skip this due to cost or throughput constraints.
Common Pitfalls That Waste Time
Membrane prep quality is critical and easy to mess up. When I lyse cells for binding assays, I keep everything cold, use a Dounce homogenizer with three passes rather than sonication to avoid shearing the membrane proteins, and centrifuge at 40,000 times g for twenty minutes to pellet the crude membrane fraction. The supernatant from that spin contains soluble proteins and debris that can interfere with downstream assays. Some protocols recommend a second high-speed centrifugation step at 100,000 times g to obtain a purified membrane fraction, but this is usually unnecessary unless you are doing very sensitive work. The extra handling time typically introduces more variability than it removes. Receptor stability during storage is another area where people make mistakes. Most GPCRs lose activity within hours to days after solubilization, even in the presence of detergents. I keep aliquots at minus eighty degrees Celsius and avoid more than two freeze-thaw cycles. The activity loss is not linear. You might see twenty percent decline after the first thaw, then another twenty percent after the second, but the third cycle often causes catastrophic failure. I learned this experimentally with a dopamine receptor preparation where the activity curve looked acceptable through multiple titrations before suddenly dropping off completely. The detergent concentration also matters significantly. DDM is milder than OG or LDAO for most membrane proteins, but the optimal choice depends heavily on the specific receptor you are working with. Testing two or three detergents during initial characterization usually takes less than a week and prevents months of troubleshooting later. Nonspecific binding in radioligand assays is another persistent problem. I typically determine nonspecific binding using a five hundred to thousand-fold excess of unlabeled competitor ligand. If the nonspecific signal exceeds twenty percent of total binding, the data becomes unreliable and the assay needs reoptimization. This can happen due to hydrophobic interactions with the membrane lipids, stickiness to the filtration apparatus, or aggregation of the radioligand itself. Adding a small amount of fatty acid-free BSA to the assay buffer often helps reduce hydrophobic nonspecific binding without affecting specific receptor interactions.
Get the Full Details
Data Interpretation Beyond Basic Curves
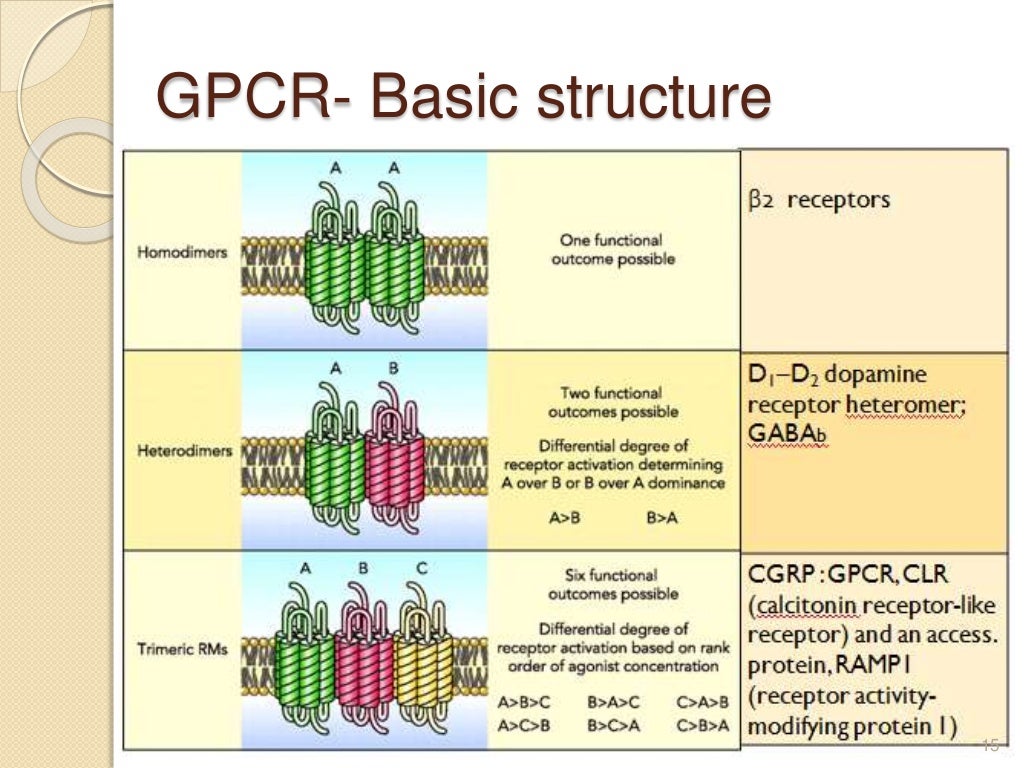
Curve fitting is where most problems emerge. A standard four-parameter logistic equation works for clean data, but real GPCR experiments rarely produce clean data. You will encounter shoulders on the curve, flattened responses at high concentrations, or biphasic patterns that suggest multiple binding sites or receptor oligomerization. I fit the data with both the standard model and alternative equations, then use an F-test to determine whether the more complex model provides a statistically significant improvement. If it does not, I stick with the simpler model even if the residuals look slightly worse. Overfitting is a real risk with GPCR dose-response data, especially when you have fewer than eight concentration points per experiment. Operational models of agonism provide a more rigorous framework than simple EC50 values. The Black-Leff operational model accounts for receptor density and efficiency of coupling, which means you can compare potencies across different expression systems. This matters because the same agonist might show a fiftyfold difference in apparent potency between a low-expression cell line and a high-expression one. The intrinsic efficacy parameter from the operational model is independent of receptor density, making it a more meaningful comparison metric. I use this approach whenever I need to compare lead compounds from different medicinal chemistry teams working in different assay systems. Allosteric modulators complicate data interpretation further. Positive allosteric modulators shift the orthosteric ligand curve to the left without necessarily producing a response on their own. Negative allosteric modulators do the opposite. Detecting allosteric behavior requires a specific experimental design where you test the orthosteric ligand at multiple fixed concentrations of the modulator and look for parallel shifts in the curve. A simple IC50 determination in the presence of a suspected modulator can give misleading results if you do not account for the change in apparent affinity versus the change in maximum response. I have seen colleagues misinterpret allosteric modulation as competitive antagonism because they only measured endpoint responses without generating full concentration-response curves.
When GPCR Assays Fail Completely
Some receptors refuse to express well in standard heterologous systems. I worked with a chemokine receptor that showed negligible surface expression in HEK293 cells regardless of the construct design, promoter strength, or tags used. Switching to a stabilizing mutation in the third intracellular loop, which is a well-documented strategy for certain GPCR families, finally produced functional surface expression. The mutation was not adjacent to any known orthosteric binding site, but it locked the receptor in a conformation compatible with proper trafficking through the secretory pathway. This kind of receptor engineering is necessary for roughly ten to fifteen percent of GPCR targets and should be anticipated during early project planning. Lipid requirements are another source of unexpected failures. Some GPCRs require specific phospholipids or cholesterol for proper function, and standard assay buffers may not supply adequate amounts. I routinely include five to ten micrograms per milliliter of cholesterol hemisuccinate or cholesteryl hemisuccinate in membrane prep buffers when working with receptors known to be cholesterol-dependent. The effect can be dramatic. A serotonin receptor I was studying showed almost no ligand binding in standard buffer but recovered full activity within thirty minutes of adding the lipid supplement. The receptor was not denatured. It was simply missing a structural component required for the binding pocket to maintain its proper geometry. Agonist-induced desensitization can also confound experiments if you do not account for it. Prolonged exposure to high agonist concentrations leads to phosphorylation by GRKs, beta-arrestin recruitment, and internalization. This is a normal physiological process but it ruins time-course experiments if you are not careful. I keep agonist exposure times under five minutes for acute signaling assays and use cold temperatures to slow internalization when measuring early kinetic events. For chronically stimulated systems, I pre-treat cells with the agonist for the desired duration, then wash extensively before adding the detection reagent. The wash step is critical. Residual agonist in the detection buffer will continue driving signaling during your measurement window and produce artificially elevated responses.
Practical Workflow Recommendations
A typical characterization project follows this sequence: confirm expression and surface localization, determine binding parameters with a radioligand or fluorescent ligand, establish functional signaling through at least two pathways, test for agonist bias across those pathways, then optimize lead compounds against the preferred pharmacological profile. Rushing through any of these steps usually creates problems downstream. I have seen projects where teams moved directly from expression cloning to in vivo efficacy studies without characterizing the basic pharmacology first. When the compounds failed in animals, they had no idea whether the issue was poor pharmacokinetics, wrong dosing, or fundamental lack of efficacy against the target in the relevant tissue. The investment in thorough in vitro characterization typically pays for itself within weeks. A complete GPCR pharmacology package including binding, functional signaling, and bias assessment usually takes two to three weeks with a small team. Skipping it to save time often results in three to six months of wasted effort chasing artifacts or misinterpreted data later. The cost of reagents and cell culture is minimal compared to the cost of late-stage clinical failures caused by inadequate early characterization. For anyone starting out with GPCR work, I recommend becoming proficient in at least one binding assay and one functional assay before expanding to more complex measurements. The underlying techniques are transferable across receptor families, and building a solid foundation in the basics prevents many common errors. Membrane preparation, saturation binding, competition binding, calcium imaging, and cAMP detection are the core skills. Everything else builds on these fundamentals. I spend roughly two weeks training new team members on these techniques before letting them run independent projects, and that time investment consistently reduces the error rate and improves data quality throughout the group.