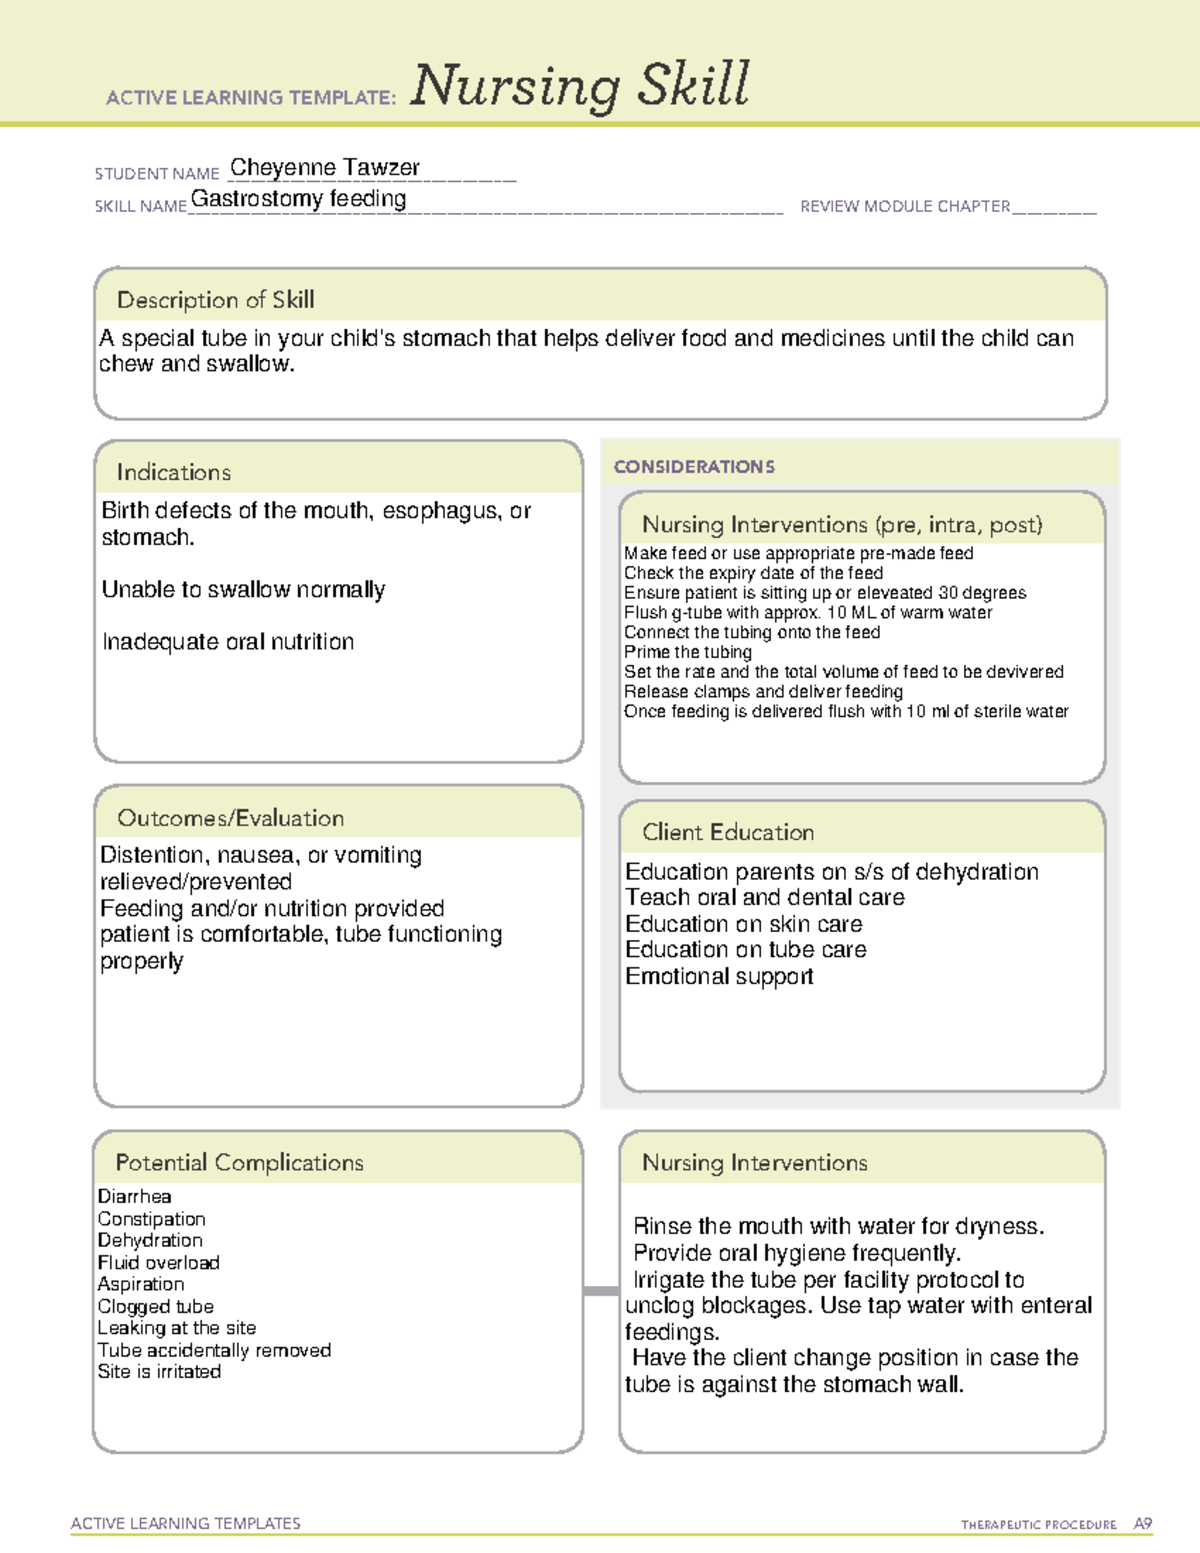
The Real Way I Do G Tube Feeding Checks Before a Shift
Most people learn G Tube Nursing Assessment from a textbook that says check placement, check residuals, check the site. That's technically correct but doesn't tell you what happens at 2am when the pump alarm is screaming and the family is asking why the stomach looks bigger than it did at dinner. I've been placing and managing G-tubes long enough to know that the standard checklist misses several things that actually matter in clinical practice. What follows is my approach, not someone's lecture notes.
G Tube Nursing Assessment: What Actually Matters at the Stoma Site
The stoma site is where most complications show up first. Redness, drainage, granulation tissue. You check these every shift, but here's what the guides don't emphasize enough: the skin underneath the bumper or disk is often the problem area, not the visible ring around it. I learned this after missing a stage two pressure injury under a low-profile device on a patient who had been repositioned improperly for three days straight. The workaround was simple but not obvious. I started lifting the device slightly during each assessment, just enough to see the peristomal skin that gets trapped between the disk and the abdominal wall. It takes four seconds. It caught that pressure injury that would have become a full-thickness wound within another week. Granulation tissue is another thing nobody warns you about early enough. A little bit is normal, especially in the first few months after placement. But if you see tissue that bleeds easily, looks beefy red, or is growing above the skin line, that's your signal. I use silver nitrate sticks for minor granulation. One application, hold for ten seconds, and it shrinks right back down. The nursing assistant who trained me taught me this trick and I've used it on probably fifty patients over the years.
Residual Checks That Actually Predict Problems
Residual volume is the most contested part of G-tube management. Some protocols say anything under 500 milliliters is fine. Others are much more conservative. The truth is that residual volume alone tells you very little without context. A 200-milliliter residual in a patient who's on a continuous feeding at 60 milliliters per hour means something different than a 200-milliliter residual in someone who just had their bolus complete twenty minutes ago. I assess residual by tracking trends, not single numbers. If the residual climbs by 100 milliliters or more from one check to the next on the same patient, that's a signal regardless of the absolute number. I document it, I reassess in an hour, and I communicate with the provider if it doesn't resolve. That pattern-based approach caught early gastric dysrhythmia in a patient who otherwise looked stable. Here's the counter-intuitive part that will get you in trouble if you follow rigid protocols: retching or vomiting does not always mean the residual is high. I had a patient whose residuals were consistently under 100 milliliters but who vomited after every feeding attempt. Turns out the tube tip was migrated and resting against the pylorus, triggering a nausea response that looked like intolerance but was actually mechanical irritation. Aspiration of the residual showed nothing wrong. The fix was a simple positioning change and sometimes repositioning the tube, which the radiology team confirmed on X-ray.
Get the Full Details
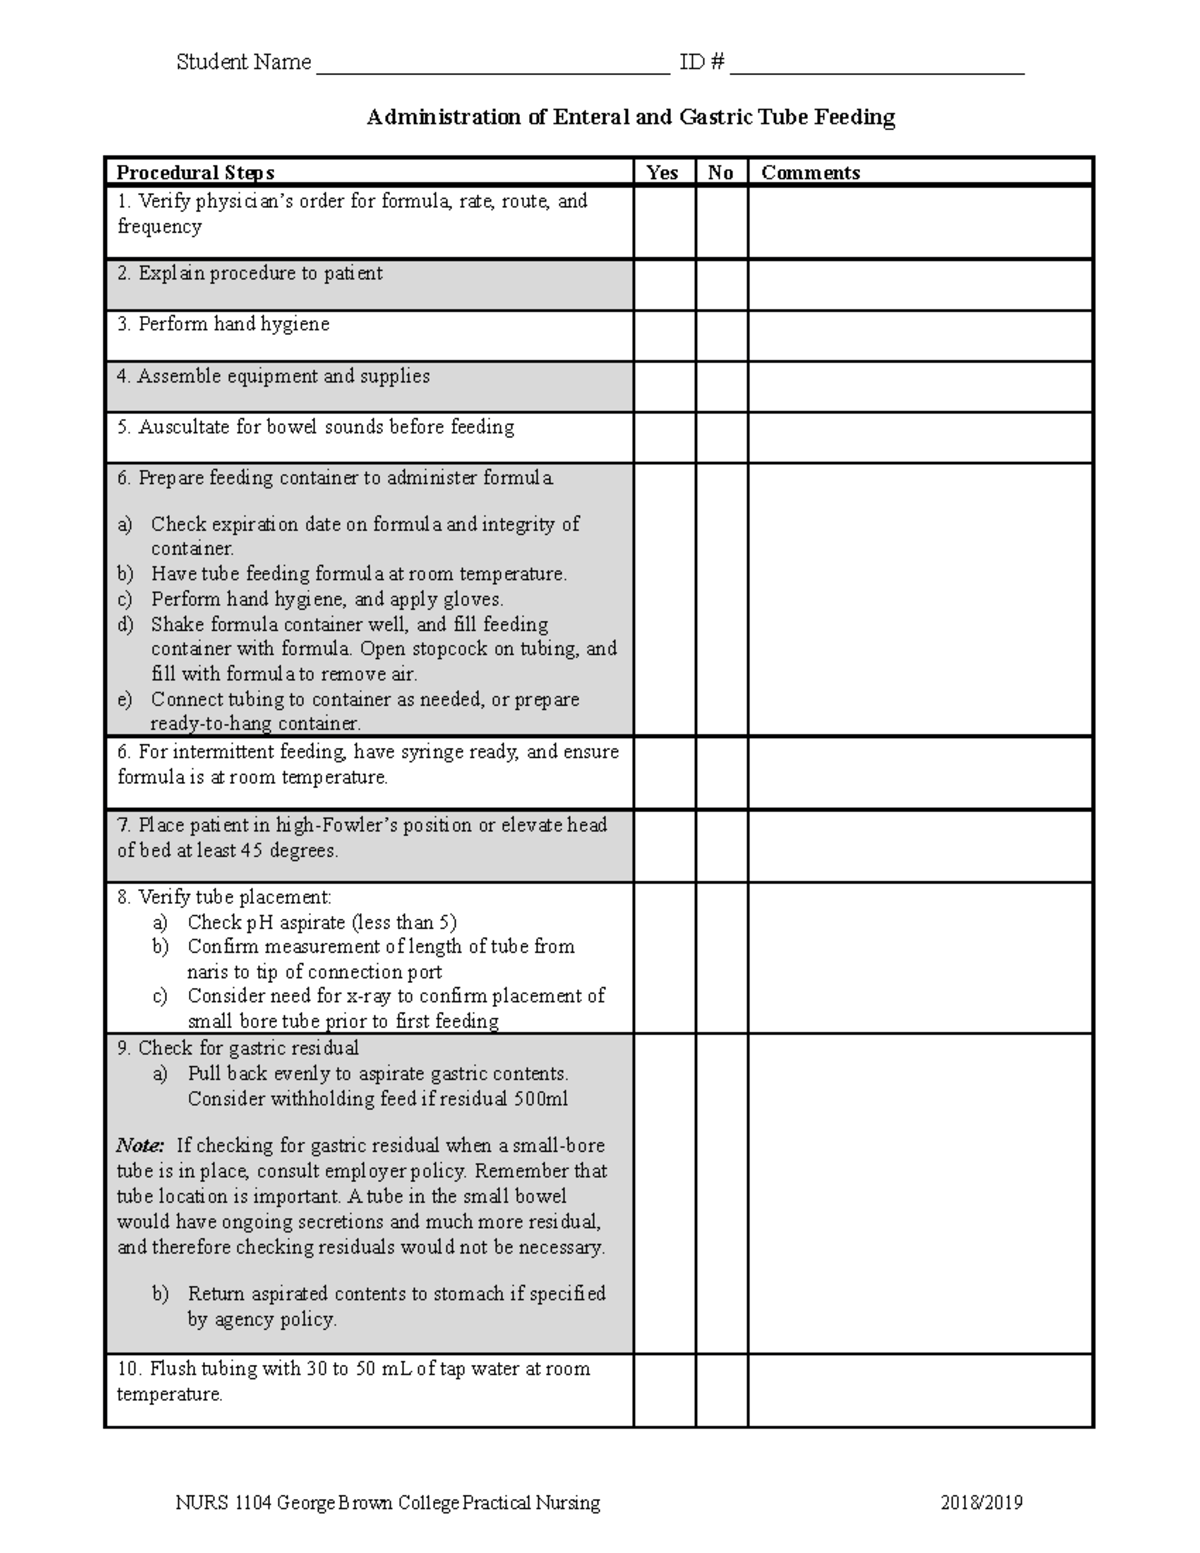
Don't discard the aspirate back into the stomach blindly if the residual is bloody, green, or frankly suspicious. I've seen bile-stained aspirate ignored because the protocol said "reinstill regardless." It wasn't bile. It was upper GI bleeding and the patient ended up in the ICU. Trust your eyes before you trust the protocol.
Site Care and Device Maintenance Most Nurses Rush Through
Rotation of the tube at the stoma site is standard practice and should happen every few days once the tract is mature, usually after four to six weeks. But the technique matters. You rotate a fraction at a time. You don't yank it out and force it back in like you're trying to win a tug-of-war. The tract is a epithelialized tunnel that will partially close within minutes if you neglect it, and you don't want to be reinserting on a fresh tract in the emergency department at midnight. I keep a supply of water-soluble lubricant at the bedside specifically for this. Alcohol wipes or hydrogen peroxide damage the stoma tissue over time. Saline or plain water for cleaning is plenty. I rotate the tube clockwise and countercounterclockwise, about a quarter turn each direction, until it moves freely. That's it. Twenty seconds of work that prevents an hour of problem-solving later. For balloon retention tubes, the balloon volume should never exceed what the manufacturer specifies. Overinflating to prevent migration is a common mistake I see repeatedly. It causes pressure necrosis at the pylorus and can create a ball-valve effect that blocks feeding. I check balloon volume every time I replace the water, which is every seven to fourteen days depending on the device. A syringe and some patience solve this. If the balloon won't hold volume, replace the tube. Don't try to top it off and hope for the best.
Documentation and Communication Gaps in G Tube Nursing Assessment
The assessment itself is only half the job. What you document and what you hand off determines whether the next nurse catches a problem or misses it entirely. I used to chart residuals as a single number and call it a day. That changed after I realized I was looking at yesterday's 150 milliliters while the current one was 450, because the baseline had shifted upward over twelve hours and I didn't notice. Now I document residuals with a running trend. Baseline, current value, change from prior, and any interventions taken. When I hand off, I state the trend, not just the number. This has caught more issues than any formal assessment tool I've used. The other gap is the family or caregiver communication piece. Parents and home caregivers often notice changes before the nurse does because they're the ones seeing the patient between shifts. I ask specific questions: has the feeding tolerance changed, is there new discomfort around the site, has the output pattern shifted. Open-ended questions get open-ended answers. "Everything okay?" gets a nod and a dismissal ninety percent of the time.
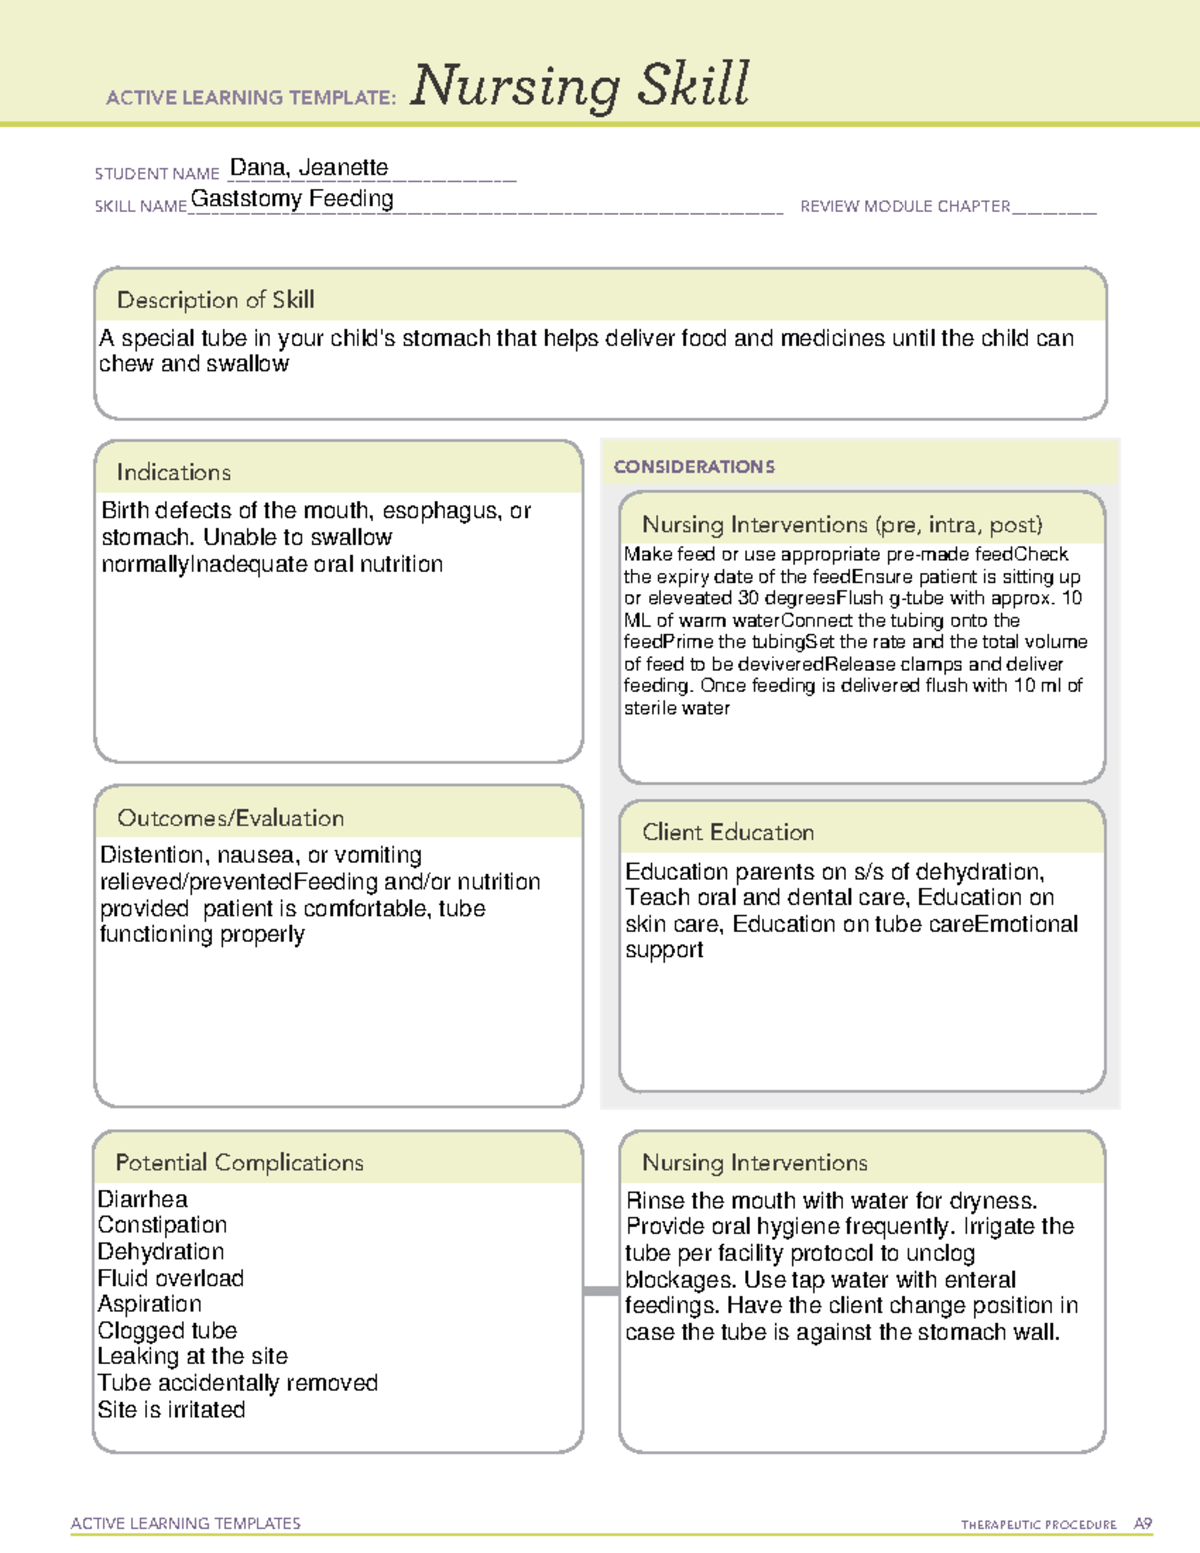
When the Standard Approach Fails
Let me be clear about what G Tube Nursing Assessment cannot do. It cannot reliably confirm intragastric placement when the tube is newly placed and no imaging has been done. pH testing of aspirate is helpful but not definitive, especially in patients on acid suppression therapy. A pH above 5.5 doesn't mean the tube is in the lung, but it does mean you need to pause and get confirmation before starting anything through that tube. External length measurements can drift. Skin edema, weight changes, and tissue remodeling at the stoma site all affect how much of the tube is visible externally. If you're using external markings to verify position, you need a baseline measurement from the initial placement and periodic comparison. Relying on a single measurement without a reference point is how tubes migrate unnoticed. Buried bumper syndrome is rare but devastating when missed. It occurs when the internal bolster erodes into the gastric wall, usually from chronic tension or over-tightening. The tube may still pass feeds through for a while because the lumen remains patent. But the patient develops pain, recurrent infections, and eventually the tube becomes irretrievable endoscopically. I've seen three cases. All three had been assessed repeatedly without anyone lifting the device to inspect the peristomal tissue deeply enough. If a patient with a long-standing G-tube complains of new epigastric pain or the tube won't advance or rotate easily, buried bumper is on your differential regardless of what the superficial assessment shows.
If you're managing G Tube Nursing Assessment on a busy unit, prioritize the trend data and the hands-on inspection over the checkbox routine. The patients who fall through the cracks are the ones who look fine on paper but have a problem you'd notice if you actually looked at them.



