What This Tool Actually Does
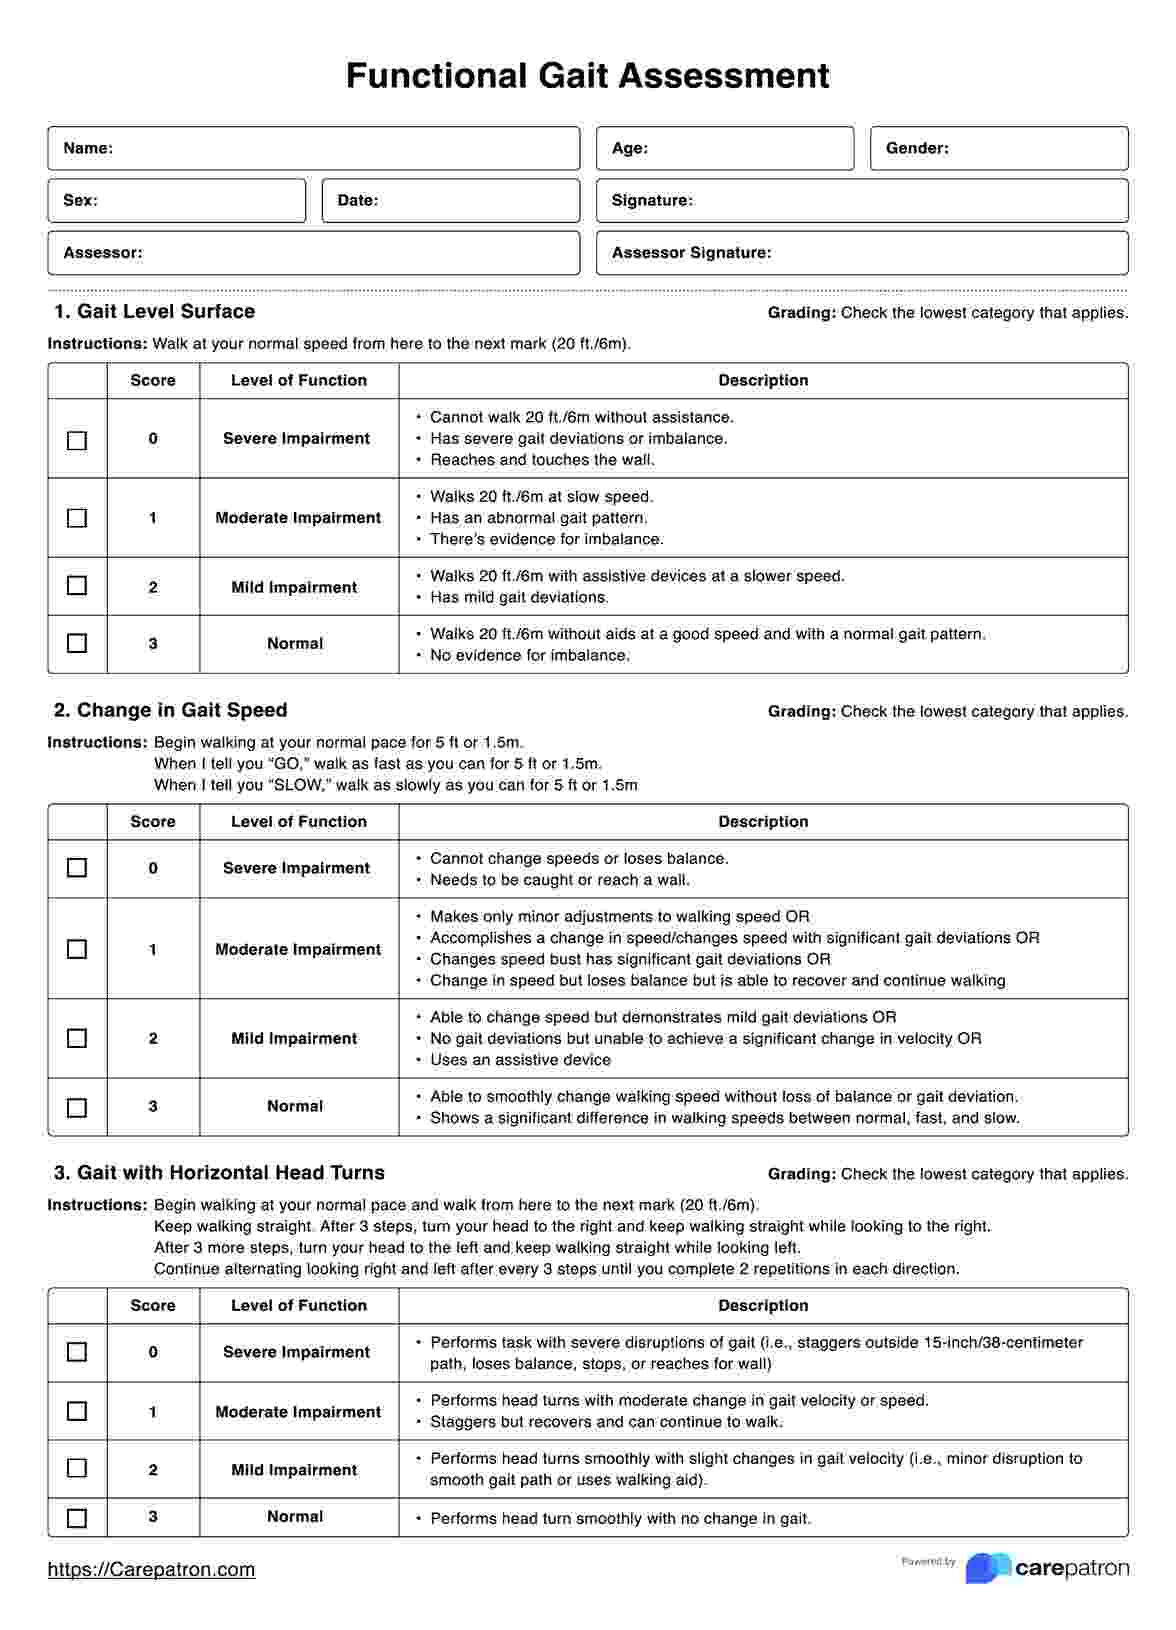
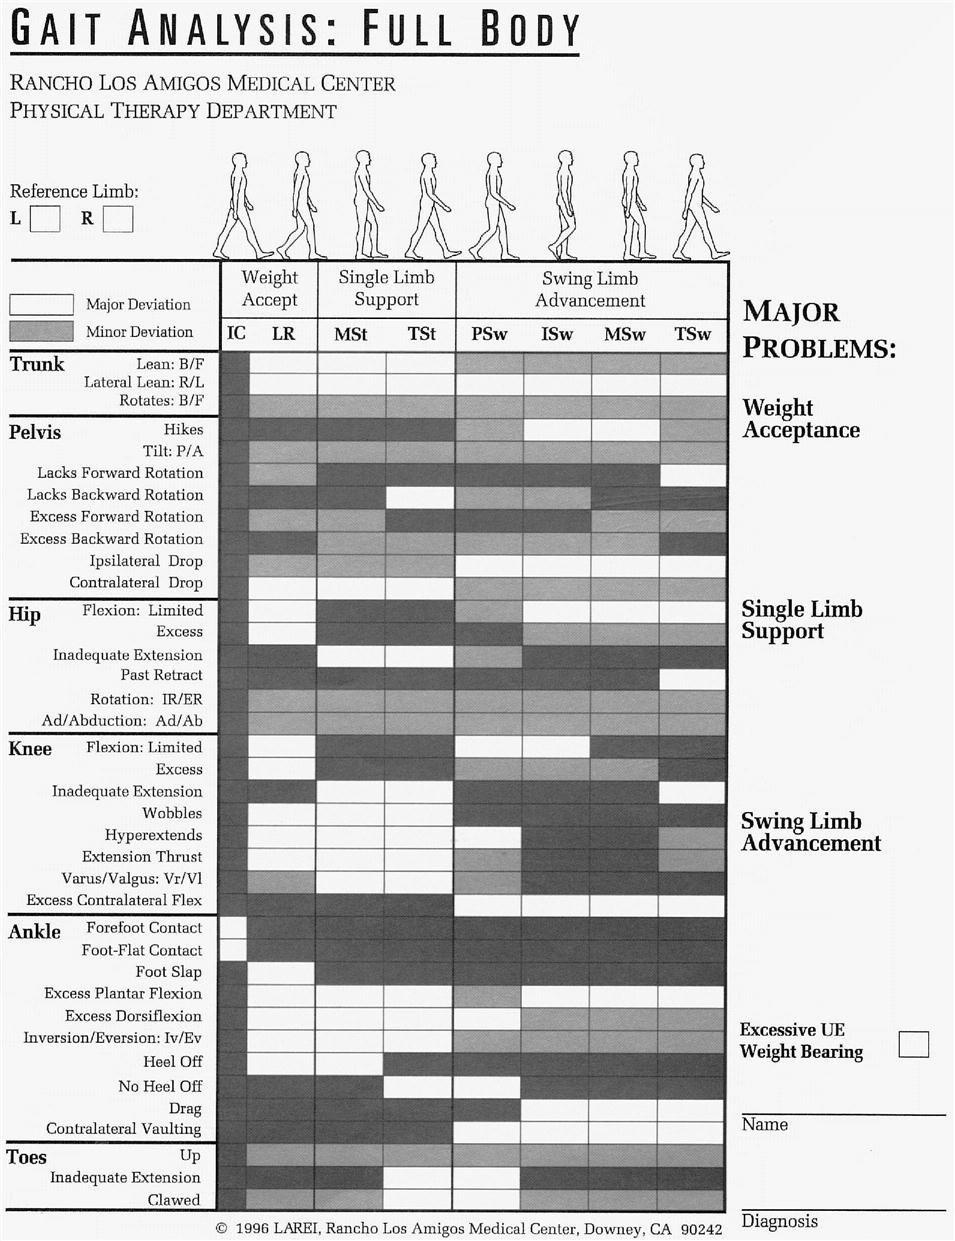
A Gait Assessment And Intervention Tool is a software or hardware system used to capture, analyze, and modify how a person walks. The assessment side records stride length, cadence, ground reaction forces, joint angles, and temporal-spatial parameters. The intervention side takes those measurements and generates a treatment plan or real-time feedback. Most commercial systems combine both, which is why the term gets lumped together even though the two halves can function independently. I spent roughly four years working with these systems across outpatient orthopedic and neurology clinics. The core technology hasn't changed dramatically since then. It relies on instrumented treadmills, pressure mats, 3D motion capture cameras, or more recently, markerless video-based systems paired with force plate data. The output is a report that identifies asymmetries and deviations, then suggests corrections ranging from orthotics and gait retraining to surgical referral.
Gait Assessment And Intervention Tool: How to Use One Properly
Setting one up sounds straightforward because the marketing materials make it sound straightforward. In practice, the calibration and data-capture phase is where most people lose quality and waste time. Here is the process I use now, after watching teams spend thirty minutes on setup and produce unusable datasets half the time. First, verify that the patient's shoe weight matches the reference protocol. If you're using force plates, barefoot trials should default to zeroed plates. If you're doing instrumented treadmill work, shod trials require the treadmill's running surface compliance curve to match the shoe sole hardness. Mismatch here throws off ground reaction force readings by enough to flip a diagnosis. I once had a patient flagged as exhibiting a dramatic increase in impact transient loading, only to discover later that the lab had switched from a gel-insert shoe to a minimalist model between sessions without recalibrating the force plates. The apparent worsening was an artifact. Correcting it meant logging the footwear type as a fixed variable and adjusting the calibration matrix, which took about twelve minutes. Second, establish a consistent walking speed protocol. Gait parameters change non-linearly with speed. A subject walking at 1.2 m/s will show different knee kinematics than at 1.6 m/s, and the difference isn't just magnitude, it's pattern. Force the patient to walk at their preferred speed once for baseline, then record three trials at controlled speeds if you need comparative data. Most tools let you set target speeds using auditory cues or visual pacer bars on a screen. Do not skip this step. Comparing slow-speed assessments to fast-speed baselines is one of the most common errors I see in clinical readouts, and it leads directly to false-positive asymmetry flags.
Third, collect at least five complete stride cycles per condition for temporal data and ten for kinematic data. Anything fewer and the signal-to-noise ratio in the averages becomes unreliable. Most systems will auto-accept three strides and call it a day. That is wrong. Leave the defaults alone. Fourth, export raw data before the software applies its filtering. Every tool applies a low-pass filter somewhere between 6 Hz and 20 Hz by default. The published standards vary, and the software vendor usually picks a middle ground. Export the unfiltered time-series, then apply your own filter in a spreadsheet or scripting environment where you control the cutoff frequency. I recommend a 6 Hz Butterworth filter for kinematic data and 20 Hz for kinetic data per Winter's standards, but your choice should match your research or clinical question. Fifth, when you move to the intervention stage, document the specific parameter you are targeting. Vague referrals like "improve gait symmetry" don't translate into actionable treatment. Specify whether you are targeting stance-phase duration, swing-phase clearance, vertical oscillation, or hip adduction angle during loading response. The tool will give you numbers. Your job is to turn those numbers into a prescription.
Get the Full Details

Common Pitfalls That Nobody Warns You About
Markerless systems are the current trend and they work well in controlled environments. They fail catastrophically in busy clinic settings where lighting shifts, clutter enters the frame, or patients wear visually complex clothing that confuses the pose-estimation algorithms. I had a patient with a unilateral hip replacement who showed near-normal gait patterns on camera but had a documented Trendelenburg sign on physical exam. The markerless system missed the pelvic drop entirely because the patient's coat obscured the greater trochanter landmarks the model was tracking. Switching to reflective markers solved it in under four minutes. Markerless is convenient until it isn't, and when it fails, you won't know it failed unless you cross-check with a physical observation. Another issue that comes up constantly: normalization. Joint angles and moments are often normalized to body mass and height. This makes cross-patient comparison cleaner, but it also smooths over clinically relevant differences in body composition. Two patients with identical BMI but different lean mass distributions will produce nearly identical normalized outputs despite having very different musculoskeletal loads. I stopped relying solely on normalized values a long time ago. I keep both normalized and absolute values side by side in my reports. The absolute numbers catch things the normalized ones hide. Force plate placement matters more than most protocols acknowledge. If the plate is not flush with the walking surface or if there is even a millimeter of gap around the edges, the force vector calculations drift. I once traced a persistent artifact in ground reaction force data to a worn rubber gasket on the plate housing. Replacing the gasket eliminated the noise. The software did not flag any calibration error. The error was purely mechanical and completely invisible to the digital readout.
When This Tool Is the Wrong Choice
Gait assessment and intervention tools are not appropriate for every situation. If you are dealing with a patient who cannot walk safely without assistance and lacks the balance to perform repeated trials on a force plate or treadmill, the data you collect will be noisy at best and dangerous at worst. In those cases, observational gait analysis by a trained clinician or a simpler handheld accelerometer system is more appropriate. The tool adds cost and complexity without adding diagnostic value when the patient cannot reliably produce the movement you are trying to measure. Similarly, if your goal is gross classification rather than detailed biomechanical analysis, a full gait lab assessment is overkill. Instruments like the GAITRite mat or a basic pressure-sensing walkway can give you sufficient temporal-spatial data for screening purposes at a fraction of the cost and setup time. The high-end systems are designed for research-grade precision or for cases where joint-level kinetics are necessary for surgical planning. Using one for routine outpatient follow-ups is throwing money at the problem without a clear return.
Download and Access
Most Gait Assessment And Intervention Tool platforms are proprietary and require institutional licensing rather than individual download. Commercial systems from companies like Vicon, Qualisys, Bertec, and Novel operate on site licenses. Several open-source alternatives exist for researchers who need flexibility. OpenSim is a widely used musculoskeletal modeling platform that can ingest gait data and run inverse dynamics simulations. The Gait2392 and Gait10D1939 model sets are community standards within that ecosystem. R packages like ggplot2 paired with custom scripts can also process raw .c3d and .trc files if you have programming experience. For clinical settings where licensing is a barrier, some hospitals share standardized analysis workflows through institutional collaborators rather than distributing proprietary software directly. If you need a specific tool recommendation, the answer depends entirely on your budget, your patient population, and whether you need research-grade output or clinical screening. The technology is mature enough that the differentiating factor is rarely capability. It is almost always implementation quality and how carefully the operator follows the setup protocol. That is the part that actually determines whether your results are useful or just expensive noise.