Getting past the basics of liver and gallbladder relationships
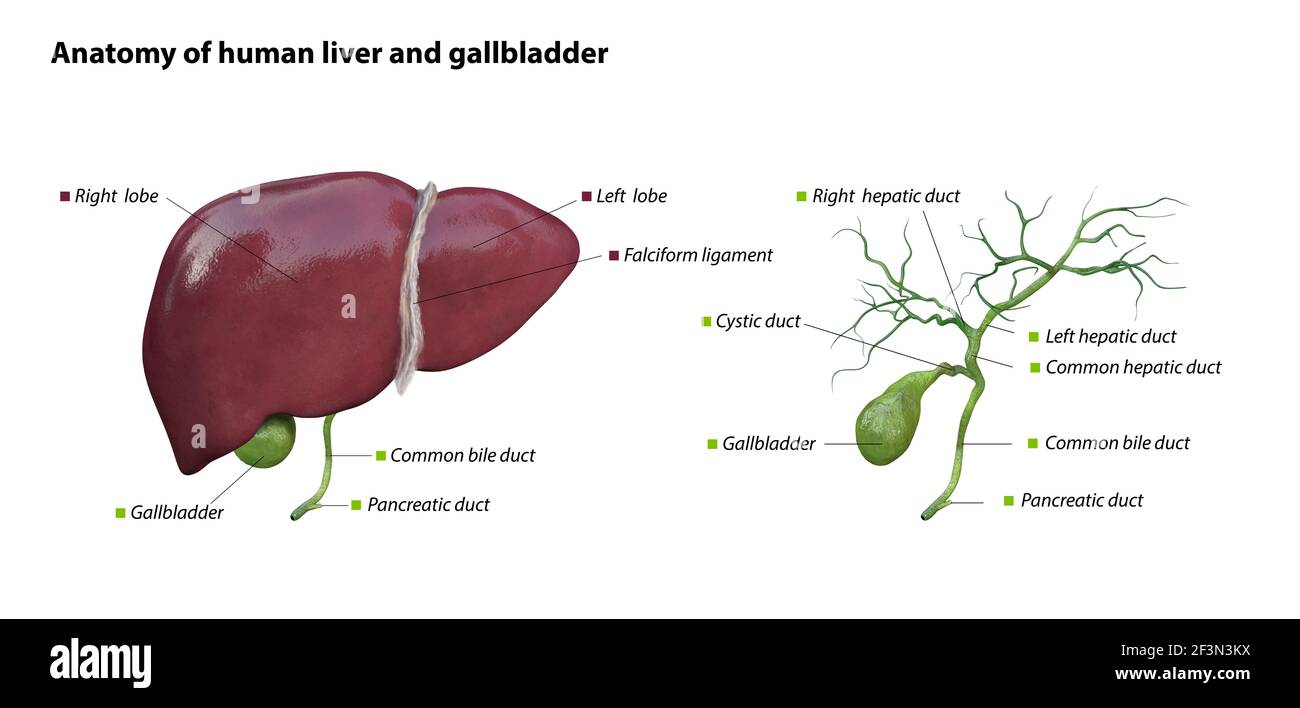
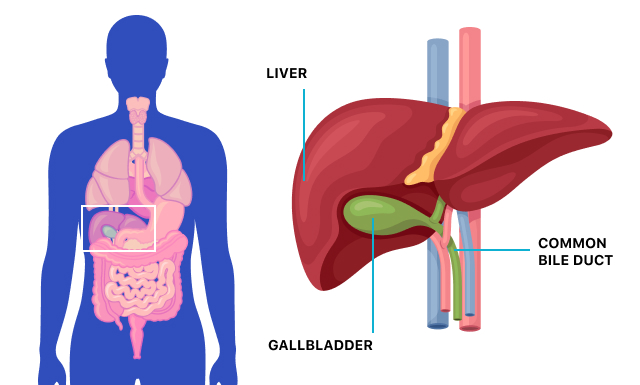
Most people learning this topic start with a textbook diagram and assume they understand it until they actually have to use that knowledge in a clinical setting. The liver sits mostly in the right upper quadrant, anchored by the falciform and round ligaments, and the gallbladder nestles into the gallbladder fossa on the visceral surface. That's the surface-level version. The real complication comes from how these structures actually present when you're dealing with pathology or planning an intervention. I spent weeks trying to memorize the segments of the liver using Couinaud classification, and it felt like rote learning until I encountered a real case that changed how I think about it. A patient came in with right upper quadrant pain and suspected cholecystitis. On ultrasound, the gallbladder looked normal-ish but there was this weird hypoechoic area near the porta hepatis that didn't quite fit the typical picture. Turns out the patient had a Type III cystic duct insertion - where the cystic duct joins the right hepatic duct rather than the common hepatic duct. If you're operating blind on that anatomy, you risk injuring the right hepatic artery or bile duct. That one case taught me more about biliary variants than months of studying standard diagrams ever did. The liver gets its blood supply from two sources, and this dual system is where people usually get tripped up. The hepatic artery proper delivers oxygenated blood at about twenty-five percent of total liver flow, while the portal vein brings nutrient-rich venous blood at roughly seventy-five percent. During hepatectomy or liver transplantation, surgeons need to control both inflow and outflow. The hepatic veins drain into the inferior vena cava, and there are usually three main ones - right, middle, and left. The right hepatic vein is typically the shortest and closest to the IVC, which matters when you're trying to preserve it during surgery.
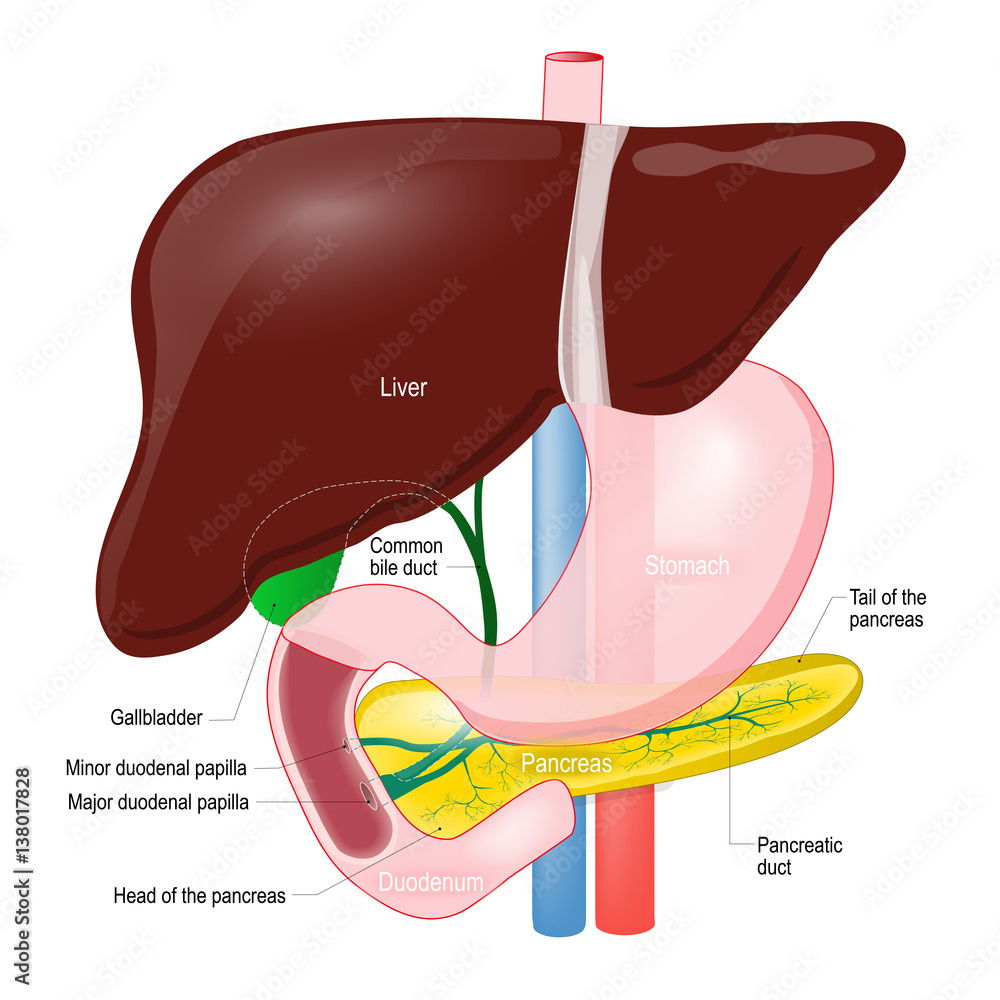
The gallbladder receives its blood supply primarily from the cystic artery, which branches from the right hepatic artery in about seventy percent of people. But that percentage drops significantly if you account for anatomical variation. I've seen cases where the cystic artery arose from the left hepatic artery, the gastroduodenal artery, or even directly from the superior mesenteric artery. During laparoscopic cholecystectomy, this is the exact moment where things can go wrong fast. The critical view of safety requires identifying only two structures entering the gallbladder - the cystic duct and the cystic artery. If you see three or more, you stop and reassess. Every surgical textbook mentions this, but the reality is that intraoperative cholangiography doesn't always catch variant anatomy either. Bile duct anatomy follows a predictable enough pattern from the hepatic ducts down to the common bile duct, which courses through the free edge of the lesser omentum before joining the pancreatic duct at the ampulla of Vater. The sphincter of Oddi controls the flow into the duodenum. Here's the part that's not always emphasized: the common bile duct has segments named after their anatomical relationships. The supraduodenal portion runs in the hepatoduodenal ligament, the retroduodenal segment passes behind the first part of the duodenum, the pancreatic portion travels through or behind the head of the pancreas, and the intraduodenal segment pierces the wall. Each segment has different surgical implications, and knowing which segment is involved helps you plan the approach for things like choledocholithiasis or biliary strictures. Lymphatic drainage is another area where practical knowledge matters. The cystic lymph node, also called the node of Lund, sits near the cystic duct and can be a site of metastasis in gallbladder cancer. More importantly, it's a landmark for identifying the cystic artery during dissection. I remember being on call during a difficult lap chole where the anatomy was obscured by inflammation and adhesions from chronic cholecystitis. The surgeon had to convert to open because the view was completely lost, and we nearly took out the common bile duct thinking it was the cystic duct. After that case, I made it a habit to always confirm the triangle of Calot before clamping anything.
The liver's functional segmentation is based on the distribution of portal triads and hepatic veins, not just surface landmarks. The Cantlie line divides the liver into left and right functional lobes, running from the gallbladder fossa anteriorly to the inferior vena cava posteriorly. This is clinically relevant because tumors or disease in one sector can often be resected while preserving the other, since each half has its own vascular and biliary supply. Sectoral anatomy within those lobes follows the same principles, and understanding it is essential for partial hepatectomies. Most imaging modalities can map this out - CT with contrast, MRI, or even transarterial portography during angiography. One thing that consistently trips up students and even some practitioners is the relationship between the liver and the diaphragm. The bare area of the liver contacts the diaphragm directly, without peritoneal covering. This matters because it's a pathway for spread of infection or malignancy between the liver and the thoracic cavity. Subphrenic abscesses can track up through this space, and liver tumors can invade the diaphragm or even the pleura. I once saw a patient with a hepatic abscess that presented with shoulder tip pain - referred pain from diaphragmatic irritation via the phrenic nerve. The abscess itself wasn't causing respiratory symptoms, but the patient couldn't take a deep breath without wincing. The portal venous system deserves more attention than it typically gets in basic courses. The portal vein forms from the union of the superior mesenteric and splenic veins, usually behind the neck of the pancreas. It then enters the porta hepatis and divides into right and left branches. The right portal vein is shorter and larger in caliber, which is why right-sided portal hypertension or thrombosis tends to have more dramatic effects. Portal hypertension changes the entire hemodynamic picture, creating portosystemic anastomoses at the esophagus, rectum, and umbilicus. Caput medusae, esophageal varices, and rectal varices are the clinical manifestations, but the underlying mechanism is increased resistance through the liver sinusoids.
Get the Full Details

Kupffer cells line the sinusoids and are part of the reticuloendothelial system. They filter bacteria and debris from the portal blood before it reaches the general circulation. In liver disease, especially alcoholic hepatitis or cirrhosis, these cells become activated and contribute to the inflammatory cascade that drives fibrosis. This is why liver function tests alone don't tell the whole story - you need to understand what's happening at the cellular level to interpret them correctly. Elevated AST and ALT indicate hepatocyte injury, but the ratio between them can point toward different etiologies. An AST to ALT ratio greater than two suggests alcoholic liver disease, while a ratio less than one is more typical of viral hepatitis or non-alcoholic fatty liver disease. When it comes to imaging the gallbladder and biliary tree, ultrasound is the first line because it's fast, cheap, and effective for detecting gallstones. But ultrasound has limitations, particularly with obesity or bowel gas interference. MRCP provides detailed visualization of the biliary tree without the risks of ERCP, which remains the gold standard for both diagnosis and therapeutic intervention. ERCP carries a five to ten percent risk of complications including pancreatitis, bleeding, and perforation. So it's reserved for cases where intervention is anticipated or when MRCP findings are equivocal. I've found that drawing out the anatomy repeatedly while saying the structures out loud helps more than passive reading. There's something about the physical act of sketching the porta hepatis and labeling the hepatic artery, portal vein, and common bile duct that makes the relationships stick. It doesn't replace understanding the clinical relevance, but it builds a mental map that you can reference quickly under pressure. When you're in the operating room or reviewing a complex CT scan at two in the morning, you need that map to be accessible without hunting through notes.