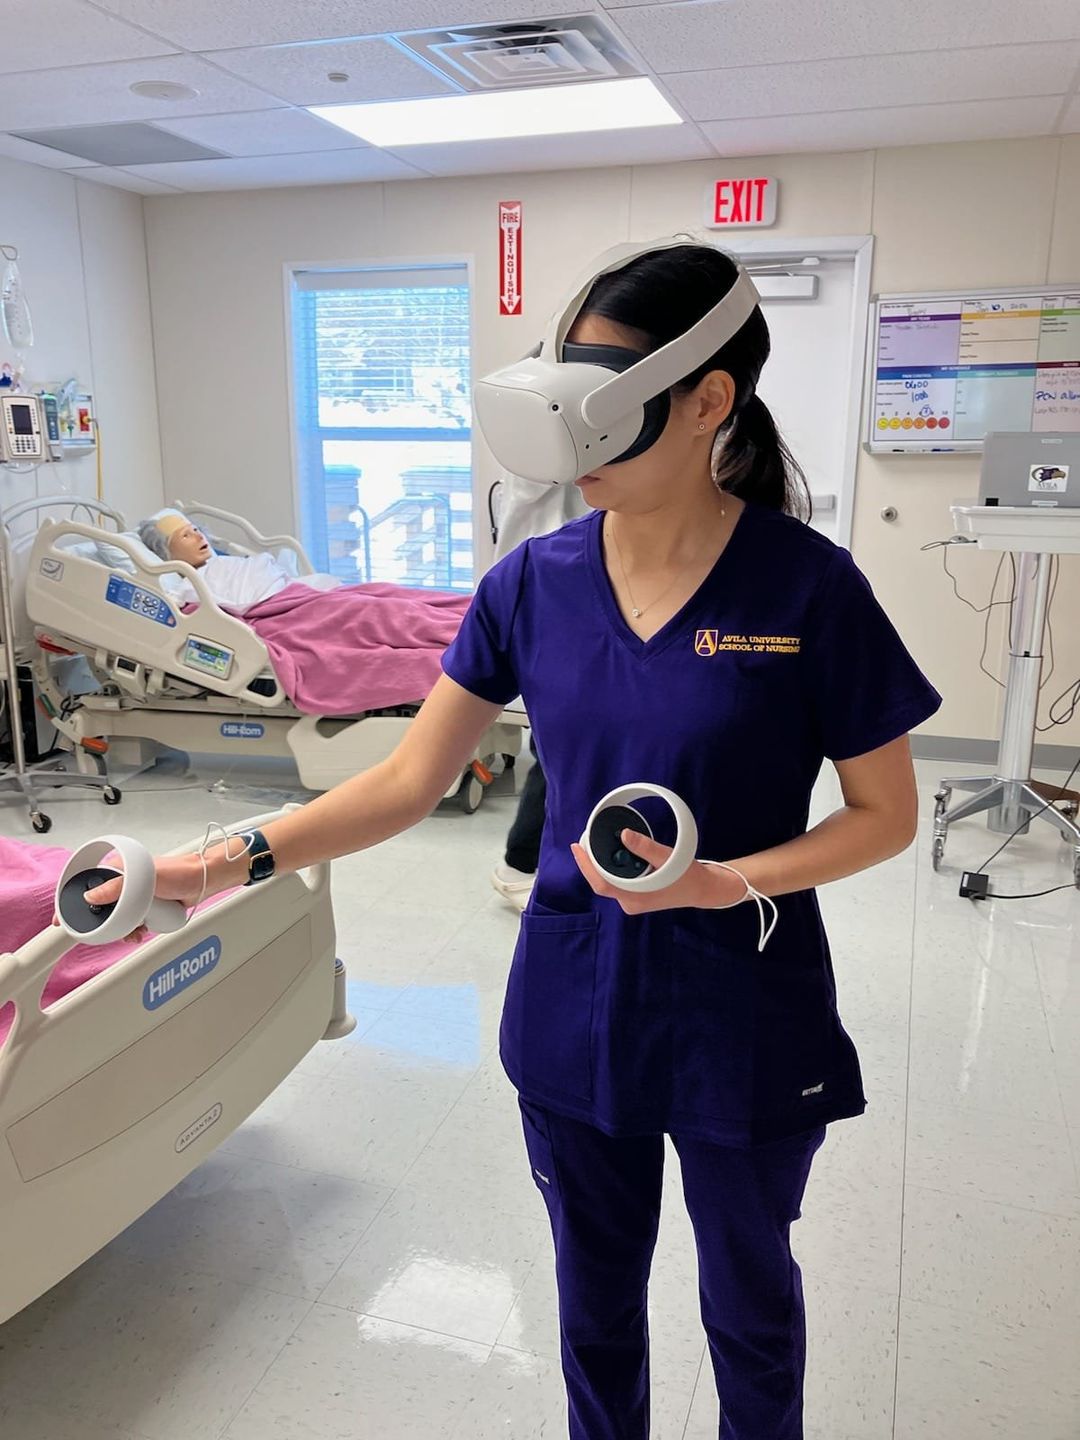
Working Through Clinical Simulations in Modern Nursing Education
I've spent the last few years integrating digital patient scenarios into our associate degree program, and the learning curve is steeper than most vendors admit. The tools marketed as turnkey solutions usually require about three weeks of custom configuration before they're usable in a real classroom. The installation process assumes you already have an active LTI integration with your institution's LMS. If your school still runs Blackboard 9 or an unsupported Moodle version, you'll hit compatibility walls immediately. I had to fall back to standalone mode with manually tracked student scores for a full semester before we could get the integration working with Canvas. Start by provisioning student accounts through your SSO system rather than creating them manually. The platform accepts LDAP imports, but the documentation glosses over the field mapping requirements. Your usernames need to match exactly between systems or the grade sync fails silently.
Scenario selection matters more than quantity. I learned this after assigning twelve acute care cases in week one and watching pass rates drop below sixty percent because the students had never practiced assessment sequencing. We cut the library down to five core cases and ran each one three times across the term. Retention improved noticeably after that change.
The Assessment Mechanics
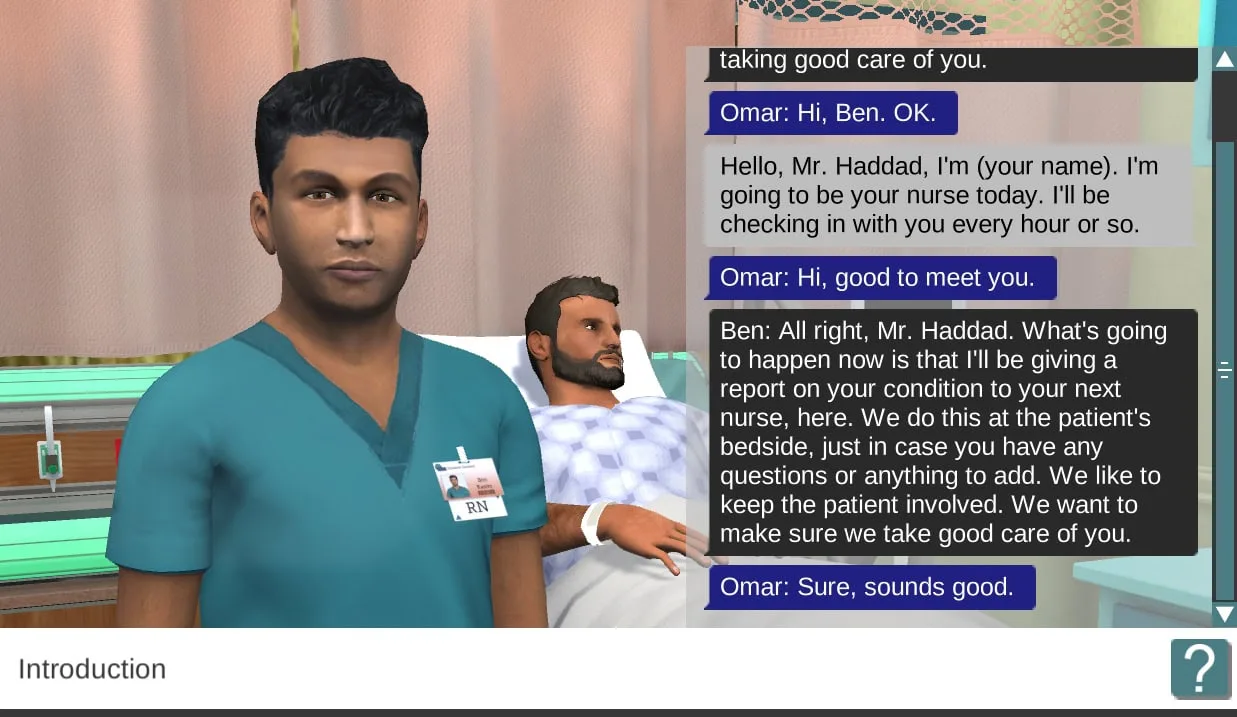
The clinical judgment rubric maps directly to the NCSBN Clinical Judgment Measurement Model, which covers five distinct steps. Students enter patient data, analyze findings, prioritize hypotheses, generate actions, and evaluate outcomes. The engine grades each step independently rather than giving a single score at the end. Here's where most programs miss the point. The platform tracks time spent on each decision node, and that metric gets folded into the final grade. A student who rushes through assessment data collection to get to interventions quickly will actually score lower than someone who methodically reviews lab values and vital sign trends. I had to adjust our grading weights to prevent students from gaming the system by clicking through scenarios as fast as possible. The feedback mechanisms vary depending on the case type. Medical-surgical scenarios provide detailed rationales when students select wrong medications, but mental health cases offer much thinner guidance. I encountered a specific edge case last spring where a psychiatric evaluation scenario wouldn't register proper therapeutic communication responses unless the student used exact keyword phrases from the teaching module. We spent two days manually reviewing the response tree and updating our answer keys to account for natural language variations students actually use.
Get the Full Details
Integration Strategies That Actually Work
Rather than using these simulations as standalone assignments, I embed them into case study sequences that mirror actual clinical rotations. Students complete a pre-simulation reading assignment, run the scenario, then discuss their clinical reasoning in small groups. The debrief conversations typically reveal gaps in critical thinking that the software alone doesn't catch. Scoring thresholds should align with your program's progression model. We set baseline requirements at seventy percent for foundational cases and eighty-five percent for complex multi-system scenarios. Students who fall below those thresholds enter mandatory remediation modules before advancing. The attrition rate dropped from eighteen percent to eleven percent after we implemented that structure. Faculty training is where most programs shortchange themselves. I've seen instructors assigned to run these platforms with zero preparation time, which guarantees poor student outcomes. Our department requires three hours of orientation covering scenario configuration, rubric adjustment, and gradebook synchronization before educators can run independent sessions. That investment pays off within the first month.
Known Limitations and Workarounds
The simulation engine struggles with non-linear patient presentations. Cases where symptoms develop asynchronously or where comorbidities interact unpredictably tend to produce scoring inconsistencies. I've personally adjusted scoring weights for diabetes patients presenting with concurrent respiratory infections, since the default algorithm penalizes students who prioritize airway management over glycemic control. Mobile accessibility remains incomplete. The platform works on tablets but performance degrades significantly on devices smaller than ten inches. Students attempting scenarios on phones experience laggy interface responses that skew timing metrics. We restricted usage to laptops and institutional tablets until the mobile optimization catches up. Report generation has blind spots. The standard analytics dashboard shows aggregate performance across scenarios but doesn't break down individual clinical judgment step failures unless you purchase the premium analytics add-on. For a program managing four hundred students across multiple sections, that limitation makes it difficult to identify specific reasoning gaps affecting the cohort.
Custom scenario creation requires proprietary scripting knowledge. The vendor provides basic case templates, but building complex multi-pathway scenarios demands either hiring technical support or learning their development environment, which operates on a legacy architecture that slows iteration cycles considerably.
Alternative Approaches Worth Considering
Not every program needs a full simulation platform. For introductory courses, structured case studies with guided discussion questions often achieve comparable learning outcomes at lower cost. The hands-on assessment mechanics matter more in advanced practice courses where students need repeated decision-making practice before clinical rotations. Some institutions combine free Open Educational Resources with live standardized patient programs. We trialed that hybrid model alongside the digital platform for one semester. Student satisfaction scores favored the hybrid approach, though clinical judgment measure scores showed no significant difference between groups. The determining factor became budget allocation and faculty comfort with technology management. If your program lacks dedicated instructional technology support, I recommend starting with a single instructor running a pilot section rather than department-wide deployment. The configuration time and troubleshooting burden scales poorly without institutional backing, and early failures create resistance to future adoption attempts.
-p-1080.jpg "7 Interactive Nursing Games: A Fun Way to Learn Critical Skills")