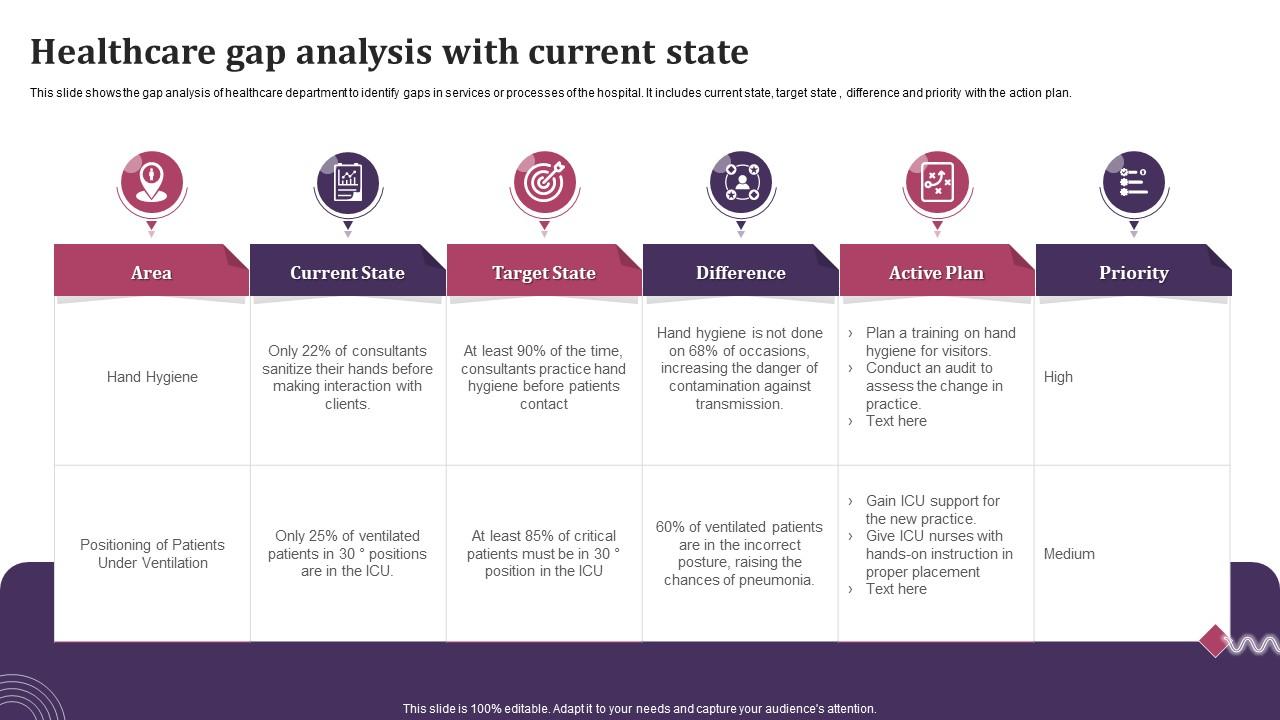
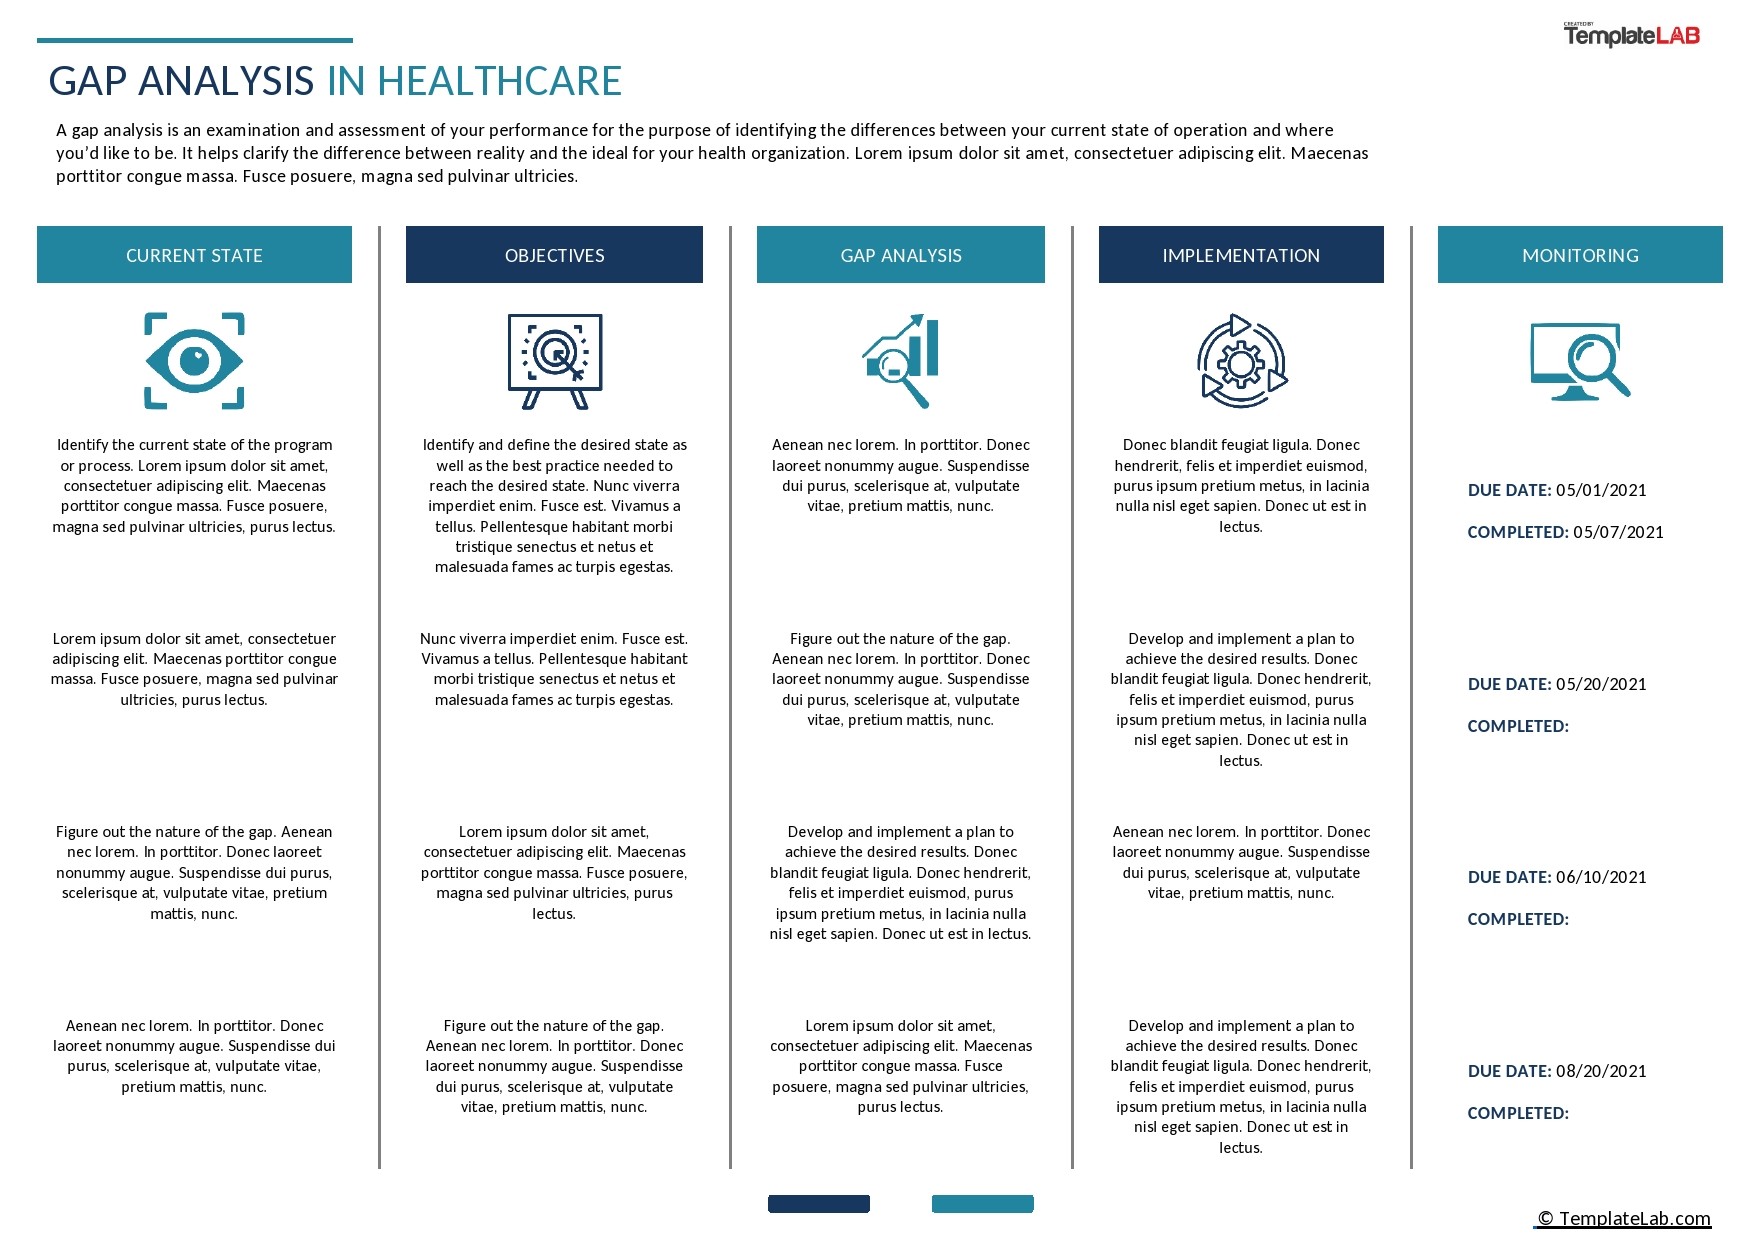
Most people think gap analysis is just a fancy term for checking boxes on a compliance spreadsheet. It's not. It's the process of comparing where your clinical or operational outcomes currently are against where they need to be based on regulations, standards, or benchmarks. In healthcare, that "need to be" usually comes from HIPAA requirements, Joint Commission standards, CMS conditions of participation, or internal quality targets.
I've watched teams waste months building these analyses in Excel because they couldn't find a tool that actually spoke their language. The spreadsheet approach works until it doesn't. Then you have three different versions of the truth circulating across departments and the auditor walks in asking questions nobody can answer consistently.
What You Should Actually Look For in Gap Analysis Tools In Healthcare
Before I break down the specific tools, let me tell you what separates something usable from something that collects digital dust.
The biggest mistake I see is buying a tool that handles general compliance but doesn't understand healthcare-specific frameworks. A tool that can map to ISO 27001 is useless to you if it can't also cross-reference those controls against NIST 800-66 or HITECH requirements. These frameworks overlap in messy ways that generic GRC platforms fumble.
Another thing nobody tells you: the tool needs to handle evidence collection natively. Your gap analysis is only as good as the documentation backing it up. If you're still exporting screenshots to a shared drive and naming them "FINAL_v3_ACTUAL.pdf," you're doing it wrong. The best tools let you attach policies, procedure documents, audit logs, and incident reports directly to each control or requirement line item.
Here's a practical example. I was working with a mid-sized health system that needed to assess their readiness for an upcoming survey. They had roughly 400 control objectives across HIPAA, state licensing, and internal policy. Their existing process involved four people spending about two weeks pulling evidence from five different systems. We switched them to a dedicated healthcare gap analysis tool and brought that down to about three days. The tool pulled active directory export data, connected to their vulnerability scanner API, and had a template for each requirement category. The time savings came from not rebuilding the same evidence request workflow every single assessment cycle.
Core Features That Separate Good Tools From Bad Ones
Control-to-regulation mapping is the foundation. When you select a standard like OCR's HIPAA Security Rule, the tool should auto-populate the relevant controls and sub-controls with their full text. You shouldn't be manually typing out "Access Control - §164.312(a)(1)" into a cell. Any competent tool handles this natively.
Risk scoring matters more than people realize. Not all gaps are equal. A missing encryption requirement on a system that processes nothing but appointment scheduling isn't the same severity as the same gap on a system handling ePHI for inpatient medication records. The tool should let you assign risk values based on impact and likelihood, then aggregate those into an overall risk posture score for each department or facility.
Version tracking is non-negotiable. Regulations change. Your organization changes. I've seen gap analyses that were six months stale because nobody realized the tool hadn't been updated when the org moved to a new EHR platform. The tool should maintain a full history of every change, who made it, and when, so you can reconstruct your compliance posture at any point in time.
Reporting needs to serve two audiences simultaneously. Your compliance officer needs a detailed evidence matrix for auditors. Your C-suite needs a one-page dashboard showing risk trends and priority gaps. If the tool only generates one format, you'll end up spending more time reformatting reports than you saved by using the tool in the first place.
Specific Tools Worth Considering
Arbix is a notable option in this space. It was built specifically for healthcare compliance workflows and handles the framework mappings that generalist tools miss. The control library includes OCR, NIST, HITRUST, and Joint Commission references. It took our team about two weeks to get fully migrated from spreadsheets, and the ROI hit within the first quarter because we stopped repeating the same evidence-gathering work.
Drata has gained traction recently, particularly for organizations that already use it for SOC 2 compliance. The healthcare module covers HIPAA and HITECH mappings. The onboarding is faster than Arbix if you're already within their ecosystem. The tradeoff is that some of the deeper healthcare-specific controls require manual configuration that takes longer to set up properly.
Vanta operates similarly. It's leaner on the healthcare-specific side out of the box but compensates with automation depth. If your environment uses standard cloud infrastructure, Vanta's continuous monitoring can cut down the manual review time significantly. The gap analysis itself is less granular than dedicated tools but good enough for smaller organizations that don't have complex hybrid environments.
For organizations that need something customizable rather than boxed, Microsoft Power Platform with a custom compliance model can work. I've seen this done well and done poorly. The well-done version required a dedicated administrator who understood both the tool and healthcare compliance. The poorly done version looked like a fancy spreadsheet with a lot of overhead and very little actual capability. The decision really comes down to whether you have the internal resources to maintain a custom build.
How to Actually Implement This Without Losing Your Mind
Start with scope definition before you touch any tool. I can't stress this enough. Determine which regulations apply to your organization, which departments and facilities are in scope, and what time period the analysis will cover. A community hospital doing annual HIPAA risk analysis has a completely different scope than a multi-state health system preparing for Joint Commission renewal. Trying to run both scopes through the same tool configuration will produce garbage results.
Map your current state first. Before configuring controls or running assessments, inventory what you actually have. This means listing every information system that touches ePHI, every policy that exists, every procedure that's documented, and every control that's currently active. I learned this the hard way. Early in my career, I configured a tool's control library assuming a certain policy existed. Six months later, an auditor asked for evidence and we discovered the policy had never been formally adopted. It existed only in a senior manager's head. Configuring the tool after a real inventory saved us from building an analysis on a foundation of assumptions.
Run a pilot with one framework before rolling out to all of them. Pick the most applicable standard and work through a complete assessment cycle. Document every friction point. This gives you a realistic sense of how long full implementation will take and what training your team actually needs. A team that completes a full pilot can typically execute subsequent assessments in half the time it took the first one.
Train the people who will actually use the tool daily, not just the compliance manager. In my experience, the tool fails when only one person knows how it works. That person goes on vacation or leaves the organization and suddenly everyone is back to spreadsheets. Spread the knowledge. Have at least two people per department who can navigate the tool and pull evidence.
Maintenance is where most implementations quietly fail. Gap analysis isn't a quarterly event anymore with modern tools. It should be continuous. Set up automated evidence collection where possible. Schedule periodic reviews of your control mappings to make sure they still match your current environment. When the organization acquires a new clinic or deploys a new system, the tool should reflect that change within days, not months.
Common Pitfalls to Avoid
Assuming the tool replaces your professional judgment. These tools map controls to requirements and flag gaps. They don't interpret whether a gap is actually material to your organization's risk posture. I've seen analysts accept every red flag from a tool without question and then waste time remediating low-risk items while ignoring a genuinely dangerous one that the tool scored as acceptable due to a configuration issue.
Over-configuring the tool in the first month. It's tempting to spend weeks setting up every possible framework, mapping every control, and building custom workflows. This usually backfires. You end up with a bloated tool that's hard to navigate and nobody uses because it's too slow. Start minimal. Add complexity only when you hit a real limitation.
Underestimating the evidence burden. A tool might say it has 500 controls to assess. Each control needs supporting evidence. That evidence has to be current, attributable, and verifiable. If each evidence item takes ten minutes to collect and validate, you're looking at roughly eighty-three hours of work minimum. Plan for that. Budget accordingly. Don't promise leadership that the tool will cut your assessment time by eighty percent without understanding where the actual time goes.
Choosing a tool based on price alone. The cheapest option that meets the bare minimum usually becomes the most expensive option over time because it can't scale with your organization. A tool that works for fifty controls will fracture at two hundred. The incremental cost of a better tool is almost always less than the cost of switching tools after you've already invested months of configuration and data entry.
What Doesn't Work
Spreadsheets aren't a tool choice, they're an anti-pattern at scale. They work fine for small practices with ten or twenty controls. Once you cross roughly thirty control objectives, the maintenance burden grows faster than your ability to keep the spreadsheet accurate. Version conflicts, broken formulas, and inconsistent evidence formatting become the norm rather than the exception.
DIY solutions built on top of project management tools like Asana or Monday.com are tempting because you already have access. They also don't hold up. The lack of native compliance frameworks, weak audit trails, and poor evidence linking make them adequate for tracking tasks but inadequate for producing defensible gap analyses.
Free or open-source options in this specific domain are rare and usually underpowered. General GRC open-source tools exist but they lack healthcare-specific framework content. Importing your own control libraries is possible but requires ongoing maintenance when regulations update. The total cost of ownership often exceeds a commercial tool once you factor in the engineering time.
Measuring Whether Your Tool Actually Works
Track the time from assessment kickoff to final report. A well-configured tool should get your first full assessment done in roughly one to two weeks for a mid-sized organization. Subsequent assessments should take days, not weeks. If you're still spending more than three weeks per cycle after three months of tool usage, something is misconfigured or you picked the wrong tool.
Measure evidence coverage rates. After each assessment, check what percentage of your controls have complete, current evidence. A functioning tool with proper workflows should get this to above ninety percent within a few cycles. Staying below seventy percent usually indicates either a tool limitation or a process problem that the tool isn't solving.
Monitor auditor feedback. This is the ultimate metric. If your gap analyses are consistently accepted without major findings on control-related questions, the tool is doing its job. If every audit cycle produces the same findings about missing or incomplete documentation, revisit your tool configuration or evidence collection workflow.
The landscape shifts frequently. New frameworks emerge, existing ones get updated, and tools add or remove capabilities. What worked two years ago may not be the right choice today. The principles stay the same though. Define your scope accurately, pick a tool that understands healthcare compliance natively, invest in proper implementation, and maintain it continuously rather than treating it as a point-in-time project.
Gallery Gap Analysis Tools In Healthcare
Gap Analysis In Tracking Healthcare Comprehensive Approach To Strategic Pla
How To Successfully Perform A Gap Analysis In Healthcare
How To Perform A Gap Analysis In Healthcare Example Of A Gap Analysis On The Surgical Unit ...
What Is Gap Analysis In Nursing at Jane Whitsett blog
Gap Analysis Template For Healthcare - Alberguepankotsi