Working with the GARS in Clinical Settings
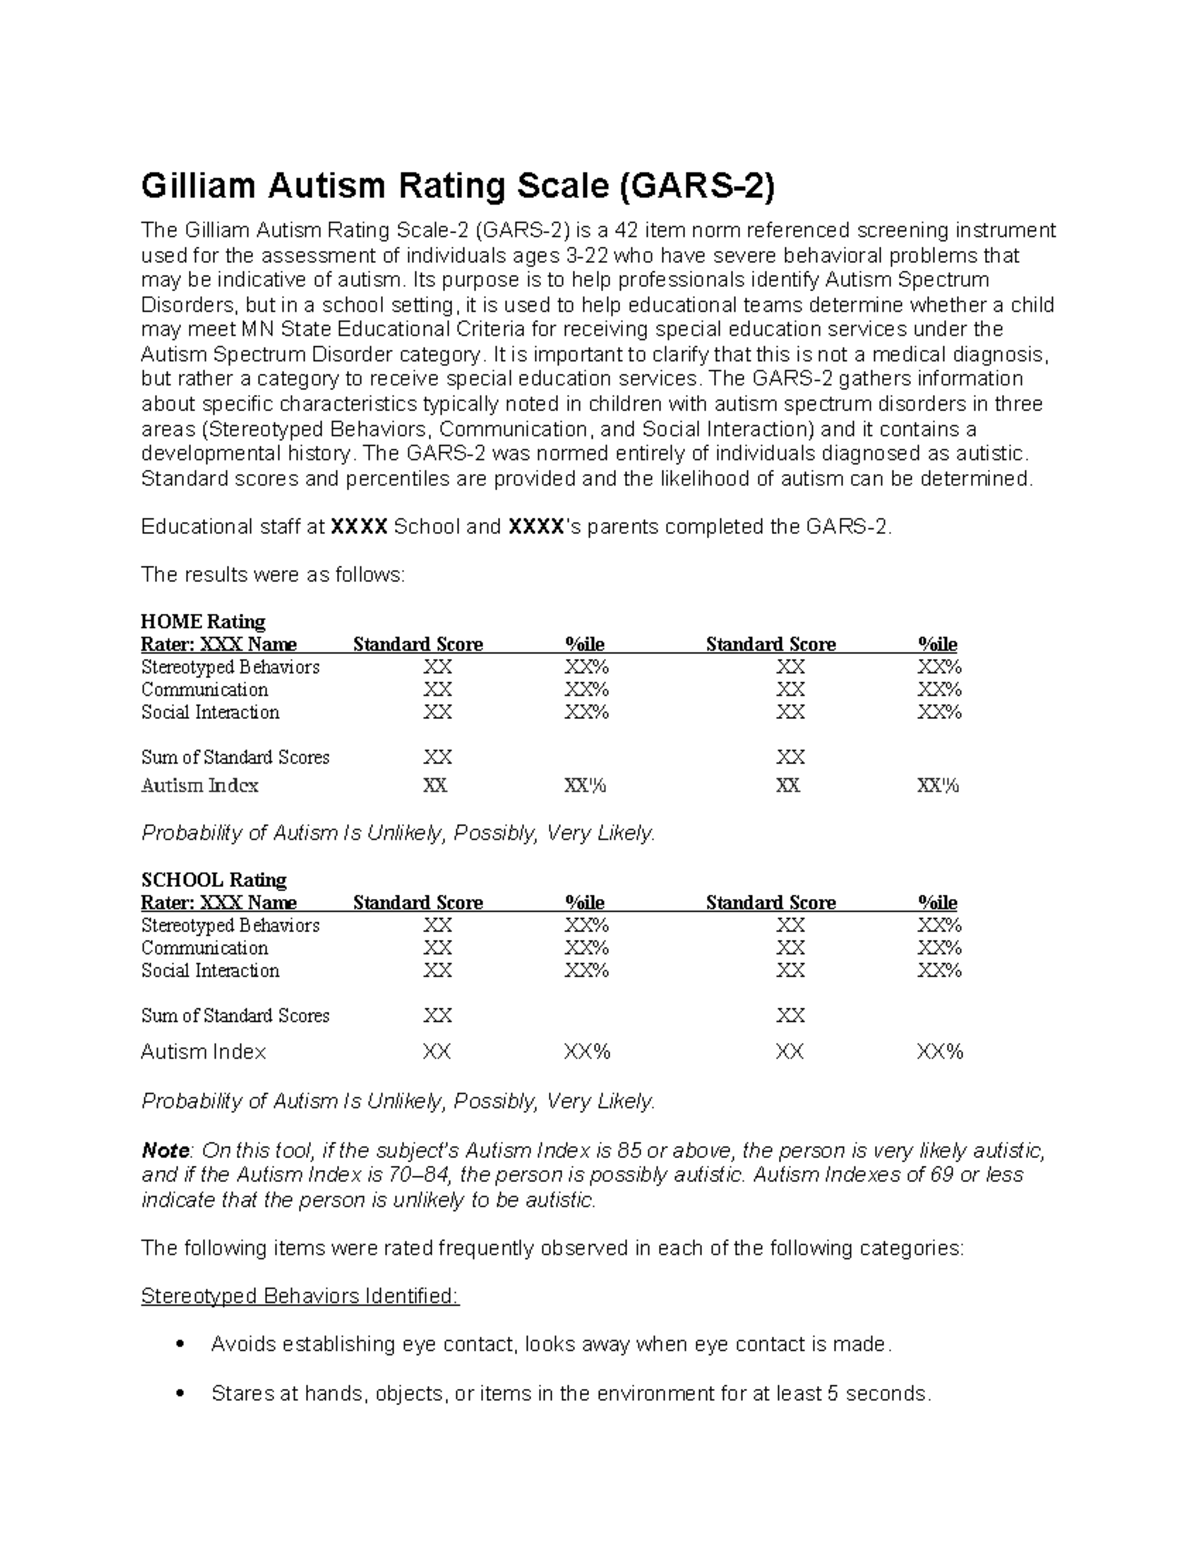
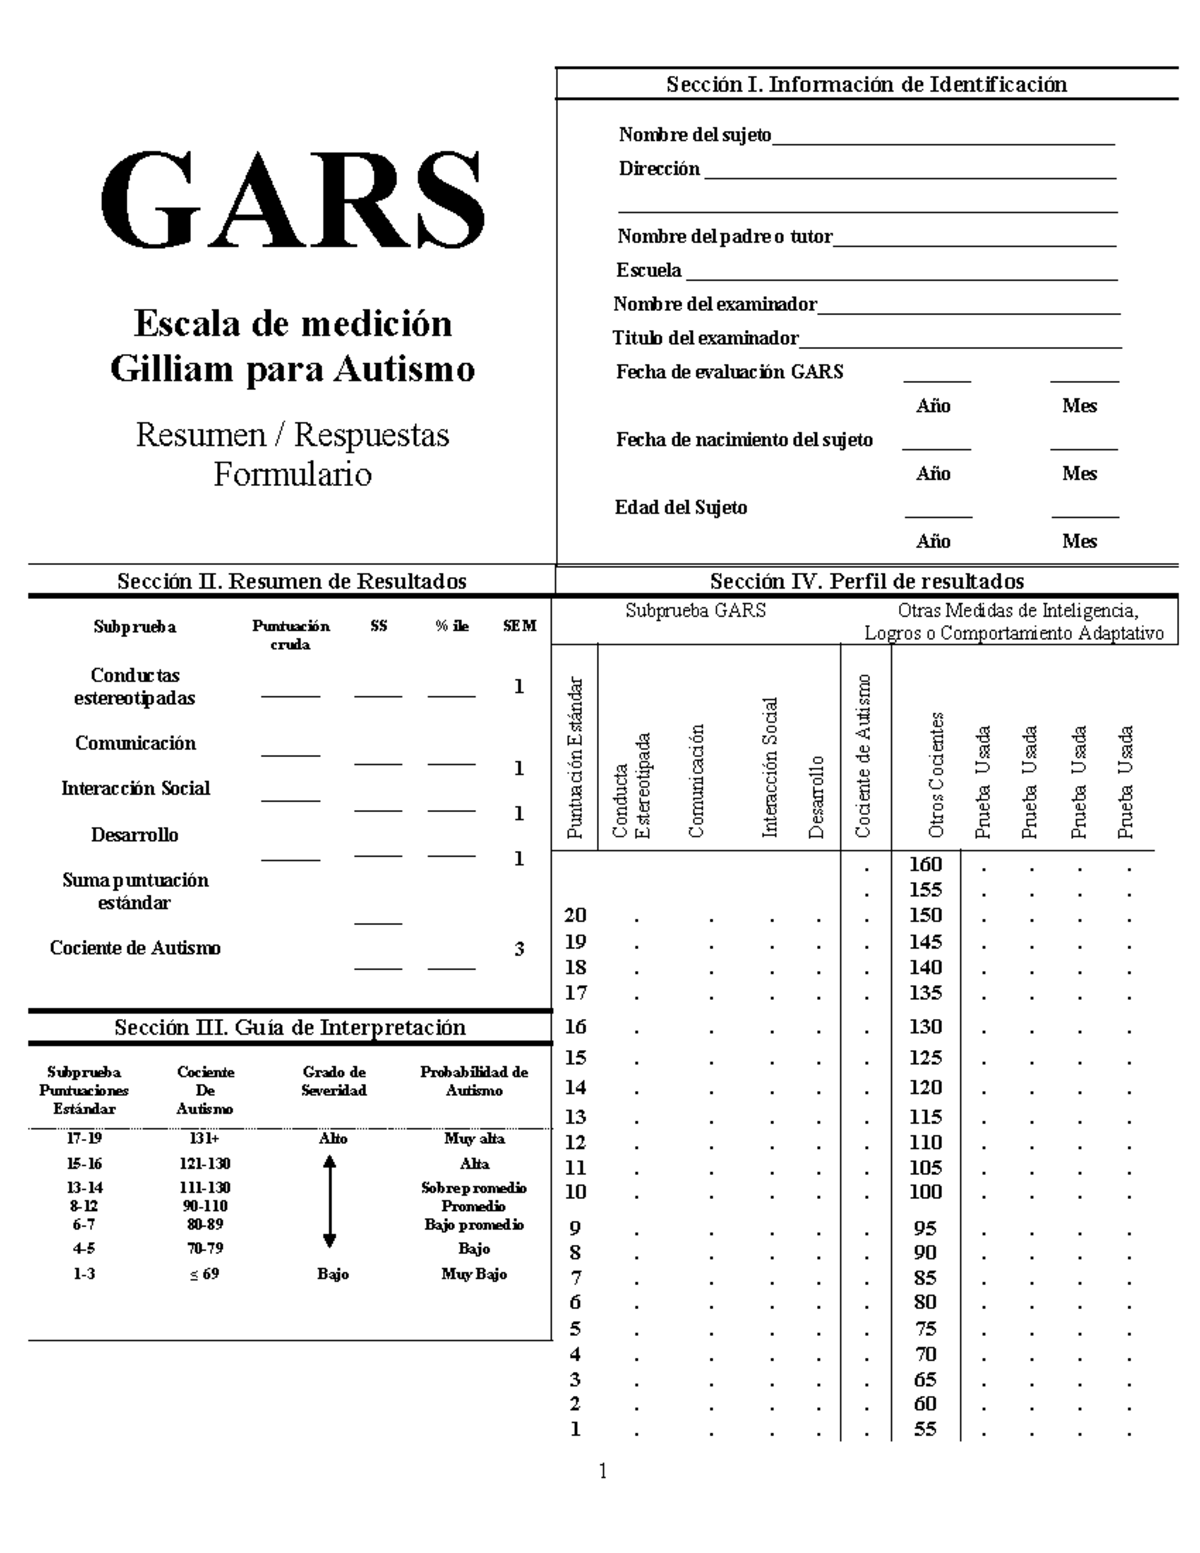
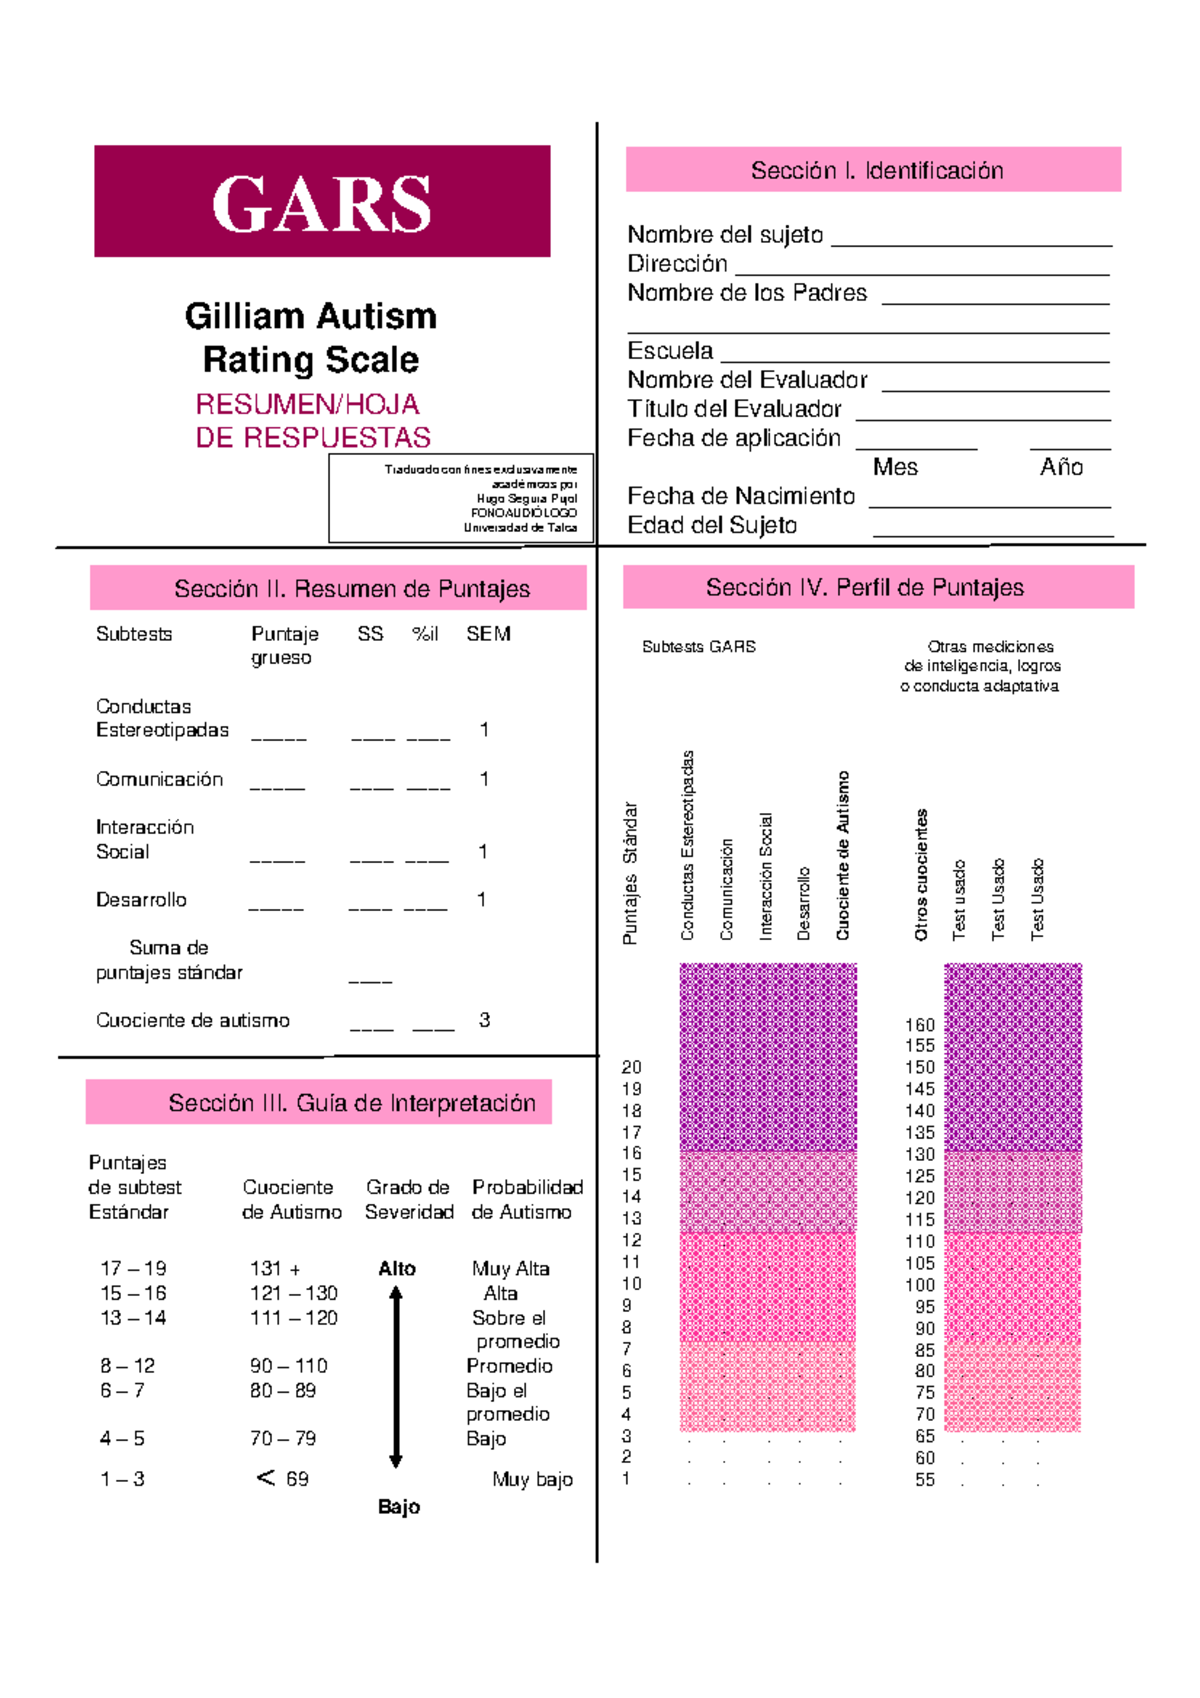
I've spent years administering rating scales for autism spectrum assessments, and the GARS remains one of the most commonly referenced tools in the field. Whether you're looking at the Gars Gilliam Autism Rating Scale Aemuy or the standard GARS-3, the process shares core elements that most practitioners learn through repeated use rather than any single manual. The scale itself is designed to be completed by someone who knows the individual well — a parent, teacher, or caregiver. You're rating the frequency of specific behaviors across domains like stereotypy, communication, social interaction, and adaptation. The scoring process produces an Autism Score, an Autism Spectrum Index, and a severity classification ranging from mild to extreme. What the manual doesn't always make clear is how much weight a single rater's perspective carries. I once worked with a child whose parents scored everything in the severe range at home, but the classroom teacher submitted ratings that placed the same child in the mild category. The discrepancy wasn't about bad data — it was about context. The child's meltdowns were concentrated in unstructured transitions, which the teacher simply didn't observe during structured academic periods. This is the kind of edge case where the scale starts to show its limits, and where clinical judgment matters more than any computed score.
The workaround I settled on was straightforward: always collect at least two independent raters from different environments, then review the profiles item by item rather than comparing aggregate scores. The item-level analysis revealed that the child's social interaction deficits were consistent across settings, but the stereotypic behaviors were environment-dependent. That distinction changed the intervention plan entirely.
Scoring and Interpretation
Manual scoring takes roughly 10 to 15 minutes once you're familiar with the form. Digital versions through the official publisher reduce that to about five minutes, but they require an active license. The raw scores convert to age-standardized T-scores using built-in tables. An index score above 100 suggests the individual exhibits a higher-than-average number of autism-relevant behaviors relative to the normative sample. One thing beginners routinely miss is that the GARS was normed on a sample collected before DSM-5 was published. The behavioral descriptions don't perfectly align with current diagnostic criteria, particularly around social communication and restricted interests. A score that reads as "autistic" on the GARS doesn't automatically confirm an autism diagnosis under current standards. It's a screening and descriptive tool, not a diagnostic instrument. That distinction matters when you're presenting results to a multidisciplinary team. Another counter-intuitive point: high variability within a single profile — where some subtests score in the extreme range while others are average — often points to environmental factors or co-occurring conditions rather than a pure autism presentation. I've seen this pattern consistently with individuals who have significant anxiety or ADHD alongside ASD. The scale flags autism-relevant behaviors, but it can't differentiate which disorder is driving which behavior cluster.
Get the Full Details
Limits and When to Look Elsewhere
The GARS has real weaknesses. It tends to over-identify autism in nonverbal children with intellectual disability because several items conflate communication delays with social-communication deficits. It also has limited utility for adults, since the normative data skews heavily toward school-age populations. For adolescents and adults, the ADOS-2 or a structured clinical interview paired with developmental history tends to produce more reliable results. If you need the official instrument, it's distributed exclusively through the publisher's website. There's no legitimate free version, and any site offering a or cracked PDF is distributing stolen material. The GARS-3 typically runs between $150 and $200 for the complete kit, which includes the questionnaire, scoring book, and access to the online scoring platform. Individual test forms can sometimes be purchased separately, but you still need the manual for proper interpretation. The scale itself is a useful piece of the assessment puzzle. It gives you a common language for describing behavioral patterns across settings. But the score alone never tells the full story, and treating it like one is the most common mistake I see in early-career practitioners. The real work happens in the space between the numbers and the actual person you're trying to understand.