Getting Gemcitabine Bladder Instillation Right Without Losing Your Mind
I've been doing this long enough to know that patient education for gemcitabine bladder instillation is where most protocols fall apart. The actual procedure isn't that complicated. Getting patients to actually follow it correctly is the hard part. Here's the straightforward version. Gemcitabine is administered intravesically — that means directly into the bladder through a catheter. It's primarily used for non-muscle invasive bladder cancer, usually after a TURBT procedure. The idea is to expose the bladder lining to the drug for a set period, then have the patient void it out.
Gemcitabine Bladder Instillation Patient Education
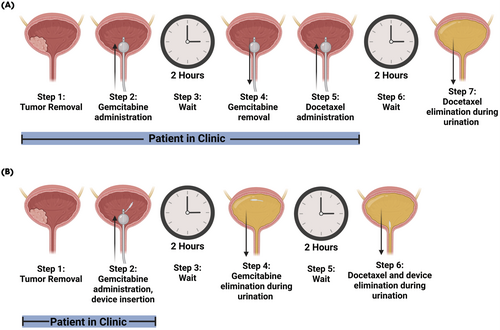
The standard regimen I see in practice involves instilling the drug and having the patient hold it for roughly an hour. They'll be given specific positioning instructions — typically rotating between supine, prone, and lateral positions every fifteen minutes or so. This isn't some kind of wellness yoga routine. The reason exists. The goal is to ensure the solution contacts all areas of the bladder mucosa, including areas where tumor cells might be hiding. Most patients struggle with the positioning part. You'd be surprised how many people just lie still the entire time because it feels weird to roll around with a bladder full of fluid. I made them do it anyway. One patient, a seventy-two-year-old retired teacher, literally refused to turn onto her left side. She told me it felt like she was going to pee herself. I explained that she literally cannot pee while the catheter is in place, and that if she doesn't rotate, the treatment is less effective. She rolled over. We finished the rotation. She was fine. Let me be clear about something that nobody puts in the pamphlets: gemcitabine intravesical therapy isn't well-absorbed systemically, which is why it's safer than some alternatives. But that doesn't mean it's harmless. Local side effects are common. Hematuria, dysuria, frequency, and bladder spasms will happen. Usually mild. Sometimes not. I had a patient who developed significant chemical cystitis after the second instillation — basically her bladder lining got irritated enough that she couldn't keep the drug in for the full retention period. We shortened the dwell time to forty-five minutes for the next cycle, and she tolerated it better. That's not in the standard guidelines. It's just what I learned to do.
Pre-procedure education needs to cover hydration. Patients should be well-hydrated before coming in, but they shouldn't empty their bladder right before the instillation either. There's a narrow window here. Come in with a moderately full bladder and the catheter placement is harder. Come in completely empty and you're draining the drug almost immediately after it goes in. I usually tell patients to drink about two glasses of water an hour before their appointment and not void after that until the procedure is done. The instillation itself goes through a Foley catheter or a straight catheter. The drug is mixed according to pharmacy protocol — typically gemcitabine 1000 mg per liter of saline, though some centers use different concentrations. I've seen ranges from 600 mg to 2000 mg per instillation depending on the institution. The exact dose depends on your urologist's preference and the patient's body surface area in some protocols. Post-instillation, the patient drains the bladder into the toilet. Here's where education matters most. They should avoid close contact with pregnant women and young children for about forty-eight hours after the procedure. The drug is excreted in urine during that window. This isn't a theoretical concern — I had a nurse who didn't follow this instruction and exposed her toddler to gemcitabine-contaminated urine. The kid was fine, but it was a stupid risk that could have been avoided with proper counseling.
Get the Full Details

Patient compliance with the full course matters. The typical schedule is weekly instillations for six to eight weeks, then maintenance cycles. Some patients drop out after two or three sessions because of side effects or inconvenience. I've seen programs where dropout rates hit thirty percent simply because patients weren't given clear expectations about what would happen. Telling someone upfront that they'll likely experience burning with urination for a day or two after each treatment changes the whole conversation. They're not surprised when it happens, and they're more likely to stick with it. There's a practical issue with the retention period that people don't talk about enough. The one-hour dwell time assumes the patient can comfortably hold the fluid. For patients with reduced bladder capacity from prior surgery or radiation, this is genuinely difficult. I've had to work with those patients to use a shorter retention period — thirty to forty-five minutes — rather than lose them entirely from the protocol. Shorter exposure is better than no exposure. Monitoring during the treatment period should include repeat cystoscopies at intervals recommended by the treating urologist. Most programs do a mid-treatment cystoscopy after about three or four instillations to assess response. If there's persistent visible disease, the approach may need to change. I've seen cases where patients continued weekly gemcitabine despite clear tumor recurrence on intermediate cystoscopies. That's not good practice. The treatment should be re-evaluated if there's no response.
One thing I wish more people understood: gemcitabine intravesical therapy has fallen behind mitomycin C in some circles because of convenience factors. Mitomycin is typically a single immediate post-TURBT instillation. Gemcitabine requires multiple visits over weeks. But gemcitabine has shown better efficacy in some studies for superficial bladder cancer, particularly in terms of recurrence reduction. The tradeoff is real. More visits for potentially better outcomes. Patients need to understand this explicitly when you're presenting the option. If you're putting together educational materials for patients, keep it simple. Written materials should be at a sixth-grade reading level or below. Most of these patients are older and not dealing with medical jargon well. Include a concrete timeline — "you'll come in once a week for eight weeks" is clearer than "weekly instillations." Give them a symptom diary to track side effects. And absolutely include the pregnancy and child exposure warning in large print. The biggest gap I see in patient education programs is the lack of clear guidance on what to do when side effects become problematic. Patients need a direct phone number to call if they experience severe pain, fever, or heavy bleeding after an instillation. Not a general clinic line that routes them through four menus. A direct number. I've watched too many patients suffer unnecessarily because they didn't know who to call or were too embarrassed to bother anyone.
Practical note about the positioning rotations: most patients find the prone position (lying on their stomach) the most uncomfortable. Suggest they use a pillow under their abdomen for support. It's a small thing but it makes a noticeable difference in whether they'll actually comply with the rotation schedule. For patients with indwelling catheters already in place, the instillation is technically simpler but introduces a different set of issues. Catheter-related discomfort, risk of infection, and the mechanical challenge of instilling through an existing catheter without contaminating the system. I prefer using a fresh catheter insertion for each treatment when possible, but that's not always practical for patients who already have chronic indwelling catheters for other reasons. The evidence base for gemcitabine intravesical therapy continues to grow. Recent studies suggest it may be particularly effective as a maintenance therapy after induction cycles, though the optimal duration and schedule aren't fully established yet. Until those answers come in, most programs stick to the established weekly-then-monthly framework.
Bottom line: the procedure itself is straightforward. The patient education component determines whether it works in practice. Clear instructions, realistic expectations, accessible support when things go wrong, and flexibility for patients who can't tolerate the textbook protocol. That's what separates programs that get good compliance and outcomes from ones that don't.