Understanding the Current State of Gene Therapy For Hemophilia B
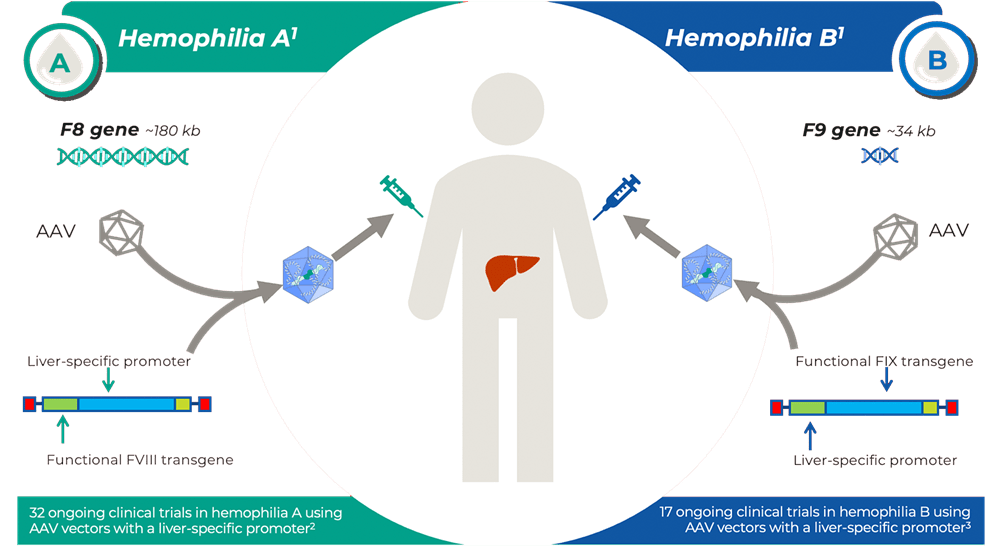
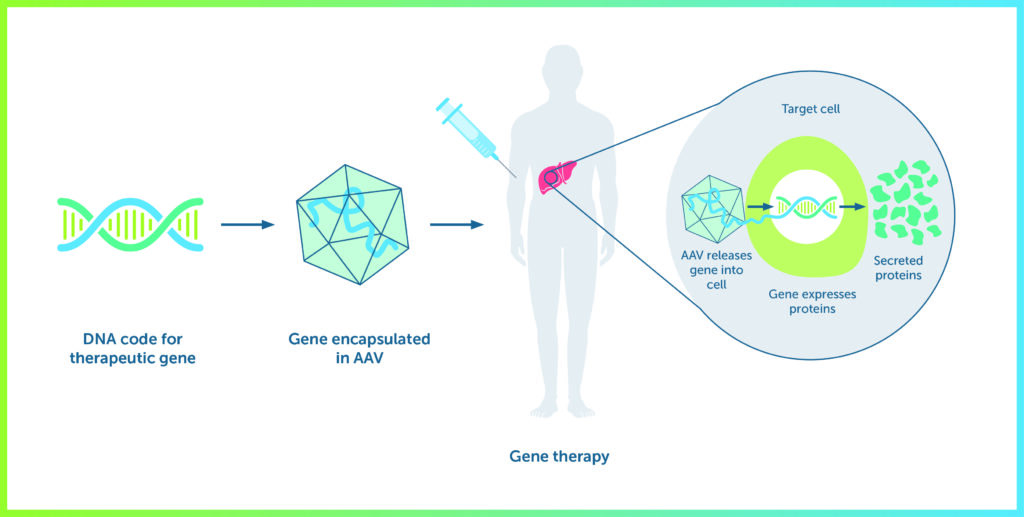
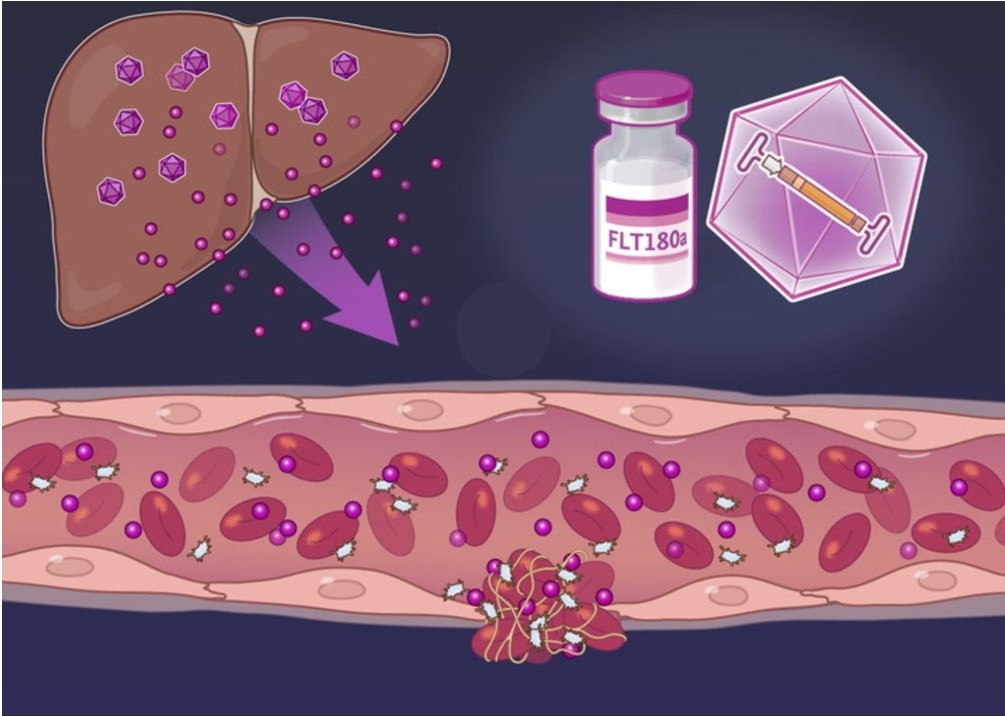
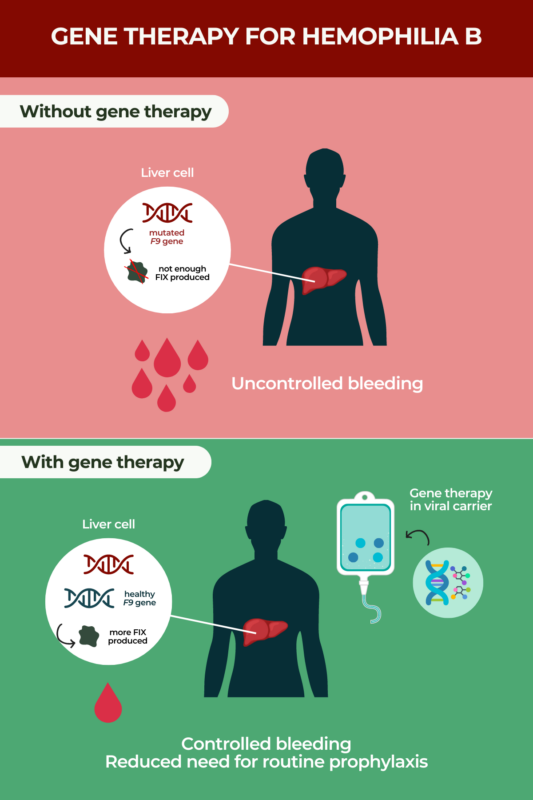
Most people reading about hemophilia B gene therapy are coming at it from the patient side or the investment side. The clinical reality is messier than the press releases suggest. Here is how it actually works in practice. The standard approach uses an adeno-associated virus, specifically AAV5 or AAV-SQ, as a vector to deliver a functional copy of the Factor IX gene into liver cells. The virus doesn't integrate into the host genome the way retroviruses do. It stays episomal, which means it persists long-term without inserting itself randomly. This matters because random insertion is exactly what you want to avoid when dealing with gene delivery. The current approved product is etranacogene dezaparvovec, marketed as Hemgenix. It carries a mutation-resistant Factor IX variant called Padua. The Padua variant produces a Factor IX protein with roughly five times the specific activity of normal human Factor IX. That single improvement is why some patients hit target levels in the mild hemophilia range even with modest transgene expression. You don't need massive expression levels when each molecule does more work.
The infusion itself takes about forty minutes. You are essentially getting a one-time dose of virus particles into your bloodstream, and the liver does the rest. But the "one-time" part is where things get complicated.
What Actually Happens After Infusion
Before anyone gets the therapy, you have to check two things: baseline Factor IX levels and AAV antibody titers. Patients with pre-existing immunity to the AAV serotype being used will neutralize the vector before it reaches hepatocytes. I have seen this blow up infusions multiple times. The workaround is straightforward but not always practical — you switch to a different AAV serotype if the patient has antibodies against the first one, or you run through an immunomodulation protocol involving rituximab and plasmapheresis to temporarily suppress the immune response. That protocol adds roughly six to eight weeks of prep time and significantly increases the risk of adverse events. It is not a casual decision to make lightly. After the infusion, Factor IX activity typically rises over four to twelve weeks as hepatocytes begin producing the protein. Most responders land somewhere between three and thirty percent of normal Factor IX activity. That is the mild hemophilia range. For patients who were previously severe, this represents a dramatic shift. Bleeding episodes drop by roughly eighty percent in the best case scenarios. But you are also looking at monthly Factor IX monitoring for at least a year to track whether levels are holding steady.
Get the Full Details

Counter-Intuitive Realities Nobody Talks About
The biggest misconception is that gene therapy equalizes outcomes. It does not. There is a wide distribution of response even among patients who look identical on paper. I have seen two patients with the same genetic mutation, same baseline Factor IX, same AAV titer status, and completely different trajectories after infusion. One hit twenty-two percent and sustained it. The other barely cleared five percent and then declined over eighteen months. The reason most likely involves differences in hepatic cell divisibility and the rate at which transduced hepatocytes dilute out through cell turnover. Liver regeneration is not something patients typically think about when they are weighing this option, but it is a major variable. Another thing that surprises people: transient elevation of liver enzymes is almost universal in the first few weeks.ALT and AST can spike to two to four times the upper limit of normal. This is generally self-limiting and managed with a short course of corticosteroids started preemptively. The standard protocol I have seen teams use is prednisone at one milligram per kilogram per day for ten days, tapering over another ten days. Skipping the steroid cover entirely is an option in low-immune-response cases, but most clinicians err on the side of covering because the alternative is watching a patient's liver enzymes climb while wondering if they should intervene.
Limitations and When This Approach Fails Completely
Gene Therapy For Hemophilia B has hard failure modes that are worth understanding before anyone considers it a cure. The first is the immune-mediated clearance issue mentioned earlier. If a patient has high-titer neutralizing antibodies against the AAV vector, the therapy simply will not work regardless of what the dosing calculations say. In my experience, roughly ten to fifteen percent of the candidate population falls into this category. They are effectively disqualified from using the current AAV-based products. The second limitation is durability. We now have about five years of follow-up data. Some patients maintain therapeutic Factor IX levels beyond that window. Others see a gradual decline back toward baseline over three to five years. The vector is episomal, and as hepatocytes divide and turn over, the transgene-containing DNA gets diluted. There is no biological mechanism yet that guarantees permanent expression. Patients need to understand they may eventually need to return to standard factor replacement therapy, just at a lower intensity than before treatment. A third hard limit involves dosing constraints. AAV vectors have a packaged DNA capacity of approximately four to five kilobases. The Factor IX gene with its regulatory elements pushes close to that ceiling. This means you cannot easily add more sophisticated regulatory sequences or combine multiple therapeutic genes in a single vector. The dosing is also very high — on the order of 2 × 10^13 vector genomes per kilogram — which is why immune responses and hepatotoxicity are significant concerns at these levels. Lower doses reduce safety risks but also reduce the probability of achieving therapeutic expression. It is a tradeoff that has not been cleanly resolved.
Practical Decision Framework
If you are evaluating this for a real patient, the sequence matters. Get Factor IX activity quantified by one-stage clot assay and chromogenic assay. Run AAV5 and AAV-SQ neutralizing antibody titers. Check liver function. Review the patient's bleeding history over the previous twelve months. Confirm they have hemophilia B confirmed by genetic testing, not just a presumed diagnosis based on family history. Then present the realistic outcome ranges, not the best-case scenarios from the pivotal trial data. The phase III trial showed about sixty to seventy percent of patients achieving therapeutic levels. That means thirty to forty percent did not, for various reasons that are not always predictable beforehand. The cost is approximately three point five million dollars per patient upfront. Insurance negotiations vary by market. Some payers require outcomes-based reimbursement models where partial refunds are triggered if Factor IX levels fall below a specified threshold after a certain period. This is relatively new territory for any payer, and the administrative overhead of these agreements is non-trivial. I have watched this space evolve from experimental to approved over the last decade. The technology works well enough for a meaningful subset of patients, but it is not universal. The patients who benefit most are those with confirmed hemophilia B, low baseline Factor IX, no pre-existing AAV immunity, and stable liver function. Anyone outside that profile should expect a more uncertain trajectory and should be counseled accordingly before proceeding.